

Overview
Whiplash is an acceleration–deceleration mechanism that transfers energy to the neck, most commonly during a motor vehicle collision. The resulting bony or soft-tissue injury may produce a range of clinical manifestations collectively termed whiplash-associated disorders (WAD).
WAD commonly presents with neck pain, stiffness, restricted movement and headache. Some patients also experience shoulder or arm pain, dizziness, paraesthesia, visual disturbance, tinnitus, fatigue, sleep disturbance or cognitive symptoms. Most presentations are WAD grade I or II, without fracture, dislocation or objective neurological deficit.
The cervical facet joints may be one source of persistent pain following whiplash, but whiplash and facet-mediated pain are not synonymous. Symptoms, examination findings and routine imaging cannot independently confirm that a facet joint is the pain generator. In appropriately selected patients with persistent axial neck pain, image-guided cervical medial branch blocks may be used to test whether pain arises from one or more facet joints.
Fracture, dislocation, spinal cord injury, significant nerve-root injury, vascular injury and head injury must be considered early. WAD grade IV—neck symptoms with fracture or dislocation—requires urgent specialist or emergency management.
Definition
- Whiplash
- An acceleration–deceleration mechanism that transfers energy to the neck and may cause bony or soft-tissue injury.
- Whiplash-associated disorder
- The clinical symptoms and signs arising after a whiplash injury.
- Cervical facet joint
- A paired synovial joint between adjacent cervical vertebrae that guides movement and contributes to spinal stability.
- Facet-mediated pain
- Neck pain arising from a cervical facet joint or its associated structures.
- Cervical medial branch block
- An image-guided injection of local anaesthetic around the medial branch nerves supplying a suspected painful facet joint.
- Radiofrequency ablation
- A procedure that uses radiofrequency energy to interrupt pain transmission through selected medial branch nerves.
Anatomy & Physiology
The cervical spine consists of seven vertebrae. Adjacent vertebral bodies are connected by intervertebral discs, while paired facet—or zygapophyseal—joints connect the posterior elements.
Each facet joint is a true synovial joint containing:
- Articular cartilage.
- A joint capsule.
- Synovial lining and fluid.
- Sensory nerve endings capable of transmitting nociceptive signals.
The orientation of the facet joints permits flexion, extension, rotation and lateral flexion while limiting excessive translation. The discs, facet joints, ligaments and cervical muscles work together to maintain movement and stability.
Most cervical facet joints receive sensory innervation from the medial branches of the dorsal rami above and below the joint. The C2–3 joint differs because it is primarily supplied by the third occipital nerve. This innervation explains why diagnostic blocks must target the relevant medial branch nerves rather than the spinal nerve root.
Upper cervical facet joints can refer pain towards the occiput and head. Lower cervical joints more commonly refer pain into the neck, shoulder or scapular region. These patterns overlap and are not sufficiently specific to establish the diagnosis alone.
Facet-mediated pain usually remains axial or referred to the head, shoulder or scapular region. Dermatomal arm pain accompanied by sensory loss, weakness or reflex change should instead raise concern for cervical nerve-root involvement.
Aetiology & Risk Factors
Aetiology
Whiplash most commonly follows a motor vehicle collision, particularly a rear impact. It may also occur after:
- Sporting collisions.
- Falls.
- Cycling accidents.
- Assaults.
- Other sudden acceleration–deceleration trauma.
The symptoms of WAD may arise from injury or sensitisation involving several structures, including:
- Cervical facet joints and joint capsules.
- Intervertebral discs.
- Muscles and tendons.
- Spinal ligaments.
- Nerve roots or the brachial plexus.
- Pain-processing pathways.
A single injured structure frequently cannot be identified, particularly in uncomplicated WAD grades I and II.
Risk Factors
Risk factors associated with persistent pain or disability include:
- High initial neck-pain intensity.
- High initial disability, particularly an elevated Neck Disability Index.
- Restricted cervical range of motion.
- Cold hyperalgesia or widespread sensory hypersensitivity.
- Post-traumatic stress symptoms.
- Poor expectation of recovery.
- Depressive symptoms, catastrophising or fear of movement.
- Pre-existing bodily or neck pain.
- Persistent neurological abnormalities.
Crash characteristics such as impact direction, vehicle position and head-restraint use are not reliable predictors of recovery. Initial pain, disability and psychological responses are generally more clinically useful than the apparent severity of vehicle damage.
Pathophysiology
Whiplash exposes the cervical spine to rapid changes in velocity. During a rear impact, the torso may initially move forwards with the vehicle while the head temporarily lags behind, creating complex extension, shear and compression forces. This is followed by forward movement and flexion of the neck.
Potential consequences include:
- Stretching or compression of the facet-joint capsule, muscles and ligaments.
- Mechanical stimulation of nociceptors within injured tissues.
- Local pain, muscle guarding and reduced cervical movement.
- Referred pain from cervical structures into the head, shoulder or upper back.
- In more severe injuries, nerve-root irritation or structural disruption.
- In some patients, persistent peripheral and central sensitisation, altered motor control and psychological distress that sustain pain after tissue healing.
Facet-joint injury may involve capsular strain, synovial irritation or abnormal loading. Persistent facet-mediated pain is thought to arise from nociceptive input transmitted through the cervical medial branches. However, similar symptoms can arise from discs, muscles and other cervical structures, making clinical localisation difficult.2,3
Clinical Manifestations
Typical Features
Symptoms may begin immediately or develop over several hours after the injury. Common manifestations include:
- Neck pain and stiffness.
- Reduced or painful cervical movement.
- Cervical and upper-trapezius tenderness.
- Occipital or cervicogenic headache.
- Shoulder, interscapular or upper-arm pain.
- Muscle spasm or fatigue.
- Dizziness or disequilibrium.
- Paraesthesia without an objective neurological deficit.
- Sleep disturbance, fatigue or difficulty concentrating.
- Anxiety or distress related to the collision and symptoms.
Features Suggesting Facet-Mediated Pain
Possible clinical features include:
- Predominantly axial neck pain.
- Unilateral or bilateral paraspinal pain.
- Referred pain into the occiput, shoulder or scapular region.
- Local tenderness over the cervical paraspinal or facet region.
- Pain reproduced by extension, rotation or lateral flexion.
- Absence of a clear dermatomal sensory deficit or myotomal weakness.
These findings may increase suspicion but cannot reliably identify a painful facet joint without confirmatory diagnostic procedures
Red Flags
Urgent investigation or specialist assessment is required when there is:
- Midline cervical tenderness after significant trauma.
- A dangerous injury mechanism.
- Progressive limb weakness or objective sensory loss.
- Bilateral neurological symptoms.
- Lower-limb symptoms, gait disturbance or upper motor neurone signs.
- Bladder or bowel dysfunction.
- Severe or progressive headache.
- Altered consciousness or features of significant head injury.
- Dysphagia, dysarthria, diplopia, ataxia or other possible vascular symptoms.
- Constitutional symptoms or concern for infection or malignancy.
- Suspected fracture, dislocation or spinal instability.
Do not label traumatic neck pain as uncomplicated whiplash until fracture, dislocation, spinal cord injury and significant neurological injury have been considered. WAD grade IV is a structural cervical injury requiring urgent management.
Diagnosis
WAD is principally a clinical diagnosis based on the injury mechanism, symptoms and examination findings. Assessment should determine the WAD grade, exclude serious injury and identify factors associated with delayed recovery.
Pain intensity and disability should be documented using a reproducible measure such as a numerical pain scale and the Neck Disability Index. Serial measurements are more useful than isolated findings for monitoring recovery.
Imaging
For alert, stable trauma patients, the Canadian C-Spine Rule should be used to determine whether cervical-spine imaging is required. High-risk features include age 65 years or older, a dangerous mechanism or paraesthesia in the extremities.
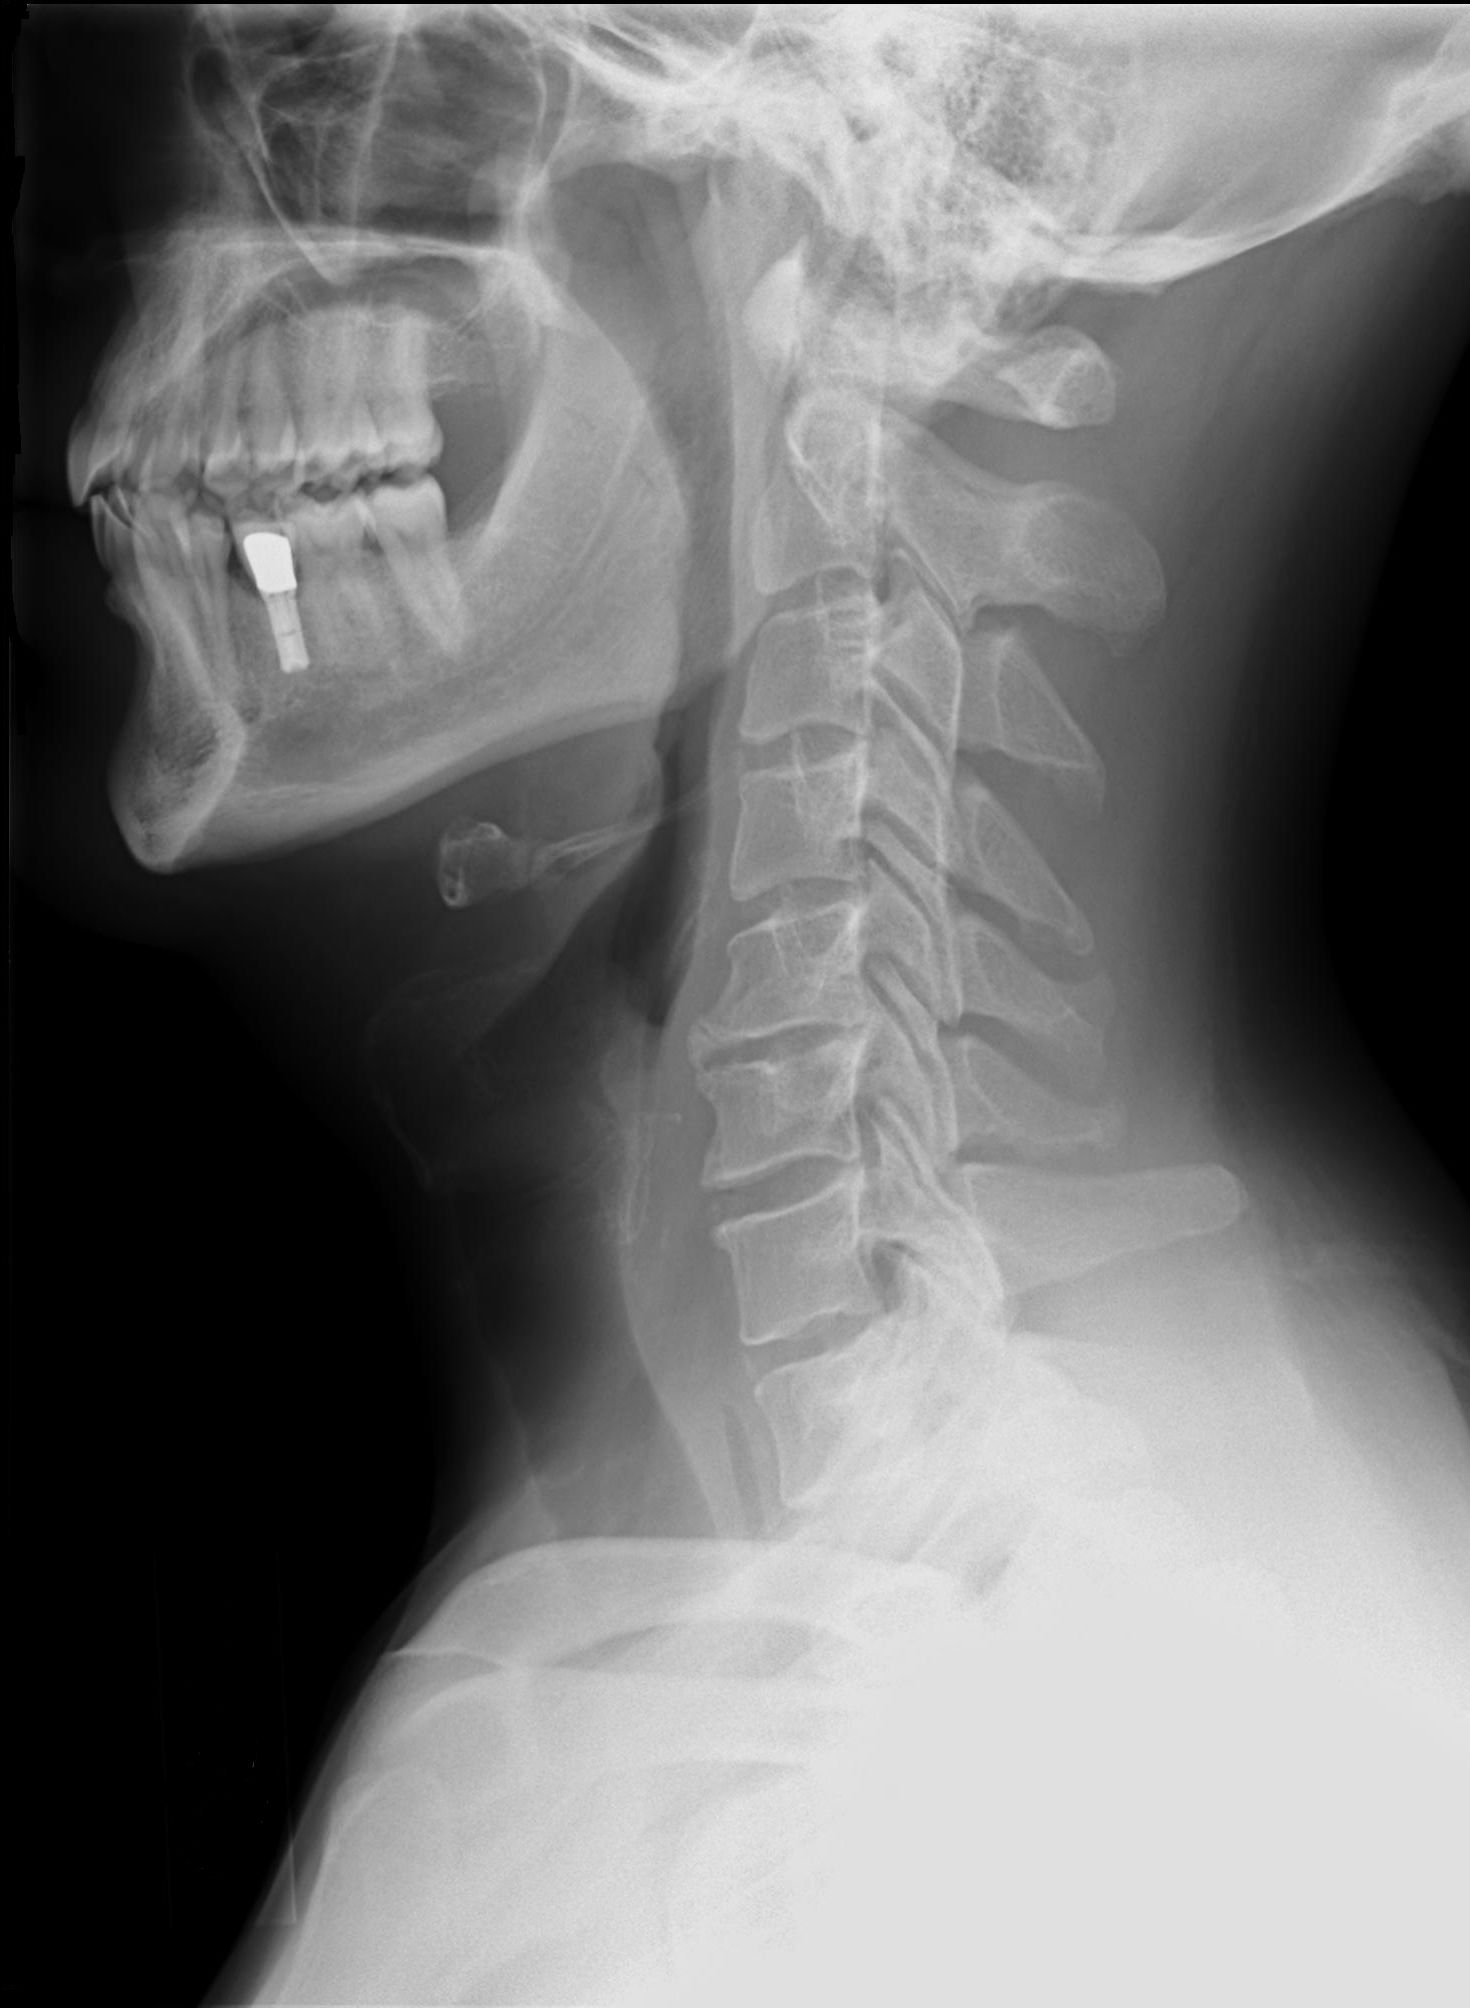
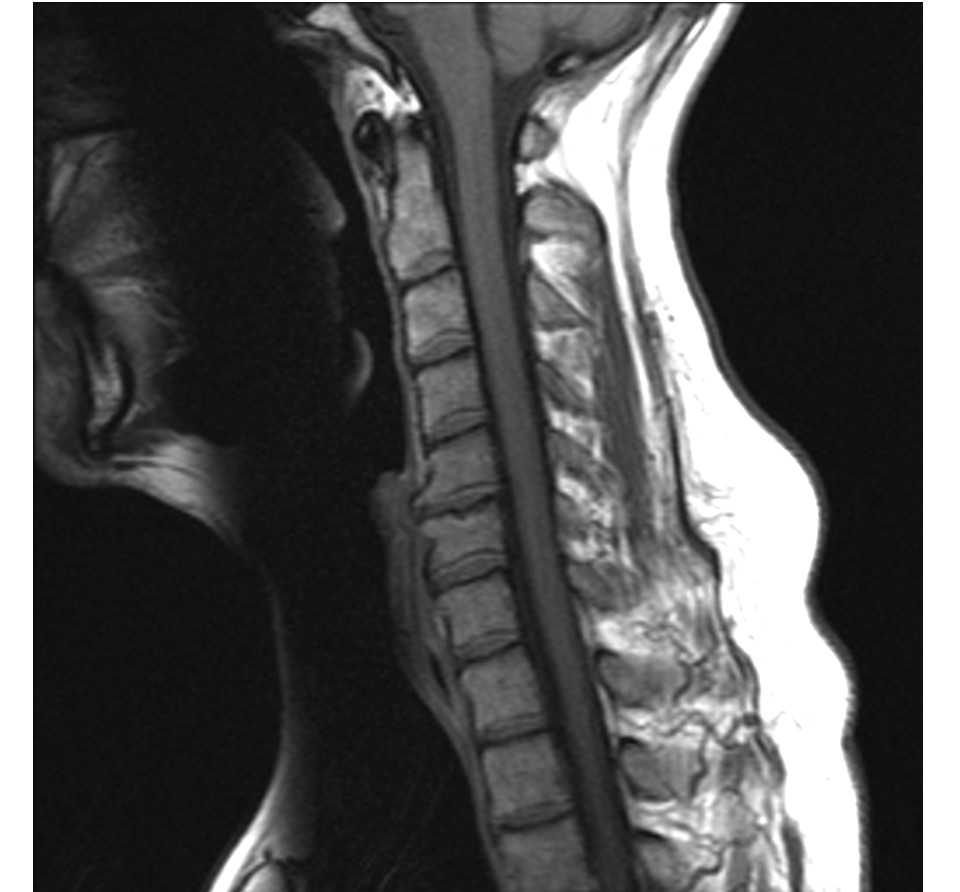
Routine CT or MRI is not recommended for uncomplicated symptoms. Imaging is used to identify or exclude structural pathology rather than to prove the presence of whiplash or facet-mediated pain.
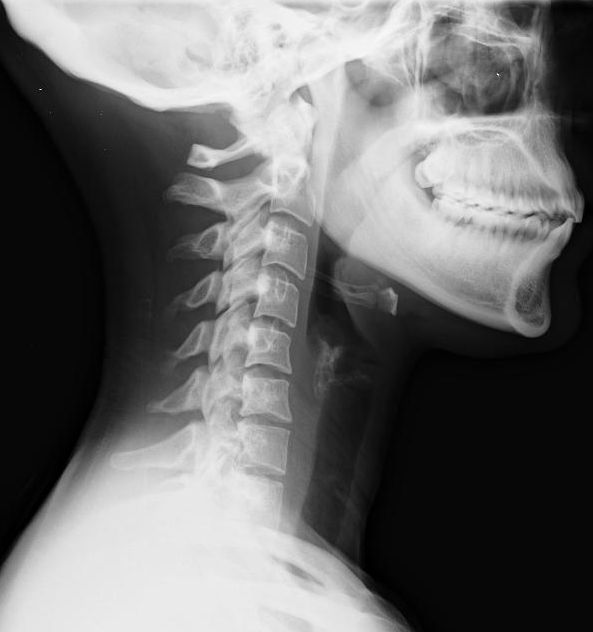
Degenerative facet changes on imaging are common and may be asymptomatic. Conversely, a painful facet joint may appear normal. Imaging findings must therefore be interpreted in the clinical context.
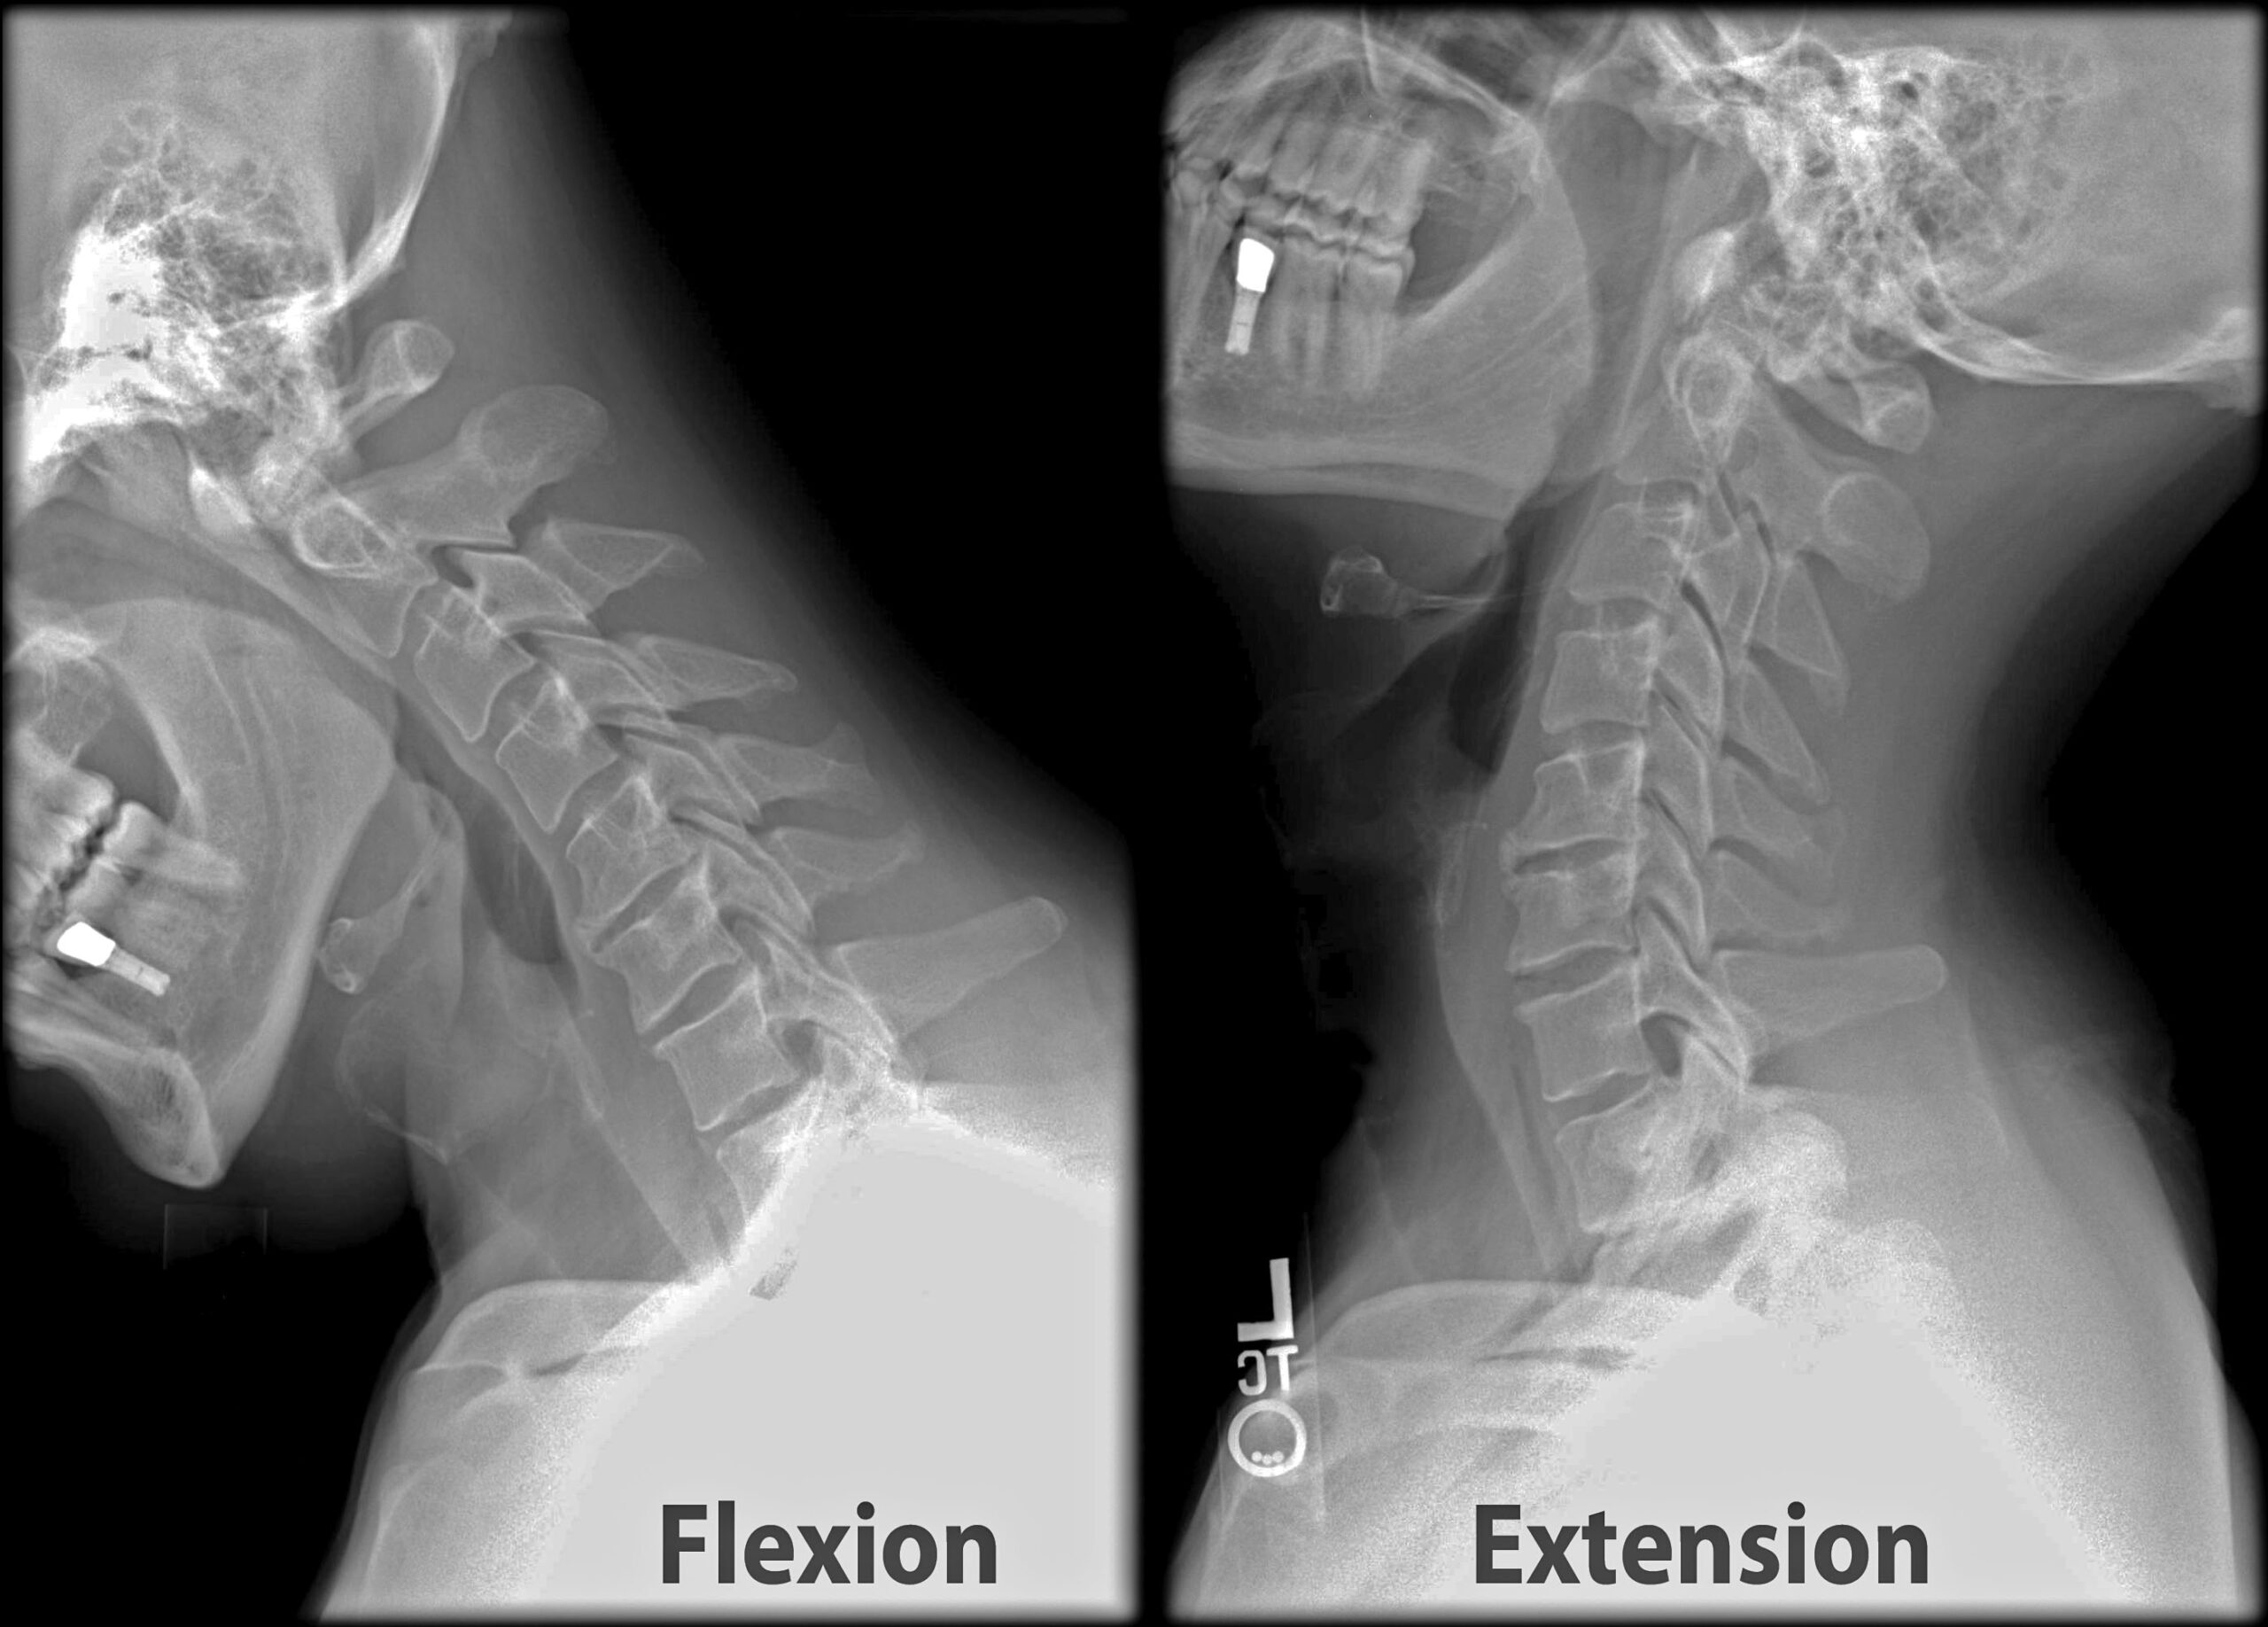
Imaging is not routinely required unless there are red flags or concern for cervical spine fracture, guided by rules such as the Canadian C-spine rule.
A tender facet region or pain on extension–rotation raises suspicion but does not establish facet-mediated pain. Routine imaging demonstrates anatomy; a correctly performed medial branch block tests whether the targeted joint’s nerve supply contributes to the patient’s pain.
Treatment
Immediate and Early Management
Initial management should prioritise exclusion of serious injury, followed by reassurance and active recovery.
Recommended measures include:
- Explain that pain and stiffness are common after whiplash and that recovery is expected for many patients.
- Encourage continuation or gradual resumption of normal daily activities.
- Avoid unnecessary restriction of activity.
- Provide cervical range-of-motion exercises.
- Progress to low-load isometric, postural endurance, coordination and strengthening exercises.
- Modify work or activities temporarily when required while maintaining participation.
- Review pain, disability and neurological findings over time.
Exercise may improve pain and disability, although the certainty and magnitude of benefit vary between studies. Programmes should be individualised and progressed according to symptoms and function.
Analgesia may include:
- Paracetamol for short-term pain relief when appropriate.
- A short course of a non-steroidal anti-inflammatory drug when simple analgesia is inadequate and there are no contraindications.
- Reassessment rather than automatic continuation when severe pain requires stronger analgesia.
Prolonged use of soft cervical collars and extended reduction of usual activities are not recommended because immobilisation may delay functional recovery. Passive treatments should not replace education, activity and exercise.
The cornerstone of uncomplicated acute WAD management is reassurance, continuation of usual activity and progressive neck exercise—not prolonged rest or immobilisation in a cervical collar.
Persistent Symptoms
Patients who are not improving should be reassessed for:
- Missed structural or neurological injury.
- High pain or disability.
- Poor recovery expectations.
- Post-traumatic stress, fear of movement or catastrophising.
- Sleep disturbance.
- Workplace or social barriers.
- Alternative pain generators.
Management may require coordinated physiotherapy, medical review, psychological treatment and rehabilitation. Persistent symptoms should not automatically be attributed to ongoing tissue damage.
Suspected Persistent Facet-Mediated Pain
Management generally begins with conservative care, including education, graded activity, exercise and appropriate analgesia.
If disabling axial neck pain persists despite conservative treatment:
- Refer for assessment by an appropriately trained pain or spine specialist.
- Consider image-guided cervical medial branch blocks when facet-mediated pain is clinically suspected.
- Assess the patient’s response during activities that normally provoke pain.
- Consider cervical medial branch radiofrequency ablation when a prognostic block produces meaningful temporary relief and the overall clinical picture is appropriate.2
Radiofrequency ablation may provide benefit in carefully selected patients, but outcomes depend on patient selection and procedural technique. Medial branch blocks are more predictive than routine intra-articular facet injections.
Surgery has no routine role in uncomplicated WAD or isolated facet-mediated pain. It is reserved for a separate surgically treatable lesion such as instability, fracture, spinal cord compression or significant nerve-root compression.
Complications & Prognosis
Complications
- Persistent neck pain and stiffness.
- Chronic headache.
- Reduced cervical movement.
- Ongoing functional limitation or work absence.
- Neuropathic or radicular symptoms.
- Sleep disturbance and fatigue.
- Post-traumatic stress, anxiety or depression.
- Fear of movement and physical deconditioning.
- Persistent pain sensitisation.
- Medication-related adverse effects.
- Complications of interventional procedures, including bleeding, infection, nerve injury or vascular injury.
Prognosis
Recovery is variable. Many patients improve substantially during the first weeks to months, but a clinically important proportion report persistent symptoms at one year. Greater initial pain, greater disability, multiple symptoms, restricted movement, poor recovery expectations and post-traumatic psychological symptoms are associated with slower recovery.
References
- State Insurance Regulatory Authority. Guidelines for the management of acute whiplash-associated disorders—for health professionals [Internet]. 3rd ed. Sydney: State Insurance Regulatory Authority; 2014 [cited 2026 Sep 1]. Available from: https://www.sira.nsw.gov.au/resources-library/motor-accident-resources/publications/for-professionals/whiplash-resources.
- Hurley RW, Adams MCB, Barad M, Bhaskar A, Bhatia A, Chadwick A, et al. Consensus practice guidelines on interventions for cervical spine (facet) joint pain from a multispecialty international working group. Reg Anesth Pain Med. 2022;47(1):3–59. doi:10.1136/rapm-2021-103031.
- Usunier K, Hynes M, Schuster JM, Suen ACJ, Sadi J, Walton D. Clinical diagnostic tests versus medial branch blocks for adults with persisting cervical zygapophyseal joint pain: a systematic review and meta-analysis. Physiother Can. 2018;70(2):179–187. doi:10.3138/ptc.2016-89.mt.
- Chrcanovic B, Larsson J, Malmström EM, Westergren H, Häggman-Henrikson B. Exercise therapy for whiplash-associated disorders: a systematic review and meta-analysis. Scand J Pain. 2022;22(2):232–261. doi:10.1515/sjpain-2021-0064.
- Carroll LJ, Holm LW, Hogg-Johnson S, Côté P, Cassidy JD, Haldeman S, et al. Course and prognostic factors for neck pain in whiplash-associated disorders: results of the Bone and Joint Decade 2000–2010 Task Force on Neck Pain and Its Associated Disorders. Spine (Phila Pa 1976). 2008;33(4 Suppl):S83–S92. doi:10.1097/BRS.0b013e3181643eb8.