

Overview
Acne vulgaris is a chronic inflammatory disease of the pilosebaceous units, most commonly involving the face, neck, chest, and back. It is characterized by the formation of comedones, papules, pustules, nodules, and, in severe cases, deep scars.
While classically viewed as a rite of passage during adolescence, acne can persist into or present for the first time in adulthood. Beyond its physical manifestations, acne carries a profound psychosocial burden, frequently causing anxiety, depression, and social withdrawal.
Definition
Microcomedone: The primary microscopic precursor lesion of all acne, caused by hyperkeratinization of the infundibulum of the hair follicle.
Open Comedone (“Blackhead”): A dilated follicular opening plugged with sebum and keratin; the dark color is due to the oxidation of melanin and lipids, not dirt.
Closed Comedone (“Whitehead”): A small, skin-colored or whitish papule with a microscopic follicular opening, trapping sebum and bacteria beneath the skin surface.
Inflammatory Lesions: Papules, pustules, nodules, and pseudocysts resulting from immune-mediated rupture of the follicular wall and inflammation.
Post-Inflammatory Hyperpigmentation (PIH): Residual flat, hyperpigmented macules left behind after inflammation heals, particularly common in darker skin phototypes.
Classification
- Acne Conglobata: A severe, highly inflammatory form characterized by interconnected nodules, abscesses, and severe scarring, predominantly on the back and chest; lacks systemic symptoms.
- Acne Fulminans: A rare, acute, severe form characterized by explosive nodulocystic lesions accompanied by systemic symptoms (fever, arthralgias, leukocytosis, and elevated ESR). Often triggered by initiating oral isotretinoin.
- Neonatal Acne: Self-limiting pustular eruption on the face of newborns, driven by maternal/neonatal androgens; resolves spontaneously within weeks.
Aetiology & Risk Factors
Core Pathogenic Factors
- Androgen-Driven Sebum Production: Increased circulating androgens (or end-organ sensitivity) stimulate sebaceous gland hypertrophy and lipid synthesis.
- Follicular Hyperkeratinization: Abnormal desquamation of keratinocytes inside the follicular duct.
- Microbial Colonization: Proliferation of Cutibacterium acnes within the lipid-rich, anaerobic microenvironment.
- Inflammation: Immune response triggered by C. acnes releasing pro-inflammatory mediators and lipases.
Risk Factors & Exacerbating Triggers
- Genetics: Strong family history; severe acne is often linked to polygenic inheritance.
- Endocrine Disorders: Polycystic Ovary Syndrome (PCOS) or non-classic congenital adrenal hyperplasia.
- Dietary Factors: Diets high in glycemic index (refined sugars) and dairy products may exacerbate symptoms in susceptible individuals.
- Medications (“PIMPS”): Phenytoin, Isoniazid, Moisturizers (comedogenic), Phenobarbital, Steroids (systemic corticosteroids and anabolic steroids), Lithium.
- Mechanical Factors: Friction, pressure, or occlusion from helmets, straps, or tight clothing (“acne mechanica”).
Systemic corticosteroids can paradoxically cause or severely flare acne (steroid acne), which characteristically presents as monomorphic inflammatory papules lacking comedones.
Pathophysiology
- Follicular Hyperkeratosis: Keratinocytes fail to shed normally, forming a cohesive keratin plug (retention hyperkeratosis).
- Sebum Production: Sebum provides the ideal lipid nutrient medium for the anaerobic bacterium Cutibacterium acnes.
- Immune Activation: C. acnes produces lipases that break down triglycerides into free fatty acids, activating Toll-like receptors (TLRs) on keratinocytes and macrophages, driving local interleukin (IL-1, IL-8) and TNF-alpha release.
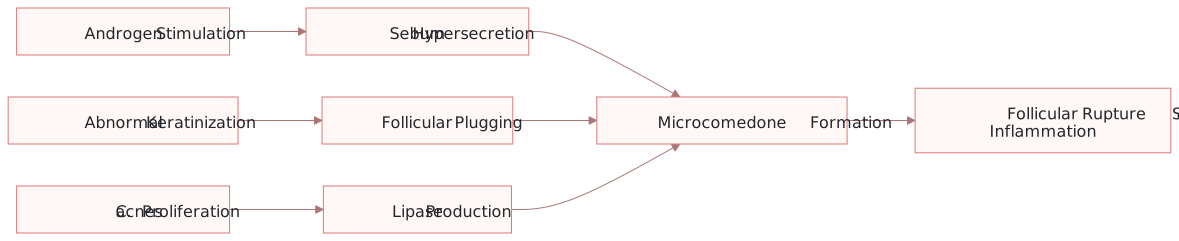
What to notice
Detailed image description
Clinical Manifestations
Predominantly affects areas with the highest density of sebaceous glands: face, upper chest, back, and shoulders.
Lesion Characteristics
- Non-inflammatory: Open and closed comedones.
- Inflammatory:
- Papules: Small, tender, pink-to-red bumps less than 5 mm in diameter.
- Pustules: Superficial, pus-filled lesions with a white or yellow apex.
- Nodules: Deep, painful, firm inflammatory lesions greater than 5 mm in diameter that may heal with scarring.
- Cysts: Deep, painful, fluctuant, pus-filled lesions that may result in scarring.
Diagnosis
Diagnosis of acne vulgaris is strictly clinical, based on lesion distribution, morphological characteristics (presence of comedones), and clinical history.
Investigations for Hyperandrogenism
- Indications: Female patients presenting with severe, sudden-onset acne refractory to standard therapy, accompanied by signs of hyperandrogenism (hirsutism, male-pattern alopecia, irregular menses, or deepening voice).
- Workup: Total and free testosterone, Dehydroepiandrosterone sulfate (DHEAS), Luteinizing Hormone (LH), and Follicle-Stimulating Hormone (FSH).
Treatment
Mild Acne (Comedonal / Mild Inflammatory)
- Topical Retinoids (First-Line): Adapalene, Tretinoin, or Tazarotene. Normalizes follicular keratinization and reduces comedones. (Note: Apply at night; cause sun sensitivity).
- Topical Antimicrobials: Benzoyl Peroxide (BPO) or Topical Clindamycin/Erythromycin (always combined with BPO to prevent bacterial resistance).
- Azelaic Acid: Alternative topical anti-inflammatory and comedolytic agent; safe in pregnancy.
Moderate Acne (Inflammatory Papules/Pustules)
- Topical Combination Therapy: Topical Retinoid + Benzoyl Peroxide +/- Topical Antibiotic.
- Oral Antibiotics: Tetracycline class (Doxycycline or Minocycline) combined with topical retinoids/BPO. Limit courses to 3–4 months to prevent antibiotic resistance.
- Hormonal Therapy (Females): Combined Oral Contraceptive Pills (containing anti-androgenic progestins like drospirenone) or Spironolactone (mineralocorticoid receptor antagonist and androgen blocker).
Severe Acne (Nodulocystic / Scarring)
- Oral Isotretinoin (13-cis-retinoic acid): The gold standard for severe, refractory, or scarring acne.
- Mechanism: Suppresses sebaceous gland size and activity, normalizes keratinization, and inhibits C. acnes.
- Crucial Precautions: Highly teratogenic (Category X)—requires strict, double-barrier contraception and monthly pregnancy testing in women of childbearing potential.
- Key Side Effects: Severe mucocutaneous dryness (cheilitis, xerosis), elevated liver enzymes, hyperlipidemia, and mood disturbances.
Complications & Prognosis
Complications
- Atrophic Scars: Permanent structural loss of dermal collagen, categorized into icepick (deep, narrow), rolling (shallow, wide depressions), and boxcar (sharp-edged, crater-like) scars.
- Hypertrophic & Keloid Scars: Raised, firm scars occurring most frequently on the chest and back.
- Post-Inflammatory Hyperpigmentation (PIH): Prolonged skin discoloration following inflammation.
- Psychological Morbidity: High rates of depression, anxiety, body dysmorphic disorder, and social isolation.
Prognosis
- Acne is typically a self-limiting condition of adolescence that resolves spontaneously by the mid-20s to 30s. However, severe nodulocystic disease requires early aggressive intervention to prevent permanent physical and psychological scarring.
References
- Zaenglein AL, Pathy AL, Schlosser BJ, et al. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol. 2016;74(5):945-973.e33. doi:10.1016/j.jaad.2015.12.037
- O’Brien SC, Lewis JB, Cunliffe WJ. Acne vulgaris. Lancet. 1998;351(9119):1871-1876. doi:10.1016/S0140-6736(98)03223-9
- Thiboutot D, Gollnick H, Bettoli V, et al. New insights into the management of acne: An update from global alliance to improve outcomes in acne group. J Am Acad Dermatol. 2009;60(5 Suppl):S1-S50. doi:10.1016/j.jaad.2009.01.019