

Overview
Chondrosarcoma is a malignant bone tumour in which neoplastic cells produce cartilage matrix. It encompasses a biologically diverse group ranging from locally aggressive, low-grade tumours to high-grade sarcomas with substantial metastatic potential. Chondrosarcoma is among the most common primary malignant bone tumours and predominantly affects adults, particularly those older than 40 years.
Conventional chondrosarcoma is the most common subtype. Tumours frequently arise in the pelvis, proximal femur, proximal humerus, ribs or scapula. Surgery is the principal treatment because most conventional chondrosarcomas respond poorly to conventional chemotherapy and radiotherapy.
Suspected chondrosarcoma should be assessed by a specialist bone-sarcoma multidisciplinary team before biopsy or definitive surgery. An incorrectly placed biopsy can contaminate uninvolved tissue and compromise subsequent limb-sparing resection.
Definition
- Chondrosarcoma
- A malignant cartilage-producing tumour arising in bone or, less commonly, soft tissue.
- Chondroid matrix
- Cartilage-like extracellular material produced by the tumour, often producing characteristic ring-and-arc calcification on imaging.
- Atypical cartilaginous tumour
- An intermediate, locally aggressive cartilaginous tumour in the appendicular skeleton that is histologically equivalent to grade 1 conventional chondrosarcoma.
- Dedifferentiation
- Abrupt transition from a cartilaginous tumour to a high-grade non-cartilaginous sarcoma.
- Wide surgical margin
- Removal of a tumour with a surrounding cuff of uninvolved tissue to reduce the risk of residual disease and local recurrence.
Chondrosarcoma is a malignant bone tumour that produces cartilage. It usually occurs in adults aged 40–70 years.
Aetiology & Risk Factors
Aetiology
Most chondrosarcomas arise sporadically. They may be classified according to their relationship with a precursor lesion:
- Primary chondrosarcoma: develops de novo within bone, usually in the medullary cavity.
- Secondary central chondrosarcoma: develops within a pre-existing enchondroma.
- Secondary peripheral chondrosarcoma: develops from the cartilage cap of an osteochondroma.
- Periosteal chondrosarcoma: arises from the bone surface beneath the periosteum.
Mutations involving IDH1 or IDH2 are found in many central conventional chondrosarcomas and enchondromas. Peripheral tumours arising from osteochondromas are associated with alterations affecting the EXT1 or EXT2 pathways. These findings support the biological relationship between certain benign cartilage tumours and secondary chondrosarcoma.
Risk Factors
- A solitary osteochondroma or enchondroma, although malignant transformation is uncommon.
- Multiple hereditary exostoses, also called hereditary multiple osteochondromas.
- Ollier disease, characterised by multiple enchondromas.
- Maffucci syndrome, characterised by multiple enchondromas and soft-tissue vascular lesions.
- Previous radiotherapy, rarely.
- Increasing age, particularly for conventional chondrosarcoma.
New pain, growth after skeletal maturity or increasing cartilage-cap thickness in a known osteochondroma should prompt specialist reassessment.
Pathophysiology
Chondrosarcoma develops through malignant transformation of cartilage-producing mesenchymal cells. Neoplastic chondrocytes produce lobules of hyaline or myxoid cartilage matrix that expand within the medullary cavity or along the bone surface.
As the tumour enlarges, it may cause endosteal scalloping, cortical thinning and eventual cortical destruction. Extension through the cortex produces an extraosseous soft-tissue mass. Higher-grade tumours show increasing cellularity, nuclear atypia and mitotic activity, with a greater capacity for local invasion and haematogenous metastasis.
Conventional chondrosarcoma spreads mainly through the bloodstream, most often to the lungs. Lymph-node metastases are uncommon. Dedifferentiated and mesenchymal chondrosarcomas behave more aggressively and may metastasise earlier than low-grade conventional tumours.1,3
Progressive pain and aggressive imaging features reflect increasing biological activity. Cortical breakthrough and a soft-tissue mass indicate that the tumour is no longer confined by bone, increasing the complexity of achieving a complete surgical margin.
Clinical Manifestations
Chondrosarcoma commonly presents with slowly progressive, deep-seated pain at the affected bone. Symptoms may be present for months before diagnosis because many conventional tumours grow gradually.3
- Persistent or progressively worsening bone pain.
- Pain at rest or during the night.
- Local swelling or a palpable enlarging mass.
- Reduced movement or function near an affected joint.
- Neurological symptoms when a spinal or pelvic tumour compresses adjacent nerves.
- Pathological fracture, particularly with extensive cortical destruction.
- Incidental detection of a cartilaginous lesion on imaging performed for another reason.
Persistent pain arising from a cartilage tumour is clinically important. New pain, growth after skeletal maturity, cortical destruction or a soft-tissue mass should not be dismissed as features of a benign enchondroma or osteochondroma.
Diagnosis
Diagnosis requires imaging and biopsy, usually coordinated through a specialist sarcoma service.
Initial imaging
Plain radiographs are usually the first investigation. Features of a cartilaginous tumour include:
- A central or surface-based lytic lesion.
- Lobulated margins.
- Stippled, ring-and-arc or popcorn-like calcification representing mineralised chondroid matrix.
- Endosteal scalloping.
- Cortical expansion or thickening.
Imaging may show a destructive bone lesion with chondroid “ring-and-arc” calcification.

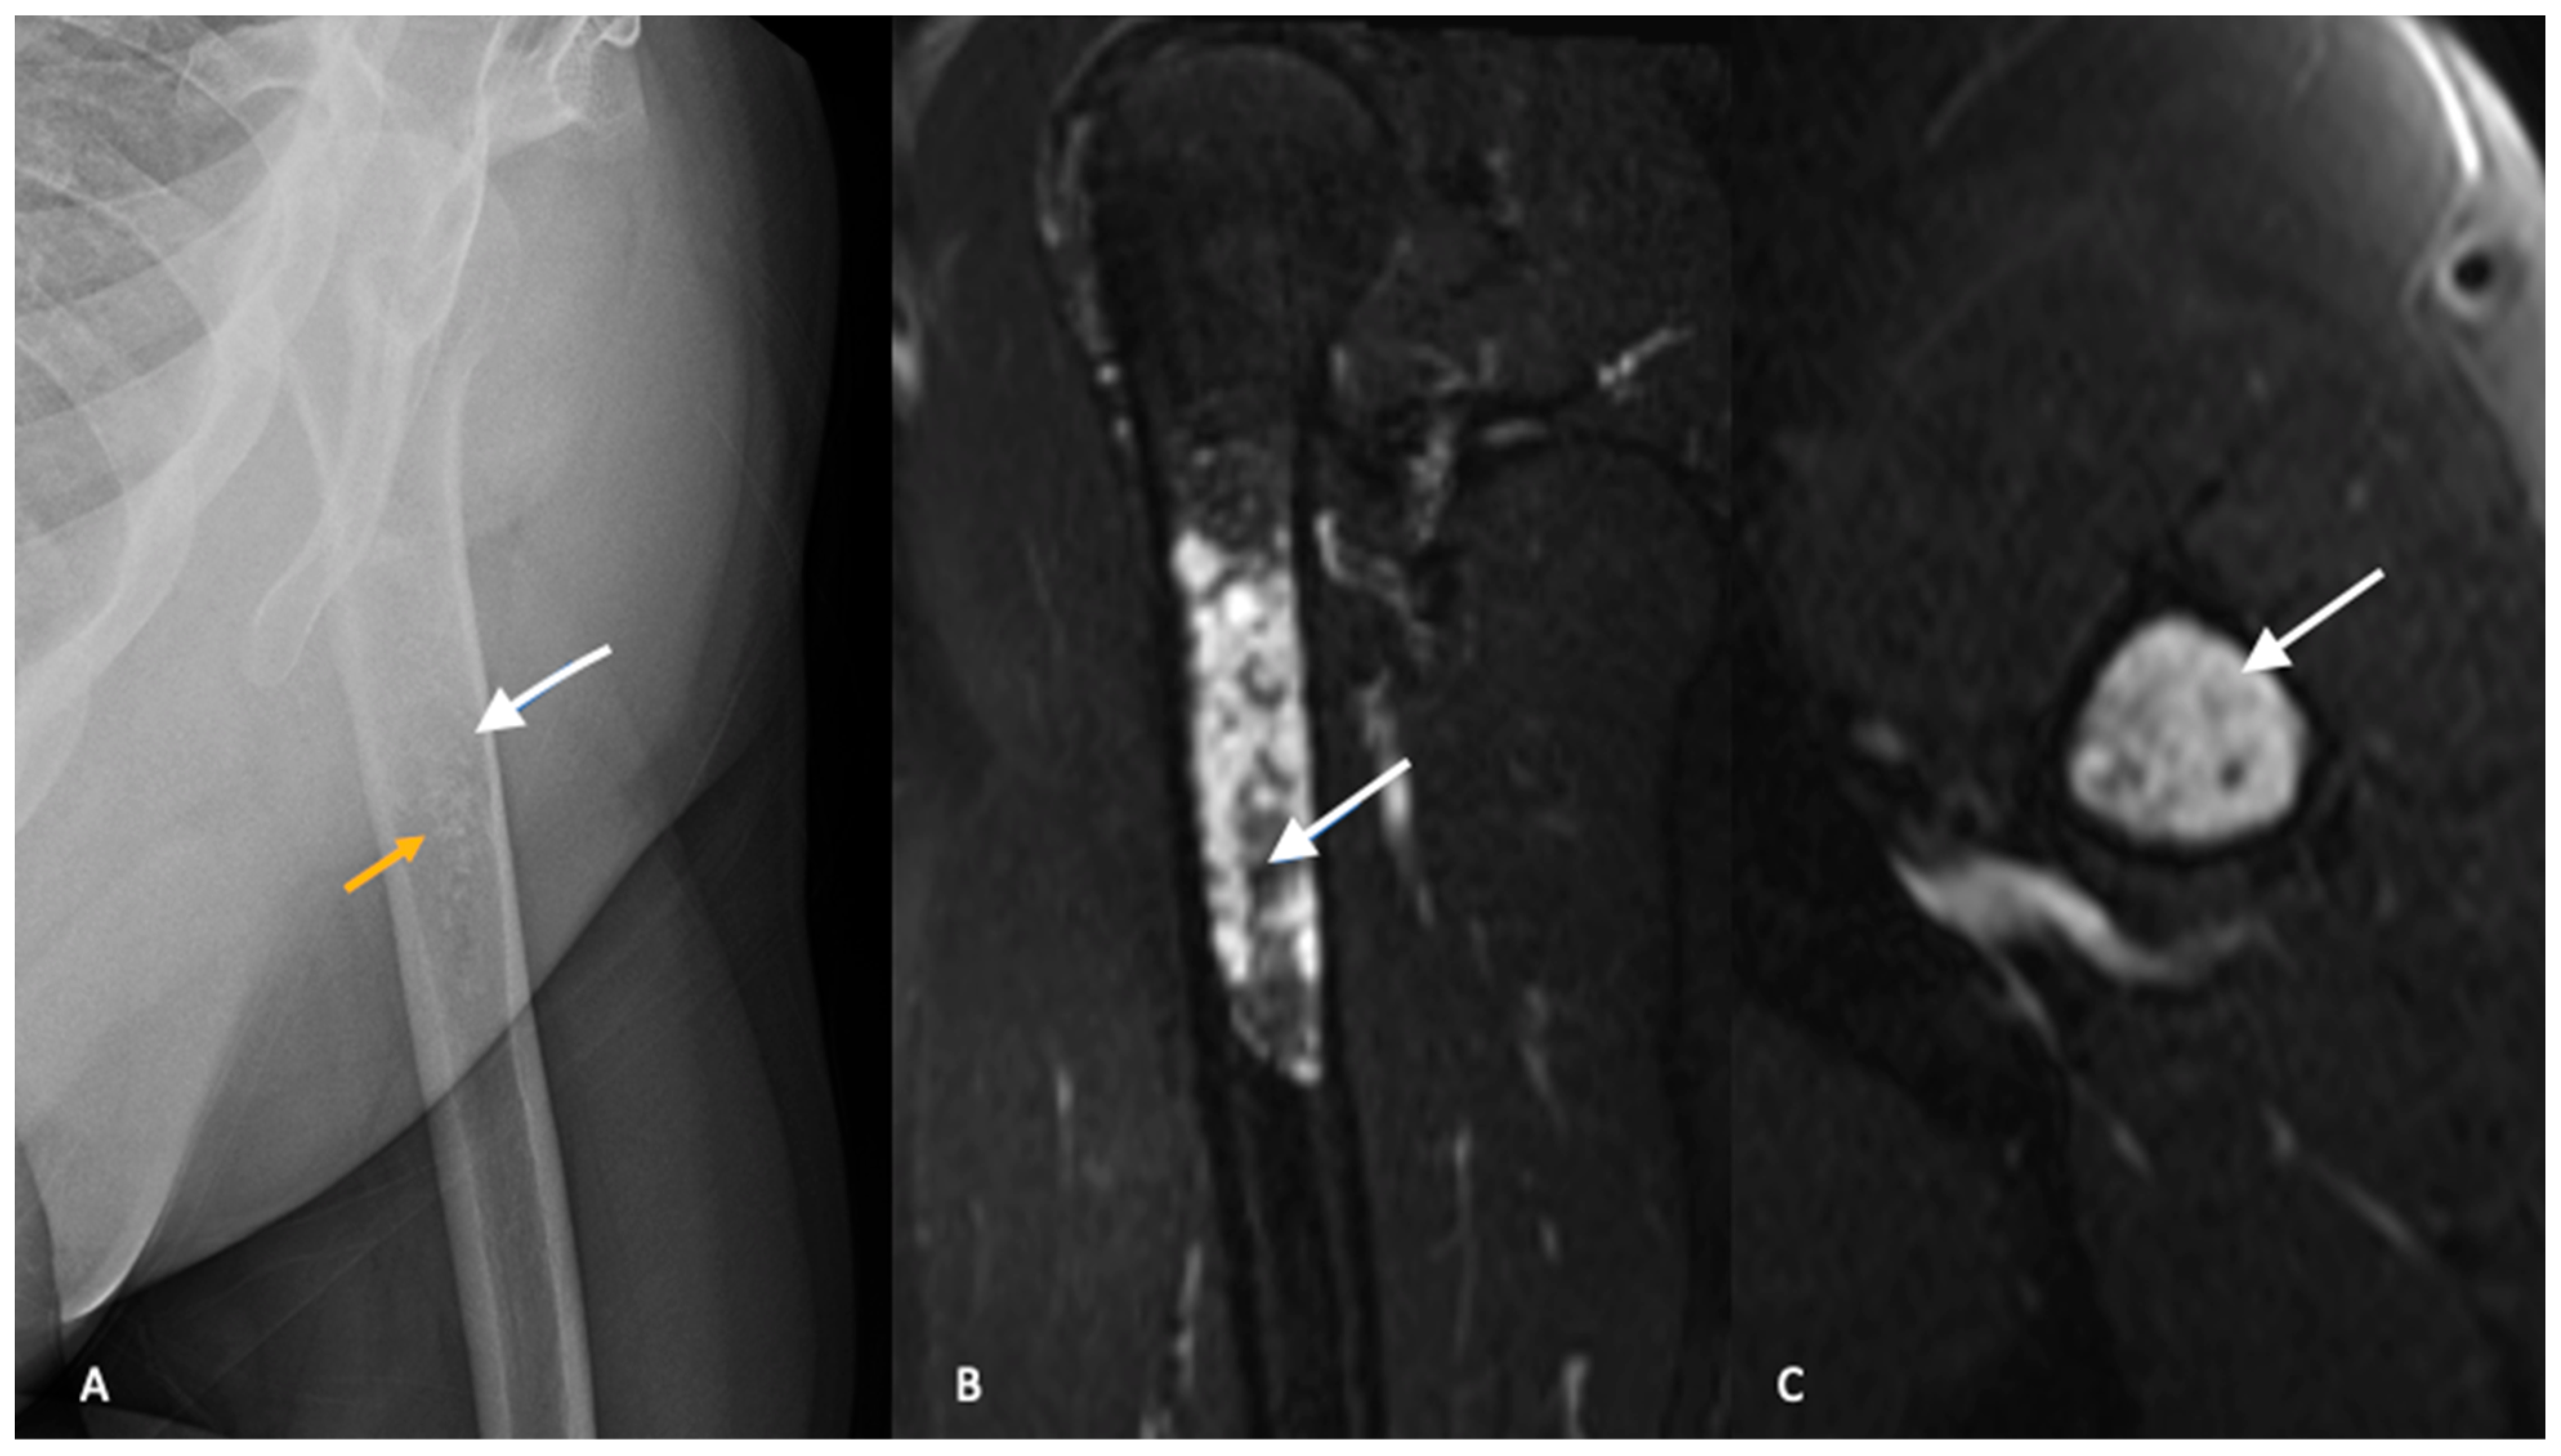
MRI is the preferred modality for defining intramedullary extent, soft-tissue extension, neurovascular involvement and the relationship of the tumour to joints and other critical structures. Cartilage-rich areas are typically lobulated and markedly hyperintense on fluid-sensitive sequences.
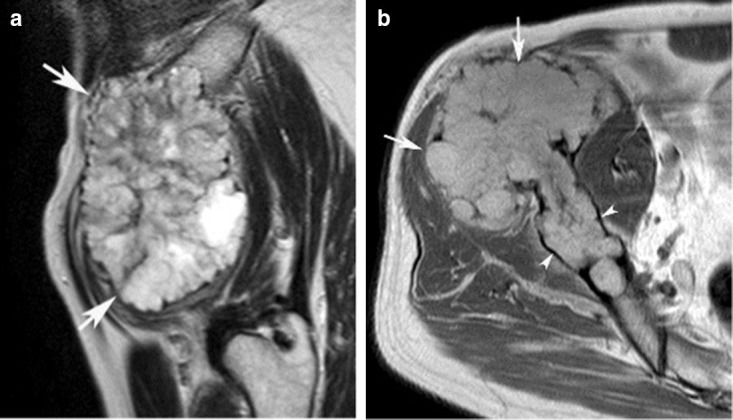
CT demonstrates matrix mineralisation and cortical destruction particularly well. It is useful for anatomically complex sites such as the pelvis, ribs and spine.
Ring-and-arc calcification identifies a cartilaginous matrix but does not by itself establish malignancy. Pain, endosteal scalloping, cortical destruction, soft-tissue extension and interval growth help distinguish a more aggressive lesion.
Staging
Staging investigations commonly include:
- MRI of the entire involved bone and adjacent joint.
- CT of the chest to assess for pulmonary metastases.
- Additional whole-body imaging, such as bone scintigraphy or positron-emission tomography–CT, in selected patients according to tumour grade, symptoms and specialist protocol.
- Baseline blood tests before biopsy or treatment, although there is no diagnostic serum tumour marker for chondrosarcoma.
Biopsy
Core-needle biopsy is commonly used
Do not perform an unplanned biopsy or excision of a suspected primary bone sarcoma. Imaging and biopsy must be coordinated by the team that will undertake definitive tumour resection.
Classification
Conventional chondrosarcoma
Conventional chondrosarcoma may arise centrally within the medullary cavity or peripherally from the surface of a pre-existing osteochondroma. Histological grade predicts biological behaviour:
- Grade 1: low cellularity and mild atypia; locally aggressive but with low metastatic potential.
- Grade 2: increased cellularity and atypia with greater risk of recurrence and metastasis.
- Grade 3: marked atypia and mitotic activity with high metastatic potential.

In the appendicular skeleton, a grade 1 central cartilaginous tumour is termed an atypical cartilaginous tumour. Histologically similar tumours in the axial skeleton—including the pelvis, spine and skull base—retain the designation grade 1 chondrosarcoma because their anatomical location makes complete excision more difficult and their clinical behaviour is less favourable.2
Important subtypes
- Dedifferentiated chondrosarcoma: contains a conventional cartilaginous component adjacent to an abrupt high-grade non-cartilaginous sarcoma. It is highly aggressive.
- Mesenchymal chondrosarcoma: a rare high-grade subtype affecting younger patients more often than conventional chondrosarcoma. It may arise in bone or soft tissue.
- Clear cell chondrosarcoma: generally low grade, often affecting the epiphysis of long bones, but capable of late local recurrence or metastasis.
- Periosteal chondrosarcoma: arises on the bone surface beneath the periosteum and most often affects long bones.
Treatment
Management should occur through a specialist bone-sarcoma multidisciplinary team. Treatment depends on anatomical site, subtype, histological grade, resectability and metastatic status.
Surgery
Surgical excision is the mainstay of treatment.
- Atypical cartilaginous tumour of a long bone: selected lesions may be treated with extended intralesional curettage, often with local adjuvant treatment and reconstruction of the defect.
- Grade 1 axial chondrosarcoma: generally requires complete surgical excision because local recurrence can be difficult to manage and pelvic or axial lesions behave less favourably.
- Grade 2 or 3 conventional chondrosarcoma: wide en bloc excision with clear margins is preferred.
- Dedifferentiated, mesenchymal and clear cell subtypes: complete surgical resection is pursued where feasible.
- Amputation: occasionally required when a safe functional limb-sparing resection cannot achieve adequate margins.
Unplanned excision, tumour rupture and positive surgical margins increase the risk of local recurrence.
Radiotherapy
Conventional chondrosarcoma is relatively resistant to standard radiotherapy. Radiotherapy may nevertheless be considered:
- For an unresectable tumour.
- When complete surgical margins cannot be achieved.
- For selected skull-base or spinal tumours, where high-dose conformal techniques or particle therapy may be useful.
- For palliation of painful or symptomatic metastatic disease.
Systemic therapy
Conventional chondrosarcoma has limited sensitivity to cytotoxic chemotherapy, so chemotherapy is not routinely used for resected localised conventional disease.
Systemic treatment may be considered for:
- Mesenchymal chondrosarcoma
- Dedifferentiated chondrosarcoma
- Unresectable or metastatic disease, preferably through a specialist sarcoma service and clinical trial.
For conventional chondrosarcoma, achieving complete surgical removal is more important than relying on chemotherapy or radiotherapy. Management differs for mesenchymal and dedifferentiated subtypes, so accurate classification is essential.
Complications & Prognosis
Complications
- Local recurrence.
- Pulmonary metastases.
- Metastases to other bones or soft tissues.
- Pathological fracture.
- Neurovascular compression.
- Chronic pain or impaired limb function.
- Complications of major resection or reconstruction, including infection, non-union, prosthetic failure and functional disability.
- Late recurrence, particularly with clear cell and some low-grade tumours.
Prognosis
Prognosis varies substantially and is determined primarily by:
- Histological grade.
- Histological subtype.
- Presence of metastases at diagnosis.
- Tumour size and anatomical site.
- Ability to achieve a complete surgical margin.
- Local recurrence.
- Dedifferentiation.
Atypical cartilaginous tumours of the extremities generally have an excellent prognosis after appropriate local treatment. Higher-grade conventional tumours carry greater risks of local recurrence and pulmonary metastasis. Pelvic and other axial tumours often have a less favourable outcome because their size and proximity to critical structures make complete excision more difficult.1,3,4
Dedifferentiated chondrosarcoma has an especially poor prognosis because of early metastatic spread. Clear cell and low-grade conventional tumours may recur many years after treatment, supporting prolonged surveillance.
Follow-up is individualised according to grade, subtype and site and generally includes clinical review, imaging of the primary site and chest surveillance. New pain, swelling, respiratory symptoms or functional decline should prompt earlier reassessment.
References
- Gerrand C, Amary F, Bate J, Brennan B, Cool P, Coyne C, et al. UK guidelines for the management of bone sarcomas. Br J Cancer. 2025;132(1):32–48. doi:10.1038/s41416-024-02868-4
- Kim JH, Lee SK. Classification of chondrosarcoma: from characteristic to challenging imaging findings. Cancers (Basel). 2023;15(6):1703. doi:10.3390/cancers15061703
- Gazendam A, Popovic S, Parasu N, Ghert M. Chondrosarcoma: a clinical review. J Clin Med. 2023;12(7):2506. doi:10.3390/jcm12072506
- Strauss SJ, Frezza AM, Abecassis N, Bajpai J, Bauer S, Biagini R, et al. Bone sarcomas: ESMO-EURACAN-GENTURIS-ERN PaedCan Clinical Practice Guideline for diagnosis, treatment and follow-up. Ann Oncol. 2021;32(12):1520–1536. doi:10.1016/j.annonc.2021.08.1995