

Overview
Adrenal crisis is an acute, life-threatening state of cortisol deficiency that causes haemodynamic instability and may rapidly progress to shock, hypoglycaemia, electrolyte disturbance, altered consciousness and death. It may be the first presentation of adrenal insufficiency or occur when glucocorticoid availability is inadequate during physiological stress.1–3
Clinical suspicion is sufficient to begin treatment. Blood samples should be collected before glucocorticoid administration when this can be done immediately, but diagnostic testing must never delay hydrocortisone and intravenous fluid resuscitation.1–3
Definition
- Adrenal crisis
- Acute, life-threatening physiological decompensation caused by inadequate cortisol activity during illness or stress.
- Primary adrenal insufficiency
- Cortisol deficiency caused by disease or destruction of the adrenal cortex, often with concurrent aldosterone deficiency.
- Secondary adrenal insufficiency
- Cortisol deficiency caused by inadequate pituitary adrenocorticotropic hormone secretion.
- Tertiary adrenal insufficiency
- Hypothalamic–pituitary–adrenal axis suppression, most commonly following prolonged exposure to exogenous glucocorticoids.
Anatomy & Physiology
Corticotropin-releasing hormone from the hypothalamus stimulates pituitary secretion of adrenocorticotropic hormone (ACTH), which promotes adrenal cortisol production. Cortisol supports vascular responsiveness to catecholamines, glucose availability and the physiological response to illness or injury.
Aldosterone is primarily regulated by the renin–angiotensin–aldosterone system and maintains sodium, potassium and extracellular fluid balance. It is usually preserved in secondary and tertiary adrenal insufficiency because the adrenal glands and renin–angiotensin system remain intact.
Aetiology & Risk Factors
Aetiology
Adrenal crisis results from absolute or relative glucocorticoid deficiency.
- Primary adrenal insufficiency: Autoimmune adrenalitis, adrenal haemorrhage or infarction, infection, metastatic or infiltrative disease, congenital adrenal hyperplasia, bilateral adrenalectomy or impaired steroid synthesis.
- Secondary adrenal insufficiency: Pituitary tumour, surgery, irradiation, haemorrhage, infarction or other hypothalamic–pituitary disease.
- Tertiary or glucocorticoid-induced adrenal insufficiency: Suppression of the hypothalamic–pituitary–adrenal axis by systemic or locally administered glucocorticoids, particularly after prolonged therapy.4
- Acute interruption of cortisol synthesis or action: Abrupt withdrawal of replacement therapy or drugs that accelerate cortisol metabolism or inhibit steroidogenesis.
Risk Factors
Common precipitants in a person with established or unrecognised adrenal insufficiency include:
- febrile illness, sepsis or another acute infection
- persistent vomiting or diarrhoea
- surgery, anaesthesia or invasive procedures without adequate stress-dose glucocorticoids
- trauma, burns, myocardial infarction or another major physiological stress
- childbirth
- missed, abruptly ceased or inadequately absorbed glucocorticoid therapy
- failure to increase glucocorticoids during illness
- initiation of thyroid hormone in untreated adrenal insufficiency
- medications that increase glucocorticoid metabolism, including some enzyme-inducing anticonvulsants and rifampicin.
Pathophysiology
Acute cortisol deficiency reduces vascular responsiveness to catecholamines and impairs maintenance of vascular tone. This produces vasodilatation, hypotension and shock that may respond poorly to fluids and vasopressors until glucocorticoids are administered.
Cortisol deficiency also reduces gluconeogenesis and the physiological stress response, contributing to hypoglycaemia, weakness, fever and altered consciousness. Increased antidiuretic hormone activity and impaired free-water excretion contribute to hyponatraemia.
In primary adrenal insufficiency, concurrent aldosterone deficiency causes renal sodium loss, hypovolaemia and hyperkalaemia. Hyperkalaemia is generally absent in isolated secondary or tertiary adrenal insufficiency because aldosterone secretion is preserved.2,3
Hyponatraemia can occur in all forms of adrenal insufficiency, whereas hyperkalaemia strongly suggests associated mineralocorticoid deficiency and therefore a primary adrenal cause.
Clinical Manifestations
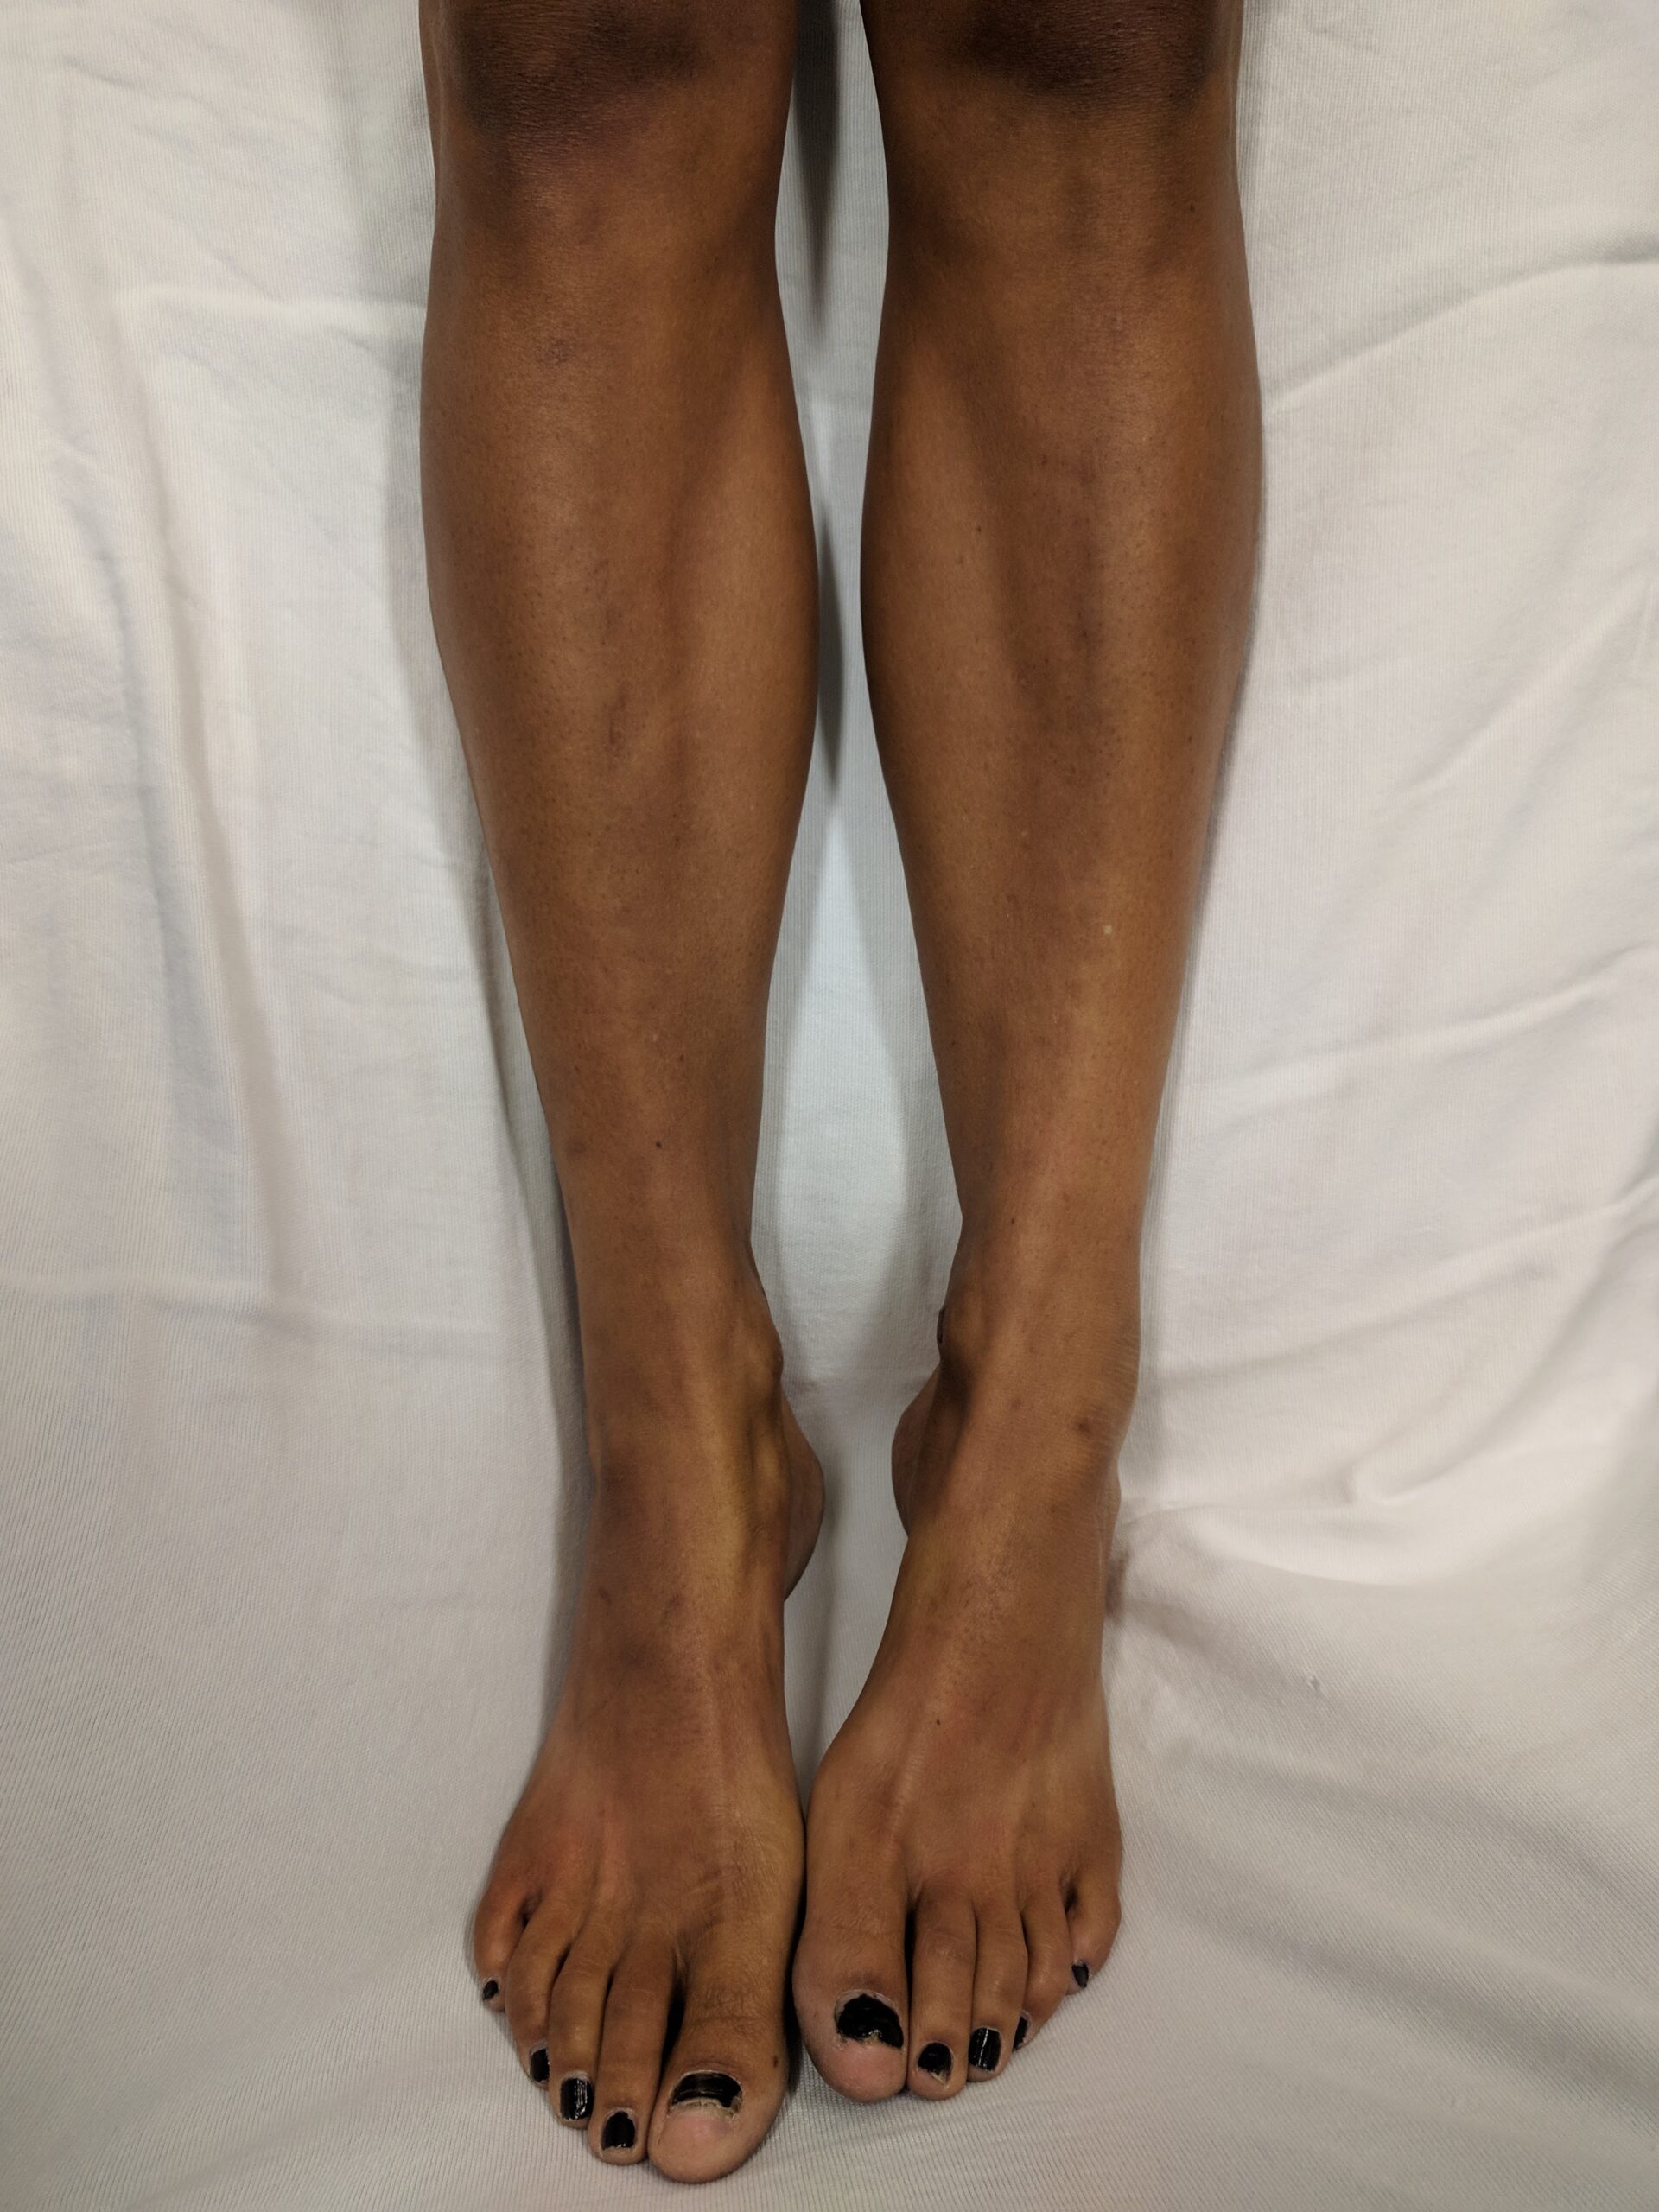
Hyperpigmentation in primary adrenal insufficiency. Source: James Heilman, MD / Wikimedia Commons, licensed under CC BY-SA 4.0.
What to notice
Detailed image description
Adrenal crisis often presents non-specifically. Important manifestations include:
- hypotension, postural hypotension or shock
- profound weakness, fatigue or collapse
- nausea, vomiting, diarrhoea or severe abdominal pain
- fever
- dehydration
- confusion, delirium, reduced consciousness, seizure or coma
- hypoglycaemic symptoms
- myalgia, arthralgia or muscle cramps.
Features suggesting pre-existing primary adrenal insufficiency include hyperpigmentation, weight loss, salt craving and postural dizziness. A history of pituitary disease, chronic glucocorticoid exposure or recent glucocorticoid withdrawal may instead indicate secondary or tertiary adrenal insufficiency.
Consider adrenal crisis in unexplained hypotension or shock—particularly when accompanied by vomiting, abdominal pain, hyponatraemia, hypoglycaemia, hyperkalaemia or a history of adrenal disease or glucocorticoid exposure.
Diagnosis & Investigations
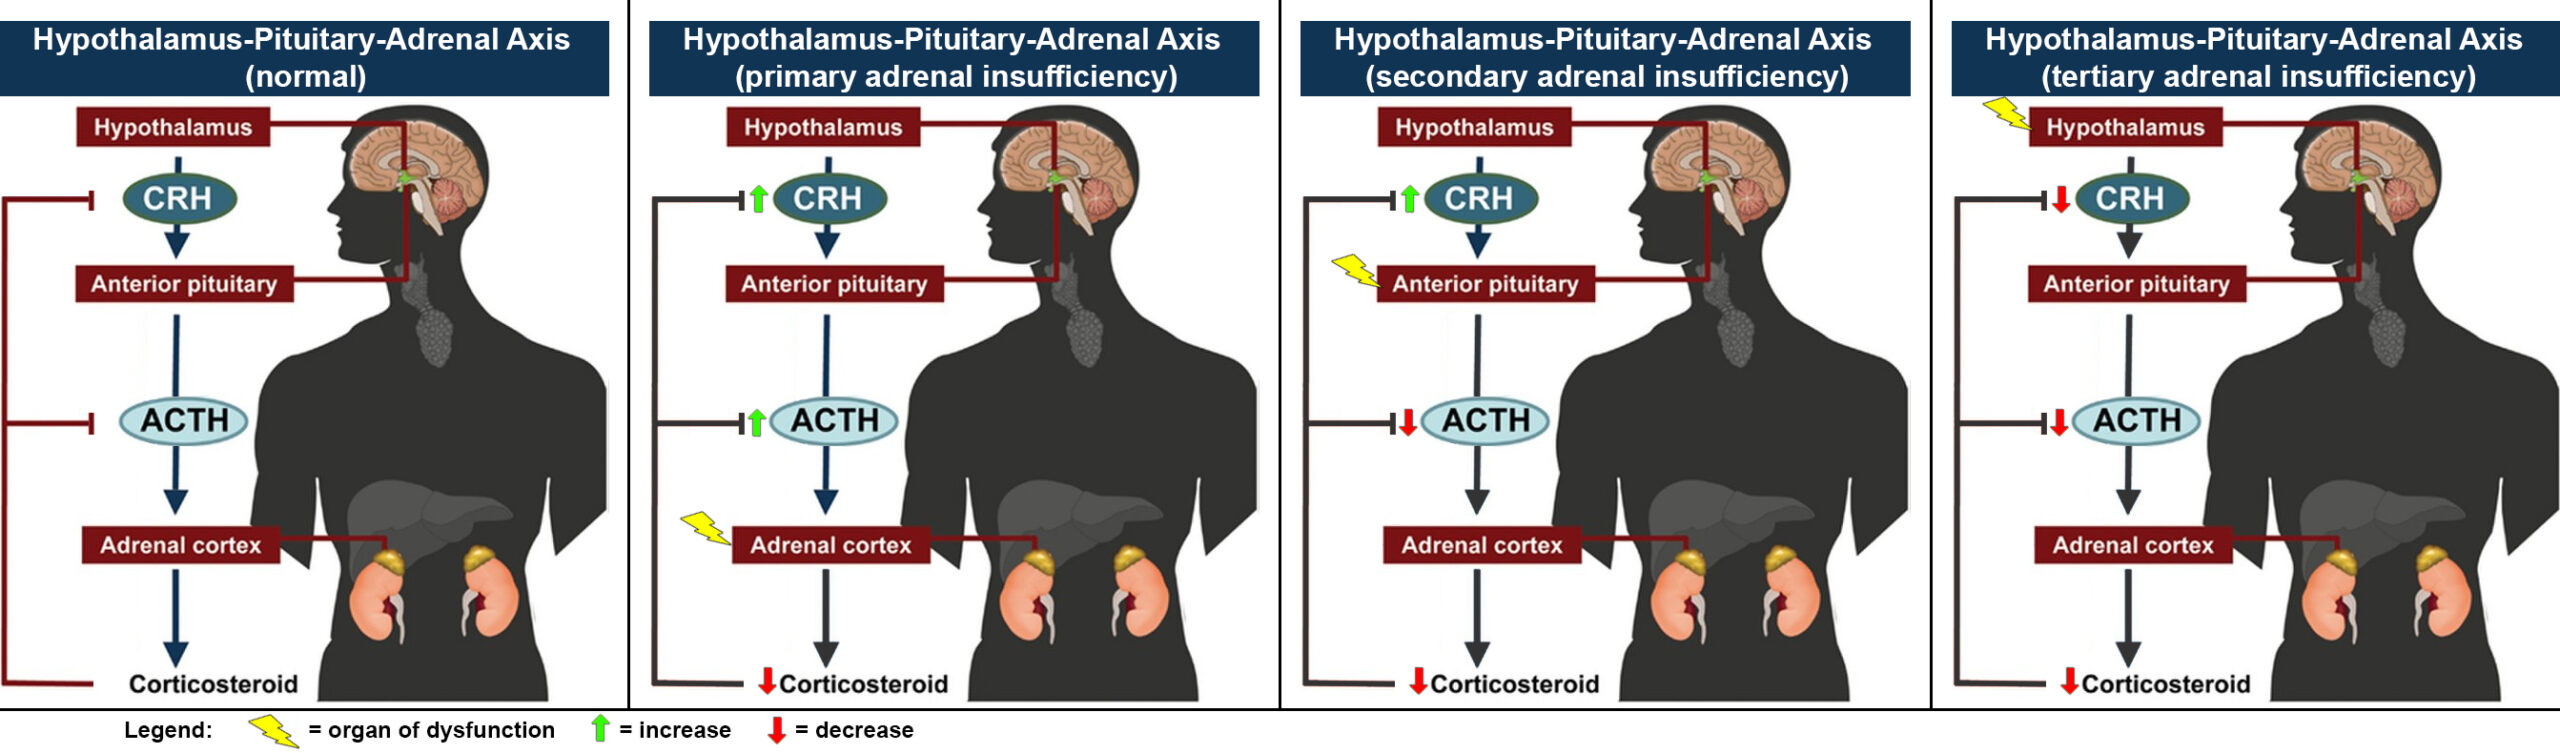
HPA axis in adrenal insufficiency. Source: Oddcomb / Wikimedia Commons, licensed under CC BY-SA 4.0.
What to notice
Detailed image description
Adrenal crisis is a clinical diagnosis requiring immediate empirical treatment. There is no single laboratory result or universally accepted biochemical definition that should be awaited before treatment.1–3
Immediate Assessment
- airway, breathing and circulation
- mental state and Glasgow Coma Scale
- blood pressure, heart rate, temperature, oxygen saturation and capillary refill
- bedside blood glucose
- fluid balance and urine output
- medication history, including oral, injected, inhaled, intranasal, topical and intra-articular glucocorticoids
- evidence of infection, trauma, bleeding or another precipitating illness.
Blood Tests
If this does not delay treatment, collect:
- serum cortisol and plasma ACTH before hydrocortisone
- full blood count
- electrolytes, urea, creatinine and glucose
- calcium and liver function tests
- venous or arterial blood gas, including lactate
- blood cultures and other microbiological samples when infection is suspected
- plasma renin and aldosterone if primary adrenal insufficiency is suspected, usually after acute stabilisation.
Typical abnormalities include hyponatraemia, hypoglycaemia and acute kidney injury. Hyperkalaemia is characteristic of mineralocorticoid deficiency in primary adrenal insufficiency but may be absent.
Hydrocortisone interferes with subsequent cortisol interpretation. Nevertheless, treatment must not be withheld to preserve diagnostic accuracy.
Confirming Adrenal Insufficiency
Once the patient is clinically stable, perform formal endocrine assessment if adrenal insufficiency was not previously established. The standard 250 microgram ACTH stimulation test measures cortisol at baseline and 30 or 60 minutes. Interpretation must use the local laboratory’s assay-specific threshold; the historically used peak cortisol threshold of approximately 500 nmol/L may not apply to newer assays.2,3
In confirmed cortisol deficiency:
- ACTH more than twice the upper limit of normal supports primary adrenal insufficiency.
- Low or inappropriately normal ACTH suggests secondary or tertiary disease.
- Renin and aldosterone help identify mineralocorticoid deficiency.
- Further investigation should determine the underlying adrenal or hypothalamic–pituitary cause.
Important Differential Diagnoses
| Differential | Distinguishing features |
|---|---|
| Septic shock | Infective source, elevated inflammatory markers and distributive shock; sepsis may also precipitate adrenal crisis, so both can coexist |
| Hypovolaemic shock | Haemorrhage or fluid loss without other evidence of cortisol deficiency |
| Cardiogenic shock | Chest pain, pulmonary oedema, electrocardiographic or echocardiographic abnormalities |
| Anaphylaxis | Acute allergen exposure, urticaria, angioedema or bronchospasm |
| Diabetic ketoacidosis | Hyperglycaemia, ketosis and high-anion-gap metabolic acidosis |
| Severe hypothyroidism | Hypothermia, bradycardia, hypoventilation and longstanding hypothyroid features |
| Acute abdominal or gastrointestinal disease | Localising abdominal findings; adrenal crisis may nevertheless mimic an acute abdomen |
Treatment
Treat suspected adrenal crisis immediately and simultaneously investigate the precipitating illness.1–3
Immediate Management
- Give hydrocortisone 100 mg intravenously or intramuscularly immediately.
- Begin rapid intravenous 0.9% sodium chloride, adjusted for haemodynamic status, comorbidities and the risk of fluid overload.
- Continue hydrocortisone at 200 mg over 24 hours by continuous intravenous infusion, or 50 mg intravenously or intramuscularly every six hours, until clinical recovery.
- Monitor blood pressure, heart rate, electrolytes, glucose, fluid balance and urine output.
- Correct hypoglycaemia promptly with intravenous glucose.
- Identify and treat the precipitating cause, including empirical antimicrobial therapy when sepsis is suspected.
- Escalate persistent shock to critical care for invasive monitoring and vasopressor support while continuing glucocorticoid and fluid replacement.
Do not wait for cortisol results or an ACTH stimulation test. In suspected adrenal crisis, immediate hydrocortisone is potentially lifesaving, while short-term emergency administration is unlikely to cause harm.1
At stress doses above approximately 50 mg of hydrocortisone per day, hydrocortisone usually provides sufficient mineralocorticoid activity. Additional fludrocortisone is therefore generally unnecessary during initial high-dose treatment.
After Stabilisation
Following clinical recovery:
- transition to oral glucocorticoid therapy under endocrinology guidance
- taper stress dosing according to the clinical course and precipitating illness
- commence or resume fludrocortisone when primary adrenal insufficiency with aldosterone deficiency is established and the hydrocortisone dose has returned towards physiological replacement
- investigate the underlying cause if adrenal insufficiency is newly diagnosed
- provide education and an emergency prevention plan before discharge.
Prevention
People with adrenal insufficiency or significant hypothalamic–pituitary–adrenal axis suppression should receive:
- written sick-day rules explaining when and how to increase glucocorticoids
- instructions to use parenteral hydrocortisone if vomiting prevents oral absorption
- an emergency hydrocortisone injection kit with practical training
- a steroid emergency card or medical alert identification
- advice to maintain an adequate supply of medication
- perioperative and procedural stress-dose planning
- education for family members or carers
- endocrinology follow-up after an adrenal crisis.1,4
Complications & Prognosis
Complications
Untreated or delayed treatment may cause:
- refractory shock
- severe hypoglycaemia
- seizures, coma or neurological injury
- acute kidney injury
- cardiac arrhythmia associated with hyperkalaemia
- aspiration or respiratory failure
- multiorgan failure
- death.
Treatment-related complications may include fluid overload, hyperglycaemia and electrolyte shifts, particularly in older people and those with cardiac or renal disease.
Prognosis
Clinical improvement in blood pressure, cognition, gastrointestinal symptoms and biochemical abnormalities is expected after adequate glucocorticoid and fluid replacement. Prognosis is worse when recognition or treatment is delayed, the precipitating illness is severe, or significant comorbidity is present.
A previous adrenal crisis identifies a person at increased risk of recurrence. Prevention depends on reliable access to medication, sick-day education, emergency injection training and appropriate glucocorticoid cover during illness and procedures.1
References
- National Institute for Health and Care Excellence. Adrenal insufficiency: identification and management [Internet]. London: NICE; 2024 [cited 2026 Aug 10]. Available from: https://www.nice.org.uk/guidance/ng243
- Society for Endocrinology. Adrenal crisis information [Internet]. Bristol: Society for Endocrinology [cited 2026 Aug 10]. Available from: https://www.endocrinology.org/clinical-practice/clinical-guidance/adrenal-crisis/
- Bornstein SR, Allolio B, Arlt W, Barthel A, Don-Wauchope A, Hammer GD, et al. Diagnosis and treatment of primary adrenal insufficiency: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. 2016;101(2):364–389. doi:10.1210/jc.2015-1710
- Beuschlein F, Else T, Bancos I, Hahner S, Hamidi O, van Hulsteijn L, et al. European Society of Endocrinology and Endocrine Society joint clinical guideline: diagnosis and therapy of glucocorticoid-induced adrenal insufficiency. J Clin Endocrinol Metab. 2024;109(7):1657–1683. doi:10.1210/clinem/dgae250