

Overview
Carpal tunnel syndrome (CTS) is a compressive neuropathy of the median nerve as it passes beneath the transverse carpal ligament at the wrist. It is the most common peripheral nerve entrapment syndrome and typically causes nocturnal paraesthesia, numbness or pain involving the thumb, index finger, middle finger and radial half of the ring finger. Advanced compression may cause persistent sensory loss, impaired dexterity, thenar weakness and muscle wasting.1
Clinically diagnosed CTS has an estimated prevalence of approximately 3.8% in the general adult population, although estimates vary according to the population and diagnostic definition used.2 Early recognition is important because prolonged severe compression can produce irreversible axonal loss and incomplete recovery after decompression.
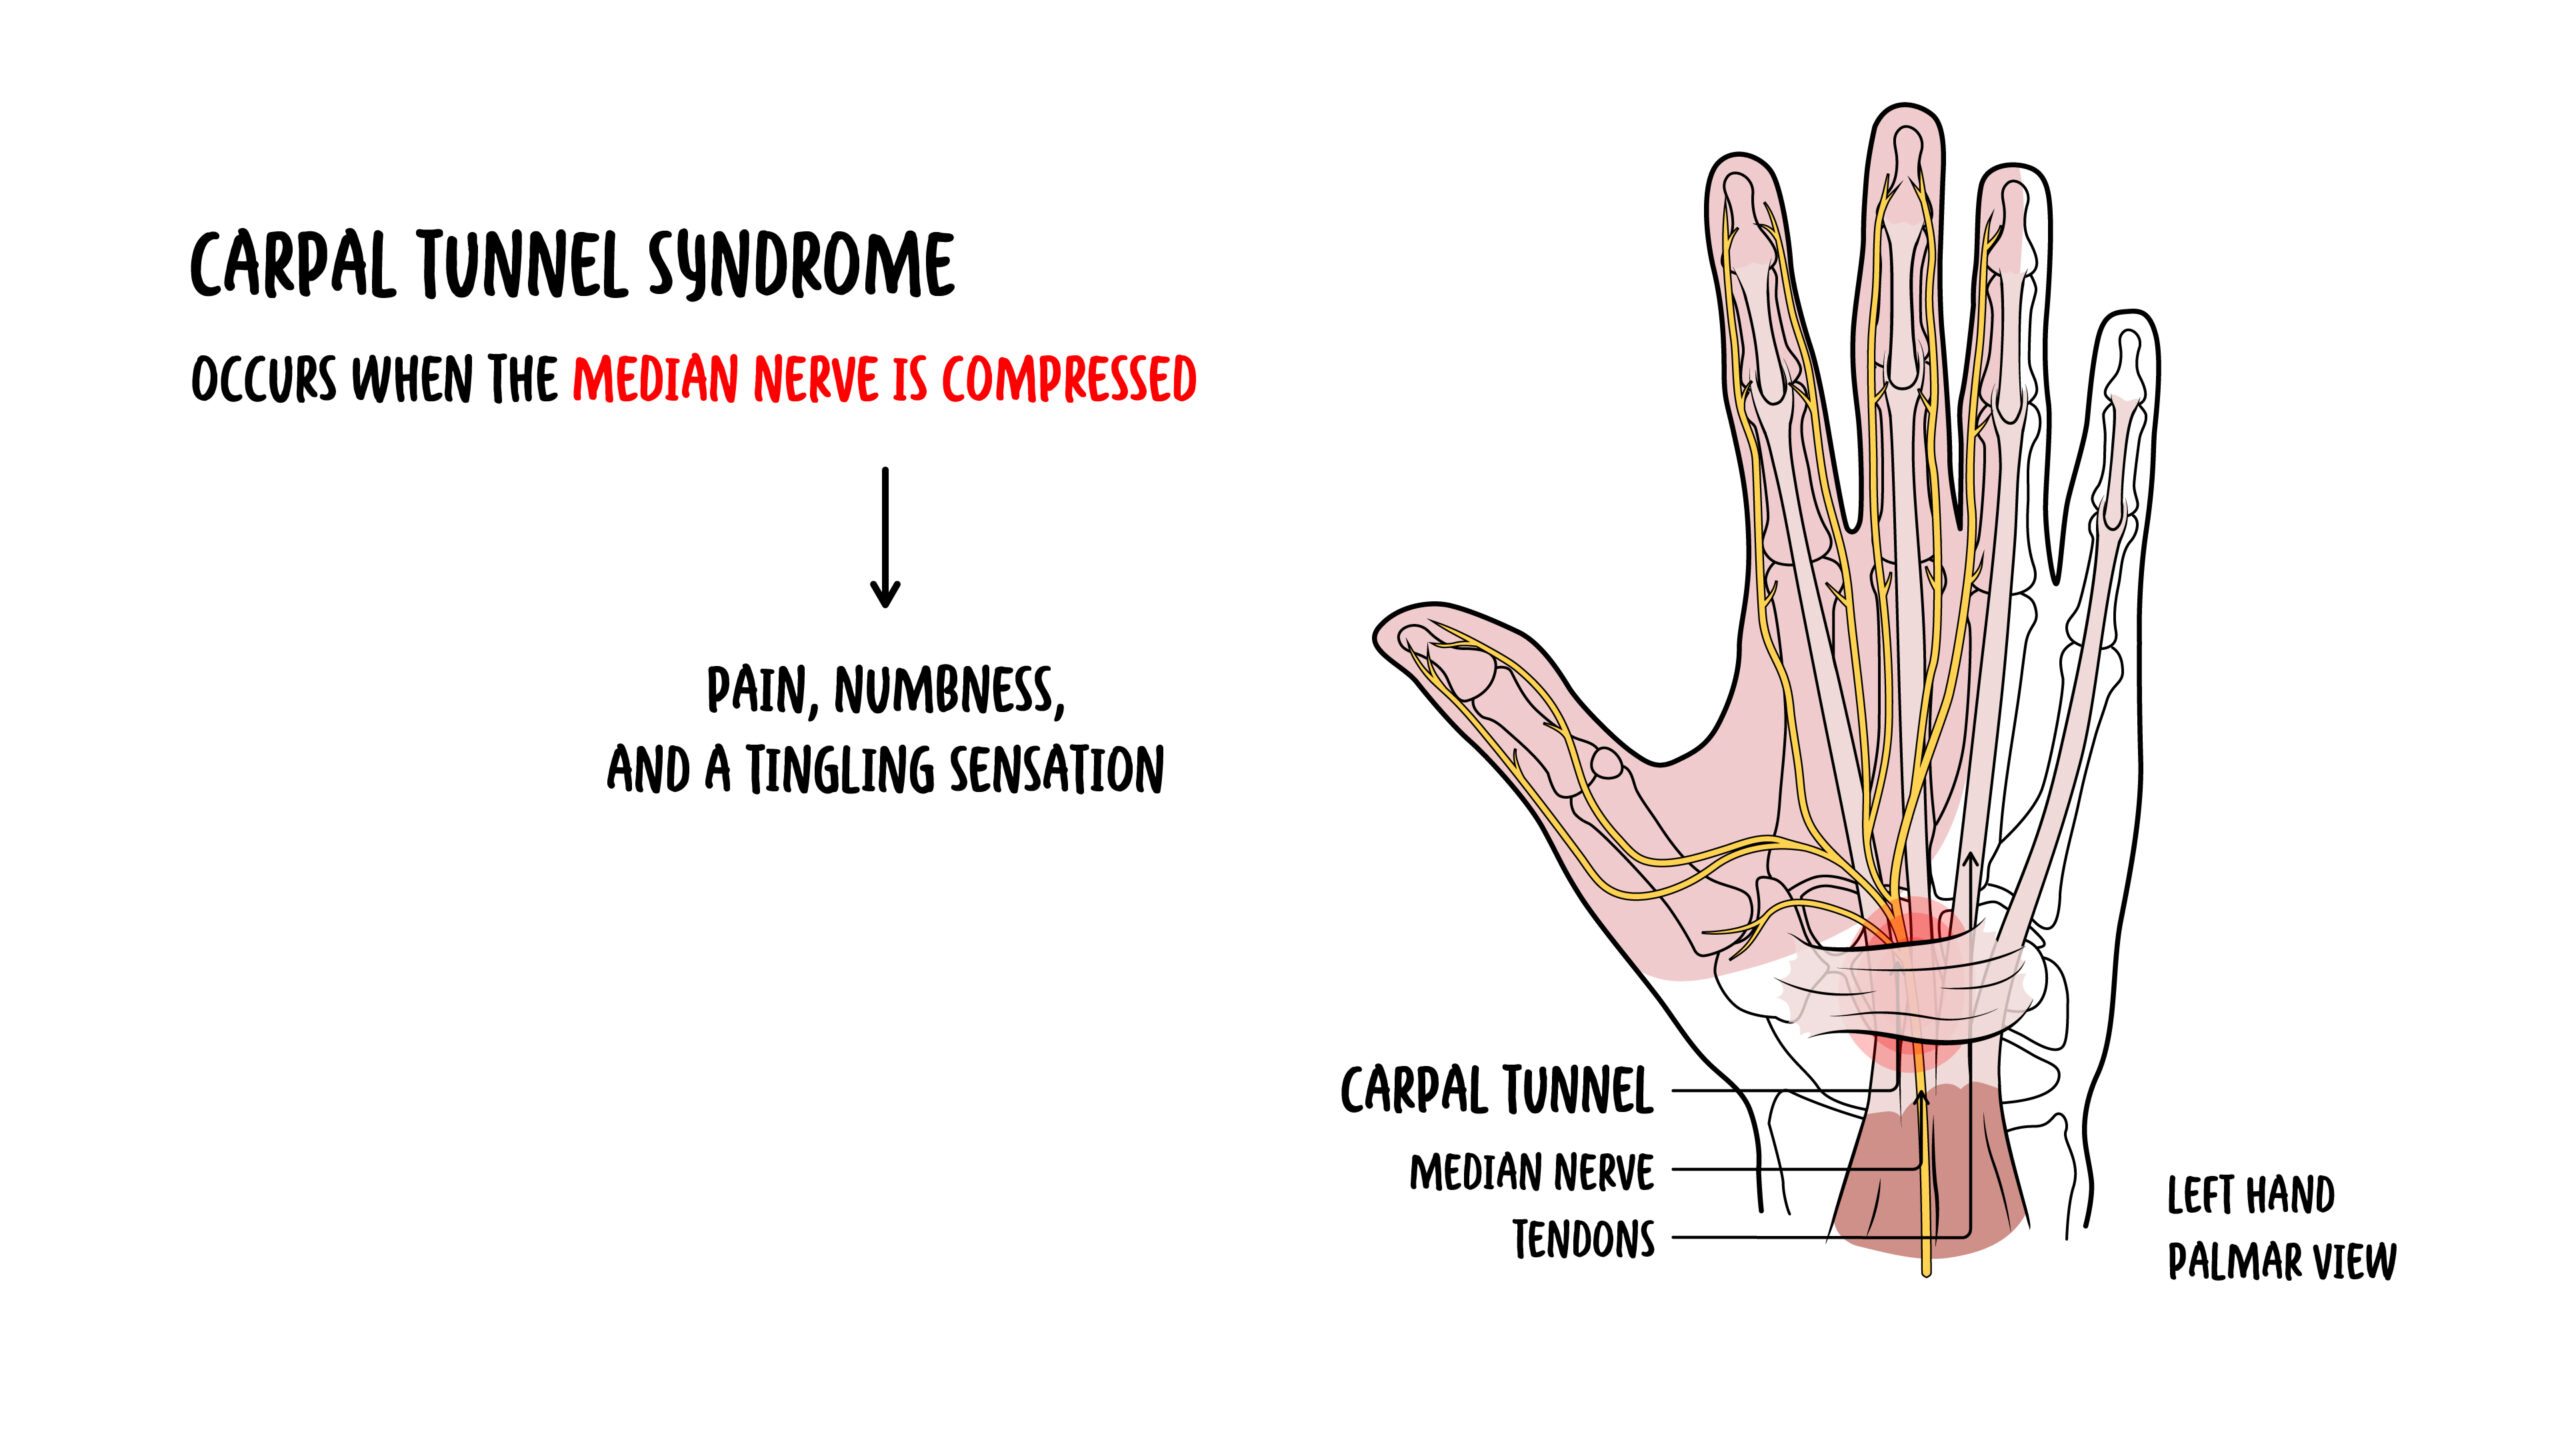
Definition
- Carpal tunnel syndrome
- A symptomatic compression neuropathy of the median nerve at the wrist.
- Median nerve
- A peripheral nerve supplying sensation to the palmar thumb, index finger, middle finger and radial half of the ring finger, as well as motor function to several thenar muscles.
- Carpal tunnel
- A rigid fibro-osseous passage at the wrist containing the median nerve and nine flexor tendons.
Anatomy & Physiology
The carpal tunnel is a narrow, relatively non-expandable passage formed by:
- Floor and walls: concave arch of the carpal bones.
- Roof: transverse carpal ligament, also called the flexor retinaculum.
- Contents: median nerve, four flexor digitorum superficialis tendons, four flexor digitorum profundus tendons and the flexor pollicis longus tendon.
Within the hand, the median nerve provides:
- Sensation to the palmar surface of the thumb, index finger, middle finger and radial half of the ring finger.
- Motor supply to the abductor pollicis brevis, opponens pollicis and superficial head of flexor pollicis brevis through the recurrent motor branch.
- Fine sensory discrimination required for precise hand function.
The palmar cutaneous branch of the median nerve arises proximal to the carpal tunnel and travels superficial to the transverse carpal ligament. Sensation over the thenar eminence is therefore usually preserved in isolated CTS.1
Numbness over the thenar eminence suggests that the median nerve lesion may be proximal to the carpal tunnel, because the palmar cutaneous branch does not pass through the tunnel.
Aetiology & Risk Factors
Aetiology
Most cases are idiopathic, without a single identifiable lesion. CTS develops when increased pressure within the carpal tunnel impairs median nerve function.
Recognised secondary causes include:
- Reduced tunnel dimensions: distal radius fracture or malunion, carpal dislocation, osteoarthritis and other structural deformities.
- Increased tunnel contents: flexor tenosynovitis, inflammatory arthritis, ganglion cysts, tumours or anomalous muscles.
- Fluid retention or tissue swelling: pregnancy, hypothyroidism and renal failure.
- Tissue deposition: amyloidosis, including dialysis-related β₂-microglobulin deposition and transthyretin amyloidosis.
- Abnormal tissue growth: acromegaly.
- Direct injury: wrist trauma, haemorrhage or, rarely, infection.
Acute CTS is uncommon but may follow a distal radius fracture, crush injury, burn, haemorrhage or rapidly increasing compartment pressure. It requires urgent surgical assessment because prolonged high pressure can cause irreversible nerve injury.
Risk Factors
Factors associated with an increased likelihood of CTS include:
- Female sex.
- Middle and older age.
- Obesity.
- Pregnancy.
- Diabetes mellitus.
- Rheumatoid arthritis and other inflammatory tenosynovial disorders.
- Hypothyroidism.
- Chronic kidney disease and haemodialysis.
- Family history or anatomical predisposition.
- Occupational exposure to forceful gripping, highly repetitive hand activity or vibrating tools.1,3
High keyboard use alone has not been shown reliably to cause CTS and should not automatically be assumed to be the explanation for symptoms.4
Bilateral CTS may occasionally be an early manifestation of systemic disease. Consider diabetes, hypothyroidism, inflammatory arthritis or amyloidosis when the presentation is atypical, severe, recurrent or accompanied by other systemic features.
Pathophysiology
CTS results from a mismatch between the volume of the tunnel contents and the available space within the rigid carpal tunnel.
The typical sequence is:
- Increased tunnel pressure compresses the median nerve and its intraneural blood vessels.
- Venous outflow is impaired, producing endoneurial oedema and further increasing pressure.
- Intermittent ischaemia and mechanical deformation initially cause focal demyelination and slowed nerve conduction.
- Continued compression produces axonal injury.
- Advanced disease causes persistent sensory loss, denervation weakness and thenar muscle atrophy.1,3
Wrist flexion and extension further reduce the functional space within the tunnel. This helps explain why symptoms are commonly provoked by sustained wrist positions during sleep, driving, reading or holding a telephone.
Sensory fibres are usually affected before motor fibres. Intermittent nocturnal paraesthesia therefore commonly precedes fixed numbness, weakness and thenar wasting.
Clinical Manifestations
Symptoms
Typical symptoms include:
- Numbness, tingling, burning or pain affecting the thumb, index finger, middle finger and radial half of the ring finger.
- Nocturnal symptoms that wake the patient from sleep.
- Relief after shaking or flicking the hand—the flick sign.
- Symptoms triggered by driving, holding a telephone, reading or sustained wrist flexion.
- Pain radiating into the wrist or forearm; radiation above the elbow may occur, but neck pain suggests an alternative or additional diagnosis.
- Subjective hand swelling despite no visible swelling.
- Reduced dexterity, clumsiness or dropping objects.
- Difficulty with buttons, handwriting, opening containers or precision pinch.
- Persistent numbness in more advanced disease.
Although the sensory disturbance is classically confined to the median distribution, patients may describe symptoms involving the entire hand. The overall pattern, rather than a rigid sensory boundary, should guide interpretation.3
Clinical Examination
Provocative manoeuvres include:
- Phalen test: sustained wrist flexion reproduces median-distribution paraesthesia.
- Tinel sign: percussion over the carpal tunnel produces tingling in the median distribution.
- Durkan carpal compression test: direct pressure over the carpal tunnel reproduces symptoms.
No single provocative test is sufficiently accurate to confirm or exclude CTS. Findings should be interpreted together with the symptom distribution, nocturnal symptoms and neurological examination.3,4
Features suggesting advanced disease include:
- Constant numbness.
- Impaired two-point discrimination.
- Weak thumb abduction or opposition.
- Thenar atrophy.
- Loss of fine motor control.
Thenar weakness or atrophy is a late finding and suggests significant motor axonal injury. Do not delay specialist assessment while repeatedly trialling conservative therapy.
Diagnosis
CTS is primarily a clinical diagnosis, based on a characteristic history and examination. A structured clinical tool such as the CTS-6 can support diagnosis and may avoid routine electrodiagnostic testing in patients with a typical presentation.4,5
The CTS-6 combines six findings:
- Numbness predominantly or exclusively in the median nerve distribution.
- Nocturnal numbness.
- Thenar weakness or atrophy.
- Positive Phalen test.
- Positive Tinel sign over the carpal tunnel.
- Reduced two-point discrimination.
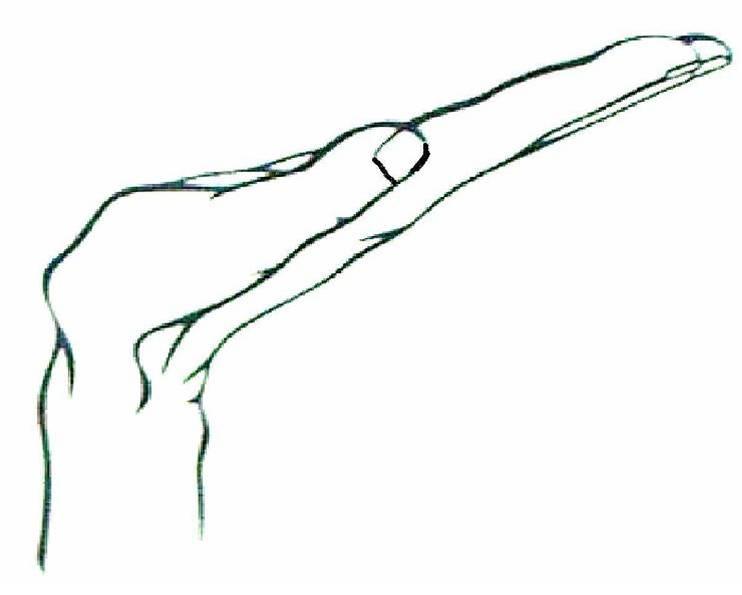
Phalen manoeuvre: sustained wrist flexion may reproduce paraesthesia in the median nerve distribution. Phalen manoeuvre illustration by Dr Harry Gouvas, via Wikimedia Commons.
What to notice
Detailed image description
Source page: https://commons.wikimedia.org/wiki/File:Phalen_maneuver.jpg Original asset: https://upload.wikimedia.org/wikipedia/commons/9/9b/Phalen_maneuver.jpg Creator: Dr Harry Gouvas Licence: Attribution-only licence; reuse, commercial use and derivative works permitted with attribution. Attribution: Phalen manoeuvre illustration by Dr Harry Gouvas, via Wikimedia Commons. Modifications: None. Rights verified: 2026-08-26.
Nerve Conduction Studies and Electromyography
Electrodiagnostic testing is not required routinely when the clinical diagnosis is clear. It is most useful when:
- The diagnosis is uncertain or the symptoms are atypical.
- Symptoms may reflect cervical radiculopathy, proximal median neuropathy, polyneuropathy or another entrapment neuropathy.
- There is persistent numbness, weakness or thenar atrophy.
- Objective assessment of physiological severity is needed.
- Surgery is being considered and confirmation or baseline severity would affect the decision.
Nerve conduction studies typically demonstrate slowed median sensory or motor conduction across the wrist. Electromyography can identify axonal loss or denervation in median-innervated thenar muscles and may identify an alternative proximal lesion. A normal study does not completely exclude clinically suspected mild CTS.3,5
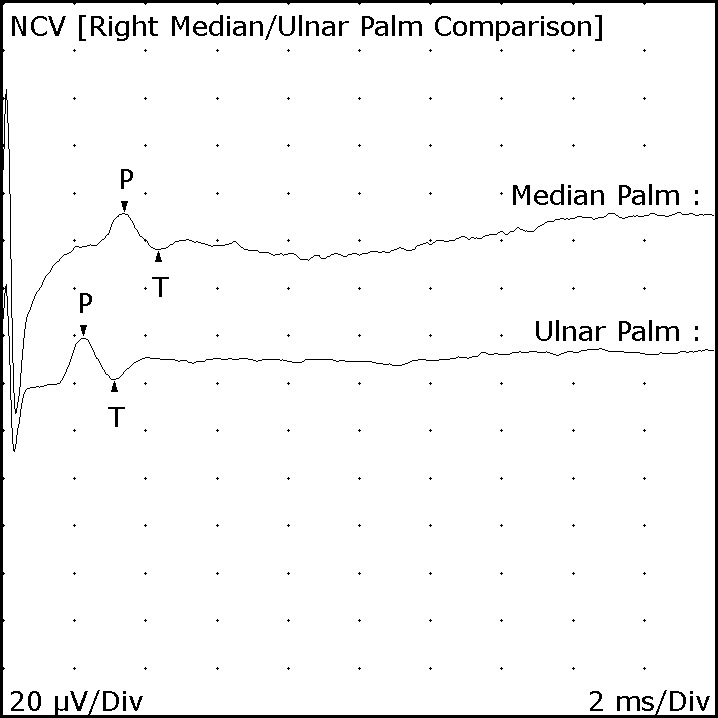
Transcarpal median–ulnar comparison demonstrating delayed median peak latency, supporting carpal tunnel syndrome. Transcarpal median–ulnar comparison waveforms by Argarrett, CC BY-SA 4.0, via Wikimedia Commons.
What to notice
Detailed image description
Source page: https://commons.wikimedia.org/wiki/File:Transcarpal_median-ulnar_palm_comparison_NCS_waveforms.png Original asset: https://upload.wikimedia.org/wikipedia/commons/1/14/Transcarpal_median-ulnar_palm_comparison_NCS_waveforms.png Creator: Argarrett Licence: Creative Commons Attribution-ShareAlike 4.0 International (CC BY-SA 4.0). Attribution: Transcarpal median–ulnar comparison waveforms by Argarrett, CC BY-SA 4.0, via Wikimedia Commons. Modifications: None. Rights verified: 2026-08-26.
Ultrasound
Median nerve ultrasound is a useful alternative or complementary test when:
- Electrodiagnostic testing is unavailable, poorly tolerated or inconclusive.
- A structural cause such as a cyst, tumour, tenosynovitis or anatomical variant is suspected.
- Visualisation of median nerve morphology would assist procedural planning.
Typical findings include median nerve enlargement at the tunnel inlet, altered echotexture and flattening within the tunnel. Diagnostic thresholds vary with technique and population; ultrasound measurements should not be interpreted in isolation.1,3
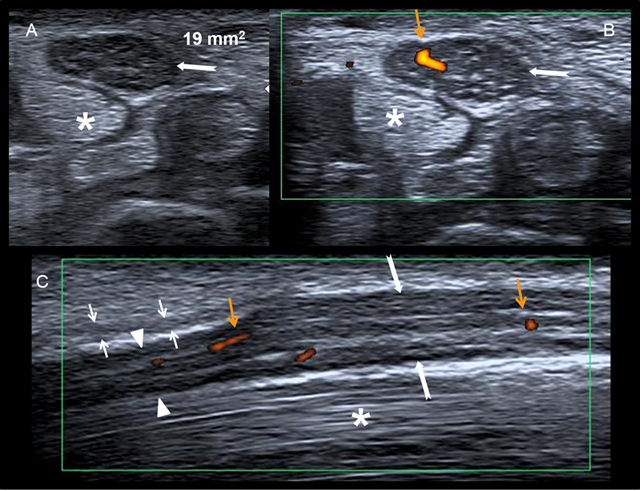
Ultrasound in carpal tunnel syndrome showing proximal median-nerve enlargement, flattening beneath the flexor retinaculum and intraneural hyperaemia. Figure reproduced from Meyer P et al., licensed under CC BY 4.0.
What to notice
Detailed image description
Source page: https://jbsr.be/articles/10.5334/jbsr.1354 Original asset: https://storage.googleapis.com/jnl-up-j-jbsr-files/journals/1/articles/1354/submission/proof/1354-10-9838-1-17-20180131.jpg Creator: Meyer P et al. Licence: Creative Commons Attribution 4.0 International (CC BY 4.0). Attribution: Figure reproduced from Meyer P et al., licensed under CC BY 4.0. Modifications: None. Publication: Meyer P, Lintingre PF, Pesquer L, Poussange N, Silvestre A, Dallaudière B. The median nerve at the carpal tunnel … and elsewhere. J Belg Soc Radiol. 2018;102(1):17. doi:10.5334/jbsr.1354. Rights verified: 2026-08-26.
Other Investigations
Routine MRI is not recommended for typical CTS. It adds little diagnostic value compared with clinical assessment, electrodiagnostic testing or ultrasound.5
Blood tests should be targeted to the clinical context rather than ordered routinely. Consider:
- HbA1c or fasting glucose when diabetes is suspected or unknown.
- Thyroid-stimulating hormone when symptoms or history suggest hypothyroidism.
- Inflammatory investigations when inflammatory arthritis or tenosynovitis is suspected.
- Amyloidosis assessment only when supported by features such as bilateral recurrent CTS, cardiomyopathy, autonomic neuropathy or other systemic manifestations.
Important Differentials
| Differential diagnosis | Distinguishing features |
|---|---|
| Cervical radiculopathy | Neck pain, dermatomal sensory loss, reflex change or weakness involving muscles outside the median nerve distribution |
| Pronator syndrome | Proximal volar forearm pain, sensory disturbance including the thenar eminence and symptoms provoked by forearm activity |
| Anterior interosseous neuropathy | Pure motor deficit affecting thumb–index pinch without sensory loss |
| Ulnar neuropathy | Paraesthesia involving the little finger and ulnar half of the ring finger, with ulnar-innervated muscle weakness |
| Generalised peripheral neuropathy | Bilateral length-dependent sensory symptoms, usually also affecting the feet |
| Thumb carpometacarpal osteoarthritis | Localised basal-thumb pain, tenderness and pain with grind testing rather than median-distribution paraesthesia |
| De Quervain tenosynovitis | Radial styloid pain and tenderness aggravated by thumb movement, without neurological symptoms |
A positive Phalen or Tinel test does not establish CTS by itself. Diagnostic confidence comes from the combination of a compatible sensory pattern, nocturnal symptoms, examination findings and the absence of a better alternative explanation.
Treatment
Treatment depends on symptom severity, duration, functional impairment, evidence of axonal loss and whether a reversible secondary cause is present.
Address Contributing Factors
- Treat active inflammatory arthritis or flexor tenosynovitis.
- Optimise diabetes and thyroid disease where relevant.
- Modify activities involving prolonged wrist flexion, forceful gripping or vibrating tools.
- Review workplace technique and equipment when symptoms are task-related.
- Manage an underlying structural lesion when identified.
Conservative Treatment
Conservative treatment is appropriate for intermittent or mild-to-moderate CTS without thenar weakness, atrophy or evidence of significant axonal loss.
Neutral-position wrist splint
- Wear at night to prevent sustained wrist flexion or extension.
- It is inexpensive, non-invasive and particularly useful for nocturnal symptoms.
- Daytime use may be considered for clearly provoking activities but can interfere with function.
Local corticosteroid injection
- Can provide short-term symptom improvement.
- May be considered when splinting is inadequate, temporary relief is required or surgery is not currently appropriate.
- It does not provide reliable long-term disease control and repeated injections should not replace definitive assessment in progressive disease.5
- Use careful anatomical technique because inadvertent intraneural injection can injure the median nerve.
Simple analgesics may help coexisting musculoskeletal pain but do not reverse median nerve compression. Evidence does not support routinely using oral corticosteroids, gabapentinoids, therapeutic ultrasound, laser therapy, acupuncture or nutritional supplements as durable disease-modifying treatment.5
Surgical Treatment
Carpal tunnel release divides the transverse carpal ligament and decompresses the median nerve.
Night pain and paraesthesia often improve rapidly after decompression. Recovery of fixed numbness and thenar weakness is slower and may be incomplete when axonal loss has been longstanding.
Conservative treatment is most appropriate for mild-to-moderate disease without motor deficit. Persistent numbness, thenar weakness, muscle wasting or severe electrodiagnostic abnormalities favour timely surgical decompression.
Complications & Prognosis
Complications
Untreated or advanced CTS may cause:
- Persistent median-distribution numbness.
- Impaired fine touch and two-point discrimination.
- Thenar weakness and atrophy.
- Reduced thumb opposition and pinch strength.
- Loss of dexterity and occupational function.
- Permanent axonal loss.
Possible complications after carpal tunnel release include:
- Scar or pillar pain.
- Wound infection.
- Injury to the median nerve or its branches.
- Persistent symptoms due to incomplete release or incorrect diagnosis.
- Recurrent symptoms from fibrosis or recurrent compression.
- Complex regional pain syndrome, although uncommon.
Persistent or recurrent symptoms after surgery should prompt reassessment of the original diagnosis, completeness of release and possible proximal or generalised neuropathy.1
Prognosis
Most patients improve with appropriate treatment. Nocturnal paraesthesia and pain generally recover more predictably than established sensory loss or motor weakness.
Less complete recovery is associated with:
- Long symptom duration.
- Constant preoperative numbness.
- Thenar atrophy or weakness.
- Severe axonal loss or absent nerve responses.
- Advanced age.
- Diabetes or coexisting generalised neuropathy.
- Incorrect diagnosis or an untreated proximal lesion.1,3
Pregnancy-associated CTS often improves after delivery, although persistent symptoms still require reassessment. Recurrence can occur, particularly when an underlying systemic or structural contributor remains active.
References
- Dahlin LB, Zimmerman M, Calcagni M, Hundepool CA, van Alfen N, Chung KC. Carpal tunnel syndrome. Nat Rev Dis Primers. 2024;10(1):37. doi:10.1038/s41572-024-00521-1
- Atroshi I, Gummesson C, Johnsson R, Ornstein E, Ranstam J, Rosén I. Prevalence of carpal tunnel syndrome in a general population. JAMA. 1999;282(2):153–158. doi:10.1001/jama.282.2.153
- Padua L, Cuccagna C, Giovannini S, Coraci D, Pelosi L, Loreti C, et al. Carpal tunnel syndrome: updated evidence and new questions. Lancet Neurol. 2023;22(3):255–267. doi:10.1016/S1474-4422(22)00432-X
- Graham B, Regehr G, Naglie G, Wright JG. Development and validation of diagnostic criteria for carpal tunnel syndrome. J Hand Surg Am. 2006;31(6):919–924.
- American Academy of Orthopaedic Surgeons. Management of carpal tunnel syndrome: evidence-based clinical practice guideline [Internet]. Rosemont (IL): American Academy of Orthopaedic Surgeons; 2024 [cited 2026 Aug 26]. Available from: https://www.aaos.org/cts2cpg
- Meyer P, Lintingre PF, Pesquer L, Poussange N, Silvestre A, Dallaudière B. The median nerve at the carpal tunnel … and elsewhere. J Belg Soc Radiol. 2018;102(1):17. doi:10.5334/jbsr.1354
- Bland JDP. A neurophysiological grading scale for carpal tunnel syndrome. Muscle Nerve. 2000;23(8):1280–1283.