

Overview
An acute exacerbation of chronic obstructive pulmonary disease (AECOPD) is an acute worsening of dyspnoea and/or cough and sputum over fewer than 14 days, often associated with increased airway inflammation triggered by infection, pollution or another insult.1 It represents a clinically important change from the patient’s usual day-to-day variation and may require additional medication, urgent assessment or hospital admission.2
Exacerbations accelerate functional decline, impair quality of life and increase the risk of subsequent exacerbations, hospitalisation and death.1 Severe breathlessness, altered mental state, haemodynamic instability, cyanosis or features of acute respiratory failure require urgent escalation.
Definition
- Acute exacerbation of COPD
- An acute worsening of dyspnoea and/or cough and sputum, usually developing over fewer than 14 days, which may require a change in treatment.
- Dynamic hyperinflation
- Progressive air trapping caused by incomplete expiration before the next breath begins.
- Acute hypercapnic respiratory failure
- Acute ventilatory failure associated with an increased arterial carbon dioxide tension, often accompanied by respiratory acidosis.
- Non-invasive ventilation
- Positive-pressure ventilatory support delivered through a mask without an endotracheal tube.
Aetiology & Risk Factors
Aetiology
Common precipitants include:
- Viral respiratory infection, including influenza, respiratory syncytial virus and SARS-CoV-2
- Bacterial respiratory infection
- Exposure to air pollution, smoke or occupational irritants
- Interruption of maintenance inhalers, incorrect inhaler technique or poor adherence
- Sedative or opioid exposure contributing to hypoventilation
- An identifiable trigger may not be found
Conditions that can mimic or aggravate an exacerbation include pneumonia, acute heart failure, pulmonary embolism, pneumothorax, pleural effusion, acute coronary syndrome and cardiac arrhythmia.1
Risk Factors
Factors associated with an increased risk of exacerbation or severe disease include:
- Previous exacerbations, particularly a recent hospital admission
- More severe airflow obstruction
- Persistent symptoms and impaired functional status
- Ongoing smoking or irritant exposure
- Older age, frailty or poor nutritional status
- Cardiovascular disease, bronchiectasis, anxiety or other significant comorbidity
- Long-term oxygen use
- Inadequate maintenance therapy, poor adherence or incorrect inhaler technique
- Limited social support or difficulty accessing medical care
Pathophysiology
A trigger increases airway inflammation, mucus production and bronchial smooth-muscle tone. The resulting airway narrowing and mucus obstruction increase expiratory flow limitation. Expiration becomes prolonged and may remain incomplete when respiratory rate rises, producing dynamic hyperinflation and intrinsic positive end-expiratory pressure.
Dynamic hyperinflation increases the work of breathing and places the inspiratory muscles at a mechanical disadvantage. Ventilation–perfusion mismatch causes hypoxaemia. Increasing respiratory muscle fatigue and reduced alveolar ventilation may cause carbon dioxide retention and respiratory acidosis.1
A patient may become markedly breathless without a large new fall in spirometric airflow because tachypnoea shortens expiratory time. Progressive air trapping and dynamic hyperinflation increase the work of breathing and can drive acute ventilatory failure.
Clinical Manifestations
Typical symptoms are an acute increase in:
- Dyspnoea
- Cough
- Sputum volume
- Sputum purulence
- Wheeze or chest tightness
- Exercise limitation
Systemic features may include fever, fatigue, reduced appetite and sleep disturbance. Headache, somnolence, confusion or reduced consciousness may indicate hypercapnia.
Clinical examination
- Tachypnoea and increased work of breathing
- Accessory-muscle use or pursed-lip breathing
- Prolonged expiration
- Reduced air entry, wheeze or coarse crackles
- Tachycardia
- Hypoxaemia or cyanosis
- Inability to speak in full sentences
- Asterixis or altered mental state in hypercapnia
- Peripheral oedema or raised jugular venous pressure when right-heart dysfunction or fluid overload coexists
A quiet chest, exhaustion, paradoxical breathing, deteriorating consciousness or haemodynamic instability suggests impending respiratory arrest.
Diagnosis & Investigations
AECOPD is primarily a clinical diagnosis based on an acute change from baseline dyspnoea, cough and/or sputum that exceeds normal daily variation.2 Assessment must determine severity, identify the precipitant and exclude important alternative diagnoses.
Initial assessment
Assess:
- Airway patency, respiratory effort and ability to speak
- Respiratory rate, oxygen saturation, heart rate, blood pressure, temperature and mental state
- Baseline symptoms, usual oxygen saturation and previous blood gas results
- Previous exacerbations, intensive care admissions or ventilation
- Current inhalers, adherence, recent antibiotics and systemic corticosteroids
- Comorbidities and treatment-escalation preferences
Investigations
Investigations should be guided by severity and the differential diagnosis:
- Pulse oximetry
- Arterial or venous blood gas
- Chest radiograph: evaluate for pneumonia, pneumothorax, pulmonary oedema, pleural effusion or another structural cause.
- Electrocardiogram
- Full blood count and biochemical profile: assess infection, anaemia, electrolyte disturbance and renal function.
- Respiratory viral testing
- Sputum microscopy and culture: consider in severe disease, treatment failure, frequent exacerbations, bronchiectasis, recent antibiotic exposure or risk of resistant organisms.
- Troponin, natriuretic peptide or CT pulmonary angiography: only when supported by the clinical differential.
Spirometry is not required to diagnose an acute exacerbation and is often unreliable during severe acute illness. If COPD has never been objectively confirmed, perform post-bronchodilator spirometry after recovery.
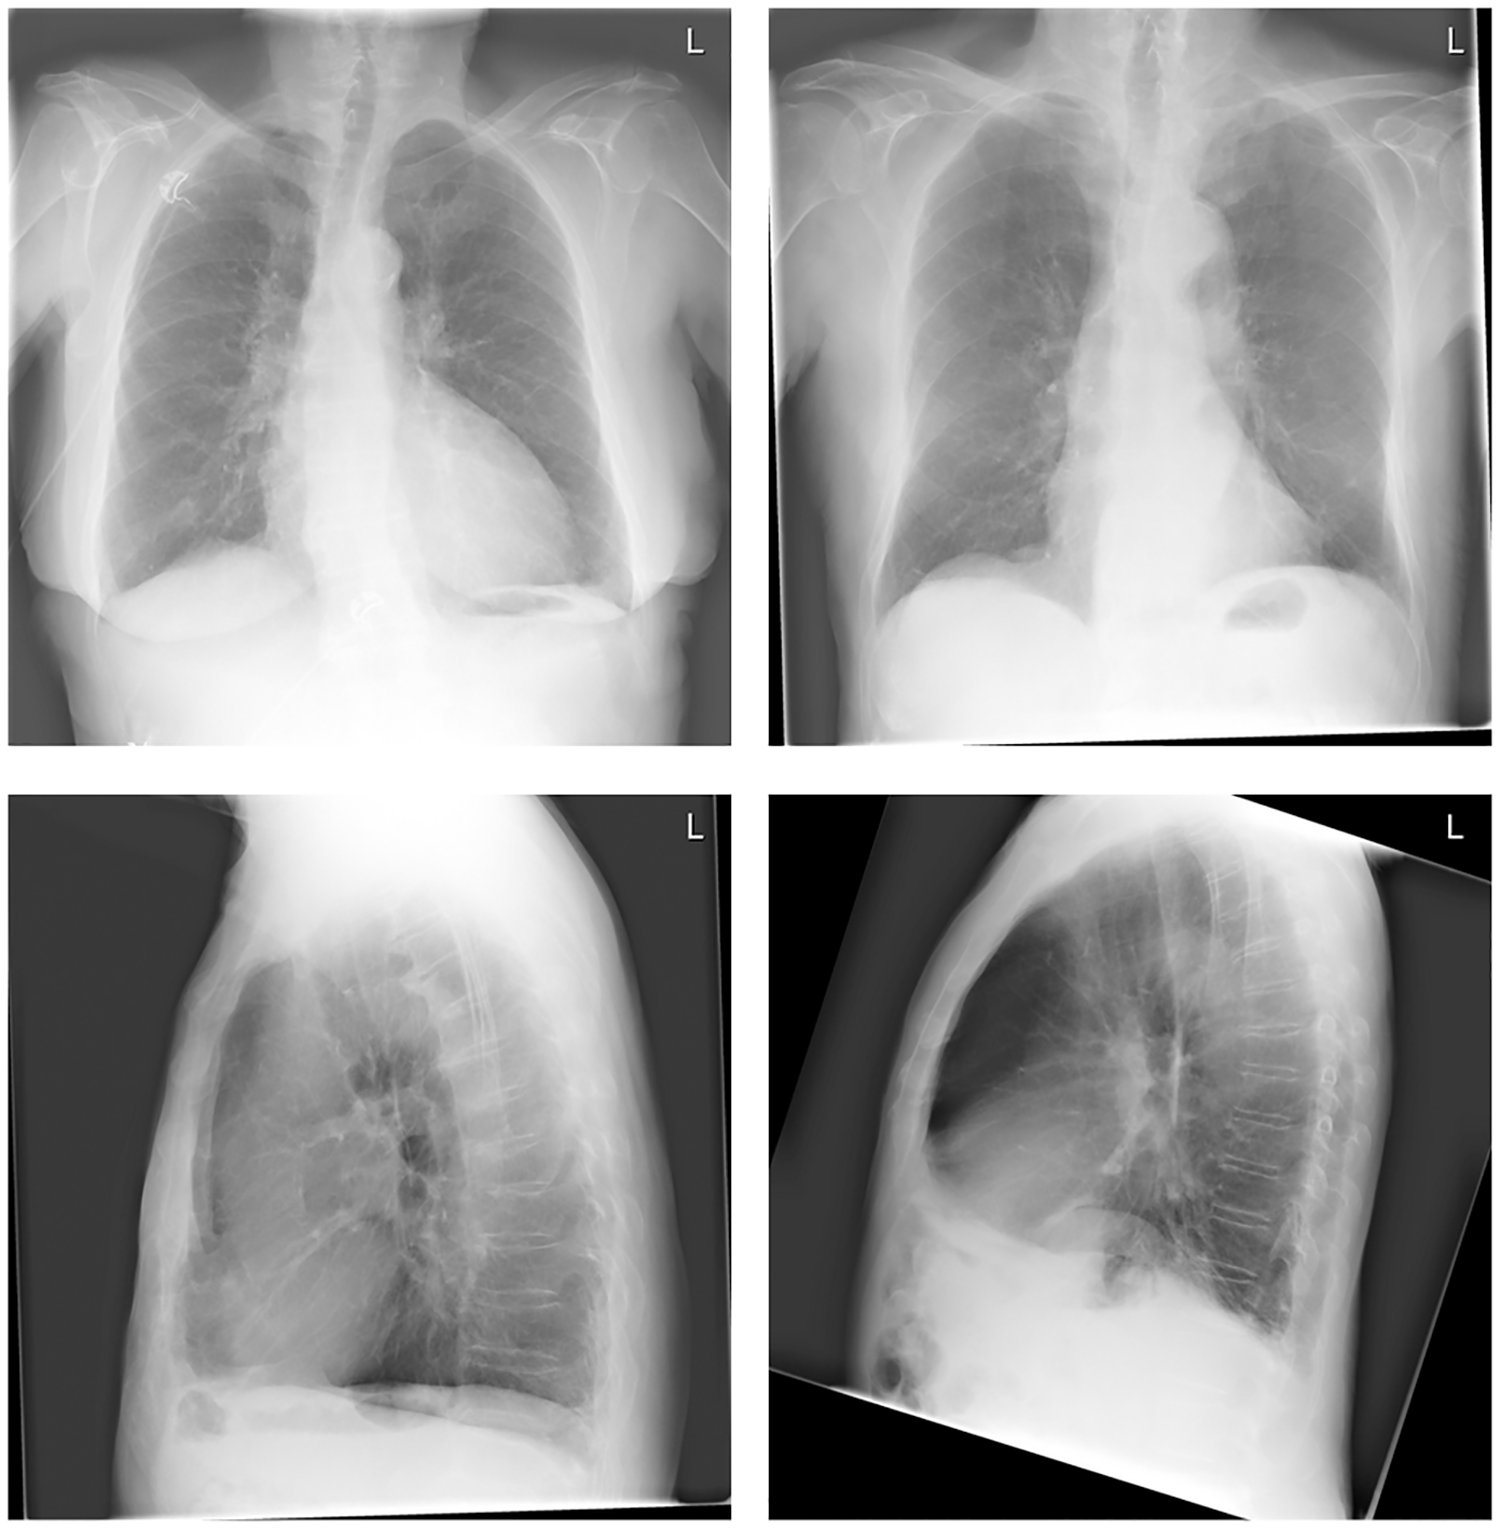
Chest radiographs demonstrating features of emphysema, including flattened diaphragms, increased lung lucency and an enlarged retrosternal airspace. Chest radiography may support assessment of COPD and help identify complications or alternative diagnoses, but does not independently diagnose an acute exacerbation. Image adapted from Çallı et al. (2022), licensed under CC BY.
What to notice
Detailed image description
Source: https://pmc.ncbi.nlm.nih.gov/articles/PMC9333227/ | Figure 1 | Licence: Creative Commons Attribution (CC BY) | Direct asset: https://journals.plos.org/plosone/article/figure/image?size=large&id=info:doi/10.1371/journal.pone.0267539.g001
| Feature | AECOPD | Important alternative |
|---|---|---|
| Increased dyspnoea, cough and sputum | Typical | May also occur with pneumonia |
| Focal crackles, fever or new infiltrate | Not required | Pneumonia |
| Orthopnoea, oedema or pulmonary congestion | May coexist | Acute heart failure |
| Sudden pleuritic pain, haemoptysis or disproportionate hypoxaemia | Atypical | Pulmonary embolism |
| Unilateral absent breath sounds | Atypical | Pneumothorax |
| Chest pain, ischaemic ECG change or dynamic troponin rise | Atypical | Acute coronary syndrome |
Do not attribute every episode of acute breathlessness in a person with COPD to an exacerbation. Abrupt onset, focal chest findings, disproportionate hypoxaemia, chest pain or poor response to initial treatment should prompt active investigation for a mimic or concurrent diagnosis.
Treatment
Treatment depends on severity, comorbidity and the available level of monitoring.
Immediate management
- Position the patient upright and assess airway, breathing and circulation.
- Give controlled supplemental oxygen for hypoxaemia, generally targeting an oxygen saturation of 88–92% while blood gas results are obtained.2
- Repeat blood gases after oxygen initiation or escalation when hypercapnic respiratory failure is possible.
- Use inhaled short-acting bronchodilators as first-line therapy, usually a short-acting beta₂-agonist with or without a short-acting muscarinic antagonist.2
- Prefer a metered-dose inhaler with spacer when the patient can use it effectively; use nebulised therapy when clinically necessary.
- Treat the precipitating condition and manage relevant comorbidities.
Uncontrolled high-concentration oxygen can worsen hypercapnia in susceptible patients. Treat hypoxaemia promptly, but titrate oxygen to a target saturation of 88–92% and reassess with blood gases.
Systemic corticosteroids
Systemic corticosteroids reduce treatment failure and shorten recovery. COPD-X recommends oral prednisolone 30–50 mg daily for five days, with the oral route preferred when possible.2 Longer courses usually provide no additional benefit and increase adverse effects.
Antibiotics
- Antibiotics are not required for every exacerbation
- Consider them when bacterial infection is clinically likely.
- COPD-X recommends a five-day course of amoxicillin or doxycycline for uncomplicated exacerbations with clinical features of infection.2
The three cardinal sputum-related exacerbation features are increased dyspnoea, increased sputum volume and increased sputum purulence. Purulence, particularly when accompanied by another cardinal feature, increases the likelihood that antibiotics will provide benefit.
Ventilatory support
Non-invasive ventilation (NIV) is indicated for acute or acute-on-chronic hypercapnic respiratory failure with respiratory acidosis despite initial medical treatment, provided the patient can protect the airway and has no immediate indication for intubation. NIV reduces mortality and the need for endotracheal intubation.3,4
Escalate urgently for invasive ventilation when there is respiratory arrest, inability to protect the airway, severe haemodynamic instability, life-threatening hypoxaemia, worsening acidosis or failure of an appropriate NIV trial.
Persistent respiratory acidosis after initial treatment is a key indication for NIV. Do not delay intubation when NIV is contraindicated or when gas exchange, consciousness or haemodynamic status continues to deteriorate.
Hospital admission
Consider hospital assessment or admission for:
- Severe or rapidly worsening symptoms
- New hypoxaemia, hypercapnia or acidosis
- Altered mental state
- Haemodynamic instability or significant arrhythmia
- Failure of initial outpatient treatment
- Serious comorbidity or an important alternative diagnosis
- Inability to eat, sleep, mobilise or manage safely at home
- Inadequate home support
Pulmonary rehabilitation should be offered during recovery, particularly following hospitalisation.2,3
Complications & Prognosis
Complications
- Acute hypoxaemic or hypercapnic respiratory failure
- Respiratory acidosis
- Need for non-invasive or invasive ventilation
- Pneumonia
- Pneumothorax
- Cardiac arrhythmia, myocardial injury or acute heart failure
- Venous thromboembolism
- Delirium and functional decline
- Adverse effects from corticosteroids, antibiotics or prolonged hospitalisation
Prognosis
Recovery may take several weeks, and some patients do not return completely to their previous functional baseline. An exacerbation increases the short-term risk of another exacerbation and hospital readmission.1,2
Poor prognostic factors include:
- Older age or frailty
- Severe baseline airflow limitation
- Frequent previous exacerbations
- Previous hospital or intensive care admission
- Acute hypercapnic respiratory failure
- Significant cardiovascular or other systemic comorbidity
- Poor functional status or low body mass
- Continued smoking
- Inadequate social support
References
- Global Initiative for Chronic Obstructive Lung Disease. Global strategy for prevention, diagnosis and management of COPD: 2026 report [Internet]. 2026 [cited 2026 Aug 7]. Available from: https://goldcopd.org/2026-gold-report-and-pocket-guide/
- Yang IA, George J, McDonald CF, Disler R, Ordman R, Goodwin A, et al. The COPD-X Plan: Australian and New Zealand guidelines for the management of chronic obstructive pulmonary disease 2025. Version 2.78, October 2025 [Internet]. Australia: Lung Foundation Australia; 2025 [published online 2025 Dec 18; cited 2026 Aug 7]. Available from: https://copdx.org.au/copd-x-plan/
- Wedzicha JA, Miravitlles M, Hurst JR, Calverley PMA, Albert RK, Anzueto A, et al. Management of COPD exacerbations: an European Respiratory Society/American Thoracic Society guideline. Eur Respir J. 2017;49(3):1600791. doi:10.1183/13993003.00791-2016
- Rochwerg B, Brochard L, Elliott MW, Hess D, Hill NS, Nava S, et al. Official European Respiratory Society/American Thoracic Society clinical practice guidelines: noninvasive ventilation for acute respiratory failure. Eur Respir J. 2017;50(2):1602426. doi:10.1183/13993003.02426-2016
- Çallı E, Murphy K, Scholten ET, Schalekamp S, van Ginneken B. Explainable emphysema detection on chest radiographs with deep learning. PLoS One. 2022;17(7):e0267539. doi:10.1371/journal.pone.0267539