

Overview
Urinary incontinence is defined by the International Continence Society as the objective demonstration of involuntary leakage of urine. It is a common and distressing clinical condition that severely impacts physical health, psychological well-being, and overall quality of life. The condition is broadly caused by a disruption in the coordinated lower urinary tract mechanisms responsible for urine storage and voiding, involving the detrusor muscle of the bladder, the bladder neck, the urethral sphincters, and their complex central and autonomic neural innervation.
Epidemiologically, urinary incontinence is a global health issue with a strong female predominance. It affects approximately 30–50% of women at some point in their lives, with peak incidence occurring during menopause and advancing age.
In men, the overall prevalence is lower (~5–15%), rising significantly in older males where it is most commonly secondary to benign prostatic hyperplasia (BPH) or post-prostatectomy sphincter dysfunction.
Due to embarrassment and social stigma, the condition remains significantly underreported, with fewer than half of affected individuals seeking medical evaluation.
Definition
Stress Urinary Incontinence (SUI): Involuntary leakage of urine occurring on effort, physical exertion, sneezing, coughing, or laughing due to hypermobility of the bladder neck or intrinsic sphincter deficiency.
Urge Urinary Incontinence (UUI): Involuntary leakage of urine accompanied or immediately preceded by a sudden, compelling desire to void that is difficult to defer.
Overactive Bladder (OAB): A symptom syndrome characterized by urinary urgency, usually accompanied by frequency and nocturia, with or without urge urinary incontinence, in the absence of proven infection or metabolic disease.
Overflow Incontinence: Involuntary leakage of urine occurring when intravesical pressure exceeds maximal urethral pressure due to chronic urinary retention and bladder overdistension.
Post-Void Residual (PVR) Volume: The volume of urine remaining in the bladder immediately following completion of voluntary micturition, measured via ultrasound or catheterization.
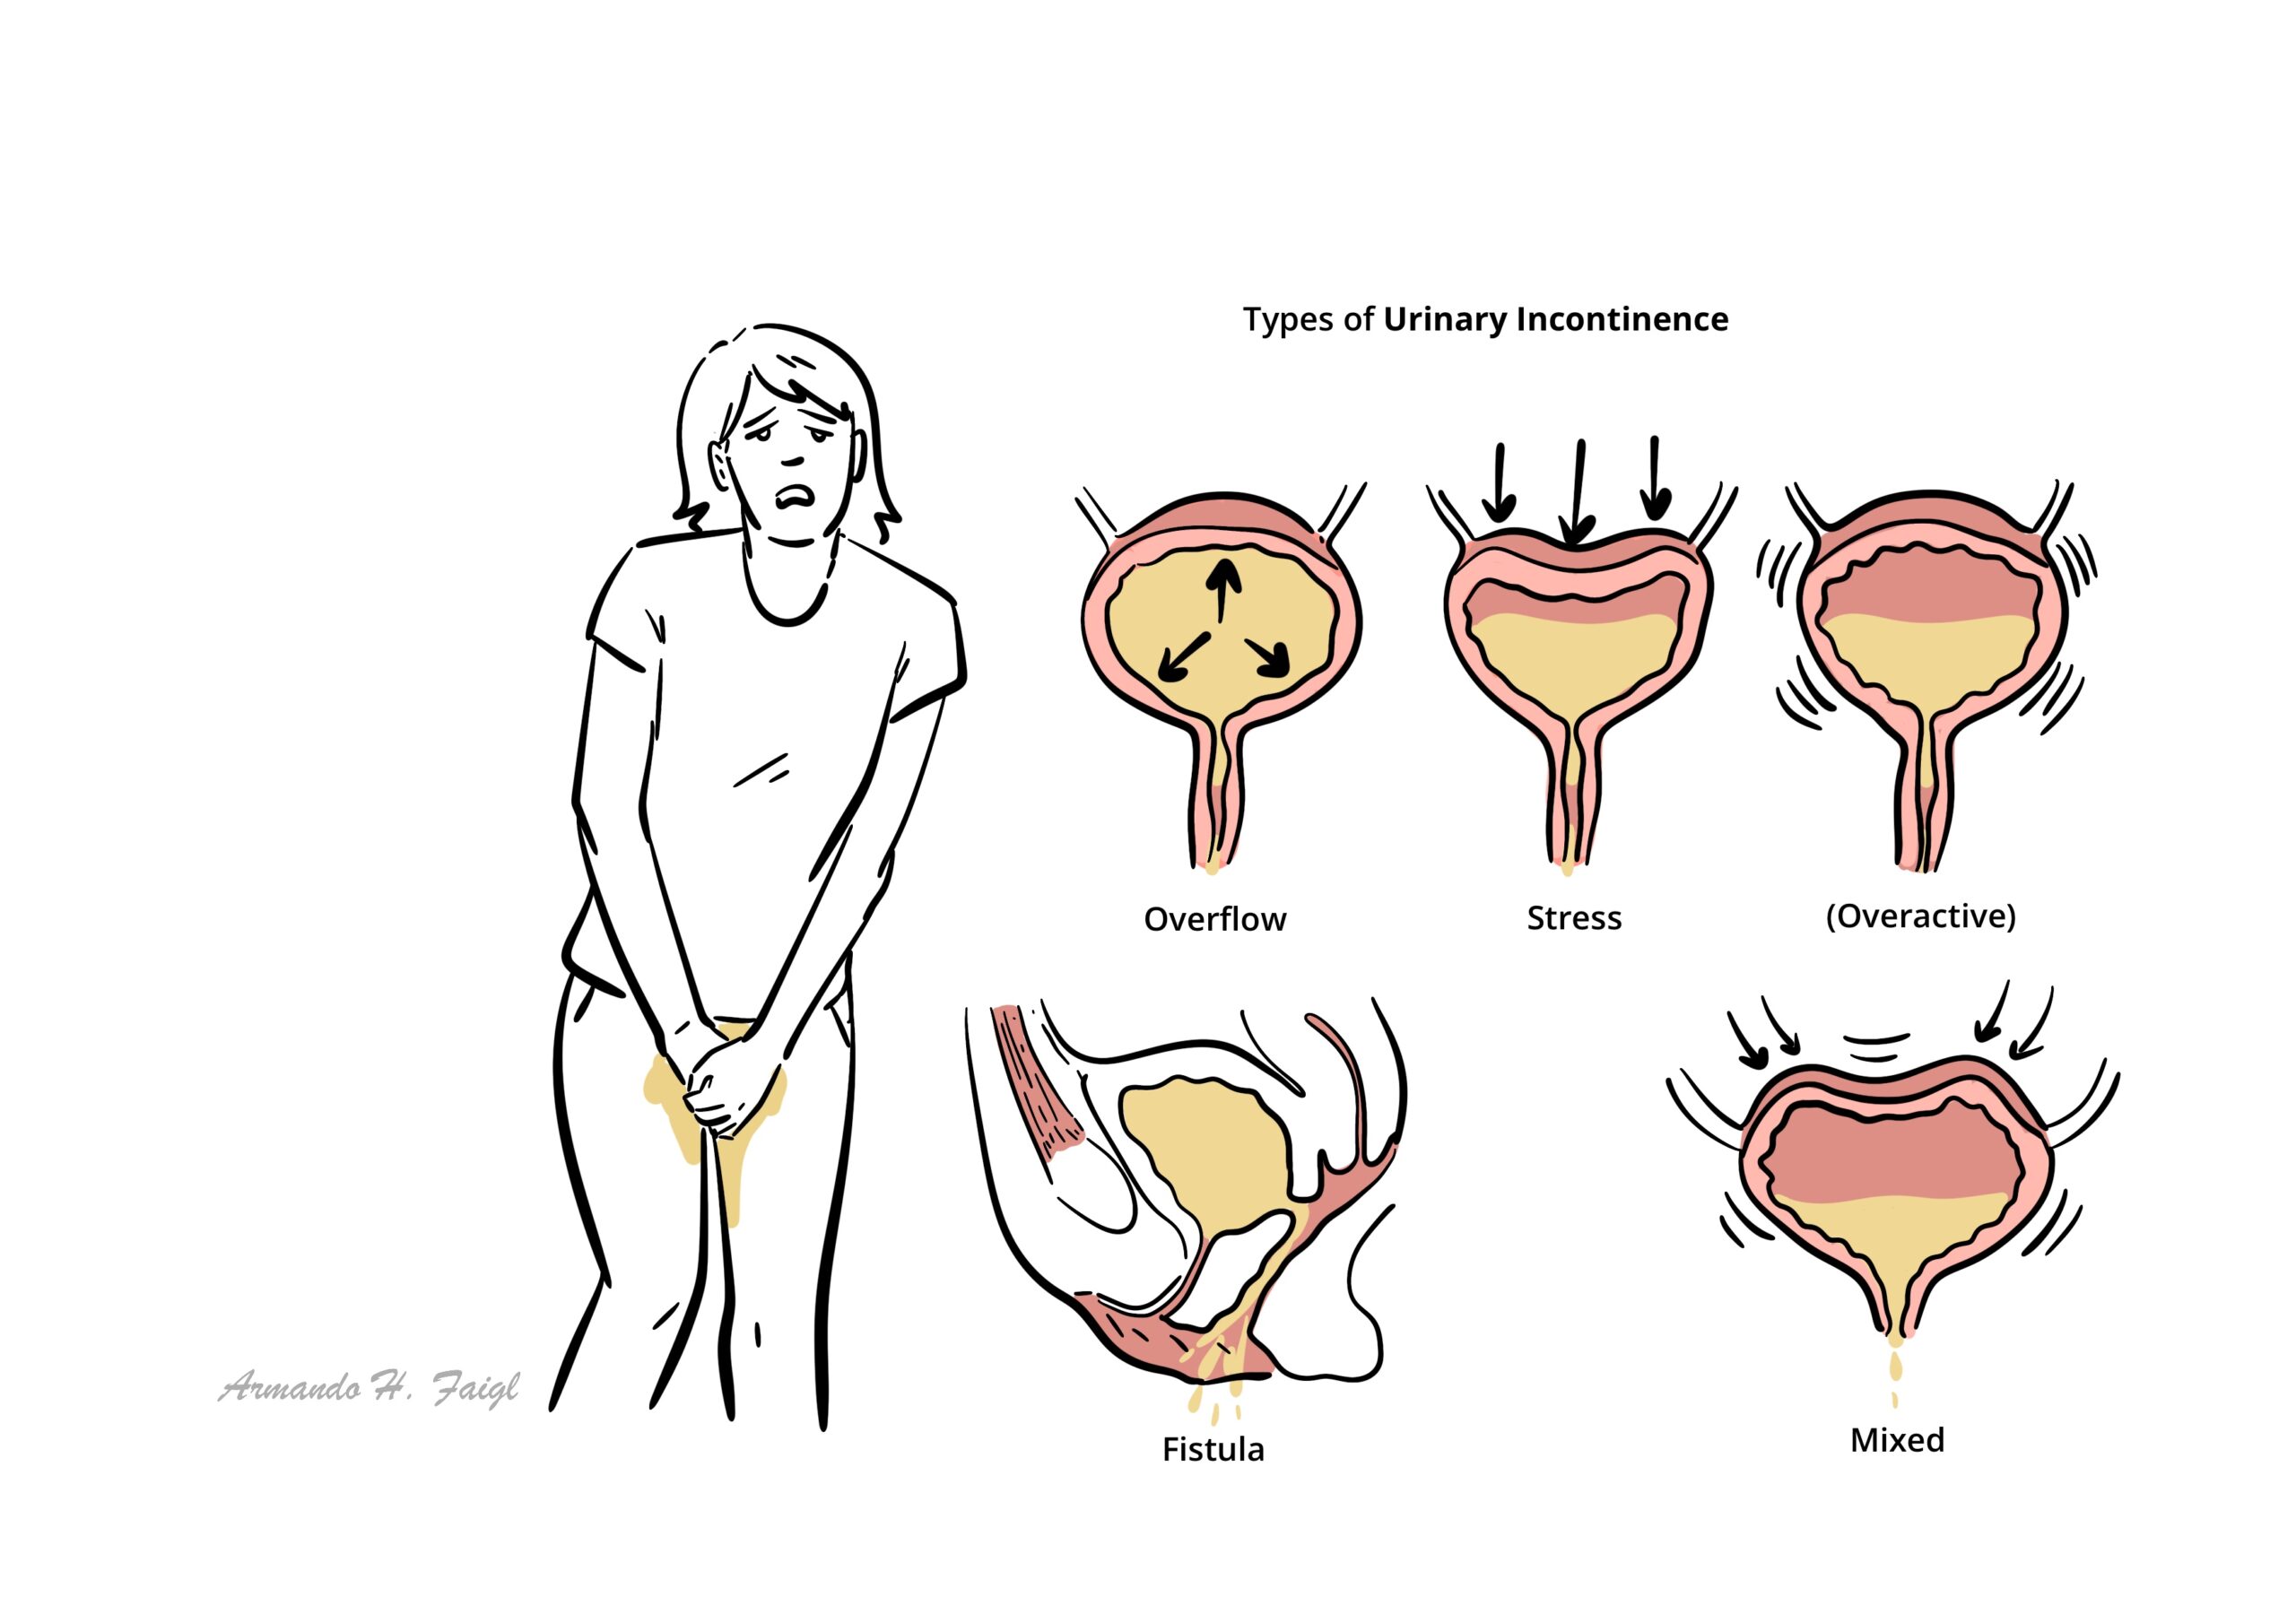
What to notice
Detailed image description
Anatomy & Physiology
Classification
- Stress Urinary Incontinence: Involuntary loss of urine during physical activities that increase intra-abdominal pressure without an associated detrusor contraction.
- Urge Urinary Incontinence: Involuntary loss of urine associated with uninhibited detrusor muscle contractions (Detrusor Overactivity).
- Mixed Urinary Incontinence: Symptomatic combination of both stress and urge urinary incontinence in the same patient.
- Overflow Urinary Incontinence: Involuntary loss of urine secondary to incomplete bladder emptying caused by bladder outlet obstruction or detrusor underactivity/aconductivity.
- Functional Urinary Incontinence: Involuntary loss of urine resulting from cognitive, physical mobility, or environmental barriers preventing the patient from reaching a toilet in time, despite intact lower urinary tract physiology.
Mixed Urinary Incontinence is extremely common in clinical practice. Always determine which component (stress vs. urge) is most bothersome to the patient, as initial treatment should target the primary symptom.
Risk Factors
Female-Specific Risk Factors
- Pregnancy & Parity: Multiple vaginal deliveries cause mechanical stretching and denervation of pelvic floor muscles and the levator ani complex.
- Menopause & Estrogen Deficiency: Loss of circulating estrogen leads to urogenital atrophy, reduced urethral mucosal vascularity, and decreased urethral closure pressure.
- Pelvic Organ Prolapse: Cystocele or uterine prolapse disturbing bladder neck anatomical alignment.
Male-Specific Risk Factors
- Prostatic Pathology: Benign Prostatic Hyperplasia (BPH) causing bladder outlet obstruction and secondary detrusor overactivity or chronic retention.
- Iatrogenic / Surgical: Radical prostatectomy or Transurethral Resection of the Prostate (TURP) damaging the internal or external urethral sphincter.
Reversible Triggers for incontinence (“DIAPPERS” Mnemonic)
- D – Delirium / Acute Confusional State
- I – Infection (Symptomatic Urinary Tract Infection)
- A – Atrophic Vaginitis / Urethritis
- P – Pharmaceuticals: Diuretics (rapid filling), Anticholinergics (retention), Alpha-blockers (sphincter relaxation), Sedatives (impaired awareness).
- P – Psychological Disorders: Severe depression or behavioral conditions.
- E – Excessive Fluid Intake / Excessive Alcohol & Caffeine
- R – Restricted Mobility: Severe arthritis, stroke, or Parkinsonism.
- S – Stool Impaction: Fecal impaction causing mechanical compression of the bladder neck.
Always rule out and correct reversible, transient causes of urinary incontinence (such as UTIs, severe constipation, or diuretic timing) before undertaking extensive urodynamic investigations or invasive procedures.
Pathophysiology
Stress Incontinence Pathophysiology
- Pelvic Floor Hypermobility: Weakness of the pelvic floor muscles (levator ani) and pubourethral ligaments reduces structural support to the bladder neck and proximal urethra. Increases in intra-abdominal pressure (coughing) transmit disproportionately to the bladder rather than the urethra, leading to leakage.
- Intrinsic Sphincter Deficiency: Direct structural or neurogenic damage to the urethral sphincter mechanism resulting in an open, non-functioning bladder neck at rest.
Urge Incontinence Pathophysiology
- Detrusor Overactivity: Involuntary contractions of the detrusor muscle during the storage phase of micturition. Can be neurogenic (loss of cortical inhibitory signals following stroke, MS, or spinal cord injury) or myogenic/idiopathic (increased sensitivity of detrusor smooth muscle to acetylcholine).
Overflow Incontinence Pathophysiology
- Mechanical Obstruction: BPH, urethral strictures, or pelvic tumors increase outflow resistance, leading to urinary retention.
- Detrusor Underactivity (Atony): Impaired detrusor contractility (e.g., autonomic neuropathy in long-standing diabetes mellitus or lower motor neuron lesions) leads to chronic large-volume retention. When intravesical pressure exceeds urethral closure pressure, urine leaks passively.
Clinical Manifestation
Stress Urinary Incontinence
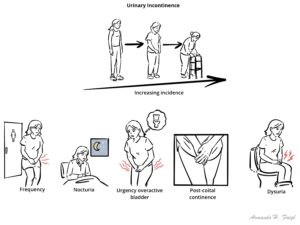
- Characteristics: Small to moderate volume leakage occurring instantaneously with physical exertion, coughing, sneezing, laughing, or lifting.
- Key Feature: Absence of urge sensation prior to the involuntary leakage.
- Postural Effect: Worse when standing or active; minimal or absent when lying down at night.
Urge Urinary Incontinence / Overactive Bladder
- Characteristics: Sudden, uncontrollable desire to urinate followed immediately by moderate to large volume involuntary leakage before reaching the toilet.
- Associated Symptoms: Marked daytime frequency (> 8 times/day) and severe nocturia (waking >= 2 times/night to void).
- Triggers: Running water, washing hands, cold weather, or stepping close to home/front door (“key-in-lock” syndrome).
Overflow Incontinence
- Characteristics: Continuous or intermittent small-volume dribbling, hesitancy, weak or interrupted urinary stream, and straining to void.
- Key Feature: Sensation of incomplete bladder emptying and lower abdominal fullness or pain.
- Nocturnal Symptoms: Frequently presents as nocturnal enuresis (bed-wetting) in adults.
Adult-onset nocturnal enuresis (wetting the bed at night) in a male patient with a history of lower urinary tract symptoms is a major red flag for Overflow Incontinence secondary to severe urinary retention.
Prolapse with coexist with stress incontinenece in over 50% of cases, and an enquiry about symptoms is essential.
Investigations
Initial Bedside Evaluation
- 3-Day Bladder Diary (Frequency-Volume Chart): Diagnostic cornerstone; logs fluid intake, voiding frequency, voided volumes, and episodes of incontinence to objectively quantify the pattern and type.
- Urinalysis & Urine Culture: Rule out urinary tract infection, microscopic hematuria, or glycosuria.
- Post-Void Residual (PVR) Volume: Measured via bedside bladder scan or in-and-out catheterization.
- PVR < 50 mL: Normal.
- PVR > 100–200 mL: Abnormal; indicates urinary retention / overflow pathophysiology.
- Cough Stress Test: Performed with a comfortably full bladder in the standing or lithotomy position. Direct visualization of immediate urethral leakage during coughing confirms SUI.
Specialised Investigations
- Urodynamic Studies (Cystometry & Pressure-Flow Studies): Gold standard for definitive physiological assessment. Measures intravesical, intra-abdominal, and detrusor pressures during bladder filling and emptying.
- Indications: Prior to surgical intervention, failed empiric therapy, mixed incontinence, suspected neurogenic bladder, or elevated PVR.
- Cystoscopy: Indicated if there is microscopic/gross hematuria, persistent bladder pain, recurrent UTIs, or suspicion of bladder carcinoma or urethral pathology.
Treatment
Management follows a stepwise approach, starting with non-invasive lifestyle and conservative interventions before escalating to pharmacotherapy or surgery.
1. General Conservative Measures (For ALL Types)
- Lifestyle Modifications: Moderation of fluid intake, reduction of dietary bladder irritants (caffeine, alcohol, carbonated drinks), weight reduction in overweight/obese patients, management of chronic constipation, and smoking cessation.
2. Management of Stress Urinary Incontinence (SUI)
- First-Line Conservative: Pelvic Floor Muscle Training (PFMT / Kegel Exercises) supervised by a specialist physiotherapist for at least 3 months (minimum 3 sets of 8–12 contractions daily).
- Pharmacotherapy (Second-Line): Duloxetine (Serotonin-Norepinephrine Reuptake Inhibitor – SNRI) increases urethral striated sphincter resting tone; used when surgery is contraindicated or declined.
- Surgical Options (Definitive):
- Mid-Urethral Sling (MUS) Procedures: Tension-free Vaginal Tape (TVT) or Transobturator Tape (TOT) supporting the mid-urethra.
- Periurethral Bulking Agents: Endoscopic injection of synthetic agents into the submucosa of the bladder neck.
- Autologous Fascial Slings / Colposuspension.
- Artificial Urinary Sphincter (AUS): Gold standard for post-prostatectomy severe SUI in males.
3. Management of Urge Urinary Incontinence (UUI / OAB)
- First-Line Conservative: Bladder Retraining (timed voiding with gradual extension of voiding intervals) combined with Pelvic Floor Muscle Training.
- First-Line Pharmacotherapy:
- Antimuscarinics / Anticholinergics: Solifenacin, Oxybutynin, or Tolterodine (inhibit M2/M3 receptors on detrusor smooth muscle). Side effects: dry mouth, constipation, blurred vision, cognitive decline in elderly.
- Beta-3 Adrenoceptor Agonists: Mirabegron (relaxes detrusor muscle during storage phase). Preferred in elderly patients due to lack of cognitive/anticholinergic side effects; contraindicated in severe uncontrolled hypertension.
- Refractory / Advanced Therapies:
- Intravesical Botulinum Toxin A (Botox) Injections: Cystoscopic injection into the detrusor muscle.
- Sacral Neuromodulation or Percutaneous Tibial Nerve Stimulation.
4. Management of Overflow Incontinence
- Urinary Decompression: Clean Intermittent Catheterization or long-term indwelling urethral/suprapubic catheter.
- Treat Underlying Obstruction: Medical management for BPH (Alpha-1 adrenergic antagonists such as Tamsulosin combined with 5-alpha reductase inhibitors like Finasteride) or surgical intervention (TURP).
Mirabegron (Beta-3 agonist) is the drug of choice for Overactive Bladder in elderly patients because it avoids the central anticholinergic burden and cognitive decline associated with traditional drugs like Oxybutynin.
Complications & Prognosis
Complications
- Dermatological: Incontinence-Associated Dermatitis, skin maceration, perineal fungal infections, and pressure ulcers.
- Infectious: Recurrent ascending Urinary Tract Infections and pyelonephritis.
- Traumatic: High risk of falls and non-vertebral fractures in elderly patients secondary to rushing to the toilet at night (nocturia).
- Psychosocial: Severe anxiety, social isolation, depression, loss of self-esteem, sexual dysfunction, and early institutionalization/nursing home placement.
Prognosis
- Pelvic floor muscle training cures or significantly improves stress incontinence in up to 60–70% of women.
- Mid-urethral sling operations for SUI carry long-term success rates exceeding 80–85%.
- Overactive bladder medications successfully manage urge incontinence symptoms in the majority of patients, though long-term compliance is often limited by side effects.
References
- Abrams P, Cardozo L, Wagg A, Wein A, editors. Incontinence: 6th International Consultation on Incontinence. Tokyo: Clinical Consultation Location Ltd; 2017.
- Aoki Y, Brown HW, Brubaker L, Cornu JN, Daly JO, Cartwright R. Urinary incontinence in women. Nat Rev Dis Primers. 2017;3:17042. doi:10.1038/nrdp.2017.42
- Kobashi KC, Albo ME, Dmochowski RR, et al. Surgical treatment of female stress urinary incontinence: AUA/SUFU guideline. J Urol. 2017;198(4):875-883. doi:10.1016/j.juro.2017.04.087