

Overview
Amyloid A (AA) amyloidosis is a systemic disorder caused by extracellular deposition of insoluble fibrils derived from persistently elevated serum amyloid A (SAA), an acute-phase protein produced mainly by the liver. It occurs as a complication of sustained inflammation from chronic inflammatory, autoinflammatory, infectious or, less commonly, neoplastic disease.1
The kidneys are affected in more than 90% of clinically recognised cases, typically causing proteinuria, nephrotic syndrome and progressive chronic kidney disease. Other sites include the gastrointestinal tract, liver, spleen, thyroid and, less commonly, the heart.1,2 Early diagnosis is important because sustained suppression of SAA can halt further deposition, permit regression of amyloid burden and improve organ outcomes.3
Definition
- Amyloid
- An insoluble extracellular fibrillar protein deposit with a characteristic cross-beta-sheet structure.
- AA amyloidosis
- Systemic amyloidosis in which the fibrils are derived from serum amyloid A protein.
- Serum amyloid A
- A hepatic acute-phase protein whose concentration may rise markedly during inflammation.
- Congo red staining
- Histological staining that produces apple-green birefringence under polarised light when amyloid is present.
Aetiology & Risk Factors
Aetiology
AA amyloidosis results from prolonged or recurrent inflammatory activity. Associated conditions include:
- Chronic inflammatory arthritis: rheumatoid arthritis, juvenile idiopathic arthritis, ankylosing spondylitis and psoriatic arthritis
- Autoinflammatory disease: familial Mediterranean fever (FMF), tumour necrosis factor receptor-associated periodic syndrome, cryopyrin-associated periodic syndromes and mevalonate kinase deficiency
- Chronic inflammatory bowel disease: particularly Crohn disease
- Chronic infection: bronchiectasis, osteomyelitis, tuberculosis, chronic skin or soft-tissue infection and infected prosthetic material
- Other inflammatory disorders: adult-onset Still disease, Behçet disease and hidradenitis suppurativa
- Neoplasia: particularly renal cell carcinoma and Castleman disease
- Inflammation of unknown cause: no underlying disorder is identified in a minority of patients1,2
Risk Factors
Risk depends more strongly on the duration and degree of inflammatory activity than on the diagnosis alone. Important factors include:
- Persistently elevated SAA or CRP
- Delayed diagnosis or inadequate treatment of the underlying inflammatory disease
- Frequent or prolonged autoinflammatory attacks
- Poor adherence to preventive treatment, particularly colchicine in FMF
- Longstanding suppurative infection
- Limited access to effective antimicrobial, immunomodulatory or biologic treatment
- Genetic susceptibility, including certain SAA1 variants
- Established proteinuria or chronic kidney disease
Not every patient with sustained inflammation develops AA amyloidosis, indicating that genetic and environmental modifiers contribute to susceptibility.1
Pathophysiology
Pro-inflammatory cytokines—particularly interleukin-1, interleukin-6 and tumour necrosis factor—stimulate hepatic production of SAA. During an acute inflammatory response, the circulating SAA concentration may rise more than a thousand-fold and usually falls rapidly when inflammation resolves.1
When SAA remains persistently elevated, it undergoes incomplete proteolysis, misfolding and aggregation into insoluble AA fibrils. These fibrils bind extracellular matrix components and progressively accumulate within tissues, distorting normal architecture and impairing organ function.
In the kidney, deposits commonly involve the glomeruli, causing disruption of the filtration barrier and heavy proteinuria. Vascular and tubulointerstitial deposition may instead produce progressive kidney impairment with less prominent proteinuria.2
AA amyloidosis is not simply a consequence of having an inflammatory diagnosis. The critical exposure is sustained circulating SAA. A patient with apparently mild symptoms may still accumulate amyloid if subclinical inflammation remains inadequately suppressed.
Clinical Manifestations
Presentation depends on the distribution and burden of amyloid deposition. Symptoms of the underlying inflammatory or infectious disease may coexist.
Renal manifestations
Renal involvement is usually the dominant presentation:
- Persistent proteinuria, which may progress to nephrotic-range proteinuria
- Nephrotic syndrome with oedema and hypoalbuminaemia
- Microscopic haematuria, although usually not a prominent feature
- Progressive reduction in estimated glomerular filtration rate
- Hypertension
- Kidney failure
The kidneys are often normal-sized or enlarged despite impaired function. Predominantly vascular or tubulointerstitial amyloid may cause reduced kidney function without marked proteinuria.2
Gastrointestinal and hepatosplenic manifestations
Possible manifestations include:
- Chronic diarrhoea or constipation
- Abdominal pain
- Malabsorption and weight loss
- Gastrointestinal bleeding
- Protein-losing enteropathy
- Hepatomegaly, usually with an elevated alkaline phosphatase
- Splenomegaly
Other manifestations
Less frequent features include:
- Goitre or thyroid dysfunction
- Adrenal infiltration and adrenal insufficiency
- Autonomic dysfunction
- Cardiac infiltration, which is substantially less common than in AL or transthyretin amyloidosis
- Increased susceptibility to thrombosis in nephrotic syndrome
Peripheral neuropathy, macroglossia, periorbital purpura and prominent cardiomyopathy are more characteristic of AL amyloidosis and should prompt reconsideration of the amyloid type.
Diagnosis & Investigations
Diagnosis requires histological demonstration of amyloid followed by reliable identification of the fibril protein as AA. Clinical context or an elevated SAA concentration alone cannot establish the amyloid type.1,2
Confirm amyloid deposition
Obtain tissue from an affected organ or a less invasive surrogate site:
- Kidney biopsy: commonly provides the diagnosis in patients with proteinuria or unexplained kidney impairment.
- Abdominal fat-pad aspiration or biopsy: less invasive, but a negative result does not exclude AA amyloidosis.
- Gastrointestinal, rectal or salivary-gland biopsy: may be considered according to the clinical presentation.
- Liver biopsy: generally avoided unless essential because amyloid infiltration may increase bleeding risk.
Amyloid appears as amorphous extracellular material on light microscopy. Congo red staining with apple-green birefringence under polarised light confirms amyloid but does not determine its type.
Type the amyloid
Accurate typing is mandatory because treatment differs fundamentally between AA, AL, transthyretin and hereditary amyloidoses.
- Laser microdissection followed by mass spectrometry is the reference method when available.
- Immunohistochemistry or immunofluorescence may identify AA deposits but depends on validated antibodies and experienced interpretation.
- Detection of a monoclonal gammopathy does not prove AL amyloidosis, particularly in older patients; the deposited protein must still be identified.
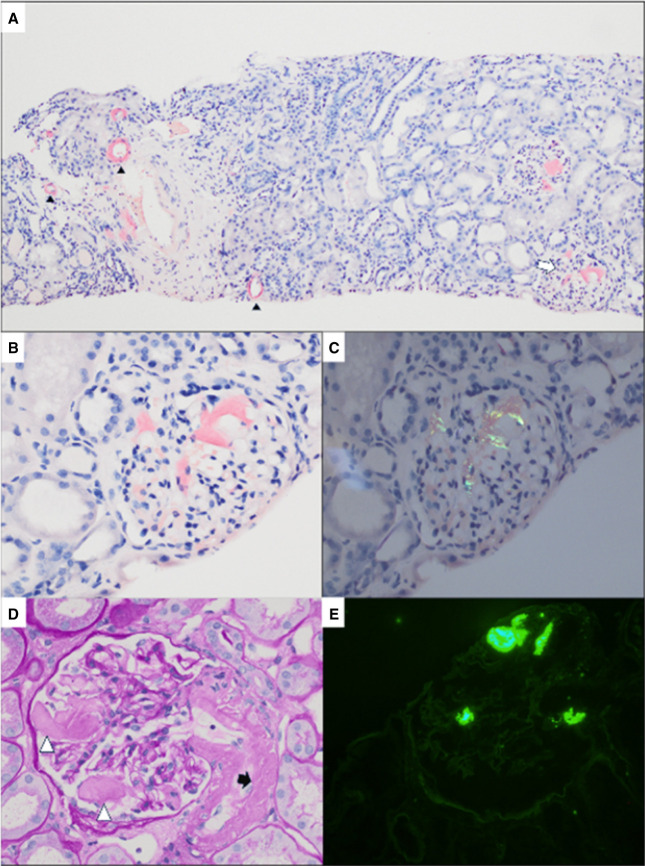
Renal AA amyloidosis showing glomerular and vascular deposits, Congo red positivity with apple-green birefringence, AA immunostaining and randomly arranged non-branching fibrils on electron microscopy. Image from Chowdhury et al. (2024), licensed under CC BY 4.0.
What to notice
Detailed image description
Source: Chowdhury R, Shah S, Latcha S, Lobato L. Kidney disease in systemic amyloidosis. Kidney360. 2024;5(12):1925–1937. doi:10.34067/KID.0000000600. Original asset: https://cdn.ncbi.nlm.nih.gov/pmc/blobs/2011/11687988/bea59ac870f8/kidney360-5-1925-g004.jpg. Licence: Creative Commons Attribution 4.0 International.
Never assign the amyloid type from the associated disease alone. A patient with rheumatoid arthritis may still have AL or transthyretin amyloidosis. Confirm the fibril protein in tissue before commencing type-specific treatment.
Assess inflammatory activity and identify the cause
Investigations may include:
- SAA concentration, where available
- CRP and erythrocyte sedimentation rate
- Careful review for inflammatory, autoinflammatory, infectious and neoplastic disorders
- Blood and urine cultures or targeted microbiological testing when infection is suspected
- Autoimmune and genetic testing guided by the phenotype
- Cross-sectional or functional imaging when an occult inflammatory focus or malignancy is suspected
SAA is preferred for monitoring the amyloidogenic inflammatory drive. CRP is a useful surrogate when SAA measurement is unavailable, but cytokine-directed therapies—particularly interleukin-6 inhibition—may suppress CRP and complicate interpretation.1
Assess organ involvement
Initial evaluation commonly includes:
- Urinalysis and urine albumin-to-creatinine or protein-to-creatinine ratio
- Serum creatinine, estimated glomerular filtration rate and electrolytes
- Serum albumin and liver biochemistry
- Full blood count
- Blood pressure and assessment for oedema
- Electrocardiogram, cardiac biomarkers and echocardiography when cardiac involvement is suspected
- Gastrointestinal investigations directed by symptoms
- Serum and urine immunofixation with serum free light chains to assess for a plasma-cell disorder
Serum amyloid P component scintigraphy can quantify systemic amyloid burden and monitor change where available, but it is not widely accessible and does not reliably assess cardiac deposits.1
Treatment
The central treatment goal is rapid and sustained suppression of SAA production by controlling the underlying inflammatory stimulus. There is no routinely available treatment that directly removes established AA deposits.1–3
Treat the underlying cause
Treatment must be tailored to the driver:
- Chronic infection: appropriate antimicrobial therapy, drainage or removal of an infected focus or prosthetic material
- Inflammatory arthritis or inflammatory bowel disease: optimise conventional immunomodulatory therapy and introduce targeted biologic treatment when required
- Autoinflammatory disease: suppress attacks and subclinical inflammation with disease-specific therapy
- FMF: continue the maximally tolerated dose of colchicine; add biologic therapy, most commonly interleukin-1 inhibition, when inflammation remains inadequately controlled4
- Castleman disease or malignancy: disease-specific therapy
Interleukin-1, interleukin-6 and tumour necrosis factor inhibitors may reduce SAA and improve proteinuria or kidney function when selected according to the underlying condition. No single biologic agent is universally preferred for all causes of AA amyloidosis.1,2
Treatment should not aim merely for symptomatic improvement. Persistent subclinical inflammation continues to drive amyloid deposition; the therapeutic target is sustained normalisation or near-normalisation of SAA, with CRP used cautiously as a surrogate when SAA is unavailable.
Renal and supportive management
Management of proteinuric chronic kidney disease may include:
- Renin–angiotensin system blockade when tolerated
- Blood-pressure optimisation
- Diuretics for oedema, with careful assessment of intravascular volume
- Dietary sodium restriction
- Cardiovascular risk reduction
- Assessment and treatment of nephrotic complications, including thrombosis and infection risk
- Avoidance of nephrotoxic medication
- Dose adjustment of medication according to kidney function
Patients with advanced kidney failure may receive dialysis. Kidney transplantation is an appropriate treatment for selected patients when the underlying inflammatory disease is well controlled. Recurrence in the allograft is uncommon when SAA remains adequately suppressed.1,5
Monitoring
Follow-up should assess both inflammatory control and organ response:
- Serial SAA, or CRP when SAA is unavailable
- Urine protein or albumin excretion
- Serum creatinine and estimated glomerular filtration rate
- Serum albumin and oedema
- Activity of the underlying disease
- Treatment adherence, adverse effects and infection risk
- Additional organ-specific testing when clinically indicated
Falling proteinuria and stable or improving kidney function suggest organ response, but these changes may lag behind biochemical control of inflammation.
Complications & Prognosis
Complications
Important complications include:
- Nephrotic syndrome
- Progressive chronic kidney disease and kidney failure
- Venous thromboembolism
- Severe oedema and intravascular volume depletion
- Malnutrition and protein-losing enteropathy
- Gastrointestinal bleeding or malabsorption
- Hepatic dysfunction
- Adrenal insufficiency
- Cardiac involvement
- Treatment-related infection or toxicity
- Recurrent amyloid deposition after transplantation when inflammation remains uncontrolled
Prognosis
Prognosis is determined principally by the degree of renal impairment, proteinuria, systemic amyloid burden and success of inflammatory suppression. Sustained low SAA concentrations are associated with stabilisation or regression of amyloid deposits, preserved renal function and markedly improved survival.3
Poor prognostic features include:
- Persistently elevated SAA
- Heavy proteinuria
- Reduced estimated glomerular filtration rate at diagnosis
- Extensive glomerular amyloid deposition
- Liver or cardiac involvement
- Greater total-body amyloid burden
- Older age
- Delayed or ineffective treatment of the underlying inflammatory disorder1,3
AA amyloidosis is therefore potentially modifiable even after organ involvement develops. Early recognition and durable control of the inflammatory driver offer the best opportunity to prevent further deposition and preserve organ function.
References
- Mirioglu S, Pamuk ON, Pamuk GE. AA amyloidosis: a contemporary view. Curr Rheumatol Rep. 2024;26:101–115. doi:10.1007/s11926-024-01147-8
- Karam S, Haidous M, Royal V, Leung N. Renal AA amyloidosis: presentation, diagnosis, and current therapeutic options: a review. Kidney Int. 2023;103(3):473–484. doi:10.1016/j.kint.2022.10.028
- Lachmann HJ, Goodman HJB, Gilbertson JA, Gallimore JR, Sabin CA, Gillmore JD, et al. Natural history and outcome in systemic AA amyloidosis. N Engl J Med. 2007;356(23):2361–2371. doi:10.1056/NEJMoa070265
- Ozen S, Kone-Paut I, Gül A, Frenkel J, Lachmann HJ, Livneh A, et al. EULAR/PReS endorsed recommendations for the management of familial Mediterranean fever: 2024 update. Ann Rheum Dis. 2025. doi:10.1016/j.ard.2025.01.006
- Schwarz C, Georgin-Lavialle S, Lombardi Y, Amselem S, Grateau G, Bienvenu B, et al. Kidney transplantation in patients with AA amyloidosis: outcomes in a French multicenter cohort. Am J Kidney Dis. 2024;83(3):329–339. doi:10.1053/j.ajkd.2023.07.020
- Chowdhury R, Shah S, Latcha S, Lobato L. Kidney disease in systemic amyloidosis: a review of amyloid, amyloid serum A protein, leukocyte chemotactic factor 2, and transthyretin amyloid. Kidney360. 2024;5(12):1925–1937. doi:10.34067/KID.0000000600