

Overview
Acute coronary syndrome (ACS) describes acute myocardial ischaemia caused by an abrupt reduction in coronary blood flow. It includes myocardial infarction (MI) and unstable angina and is a time-critical medical emergency. This article focuses on ST-segment elevation myocardial infarction (STEMI) and non-ST-segment elevation myocardial infarction (NSTEMI).1
Myocardial infarction is diagnosed when there is acute myocardial injury, demonstrated by a rise and/or fall in cardiac troponin with at least one value above the 99th-percentile upper reference limit, together with clinical evidence of acute myocardial ischaemia.2 STEMI and NSTEMI are initial electrocardiographic classifications that guide urgent management; they should not be treated as simple synonyms for transmural and subendocardial infarction.
Definition
- Acute coronary syndrome
- Acute myocardial ischaemia encompassing myocardial infarction and unstable angina.
- Myocardial infarction
- Acute myocardial injury with clinical evidence of myocardial ischaemia.
- STEMI
- Suspected myocardial infarction presenting with persistent ST-segment elevation or an accepted acute coronary occlusion equivalent.
- NSTEMI
- Myocardial infarction presenting without persistent ST-segment elevation.
- Acute coronary occlusion myocardial infarction
- Myocardial infarction caused by acute coronary occlusion, including STEMI and recognised STEMI-equivalent electrocardiographic patterns.
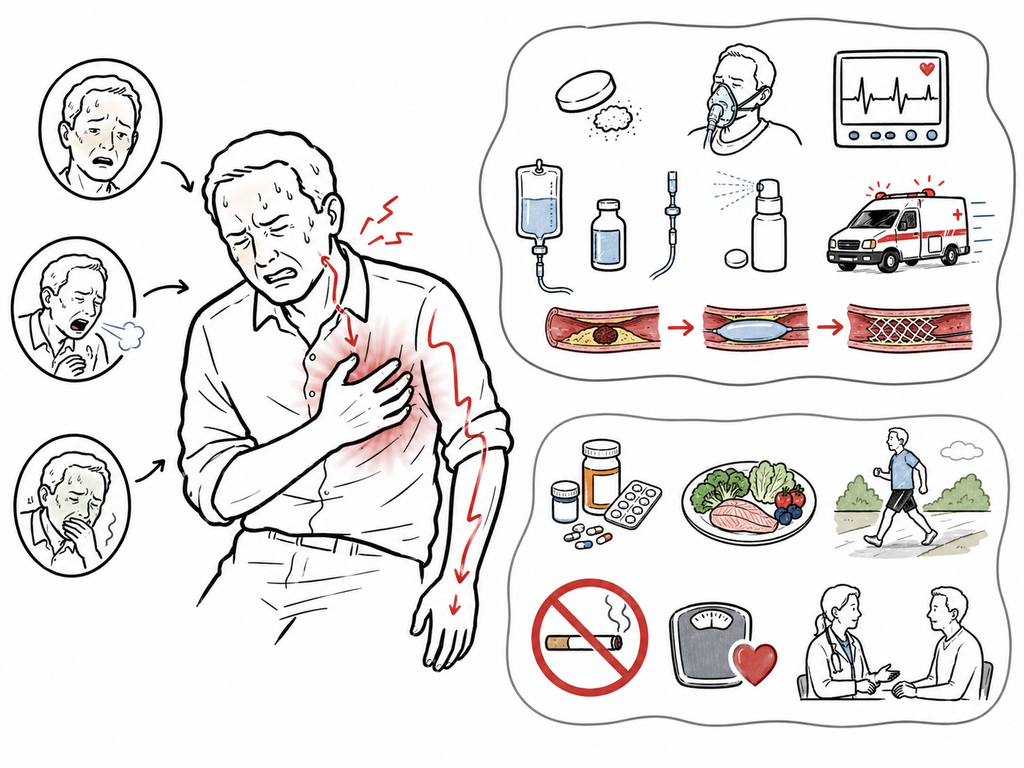
Anatomy & Physiology
The right and left coronary arteries arise from the aortic root and supply oxygenated blood to the myocardium.
- The left main coronary artery divides into the left anterior descending and circumflex arteries.
- The left anterior descending artery primarily supplies the anterior wall, anterior septum and cardiac apex.
- The circumflex artery supplies the lateral and, depending on coronary dominance, posterior myocardium.
- The right coronary artery usually supplies the right ventricle, inferior wall and atrioventricular node. In right-dominant circulation, it gives rise to the posterior descending artery.
Myocardial oxygen delivery depends on coronary blood flow, arterial oxygen content and diastolic perfusion pressure. Myocardial oxygen demand is influenced by heart rate, contractility and ventricular wall stress. Ischaemia develops when oxygen delivery becomes inadequate for myocardial demand.
Aetiology & Risk Factors
Aetiology
Most ACS-related myocardial infarctions are type 1 MI, caused by disruption or erosion of an atherosclerotic coronary plaque followed by platelet activation and coronary thrombosis. The thrombus may produce intermittent, subtotal or complete coronary occlusion.
Less common mechanisms include:
- spontaneous coronary artery dissection
- coronary embolism
- coronary vasospasm
- microvascular dysfunction
- acute oxygen supply–demand mismatch without acute atherothrombosis, producing type 2 MI
- complications of coronary intervention or cardiac surgery.
Risk Factors
- increasing age
- cigarette smoking
- hypertension
- dyslipidaemia
- diabetes mellitus
- chronic kidney disease
- established atherosclerotic cardiovascular disease
- family history of premature coronary disease
- physical inactivity
- obesity and an unhealthy dietary pattern
- inflammatory disorders associated with accelerated atherosclerosis.
Non-atherosclerotic MI should be considered particularly in younger people, pregnant or postpartum patients, and those without conventional cardiovascular risk factors.
Pathophysiology
In type 1 MI, a vulnerable atherosclerotic plaque ruptures or erodes, exposing thrombogenic material to circulating blood. Platelet adhesion, activation and aggregation occur alongside thrombin generation and fibrin formation. The resulting thrombus reduces or obstructs coronary blood flow.
Prolonged ischaemia impairs aerobic metabolism, reduces adenosine triphosphate production and disrupts membrane ion transport. Loss of myocardial contractility occurs early, followed by irreversible cardiomyocyte injury if perfusion is not restored. The area at risk and eventual infarct size depend on the affected artery, site and duration of occlusion, collateral circulation and myocardial oxygen demand.
Electrical instability within ischaemic myocardium may cause ventricular arrhythmias. Loss of functioning myocardium can produce regional wall-motion abnormalities, reduced left ventricular systolic function, acute heart failure or cardiogenic shock.
ST-segment elevation reflects an ischaemic electrical injury pattern, whereas troponin reflects cardiomyocyte injury. An occluded coronary artery may therefore produce diagnostic ECG changes before the troponin concentration has risen.
Clinical Manifestations
The characteristic presentation is acute central or retrosternal chest discomfort described as pressure, heaviness, squeezing, tightness or burning. It may radiate to one or both arms, the shoulders, neck, jaw, back or epigastrium.
Associated manifestations include:
- dyspnoea
- diaphoresis
- nausea or vomiting
- palpitations
- dizziness or syncope
- profound fatigue
- anxiety or a sense of impending doom.
Some patients present predominantly with dyspnoea, epigastric discomfort, nausea, syncope, fatigue or confusion. Less prominent chest discomfort is more frequent in older people, women and people with diabetes, chronic kidney disease or cognitive impairment. The term “atypical chest pain” should be avoided because it may falsely reduce clinical concern.3
Clinical examination
- pallor, diaphoresis or distress
- tachycardia or bradycardia
- hypotension or signs of poor peripheral perfusion
- pulmonary crackles or hypoxaemia
- raised jugular venous pressure
- a third or fourth heart sound
- a new systolic murmur suggesting acute mitral regurgitation or ventricular septal rupture
- arrhythmia or cardiac arrest.
Diagnosis
The diagnosis of acute MI requires a rise and/or fall in cardiac troponin with at least one value above the assay’s 99th-percentile upper reference limit, together with at least one of the following:2
- symptoms of acute myocardial ischaemia
- new ischaemic ECG changes
- development of pathological Q waves
- imaging evidence of new loss of viable myocardium or a new regional wall-motion abnormality consistent with an ischaemic cause
- identification of a coronary thrombus by angiography or autopsy.
Immediate assessment
Initial assessment should include a focused history, examination, vital signs, 12-lead ECG and high-sensitivity cardiac troponin measurement. The ECG should be obtained and interpreted by an appropriately experienced clinician within 10 minutes of presentation.1
A normal initial ECG does not exclude ACS. Repeat ECGs are required if symptoms persist or recur, the clinical condition changes, or suspicion remains high. Additional posterior leads may identify posterior infarction, while right-sided leads are useful when inferior MI or right ventricular involvement is suspected.
Do not wait for the troponin result before initiating reperfusion in a patient with ischaemic symptoms and clear ECG evidence of STEMI or another acute coronary occlusion pattern.1
ECG and troponin findings
| Feature | STEMI | NSTEMI |
|---|---|---|
| Initial ECG pathway | Persistent ST-segment elevation or an accepted occlusion equivalent | No persistent ST-segment elevation |
| Other possible ECG findings | Reciprocal ST depression, hyperacute T waves, new conduction disturbance or pathological Q waves | ST depression, T-wave inversion, transient ST elevation or a normal/non-diagnostic ECG |
| Troponin | Usually demonstrates an acute rise or fall, but may initially be normal | Acute rise or fall required for the final diagnosis |
| Immediate implication | Urgent reperfusion pathway | Risk-stratified invasive management; immediate angiography if very high-risk features are present |
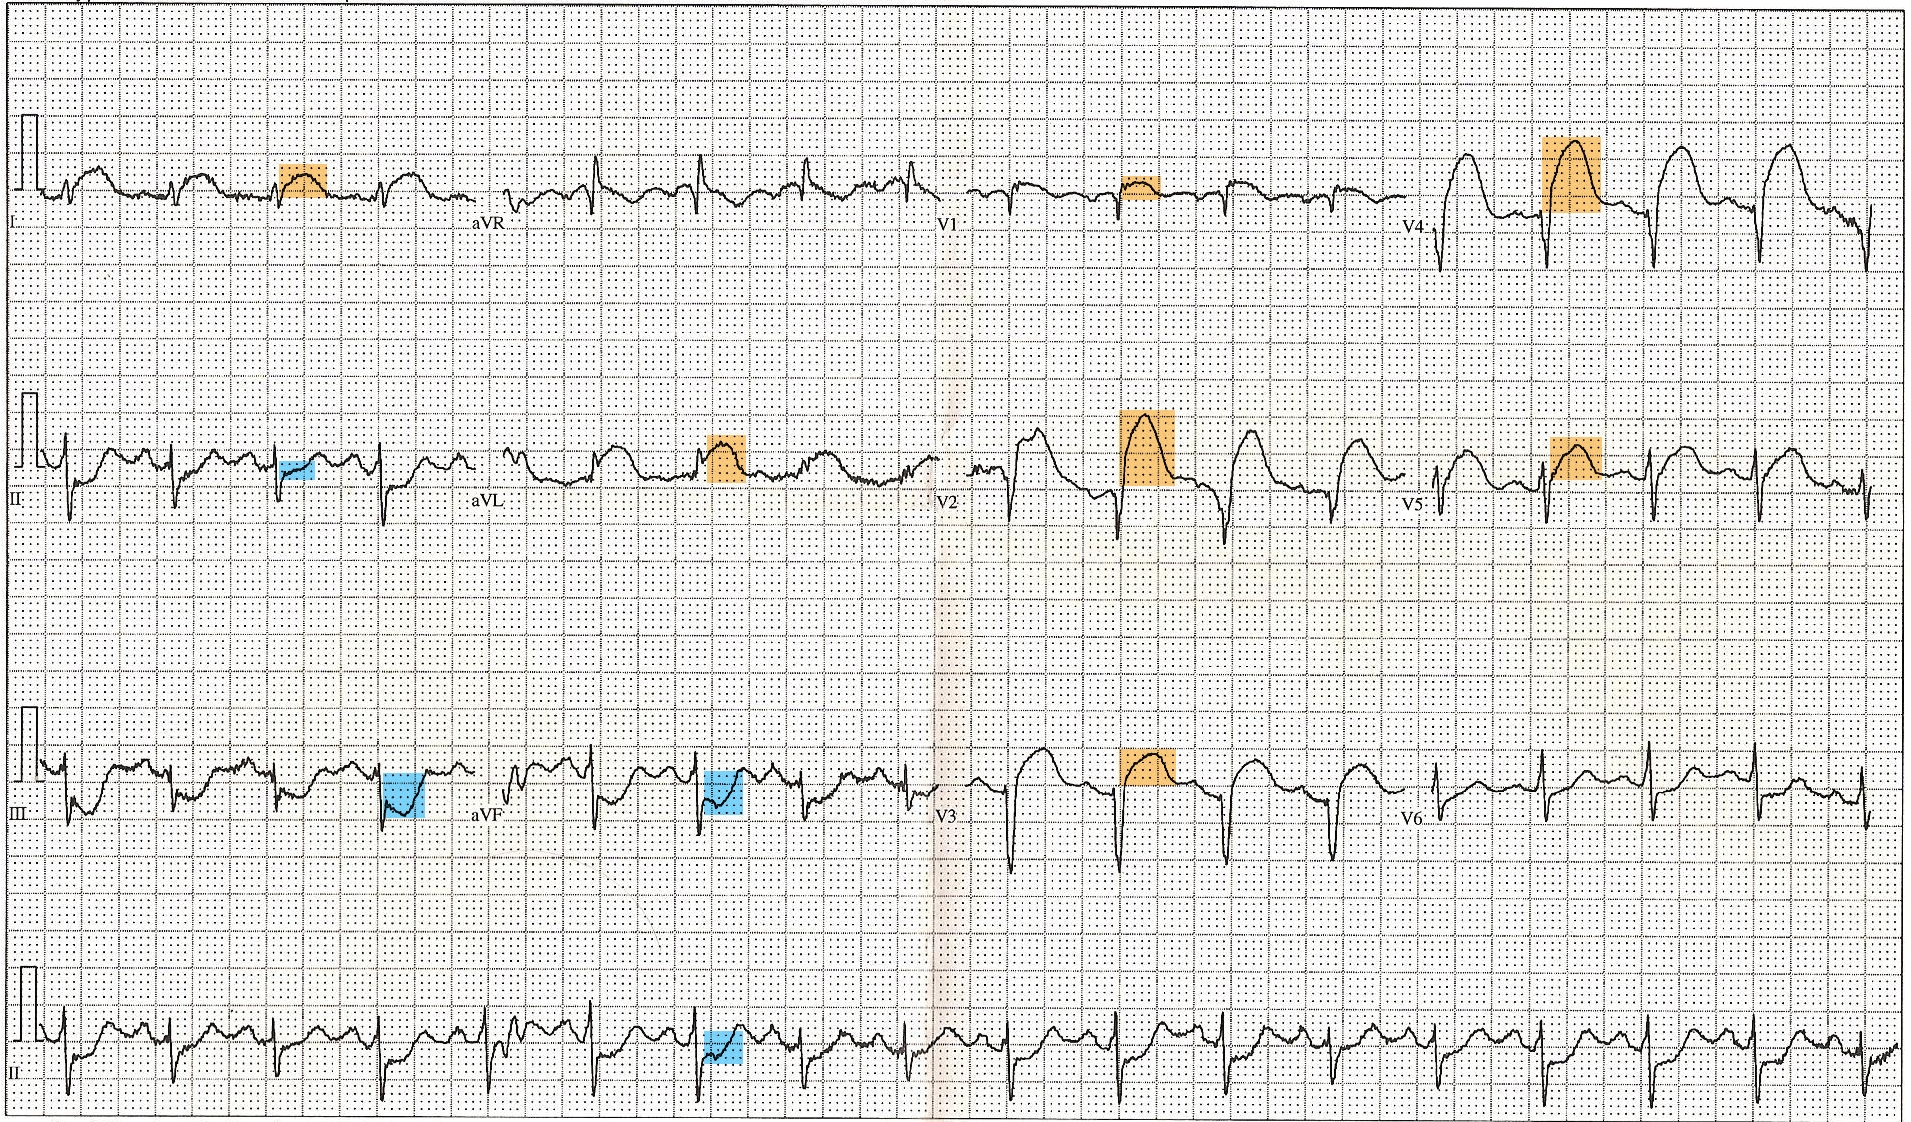
Twelve-lead ECG demonstrating anterior ST-segment elevation highlighted in orange, with reciprocal inferior ST depression highlighted in blue. “12 Lead EKG ST Elevation tracing color coded,” Displaced, public domain, via Wikimedia Commons.
What to notice
Detailed image description
Diagnosis and investigations image for Acute Coronary Syndrome. The tracing also demonstrates tachycardia and anterior fascicular block and represents one STEMI pattern.
High-sensitivity cardiac troponin I or T is the preferred biomarker. Serial testing should follow an assay-specific validated clinical decision pathway. A raised troponin indicates myocardial injury but does not independently establish MI; results must be interpreted with symptoms, serial change, ECG findings and the clinical context.1,2
Causes of troponin elevation other than type 1 MI include acute heart failure, tachyarrhythmia, myocarditis, pulmonary embolism, sepsis, renal disease and other critical illness.
Additional investigations
- Continuous cardiac monitoring: indicated when there are ongoing symptoms, ischaemic ECG changes, haemodynamic instability, arrhythmia, acute heart failure or other high-risk features.
- Full blood count: identifies anaemia and establishes the platelet count before antithrombotic treatment.
- Electrolytes, renal function and glucose: guide medication selection, contrast planning and risk assessment.
- Lipid profile and glycated haemoglobin: identify modifiable cardiovascular risk.
- Echocardiography: assesses regional wall motion, ventricular function and suspected mechanical complications; it must not delay urgent reperfusion.
- Coronary angiography: defines coronary anatomy and permits percutaneous coronary intervention.
- Chest radiography: may identify alternative or accompanying pathology but must not delay reperfusion.
- Cardiac magnetic resonance imaging: may help distinguish infarction, myocarditis and takotsubo syndrome when the diagnosis remains uncertain, particularly in myocardial infarction with non-obstructive coronary arteries.
Important time-critical differentials include acute aortic syndrome, pulmonary embolism, tension pneumothorax, pericarditis with myocarditis and oesophageal rupture.
Type 2 myocardial infarction requires acute myocardial injury with evidence of ischaemia caused by an oxygen supply–demand imbalance. Troponin elevation from non-ischaemic myocardial injury should not be labelled type 2 MI.2
Classification
Classification by presenting ECG
- STEMI: persistent ST-segment elevation or another recognised acute coronary occlusion pattern requiring immediate reperfusion assessment.
- NSTEMI: acute MI without persistent ST-segment elevation.
- Unstable angina: myocardial ischaemia without acute cardiomyocyte injury; its frequency has decreased with high-sensitivity troponin testing.
Universal classification of myocardial infarction
- Type 1: spontaneous MI caused by acute atherothrombosis.
- Type 2: MI caused by myocardial oxygen supply–demand imbalance without acute atherothrombosis.
- Type 3: cardiac death with suspected acute myocardial ischaemia before cardiac biomarkers can be obtained or become elevated.
- Type 4: MI associated with percutaneous coronary intervention, including stent thrombosis and restenosis subtypes.
- Type 5: MI associated with coronary artery bypass grafting.2
The STEMI/NSTEMI classification describes the presenting ECG pathway. The type 1–5 classification describes the mechanism or clinical context. They answer different questions and should not be used interchangeably.
Treatment
Management begins at first medical contact and proceeds concurrently with diagnosis, monitoring and preparation for reperfusion or invasive assessment.
Immediate measures
- Activate emergency medical and cardiology pathways.
- Assess airway, breathing, circulation, haemodynamic stability and pain.
- Establish cardiac monitoring, intravenous access and defibrillation capability.
- Give aspirin promptly unless contraindicated.
- Give oxygen only when the patient is hypoxaemic or requires it for another clinical indication.
- Consider sublingual or intravenous nitrate for ongoing ischaemic discomfort when blood pressure permits; avoid it in hypotension, suspected right ventricular infarction or recent phosphodiesterase-5 inhibitor use.
- Use opioid analgesia selectively for severe pain unresponsive to anti-ischaemic therapy.
- Commence an appropriate P2Y12 inhibitor and parenteral anticoagulant according to the reperfusion strategy, bleeding risk and local ACS protocol.1,3,4
STEMI reperfusion
Primary percutaneous coronary intervention (PCI) is the preferred reperfusion strategy when it can be delivered promptly. The Australian guideline recommends PCI within 120 minutes of first medical contact, with wire crossing targeted within 60 minutes at a PCI-capable centre or within 90 minutes when transfer from a non-PCI-capable service is required.1
If timely primary PCI cannot be achieved, fibrinolysis should be considered in an eligible patient presenting within 12 hours of symptom onset, provided there are no contraindications. Fibrinolysis should be followed by transfer to a PCI-capable centre. Rescue PCI is required when reperfusion fails or there is haemodynamic or electrical instability, worsening ischaemia or reinfarction.
NSTEMI invasive management
NSTEMI does not receive fibrinolysis. The timing of coronary angiography is determined by clinical risk:
- Immediate invasive strategy: haemodynamic instability or cardiogenic shock, recurrent or refractory chest pain, life-threatening arrhythmia, mechanical complication, acute heart failure attributable to ACS, or recurrent dynamic ST–T changes.
- Early/inpatient invasive strategy: confirmed NSTEMI or other high-risk features, with timing individualised according to clinical risk, comorbidity and local systems of care.
- Selective strategy: may be appropriate when ACS is not confirmed and clinical risk is low.
Secondary prevention
Before discharge, management should address:
- dual antiplatelet therapy for a duration individualised to ischaemic and bleeding risk
- high-intensity lipid-lowering therapy, with additional lipid-lowering treatment when targets are not achieved
- smoking cessation
- blood-pressure and diabetes management
- cardiac rehabilitation
- regular physical activity and a cardioprotective dietary pattern
- assessment of adherence, psychosocial health and barriers to care
- beta-blocker and renin–angiotensin system therapy when clinically indicated
- clear education about recurrent symptoms and when to seek emergency assistance.1,4
Complications & Prognosis
Complications
Early complications include:
- ventricular tachycardia or ventricular fibrillation
- bradyarrhythmia and atrioventricular block
- acute left ventricular failure and pulmonary oedema
- cardiogenic shock
- recurrent ischaemia, reinfarction or stent thrombosis
- pericarditis
- acute kidney injury
- bleeding related to antithrombotic or invasive treatment.
Mechanical complications usually occur during the first week and include:
- papillary muscle rupture causing acute severe mitral regurgitation
- ventricular septal rupture
- free-wall rupture causing haemopericardium and cardiac tamponade
- left ventricular aneurysm or pseudoaneurysm.
Later complications include chronic heart failure, left ventricular thrombus with systemic embolisation, ventricular remodelling, recurrent ACS, arrhythmia and adverse psychological outcomes.
Prognosis
Prognosis has improved with rapid reperfusion, modern antithrombotic treatment and secondary prevention. It varies with:
- age and frailty
- infarct size and location
- delay to reperfusion
- left ventricular systolic function
- haemodynamic instability or cardiogenic shock
- cardiac arrest or malignant ventricular arrhythmia
- renal impairment
- diabetes
- anaemia or major bleeding
- multivessel coronary disease
- adherence to secondary prevention and cardiac rehabilitation.1,3
References
- Brieger D, Cullen L, Briffa T, Zaman S, Scott I, Papendick C, et al. National Heart Foundation of Australia & Cardiac Society of Australia and New Zealand: comprehensive Australian clinical guideline for diagnosing and managing acute coronary syndromes 2025. Heart Lung Circ. 2025;34(4):309–397. doi:10.1016/j.hlc.2025.02.102
- Thygesen K, Alpert JS, Jaffe AS, Chaitman BR, Bax JJ, Morrow DA, et al. Fourth universal definition of myocardial infarction (2018). Circulation. 2018;138(20):e618–e651. doi:10.1161/CIR.0000000000000617
- Byrne RA, Rossello X, Coughlan JJ, Barbato E, Berry C, Chieffo A, et al. 2023 ESC guidelines for the management of acute coronary syndromes. Eur Heart J. 2023;44(38):3720–3826. doi:10.1093/eurheartj/ehad191
- Rao SV, O’Donoghue ML, Ruel M, Rab T, Tamis-Holland JE, Alexander JH, et al. 2025 ACC/AHA/ACEP/NAEMSP/SCAI guideline for the management of patients with acute coronary syndromes. J Am Coll Cardiol. 2025;85(22):2135–2237. doi:10.1016/j.jacc.2024.11.009