

Overview
Cholangitis means inflammation of the bile ducts. In clinical practice, the term commonly refers to acute cholangitis—an acute bacterial infection of the biliary system that usually develops when bile duct obstruction permits bacterial proliferation and impairs biliary drainage. It is a potentially life-threatening emergency because infection can rapidly progress to bacteraemia, sepsis and organ dysfunction.
Acute cholangitis is also called ascending cholangitis, reflecting the usual ascent of enteric organisms from the duodenum into an obstructed biliary tree. It is distinct from chronic immune-mediated cholangiopathies such as primary sclerosing cholangitis, primary biliary cholangitis and IgG4-related sclerosing cholangitis.
Definition
- Acute cholangitis
- Acute infection and inflammation of the biliary system, usually occurring in the presence of biliary obstruction.
- Biliary obstruction
- Partial or complete blockage of bile flow within the intrahepatic or extrahepatic bile ducts.
- Cholestasis
- Impaired formation or flow of bile, producing retention of bilirubin, bile acids and other biliary constituents.
- Choledocholithiasis
- Presence of one or more gallstones within the common bile duct.
- Endoscopic retrograde cholangiopancreatography
- An endoscopic and fluoroscopic procedure used to access, drain and treat disorders of the bile ducts and pancreatic duct.
Anatomy & Physiology
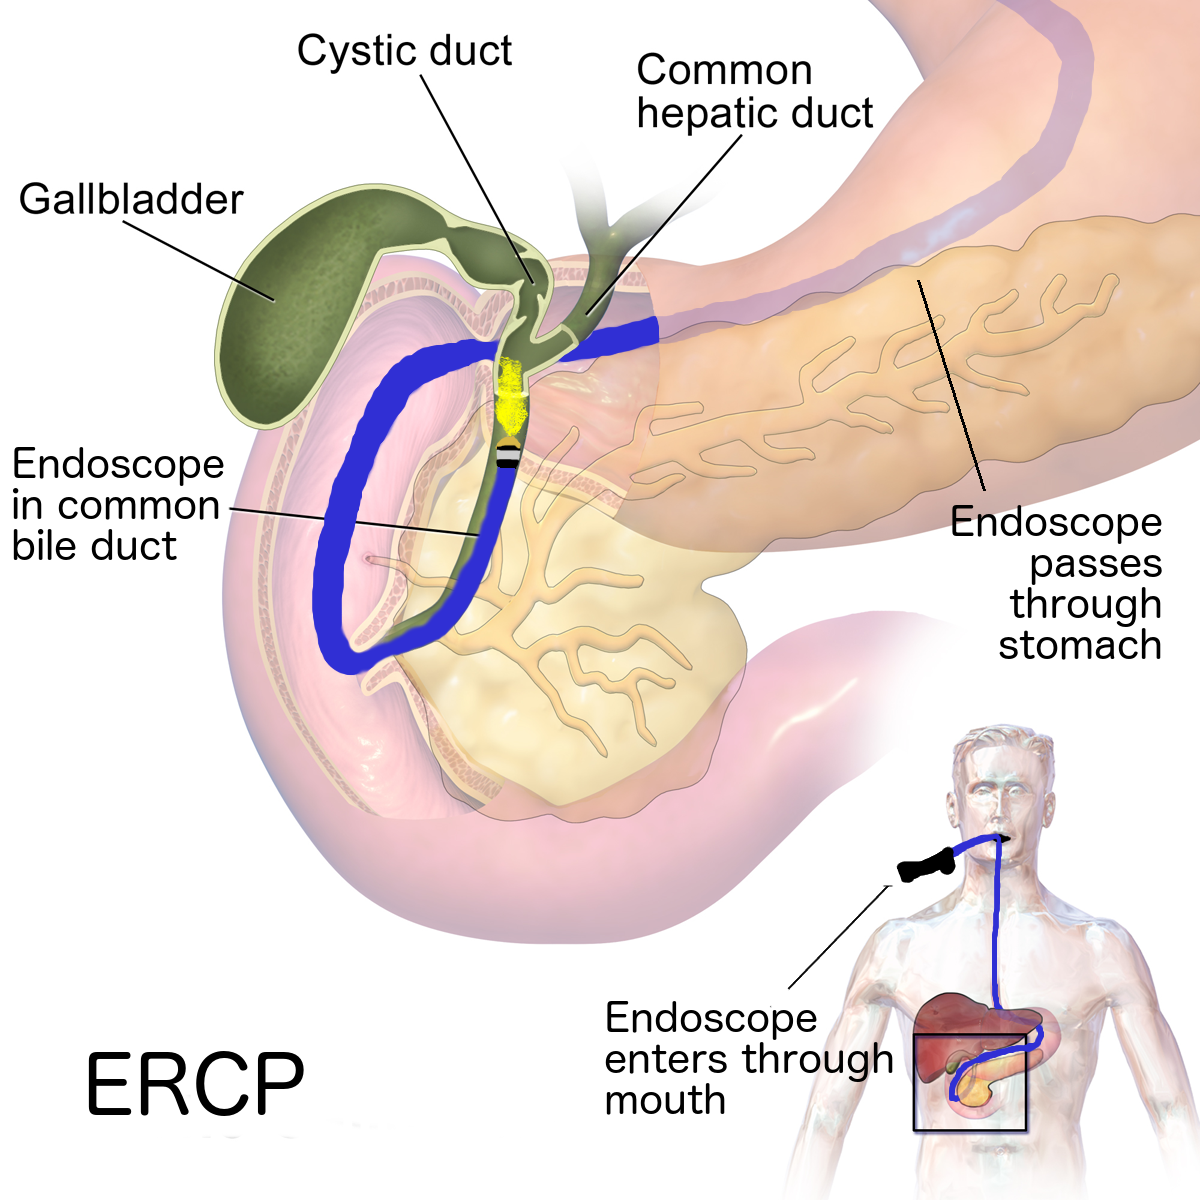
Bile produced by hepatocytes drains through progressively larger intrahepatic ducts into the right and left hepatic ducts. These unite to form the common hepatic duct, which joins the cystic duct from the gallbladder to form the common bile duct.
The common bile duct passes towards the second part of the duodenum and usually joins the main pancreatic duct at the hepatopancreatic ampulla. Bile flow into the duodenum is regulated by the sphincter of Oddi.
Normal antegrade bile flow, the flushing action of bile and the sphincter of Oddi help limit entry and proliferation of intestinal organisms within the biliary tree. Obstruction disrupts these protective mechanisms.
Aetiology & Risk Factors
Aetiology
Acute cholangitis usually requires both biliary obstruction and bacterial contamination. Important causes of obstruction include:
- Choledocholithiasis, the most common cause.
- Benign biliary strictures, including postoperative or inflammatory strictures.
- Malignant obstruction from cholangiocarcinoma, pancreatic cancer, ampullary cancer or metastatic disease.
- Occlusion or migration of a biliary stent.
- Anastomotic strictures following liver transplantation or biliary surgery.
- Primary sclerosing cholangitis with a clinically significant stricture.
- Parasites or intraductal debris, particularly in endemic settings.
- Iatrogenic obstruction or contamination following biliary instrumentation.
Common organisms are enteric bacteria, including Escherichia coli, Klebsiella species, Enterobacter species and Enterococcus species. Polymicrobial infection and resistant organisms are more likely in healthcare-associated infection, previous biliary intervention or the presence of an indwelling stent.2
Risk Factors
- Gallstone disease or previous choledocholithiasis.
- Known biliary stricture or malignancy.
- Previous endoscopic retrograde cholangiopancreatography (ERCP), sphincterotomy or biliary surgery.
- An indwelling biliary stent.
- Liver transplantation.
- Advanced age or frailty.
- Diabetes mellitus.
- Immunosuppression.
- Recurrent pyogenic cholangitis.
- Residence in or travel to areas where hepatobiliary parasites are endemic.
Pathophysiology
Biliary obstruction causes bile stasis and raises intraductal pressure. Bacteria may enter the biliary system by ascending from the duodenum, through the portal circulation or lymphatics, or during biliary instrumentation.
When intraductal pressure increases, the normal barrier between bile and the systemic circulation becomes impaired. Bacteria and endotoxins can then reflux into the hepatic venous and lymphatic systems, producing bacteraemia, systemic inflammation and sepsis.
Persistent obstruction also prevents adequate clearance of infected bile. This explains why antimicrobial therapy alone may be insufficient when significant obstruction remains.
Biliary obstruction converts a normally low-pressure drainage system into a pressurised infected space. Once bacteria and endotoxins enter the circulation, a patient may deteriorate rapidly even when the initial abdominal findings appear modest.
Clinical Manifestations
The clinical presentation ranges from mild biliary infection to septic shock.
- Fever or rigors.
- Right upper-quadrant or epigastric pain.
- Jaundice, dark urine or pale stools.
- Nausea and vomiting.
- Right upper-quadrant tenderness.
- Tachycardia and other features of systemic inflammation.
Charcot triad consists of fever, right upper-quadrant pain and jaundice. Although highly suggestive of acute cholangitis, the complete triad is not present in every patient.
Reynolds pentad consists of Charcot triad plus hypotension and altered mental status. It indicates severe infection with organ dysfunction and requires immediate resuscitation and urgent source control.
Older adults and immunocompromised patients may have an atypical presentation, including confusion, lethargy, hypotension or functional decline without prominent fever or abdominal pain.
Charcot triad: fever, right upper-quadrant pain and jaundice. Reynolds pentad: Charcot triad plus hypotension and altered mental status, suggesting severe acute cholangitis with organ dysfunction.
The absence of Charcot triad does not exclude acute cholangitis. Do not delay investigation or treatment when systemic inflammation occurs with biochemical or imaging evidence of biliary obstruction.
Diagnosis
Diagnosis is based on compatible clinical findings together with evidence of systemic inflammation, cholestasis and biliary obstruction.
Tokyo Guidelines 2018 diagnostic criteria
The Tokyo Guidelines 2018 group the findings into three categories:
| Category | Criteria |
|---|---|
| A. Systemic inflammation | Fever or shaking chills; or laboratory evidence of an inflammatory response |
| B. Cholestasis | Jaundice; or abnormal liver biochemical tests |
| C. Imaging | Biliary dilatation; or imaging evidence of an underlying cause such as a stone, stricture or stent |
- Suspected acute cholangitis: one criterion from category A plus one criterion from category B or C.
- Definite acute cholangitis: at least one criterion from each of categories A, B and C.
Clinical judgement remains essential. Investigations and severity assessment should occur alongside resuscitation rather than delaying treatment in an unstable patient.
Laboratory investigations
Initial investigations commonly include:
- Full blood count.
- C-reactive protein.
- Bilirubin, alkaline phosphatase, gamma-glutamyl transferase, alanine aminotransferase and aspartate aminotransferase.
- Urea, creatinine and electrolytes.
- Blood glucose.
- Coagulation profile.
- Venous or arterial blood gas and serum lactate when sepsis or hypoperfusion is suspected.
- Blood cultures, preferably obtained before antimicrobial therapy when this will not delay treatment.
- Lipase when gallstone pancreatitis is a possible concurrent diagnosis.
The biochemical pattern is often cholestatic, although aminotransferase concentrations may rise markedly during acute obstruction. Normal or only mildly abnormal tests early in the illness do not independently exclude cholangitis.
Imaging and procedures
- Abdominal ultrasound: usually the initial imaging investigation. It can identify gallstones and biliary dilatation but may not visualise a small or distal common bile duct stone.
- Contrast-enhanced CT: useful when ultrasound is inconclusive, complications are suspected, or malignant, postoperative or alternative intra-abdominal pathology must be assessed.
- Magnetic resonance cholangiopancreatography (MRCP): provides non-invasive delineation of the biliary tree and can identify the level and cause of obstruction when the diagnosis remains uncertain.2
- Endoscopic ultrasound: may detect small common bile duct stones or distal obstruction not demonstrated by other imaging.
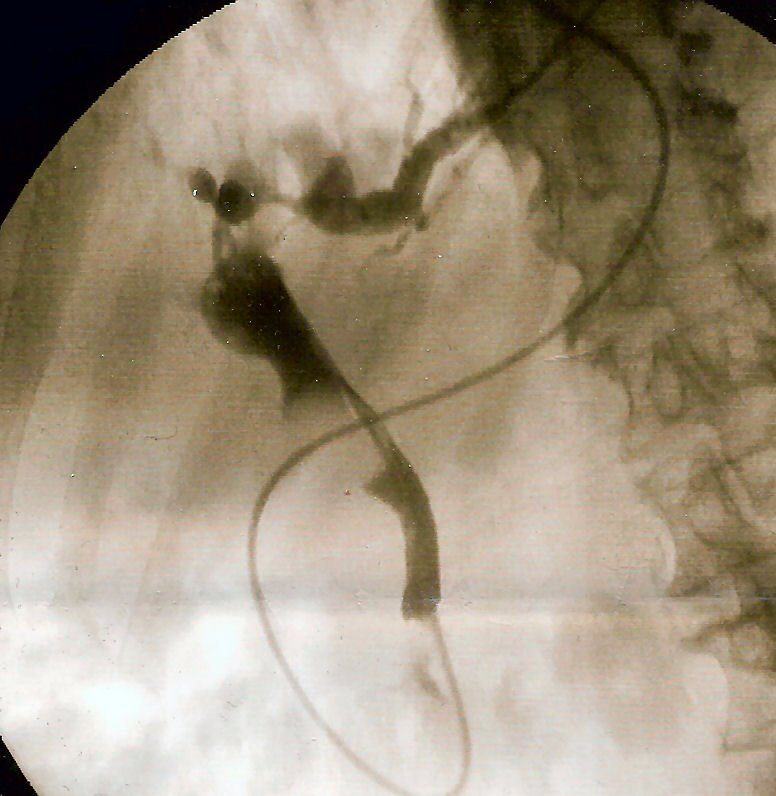
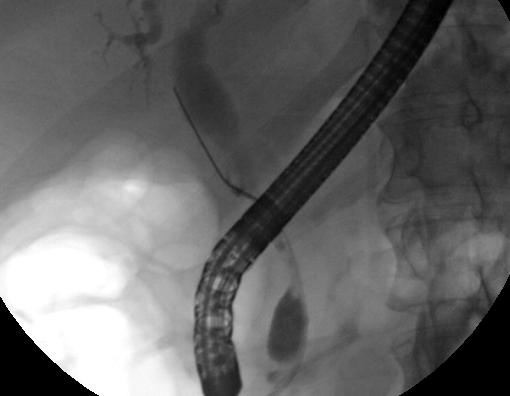
- ERCP: principally a therapeutic procedure in acute cholangitis because it allows biliary decompression, stone extraction, stricture treatment and stent placement. It should not be delayed solely to obtain further diagnostic imaging when urgent drainage is clinically indicated.2
Important differential diagnoses include acute cholecystitis, gallstone pancreatitis, viral or drug-induced hepatitis, liver abscess, sepsis from another source and malignant biliary obstruction without infection.
Classification
The Tokyo Guidelines classify acute cholangitis into three severity grades.1
Grade I — mild
Acute cholangitis that does not meet the criteria for Grade II or Grade III disease.
Grade II — moderate
Grade II disease is present when at least two of the following are identified:
- White cell count greater than 12 × 109/L or less than 4 × 10⁹/L.
- Temperature of at least 39°C.
- Age of at least 75 years.
- Total bilirubin of at least 5 mg/dL, approximately 85 micromol/L.
- Hypoalbuminaemia below 0.7 times the lower limit of the local normal range.
Grade III — severe
Grade III disease is defined by dysfunction of at least one organ system:
- Cardiovascular dysfunction requiring vasopressor support.
- Altered level of consciousness.
- Respiratory dysfunction.
- Renal dysfunction, including oliguria or elevated creatinine.
- Hepatic dysfunction demonstrated by prolonged prothrombin time–international normalised ratio.
- Haematological dysfunction with thrombocytopenia.
Severity should be reassessed because patients may deteriorate after their initial presentation.
Treatment
Acute cholangitis requires simultaneous treatment of sepsis and the obstructed biliary system.
Initial management
- IV fluids
- Analgesia and antiemetics
- Monitor for sepsis and organ dysfunction
- Take blood cultures if this does not delay antibiotics
Antibiotics
- Start IV antibiotics early
- Common empirical options include:
- ceftriaxone + metronidazole
- piperacillin–tazobactam for severe infection, sepsis, or broader Gram-negative coverage
- Adjust antibiotics according to cultures, renal function, allergy history, and local antimicrobial guidelines
- De-escalate once the causative organism and sensitivities are known
Biliary decompression
- ERCP is first-line for drainage of an obstructed biliary system
- Can also allow stone extraction or stent insertion
- Early drainage is particularly important in moderate–severe cholangitis or ongoing sepsis (PubMed)
- If ERCP fails
- Percutaneous transhepatic biliary drainage
- Surgery if required
Definitive treatment
- Treat the underlying cause, e.g. CBD stone, stricture, tumour, or blocked stent
- Consider cholecystectomy after recovery if gallstones are the cause
Antibiotics treat the infection but do not reliably correct persistent biliary obstruction. Failure to achieve adequate drainage can lead to continuing sepsis despite apparently appropriate antimicrobial therapy.
Complications & Prognosis
Complications
- Bacteraemia and sepsis.
- Septic shock and multiorgan dysfunction.
- Hepatic abscess.
- Acute kidney injury.
- Respiratory failure.
- Coagulopathy or disseminated intravascular coagulation.
- Recurrent cholangitis if the underlying obstruction is not corrected.
- Procedure-related complications, including post-ERCP pancreatitis, haemorrhage, perforation or recurrent stent occlusion.
Prognosis
Prognosis depends on disease severity, patient comorbidity, the presence of organ dysfunction and the speed with which antimicrobial therapy and effective biliary source control are achieved.
Most patients with mild or promptly treated disease recover. Poorer outcomes are associated with shock, altered mental status, respiratory or renal dysfunction, coagulopathy, advanced age, malignancy, healthcare-associated infection and delayed or unsuccessful biliary drainage.
Long-term prognosis depends on definitive management of the underlying cause. Retained stones, unresolved strictures and chronically occluded stents increase the risk of recurrence.
References
- Kiriyama S, Kozaka K, Takada T, Strasberg SM, Pitt HA, Gabata T, et al. Tokyo Guidelines 2018: diagnostic criteria and severity grading of acute cholangitis (with videos). J Hepatobiliary Pancreat Sci. 2018;25(1):17–30. doi:10.1002/jhbp.512
- Pötter-Lang S, Ba-Ssalamah A, Bastati N, Messner A, Kristic A, Asenbaum U, et al. Modern imaging of cholangitis. Br J Radiol. 2021;94(1125):20210417. doi:10.1259/bjr.20210417
- Miura F, Okamoto K, Takada T, Strasberg SM, Asbun HJ, Pitt HA, et al. Tokyo Guidelines 2018: initial management of acute biliary infection and flowchart for acute cholangitis. J Hepatobiliary Pancreat Sci. 2018;25(1):31–40. doi:10.1002/jhbp.509
- Buxbaum JL, Buitrago C, Lee A, Elmunzer BJ, Riaz A, Ceppa EP, et al. ASGE guideline on the management of cholangitis. Gastrointest Endosc. 2021;94(2):207–221.e14. doi:10.1016/j.gie.2020.12.032
- Gomi H, Solomkin JS, Schlossberg D, Okamoto K, Takada T, Strasberg SM, et al. Tokyo Guidelines 2018: antimicrobial therapy for acute cholangitis and cholecystitis. J Hepatobiliary Pancreat Sci. 2018;25(1):3–16. doi:10.1002/jhbp.518