

Overview
Carotid sinus hypersensitivity is an exaggerated autonomic response to stimulation of the carotid sinus. The resulting reflex may cause marked bradycardia, transient asystole, vasodilatation, hypotension, or a combination of these effects. This can reduce cerebral perfusion and produce presyncope or syncope.1
Carotid sinus hypersensitivity is a physiological finding demonstrated during carotid sinus massage. It should be distinguished from carotid sinus syndrome, in which a patient has otherwise unexplained, clinically compatible syncope and their spontaneous symptoms are reproduced during monitored carotid sinus massage. This distinction is important because an abnormal haemodynamic response without symptoms is relatively common in older adults and may be incidental.1,2
The condition predominantly affects adults older than 40 years and is especially recognised in older men with cardiovascular disease. Episodes may be triggered by head turning, tight collars, shaving, or direct pressure over the neck, although many patients do not identify a consistent trigger.
Definition
- Carotid sinus hypersensitivity
- An exaggerated response to carotid sinus massage, conventionally defined by an asystolic pause of at least 3 seconds, a fall in systolic blood pressure of more than 50 mmHg, or both.
- Carotid sinus syndrome
- Syncope caused by carotid sinus hypersensitivity, diagnosed when monitored carotid sinus massage reproduces the patient’s spontaneous symptoms together with the abnormal haemodynamic response.
- Cardioinhibition
- Reflex slowing of the sinus rate or atrioventricular conduction, potentially producing a prolonged ventricular pause.
- Vasodepression
- Reflex withdrawal of sympathetic vascular tone, producing vasodilatation and a substantial fall in blood pressure.
Anatomy & Physiology
The carotid sinus is a dilated region at the origin of the internal carotid artery, near the carotid bifurcation. Its arterial wall contains mechanosensitive baroreceptors that respond to stretching caused by changes in arterial pressure.
Afferent impulses travel predominantly through the carotid sinus nerve, a branch of the glossopharyngeal nerve, to the nucleus tractus solitarius in the medulla. The medulla coordinates the autonomic response through:
- Increased parasympathetic output through the vagus nerve
- Reduced sympathetic stimulation of the heart and peripheral vasculature
- Slowing of sinus-node discharge
- Slowing of atrioventricular conduction
- Peripheral vasodilatation and reduced vascular resistance
Under normal circumstances, this baroreflex provides rapid, short-term stabilisation of arterial blood pressure. In carotid sinus hypersensitivity, relatively minor stimulation generates a disproportionate cardioinhibitory or vasodepressor response.
Aetiology & Risk Factors
Aetiology
The precise cause is usually not identifiable. Proposed mechanisms include altered central processing of baroreceptor signals, age-related autonomic dysfunction, increased sensitivity of the reflex arc, and impaired compensatory sympathetic responses.
The carotid sinus itself is not necessarily structurally abnormal. The disorder reflects an exaggerated reflex response rather than obstruction of the carotid artery.
Secondary carotid sinus syndrome may occasionally occur when local disease mechanically stimulates or alters the carotid sinus, including:
- Head and neck malignancy
- Enlarged cervical lymph nodes
- Previous neck surgery
- Previous neck irradiation
- Extensive scarring near the carotid bifurcation
Risk Factors
- Age older than 40 years, with prevalence increasing substantially in later life
- Male sex
- Hypertension
- Coronary artery disease
- Diabetes mellitus
- Neurodegenerative or autonomic disease
- Coexisting orthostatic hypotension
- Sinus-node or atrioventricular conduction disease
- Previous neck surgery or radiotherapy
- Head and neck malignancy
Carotid sinus hypersensitivity is exceptional in people younger than 40 years. Syncope in a younger patient should prompt careful assessment for vasovagal, orthostatic, arrhythmic, structural cardiac, neurological, or metabolic causes before this diagnosis is considered.
Pathophysiology
Carotid sinus stimulation stretches the baroreceptors and generates an exaggerated afferent signal to the medulla. The subsequent autonomic response may affect heart rate, vascular tone, or both.
Cardioinhibitory Response
Excessive vagal activation suppresses sinus-node activity and slows atrioventricular conduction. This may produce profound sinus bradycardia, sinus arrest, atrioventricular block, or transient ventricular asystole. The abrupt reduction in cardiac output may cause cerebral hypoperfusion before peripheral vascular compensation can occur.
Vasodepressor Response
Withdrawal of sympathetic vasoconstrictor tone causes peripheral vasodilatation and a marked fall in systemic vascular resistance. Blood pressure may remain low even when the heart rate does not slow substantially.
Mixed Response
Many patients demonstrate both cardioinhibition and vasodepression. A prolonged pause may initiate the episode, while persistent vasodilatation delays blood-pressure recovery and prolongs symptoms.
Why might a patient continue to experience syncope after a technically successful pacemaker implantation?
A pacemaker can prevent or shorten bradycardia and asystole, but it cannot directly reverse the vasodepressor component. Persistent vasodilatation and hypotension may therefore cause recurrent symptoms, particularly in mixed carotid sinus syndrome.
Clinical Manifestations
Syncope and Presyncope
Episodes are often abrupt and may occur with little or no prodrome. Manifestations include:
- Sudden transient loss of consciousness
- Light-headedness or presyncope
- Visual dimming
- Generalised weakness
- Loss of postural tone
- Unexplained falls, particularly in older adults
- Injury resulting from sudden collapse
Recovery is usually rapid once cerebral perfusion is restored. Prolonged post-event confusion is not characteristic and should raise suspicion for seizure or another neurological cause.
Potential Triggers
- Turning or extending the head
- Shaving
- Wearing a tight collar, necktie, or restrictive clothing
- Direct pressure over the carotid sinus
- Neck manipulation
- Coughing or straining
- Swallowing, occasionally
- Prolonged standing or concurrent dehydration
A typical mechanical trigger increases suspicion but is not required. Many patients with carotid sinus syndrome cannot identify a consistent precipitant.
Cardioinhibitory Features
- Abrupt syncope without warning
- Pallor
- Transient absence of a palpable pulse
- Documented profound bradycardia, sinus arrest, or atrioventricular block
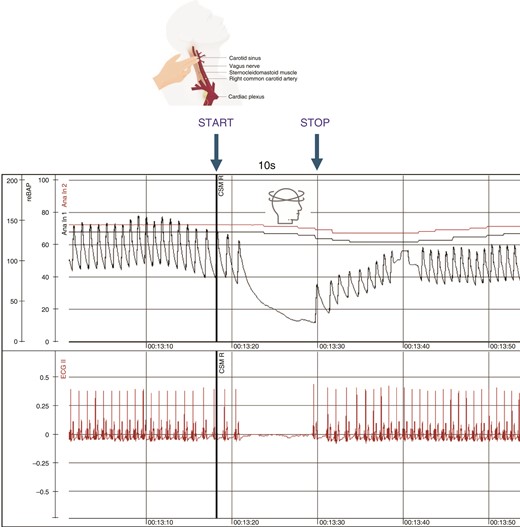
What to notice
Detailed image description
Vasodepressor Features
- Longer presyncopal symptoms
- Warmth
- Weakness
- Visual disturbance
- Symptoms aggravated by dehydration, vasodilators, or prolonged standing
Unexplained falls in an older adult may represent unwitnessed syncope. Ask specifically about abrupt collapse, amnesia for loss of consciousness, injury, head-turning triggers, tight collars, and medication-related hypotension.
Features Suggesting an Alternative High-Risk Cause
- Syncope during exertion or while supine
- Chest pain, breathlessness, or sustained palpitations
- Known structural heart disease
- Abnormal ECG
- Family history of sudden cardiac death
- Persistent neurological deficit
- Prolonged confusion
- Significant haemorrhage or anaemia
- Severe headache preceding loss of consciousness
Diagnosis
The diagnostic approach should first establish that the event was syncope, assess immediate risk, and exclude more concerning causes. Carotid sinus massage is then used selectively when the history is compatible.
Twelve-lead ECG
An ECG is required to identify alternative or accompanying causes such as sinus-node dysfunction, atrioventricular or bundle branch block, previous myocardial infarction, pre-excitation, long or short QT interval, Brugada pattern, and atrial or ventricular arrhythmia.
Carotid Sinus Massage
Carotid sinus massage is the key diagnostic test. It is most useful in patients older than 40 years with otherwise unexplained syncope compatible with a reflex mechanism, particularly when symptoms are associated with pressure or manipulation of the neck.1–3
It should be undertaken only by an appropriately trained clinician in a monitored clinical setting with continuous ECG, continuous beat-to-beat blood-pressure monitoring, immediate access to resuscitation equipment, and the patient initially supine and—when appropriate—subsequently upright on a tilt table.
Each carotid sinus is massaged separately, generally for approximately 10 seconds, allowing heart rate and blood pressure to return to baseline between attempts. Testing in both supine and upright positions improves diagnostic sensitivity.2
Carotid sinus massage should never be self-performed or undertaken casually at the bedside without continuous ECG and beat-to-beat blood-pressure monitoring.
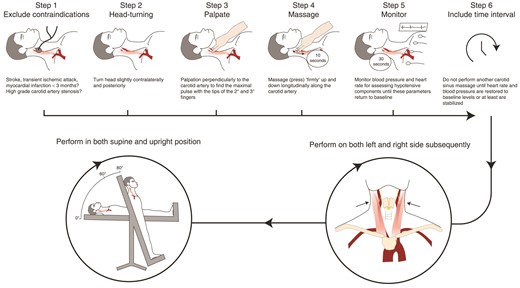
What to notice
Detailed image description
Interpretation
| Finding | Interpretation |
|---|---|
| Asystolic pause of at least 3 seconds | Cardioinhibitory carotid sinus hypersensitivity |
| Fall in systolic blood pressure of more than 50 mmHg without substantial bradycardia | Vasodepressor carotid sinus hypersensitivity |
| Both abnormalities | Mixed carotid sinus hypersensitivity |
| Reproduction of the patient’s spontaneous syncope or presyncope with an abnormal response | Supports carotid sinus syndrome |
| Abnormal haemodynamic response without symptoms | Carotid sinus hypersensitivity only; may be incidental |
Although 3 seconds defines abnormal cardioinhibition, spontaneous syncope is more commonly reproduced with longer pauses, often exceeding 6 seconds. The haemodynamic result must therefore be interpreted using the “method of symptoms” rather than the numerical threshold alone.1,2
When Carotid Sinus Massage Should Be Avoided
- Previous transient ischaemic attack or stroke
- Known significant carotid stenosis
- A carotid bruit until clinically important carotid disease has been excluded
- A previous serious adverse response to carotid sinus massage
The procedure is not indicated when the presentation already identifies a different cause of syncope or the patient is medically unstable.3
An older patient develops a 4-second ventricular pause during carotid sinus massage but remains completely asymptomatic. Does this establish the cause of recurrent falls?
No. This demonstrates carotid sinus hypersensitivity, but not carotid sinus syndrome. The response may be incidental unless the patient’s usual symptoms are reproduced and the clinical history is compatible.
Targeted Additional Investigations
- Ambulatory ECG monitoring
- Echocardiography
- Tilt-table testing: May be useful when reflex syncope remains uncertain, orthostatic hypotension or vasovagal susceptibility is possible, a substantial vasodepressor component is suspected, or the likely response to pacing requires further assessment.
- Carotid ultrasound
- Carotid ultrasound is not a diagnostic test for carotid sinus hypersensitivity.
- It is reserved for suspected carotid artery disease, particularly when a bruit is present before planned massage.
Routine neuroimaging, electroencephalography, carotid imaging, or broad laboratory panels are not indicated unless the history or examination suggests a specific alternative diagnosis.
Treatment
Treatment is guided by symptom severity, haemodynamic subtype, recurrence risk, and the presence of injury. Asymptomatic carotid sinus hypersensitivity does not require treatment.
Education and Trigger Reduction
- Explain the mechanism and generally benign reflex nature of the condition
- Avoid tight collars and direct pressure over the carotid sinus
- Minimise abrupt or sustained head turning when it is a recognised trigger
- Sit or lie down promptly when warning symptoms occur
- Maintain adequate hydration and avoid excessive alcohol
- Address heat exposure and prolonged standing
- Use physical counter-pressure manoeuvres when a sufficient prodrome is present
Patients with little or no warning should receive falls-prevention advice because counter-pressure manoeuvres may not be practical.
Medication Review
Where clinically appropriate, review or reduce medicines that lower blood pressure, cause volume depletion, slow the sinus rate, impair atrioventricular conduction, or worsen orthostatic hypotension. Changes must balance syncope prevention against the underlying indication for each medicine.
Management of Vasodepressor Carotid Sinus Syndrome
- Encourage adequate fluid intake
- Consider increased dietary salt when not contraindicated
- Reduce unnecessary hypotensive medication
- Use compression garments where appropriate
- Treat coexisting orthostatic hypotension
- Consider specialist-directed midodrine or fludrocortisone in selected patients
Evidence for pharmacological therapy is limited. Treatment should be individualised, particularly in patients with hypertension, heart failure, renal impairment, or urinary retention.
Cardiac Pacing
Dual-chamber pacing is indicated or strongly considered for patients older than 40 years with severe, recurrent, unpredictable syncope caused by cardioinhibitory carotid sinus syndrome, particularly when carotid sinus massage reproduces symptoms with a documented asystolic response.3,5
A pacemaker treats the cardioinhibitory component—not the carotid sinus reflex itself. Before implantation, confirm that the patient’s symptoms are reproduced with documented cardioinhibition and assess for an important vasodepressor component.
Complications & Prognosis
Complications
- Recurrent syncope
- Falls and fractures
- Head injury
- Motor-vehicle or occupational accidents
- Functional decline and fear of falling
- Loss of independence
- Medication-related hypertension or fluid retention
- Pacemaker complications where device therapy is required
Rare neurological complications, including transient ischaemic attack or stroke, may occur during carotid sinus massage. Careful patient selection and proper monitoring minimise this risk.1
Prognosis
Carotid sinus hypersensitivity itself does not necessarily cause symptoms or require treatment. Prognosis is determined by whether clinically significant carotid sinus syndrome is present, the frequency and unpredictability of syncope, associated cardiovascular disease, and the risk of traumatic injury.
References
- Brignole M, Moya A, de Lange FJ, Deharo JC, Elliott PM, Fanciulli A, et al. 2018 ESC guidelines for the diagnosis and management of syncope. Eur Heart J. 2018;39(21):1883–1948. doi:10.1093/eurheartj/ehy037.
- Brignole M, Moya A, de Lange FJ, Deharo JC, Elliott PM, Fanciulli A, et al. Practical instructions for the 2018 ESC guidelines for the diagnosis and management of syncope. Eur Heart J. 2018;39(21):e43–e80. doi:10.1093/eurheartj/ehy071.
- Glikson M, Nielsen JC, Kronborg MB, Michowitz Y, Auricchio A, Barbash IM, et al. 2021 ESC guidelines on cardiac pacing and cardiac resynchronization therapy. Eur Heart J. 2021;42(35):3427–3520. doi:10.1093/eurheartj/ehab364.
- Shen WK, Sheldon RS, Benditt DG, Cohen MI, Forman DE, Goldberger ZD, et al. 2017 ACC/AHA/HRS guideline for the evaluation and management of patients with syncope. Circulation. 2017;136(5):e60–e122. doi:10.1161/CIR.0000000000000499.
- Glikson M, Nielsen JC, Kronborg MB, Michowitz Y, Auricchio A, Barbash IM, et al. 2021 ESC guidelines on cardiac pacing and cardiac resynchronization therapy. Europace. 2022;24(1):71–164. doi:10.1093/europace/euab232.