

Overview
Brain herniation is the pathological displacement of brain tissue across rigid intracranial structures, such as the falx cerebri or tentorium cerebelli, or through an opening such as the foramen magnum. It develops when a pressure gradient forces tissue from one intracranial compartment into another.1
Herniation may compress the brainstem, cranial nerves and cerebral vessels, causing ischaemia, haemorrhage, obstructive hydrocephalus, respiratory failure and death. It is a time-critical neurological emergency: treatment must begin immediately when herniation is clinically suspected and should not be delayed while awaiting imaging.2
Acute brain herniation is a “brain code”. A rapidly falling level of consciousness, new pupillary abnormality or abnormal posturing requires immediate treatment and urgent neurosurgical involvement.
Definition
- Brain herniation
- Pathological displacement of brain tissue from its normal compartment across a rigid dural structure or cranial opening.
- Intracranial pressure
- Pressure within the cranial vault, determined by the combined volumes of brain tissue, blood and cerebrospinal fluid.
- Mass effect
- Compression or displacement of intracranial structures by an expanding lesion or cerebral oedema.
- Midline shift
- Displacement of central cerebral structures away from their normal position, usually due to asymmetric mass effect.
- Cerebral perfusion pressure
- The pressure gradient driving cerebral blood flow, calculated as mean arterial pressure minus intracranial pressure.
Anatomy & Physiology
The skull is a fixed compartment containing:
- Brain tissue
- Cerebral blood
- Cerebrospinal fluid (CSF)
According to the Monro–Kellie doctrine, an increase in one component must initially be compensated by a reduction in another. Early compensation occurs through displacement of CSF into the spinal canal and reduction of intracranial venous blood.
Once these compensatory mechanisms are exhausted, small increases in intracranial volume produce a steep rise in intracranial pressure (ICP).
Important intracranial boundaries include:
- Falx cerebri: separates the cerebral hemispheres.
- Tentorium cerebelli: separates the cerebral hemispheres from the cerebellum and posterior fossa.
- Tentorial incisura: opening through which the midbrain passes.
- Foramen magnum: opening through which the medulla continues into the spinal cord.
- Skull defects: surgical or traumatic openings through which extracranial herniation may occur.
Aetiology & Risk Factors
Aetiology
Brain herniation usually results from an expanding intracranial lesion, cerebral oedema or impaired CSF drainage.2
Common causes include:
- Intracranial haemorrhage
- Extradural haematoma
- Subdural haematoma
- Intracerebral haemorrhage
- Haemorrhagic transformation of cerebral infarction
- Traumatic brain injury
- Cerebral contusion
- Diffuse cerebral oedema
- Expanding traumatic haematoma
- Ischaemic stroke
- Particularly malignant middle cerebral artery or cerebellar infarction
- Intracranial mass lesions
- Primary or metastatic brain tumour
- Brain abscess
- Infection and inflammation
- Encephalitis
- Meningitis with cerebral oedema
- Obstructive hydrocephalus
- Acute hepatic encephalopathy with cerebral oedema
- Post-neurosurgical complications
- Haemorrhage
- Oedema
- CSF obstruction
- Intracranial hypotension
- CSF over-drainage or leakage may rarely cause downward or paradoxical herniation.
Risk Factors
Factors increasing the likelihood of herniation or rapid deterioration include:
- Large or rapidly expanding intracranial lesion
- Posterior fossa lesion, where limited space permits little compensation
- Severe traumatic brain injury
- Anticoagulant or antiplatelet therapy in a patient with intracranial haemorrhage
- Coagulopathy
- Delayed recognition of neurological deterioration
- Hypoxia, hypercapnia or hypotension
- Fever, seizures and severe agitation, which increase cerebral metabolic demand
- Obstruction or excessive drainage of a ventricular or lumbar CSF device
- Lumbar puncture in the presence of a clinically significant intracranial pressure gradient
Pathophysiology
An expanding lesion or cerebral oedema increases intracranial volume. CSF and venous blood are initially displaced, preserving a relatively stable ICP.
When compensation is exhausted:
- ICP rises rapidly.
- Cerebral perfusion pressure falls.
- Cerebral blood flow becomes inadequate.
- Ischaemia and cytotoxic oedema develop.
- Further swelling increases the pressure gradient.
- Brain tissue is displaced across a dural boundary or cranial opening.
- Cranial nerves, cerebral vessels and the brainstem become compressed.
- Progressive brainstem dysfunction causes coma, loss of protective reflexes, respiratory failure and cardiovascular collapse.
This creates a vicious cycle of raised ICP → reduced perfusion → ischaemia → oedema → further raised ICP.
Why does uncal herniation often cause an ipsilateral fixed, dilated pupil?
The uncus compresses the ipsilateral oculomotor nerve against the tentorial edge. The superficial parasympathetic fibres controlling pupillary constriction are affected early, producing loss of the light reflex and pupillary dilatation.
Classification
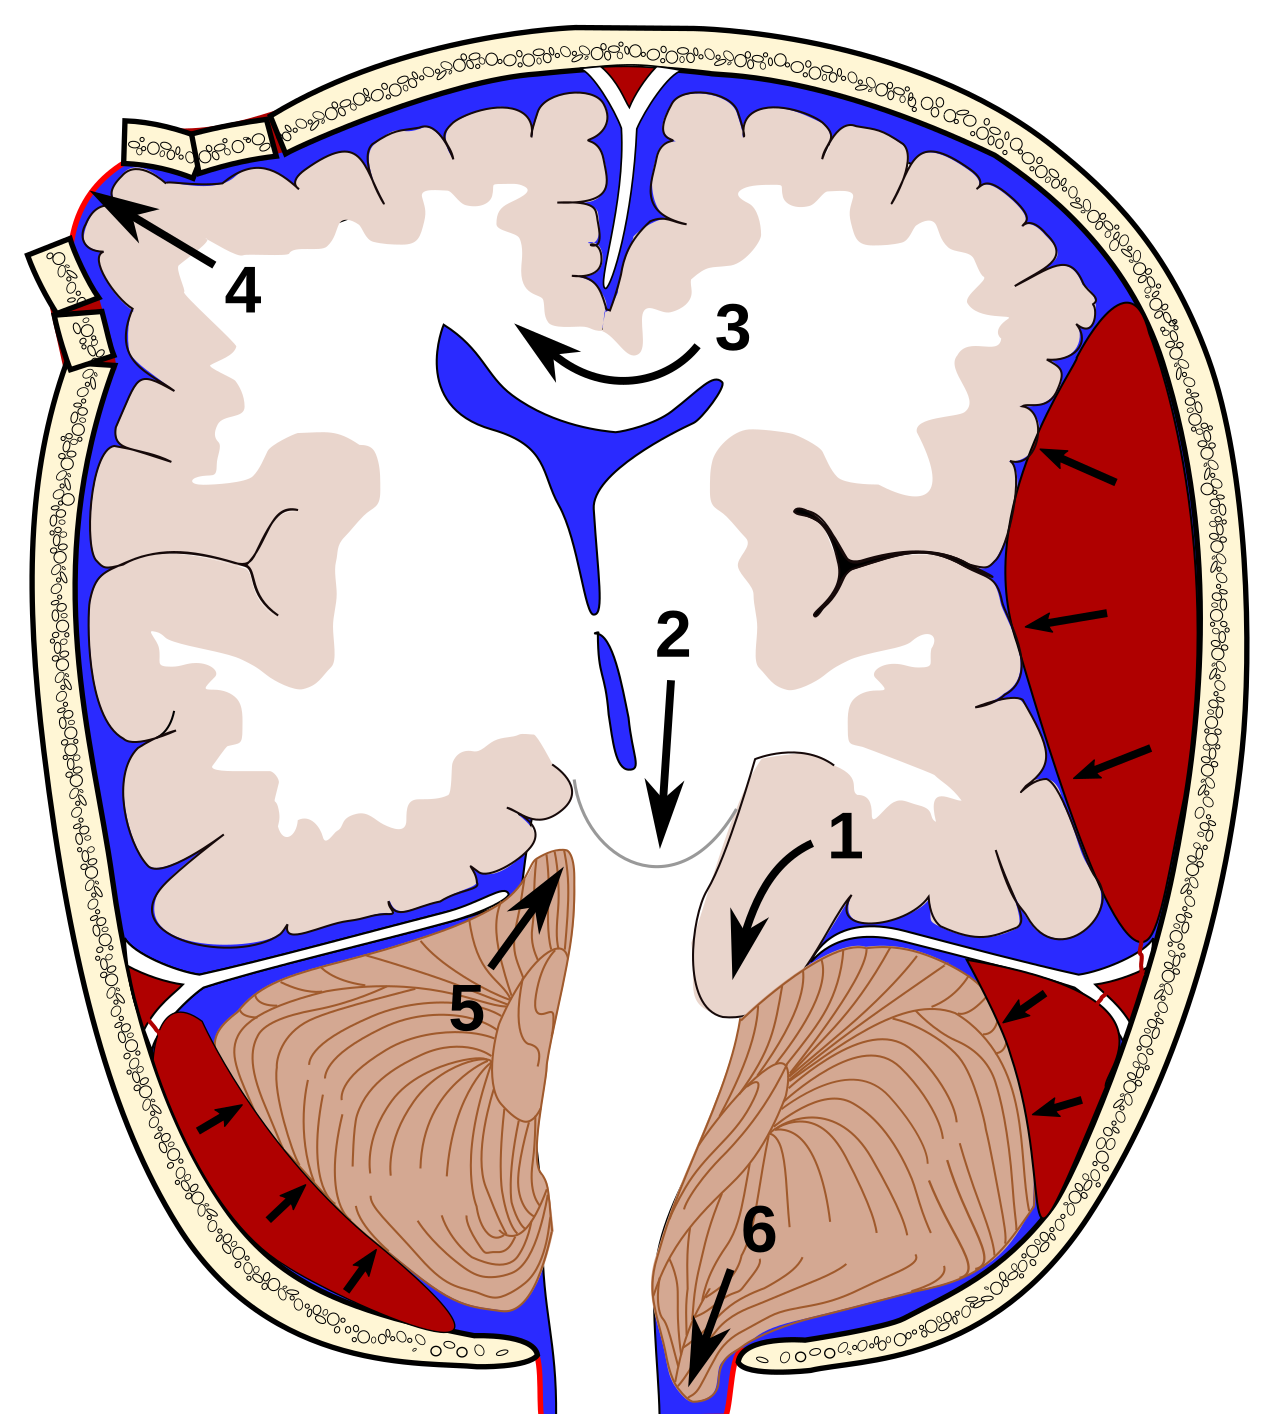
Brain herniation is classified according to the direction and anatomical site of tissue displacement.1
| Type | Tissue displacement | Important structures affected | Characteristic features |
|---|---|---|---|
| Subfalcine | Cingulate gyrus moves beneath the falx cerebri | Anterior cerebral artery | Contralateral leg weakness; anterior cerebral artery infarction |
| Uncal transtentorial | Medial temporal lobe and uncus move through the tentorial incisura | Oculomotor nerve, midbrain and posterior cerebral artery | Ipsilateral fixed dilated pupil, reduced consciousness and contralateral weakness |
| Central transtentorial | Diencephalon and midbrain move downward through the tentorial incisura | Diencephalon, midbrain and brainstem perforating vessels | Progressive coma, small then fixed pupils, abnormal posturing and disordered respiration |
| Tonsillar | Cerebellar tonsils move through the foramen magnum | Medulla and upper cervical spinal cord | Respiratory irregularity, bradycardia, hypotension and cardiorespiratory arrest |
| Upward transtentorial | Cerebellum moves upward through the tentorial incisura | Midbrain and cerebral aqueduct | Reduced consciousness, vertical gaze abnormalities and obstructive hydrocephalus |
| Transcalvarial | Brain tissue moves through a skull defect | Cortex and cortical vessels at the defect | Focal neurological deficits and tissue ischaemia |
| Paradoxical | Brain tissue shifts towards or beneath a craniectomy defect because of low intracranial pressure | Diencephalon and brainstem | Neurological deterioration following CSF loss or excessive CSF drainage |
Clinical Manifestations
The presentation depends on the rate of progression, underlying lesion and anatomical pattern of herniation.
Early features of raised ICP
- Headache
- Nausea and vomiting
- Drowsiness, confusion or behavioural change
- Agitation
- Papilloedema, although this may be absent in acute deterioration
- Sixth cranial nerve palsy
- New focal neurological deficit
- Seizures
Features suggesting evolving herniation
- Rapid fall in Glasgow Coma Scale score
- New anisocoria
- Sluggish or absent pupillary response
- Fixed, dilated pupil
- New hemiparesis
- Decorticate or decerebrate posturing
- Abnormal eye position or loss of oculocephalic responses
- Abnormal respiratory pattern
- Loss of corneal, gag or cough reflexes
- Cushing response:
- Arterial hypertension with widening pulse pressure
- Bradycardia
- Irregular respiration
Cushing’s response is a late and ominous sign. Do not wait for the complete triad before treating suspected raised intracranial pressure or herniation.
Specific manifestations based on classification
Uncal herniation
Uncal herniation classically produces:
- Ipsilateral pupillary dilatation and loss of the light reflex
- Ptosis and impaired eye adduction, elevation and depression
- Progressive reduction in consciousness
- Contralateral hemiparesis from cerebral peduncle compression
- Posterior cerebral artery compression, causing occipital infarction
Occasionally, the contralateral cerebral peduncle is compressed against the tentorial edge. This produces weakness on the same side as the mass lesion, known as the Kernohan notch phenomenon.
The Kernohan notch phenomenon is a false-localising sign. Ipsilateral weakness does not exclude an ipsilateral intracranial mass because the opposite cerebral peduncle may be compressed against the tentorium.
Central transtentorial herniation
Central herniation may produce progressive rostrocaudal deterioration:
- Declining consciousness
- Initially small, reactive pupils
- Loss of pupillary and other brainstem reflexes
- Cheyne–Stokes or other abnormal respiratory patterns
- Decorticate posturing progressing to decerebrate posturing
- Flaccidity and cardiorespiratory failure in the terminal stage
Tonsillar herniation
Tonsillar herniation compresses the medulla and may cause:
- Rapidly declining consciousness
- Neck stiffness or occipital pain
- Abnormal or absent respirations
- Loss of gag and cough reflexes
- Bradycardia and haemodynamic instability
- Sudden cardiorespiratory arrest
Diagnosis
Brain herniation is primarily an urgent clinical and radiological diagnosis. A compatible acute neurological deterioration, particularly falling consciousness, pupillary change or abnormal posturing, should trigger immediate stabilisation and empiric ICP-lowering treatment while definitive imaging and neurosurgical assessment are arranged.2
Neuroimaging
What to notice
Detailed image description
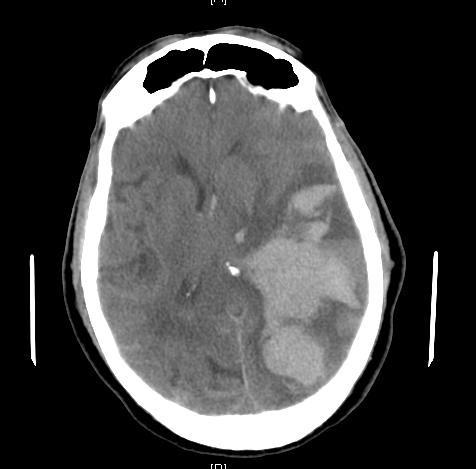
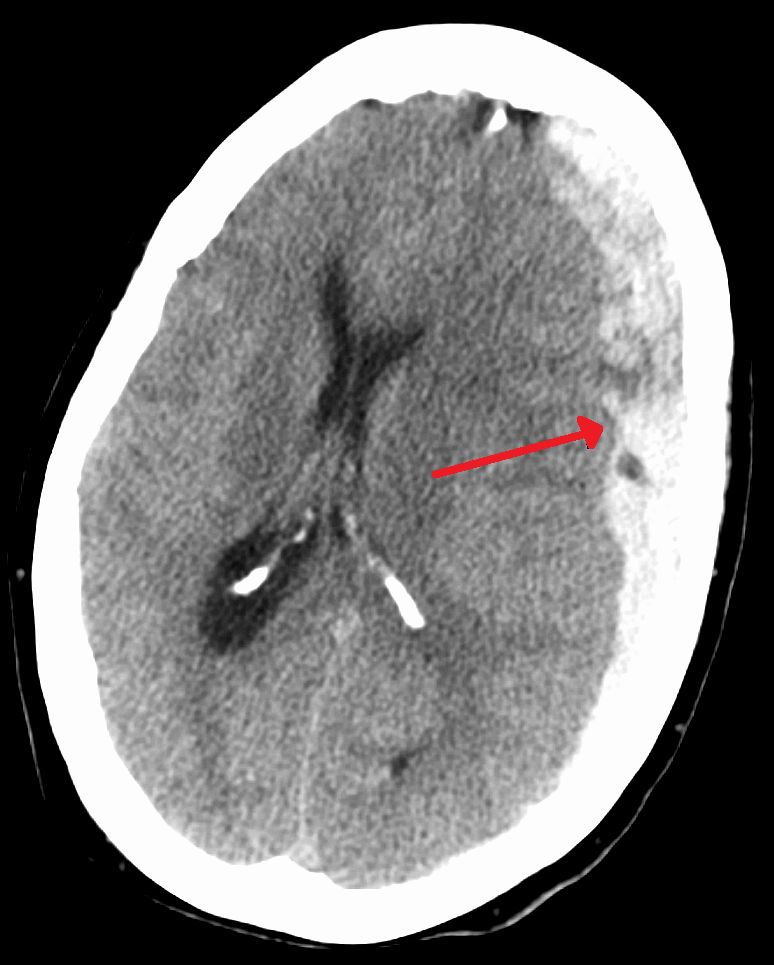
Urgent non-contrast CT brain is generally the first-line investigation because it is rapid, widely available and able to identify haemorrhage, mass lesions, hydrocephalus, cerebral oedema and major tissue displacement.1,3
Important CT features include:
- Effacement of cortical sulci
- Compression or obliteration of basal cisterns
- Midline shift
- Ventricular compression
- Contralateral ventricular dilatation from CSF obstruction
- Displacement of the uncus or cerebellar tonsils
- Brainstem distortion
- Haemorrhage, infarction, mass lesion or hydrocephalus
- Secondary vascular-territory infarction
What to notice
Detailed image description
What to notice
Detailed image description
MRI brain provides greater anatomical detail but is usually reserved for a sufficiently stable patient when CT is non-diagnostic, posterior fossa pathology requires clarification or an underlying lesion needs further characterisation. CT remains the preferred initial modality in a critically deteriorating patient.1,3
CT angiography, CT venography or other vascular imaging should be directed by the suspected cause, such as arterial occlusion, aneurysmal haemorrhage or cerebral venous thrombosis—not performed routinely in every patient.
Imaging demonstrates the anatomy, but the neurological trend determines urgency. A patient with rapidly worsening consciousness and a new pupillary abnormality may require treatment before CT confirms the full radiological pattern of herniation.
Intracranial pressure monitoring
Invasive ICP monitoring may be used in selected critically ill patients when it will guide ongoing management. In severe traumatic brain injury, treatment of ICP above 22 mmHg is recommended because higher values are associated with increased mortality; decisions should also incorporate the neurological examination and CT findings.4
ICP monitoring does not replace repeated clinical examination and neuroimaging, and it should not delay emergency treatment or evacuation of a surgically remediable lesion.
Targeted laboratory investigations
Investigations should identify reversible contributors, treatment complications and the underlying cause:
- Full blood count
- Electrolytes, urea, creatinine and serum glucose
- Coagulation profile
- Blood gas to assess oxygenation, ventilation and acid–base status
- Serum osmolality when mannitol or repeated hyperosmolar therapy is used
- Group and crossmatch when emergency surgery is anticipated
- Blood cultures and inflammatory investigations when CNS infection is suspected
- Toxicology testing only when supported by the clinical context
Lumbar puncture
Lumbar puncture is contraindicated when a clinically significant intracranial pressure gradient or space-occupying lesion is suspected because removal of spinal CSF may precipitate or worsen cerebral or tonsillar herniation.5
Do not perform lumbar puncture in a patient with suspected brain herniation, a focal mass lesion or marked pressure gradient. A normal CT does not automatically make lumbar puncture safe when the clinical features remain concerning.
Treatment
Suspected brain herniation requires simultaneous resuscitation, ICP reduction, diagnostic evaluation and definitive treatment of the underlying lesion.2
Immediate stabilisation
- Activate emergency neurological and neurosurgical pathways.
- Stabilise airway, breathing and circulation.
- Intubate when airway reflexes or ventilation are inadequate.
- Avoid hypoxaemia and hypotension.
- Elevate the head of the bed to approximately 30°.
- Keep the head and neck in a neutral position to facilitate cerebral venous drainage.
- Remove tight cervical ties or other obstruction to jugular venous outflow while maintaining required spinal precautions.
- Treat fever, severe agitation, pain and seizures.
- Avoid hypotonic intravenous fluids.
- Correct severe electrolyte and glucose disturbances.
- Reverse anticoagulation urgently when clinically indicated.
Hyperosmolar therapy
Administer bolus hyperosmolar therapy for acute clinical deterioration from raised ICP or suspected herniation:
- Hypertonic saline increases serum osmolality and draws water from brain tissue while supporting intravascular volume.
- Mannitol produces osmotic diuresis and reduces brain water but may worsen hypovolaemia or hypotension.
Agent, concentration and dose should follow the local neurocritical-care protocol and be selected according to haemodynamic status, renal function, serum sodium and the underlying neurological condition. Available evidence supports reduction in ICP or cerebral oedema, but does not establish that one hyperosmolar agent consistently improves long-term neurological outcomes across all causes.6
Monitor:
- Serum sodium
- Serum osmolality
- Fluid balance
- Blood pressure
- Renal function
- Acid–base status
Ventilation
Maintain adequate oxygenation and avoid hypercapnia.
Brief controlled hyperventilation may be used as a temporary rescue measure in impending herniation because reduced PaCO₂ causes cerebral vasoconstriction and rapidly lowers cerebral blood volume. Its effect is short-lived and excessive or prolonged hyperventilation may worsen cerebral ischaemia. Prophylactic prolonged hyperventilation is therefore not recommended.4
Hyperventilation is a bridge, not definitive treatment. Reserve it for acute neurological deterioration while hyperosmolar therapy, imaging and neurosurgical intervention are being arranged.
Definitive treatment
Definitive management depends on the cause:
- Emergency evacuation of an extradural, subdural or intracerebral haematoma
- Resection or decompression of a mass lesion
- Decompressive craniectomy for selected patients with refractory intracranial hypertension or malignant cerebral infarction
- Posterior fossa decompression for an expanding cerebellar lesion
- External ventricular drainage for acute obstructive hydrocephalus
- Antimicrobial therapy and source control for intracranial infection
- Reperfusion or neurosurgical management for selected ischaemic strokes
- Correction of hepatic failure, metabolic disturbance or other systemic cause
The response to treatment should be assessed using serial neurological examination, pupil assessment, physiological monitoring and repeat imaging when clinically indicated.
Corticosteroids
Corticosteroids are not general treatment for brain herniation.
They may reduce vasogenic oedema surrounding selected brain tumours but are not recommended for traumatic brain injury and should not be used routinely for cerebral oedema from intracerebral haemorrhage or ischaemic stroke. High-dose methylprednisolone is contraindicated in severe traumatic brain injury because it is associated with increased mortality.4,6
The treatment must match the mechanism of oedema. Corticosteroids may help vasogenic oedema around a tumour, but they do not reverse cytotoxic oedema after ischaemic stroke and are harmful in severe traumatic brain injury.
Complications & Prognosis
Complications
Brain herniation may cause:
- Brainstem compression and infarction
- Posterior cerebral artery infarction
- Anterior cerebral artery infarction
- Secondary brainstem haemorrhage, including Duret haemorrhages
- Obstructive hydrocephalus
- Cranial nerve palsies
- Persistent motor deficits
- Seizures
- Loss of airway-protective reflexes
- Respiratory arrest
- Cardiovascular collapse
- Brain death
- Death
Prognosis
Prognosis depends on:
- Underlying cause
- Anatomical pattern of herniation
- Speed of progression
- Duration and severity of brainstem compression
- Presence of hypoxia or hypotension
- Development of secondary cerebral infarction or haemorrhage
- Baseline neurological status
- Time to recognition and definitive treatment
- Reversibility of the underlying lesion
Early herniation may be reversible when recognised promptly and the causative lesion can be rapidly treated. Prolonged brainstem compression, absent brainstem reflexes, refractory intracranial hypertension and cardiorespiratory arrest are associated with a poor prognosis.2
Prognostication should be cautious immediately after resuscitation. Sedatives, neuromuscular blockade, hypothermia, seizures and metabolic disturbances may confound the neurological examination.
References
- Riveros Gilardi B, Muñoz López JI, Hernández Villegas AC, Garay Mora JA, Rico Rodríguez OC, Chávez Appendini R, et al. Types of cerebral herniation and their imaging features. Radiographics. 2019;39(6):1598–1610. doi:10.1148/rg.2019190018
- Cadena R, Shoykhet M, Ratcliff JJ. Emergency Neurological Life Support: intracranial hypertension and herniation. Neurocrit Care. 2017;27(Suppl 1):82–88. doi:10.1007/s12028-017-0454-z
- Shih RY, Burns J, Ajam AA, Broder JS, Chakraborty S, Kendi AT, et al. ACR Appropriateness Criteria Head Trauma: 2021 update. J Am Coll Radiol. 2021;18(5 Suppl):S13–S36. doi:10.1016/j.jacr.2021.01.006
- Carney N, Totten AM, O’Reilly C, Ullman JS, Hawryluk GWJ, Bell MJ, et al. Guidelines for the management of severe traumatic brain injury, fourth edition. Neurosurgery. 2017;80(1):6–15. doi:10.1227/NEU.0000000000001432
- Engelborghs S, Niemantsverdriet E, Struyfs H, Blennow K, Brouns R, Comabella M, et al. Consensus guidelines for lumbar puncture in patients with neurological diseases. Alzheimers Dement (Amst). 2017;8:111–126. doi:10.1016/j.dadm.2017.04.007
- Cook AM, Jones GM, Hawryluk GWJ, Mailloux P, McLaughlin D, Papangelou A, et al. Guidelines for the acute treatment of cerebral edema in neurocritical care patients. Neurocrit Care. 2020;32(3):647–666. doi:10.1007/s12028-020-00959-7