

Overview
Chronic inflammatory demyelinating polyradiculoneuropathy (CIDP) is an acquired immune-mediated disorder of peripheral nerves and nerve roots, causing demyelination, impaired nerve conduction, weakness, sensory disturbance and reduced or absent reflexes.
Typical CIDP causes progressive or relapsing symmetrical proximal and distal weakness with sensory loss developing over at least 8 weeks. This time course helps distinguish CIDP from the more acute Guillain–Barré syndrome.1
CIDP is treatable. Intravenous immunoglobulin (IVIG), corticosteroids and plasma exchange are established therapies.1
Definition
- Demyelination
- Damage to the myelin sheath resulting in slowed or blocked nerve conduction.
- Polyradiculoneuropathy
- A disorder affecting multiple peripheral nerves and their nerve roots.
- Conduction block
- Failure of an electrical impulse to travel through a segment of nerve due to focal demyelination.
- Temporal dispersion
- Spreading of the compound muscle action potential because individual nerve fibres conduct at different speeds.
- Albuminocytological dissociation
- Increased cerebrospinal-fluid protein with a normal or only mildly increased white-cell count.
Aetiology & Risk Factors
Aetiology
CIDP results from an abnormal immune response directed against peripheral nerves, causing segmental demyelination and remyelination. A specific trigger is usually not identified.
Risk Factors
- More common in adults over 50 years.
- Males are affected more frequently than females.
- CIDP-like neuropathies may occur with monoclonal gammopathy, plasma-cell disorders, lymphoma and HIV.
- Diabetes may coexist with CIDP but diabetic neuropathy itself can mimic the condition.
Pathophysiology
Immune-mediated injury to peripheral nerve myelin and nodal structures causes slowing or blockade of nerve conduction. Repeated demyelination and remyelination may produce onion-bulb formations. Prolonged disease can result in secondary axonal loss and permanent neurological disability.
Clinical Manifestations
Typical CIDP
- Progressive or relapsing symptoms over ≥8 weeks.
- Symmetrical proximal and distal muscle weakness.
- Distal sensory loss and paraesthesia.
- Impaired vibration and joint-position sensation.
- Sensory ataxia.
- Reduced or absent deep-tendon reflexes.
- Neuropathic pain may occur but is usually not the dominant feature.
- Cranial-nerve involvement is uncommon.
- Prominent respiratory or autonomic involvement should prompt consideration of an alternative diagnosis.
CIDP Variants
- Distal CIDP: predominantly distal weakness and sensory loss, usually affecting the legs more than the arms.
- Multifocal CIDP: asymmetrical sensory and motor deficits involving separate peripheral nerves.
- Focal CIDP: restricted to one limb or nerve territory.
- Motor CIDP: weakness without objective sensory loss; multifocal motor neuropathy is an important differential.
- Sensory CIDP: sensory loss, paraesthesia or sensory ataxia without weakness at presentation.
Diagnosis & Investigations
CIDP is diagnosed from the clinical pattern, disease course and electrodiagnostic evidence of demyelination. The 2021 European Academy of Neurology/Peripheral Nerve Society criteria classify patients as CIDP or possible CIDP.1
Nerve-Conduction Studies
Nerve-conduction studies are central to diagnosis and may demonstrate:
- Reduced motor conduction velocity.
- Prolonged distal motor latency.
- Prolonged or absent F waves.
- Conduction block.
- Temporal dispersion.
Abnormalities should be demonstrated in multiple nerves and interpreted using established electrodiagnostic criteria. Mild slowing alone is insufficient to diagnose CIDP.
Cerebrospinal Fluid
Lumbar puncture may demonstrate albuminocytological dissociation with elevated CSF protein and a normal or mildly increased white-cell count.
A CSF white-cell count greater than approximately 10 cells/µL should prompt consideration of infection, malignancy or another inflammatory disorder.
Blood Investigations
Blood testing is primarily used to identify associated conditions and exclude mimics:
- HbA1c or fasting glucose.
- Vitamin B12.
- Thyroid function.
- Serum protein electrophoresis and immunofixation ± serum free light chains.
- HIV/hepatitis testing when clinically indicated.
- Anti-MAG antibodies where an IgM paraprotein and distal demyelinating neuropathy are present.
- Targeted autoimmune, infectious or genetic testing according to the presentation.
Imaging and Nerve Biopsy
Nerve ultrasound or MRI may demonstrate enlargement of proximal nerve roots, plexuses or peripheral nerves. These findings are supportive rather than diagnostic.
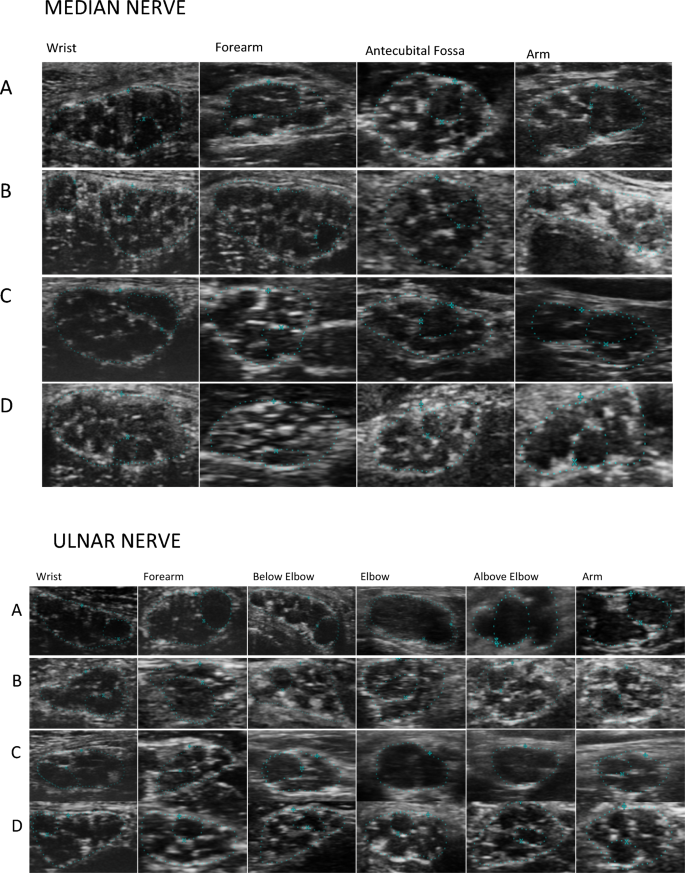
Ultra-high-frequency ultrasound comparison of nerve and fascicular morphology in typical CIDP, anti-MAG neuropathy, distal CIDP and a healthy control. Puma et al., CC BY 4.0.
What to notice
Detailed image description
Source article: https://www.nature.com/articles/s41598-024-54452-8. Figure 1. Authors: Puma A, Grecu N, Badea RȘ, et al. Licence: Creative Commons Attribution 4.0 International. Imported without modification for the CIDP Disease notes.
Nerve biopsy is not routinely required. It may be considered when an alternative diagnosis such as vasculitis, amyloidosis, sarcoidosis or an infiltrative neuropathy is suspected.
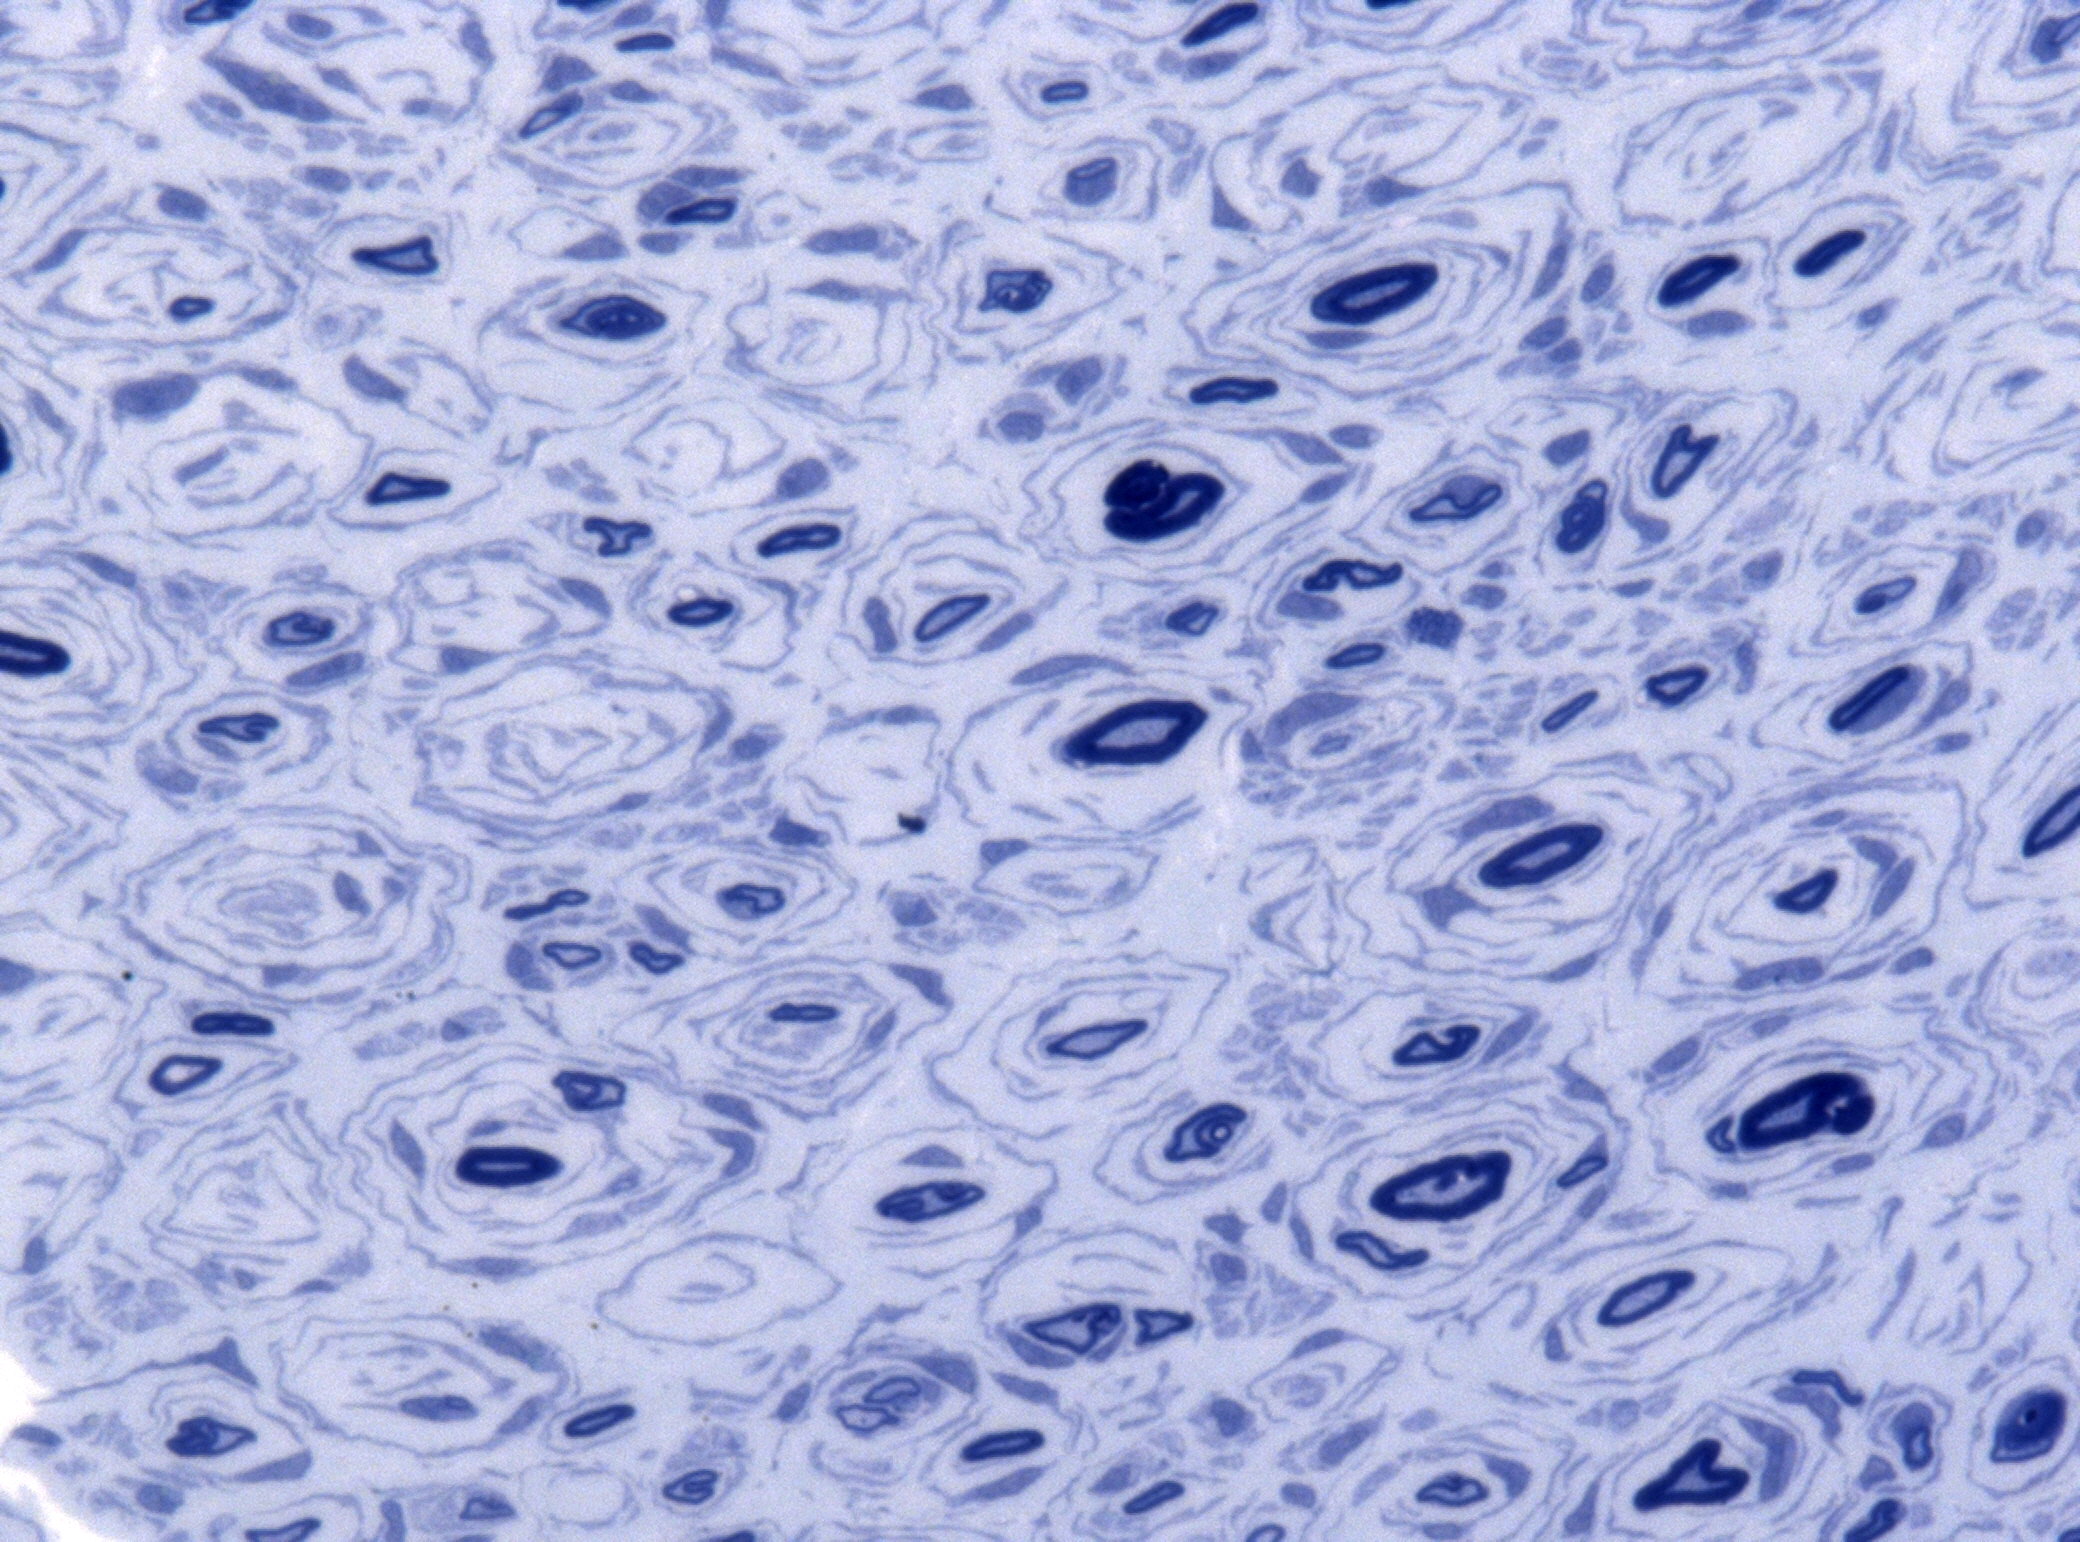
Cross-section of a peripheral nerve showing onion-bulb formations associated with repeated segmental demyelination and remyelination. Credit: Jensflorian, CC BY-SA 4.0.
What to notice
Detailed image description
Source: https://commons.wikimedia.org/wiki/File:Onion_bulbs_semi_thin_nerve_biopsy.jpg. Creator: Jensflorian. Licence: Creative Commons Attribution-ShareAlike 4.0 International. Imported without modification for the CIDP Disease notes.
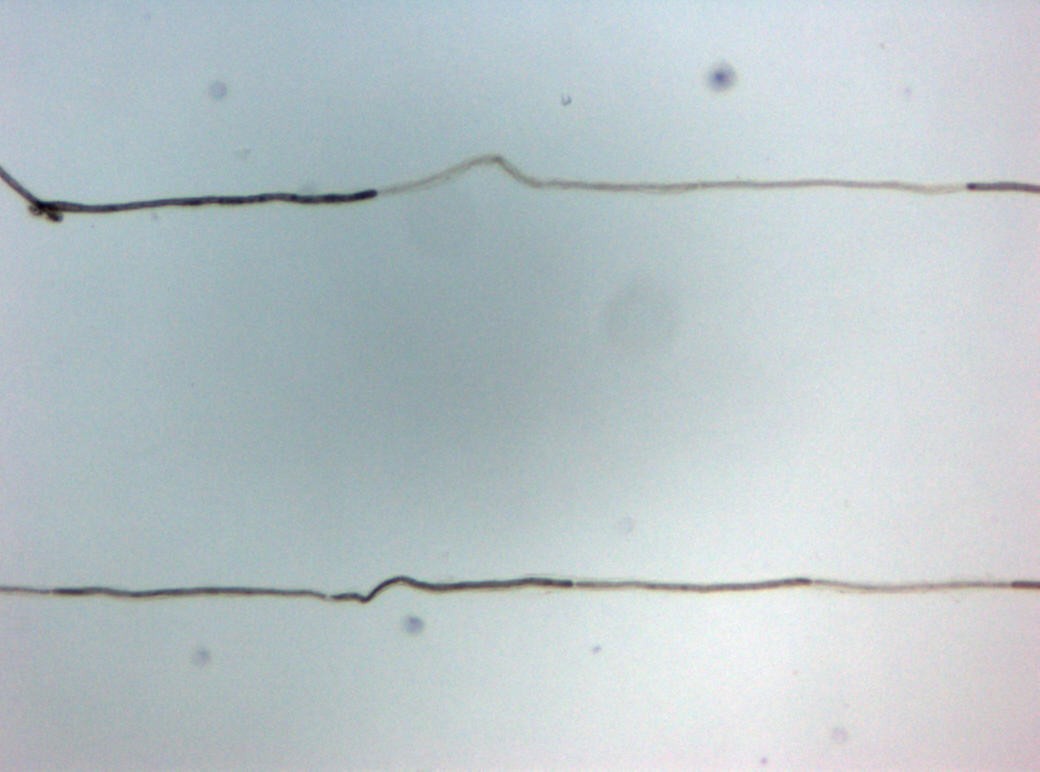
Teased nerve fibre from CIDP demonstrating segmental demyelination. Credit: Marvin 101, CC BY-SA 3.0 DE.
What to notice
Detailed image description
Source: https://commons.wikimedia.org/wiki/File:CIDP_Histopathology_Teased_fibre.jpg. Creator: Marvin 101. Licence: Creative Commons Attribution-ShareAlike 3.0 Germany. Imported without modification for the CIDP Disease notes.
Important Differential Diagnoses
- Guillain–Barré syndrome.
- Multifocal motor neuropathy.
- Anti-MAG neuropathy.
- Diabetic or hereditary polyneuropathy.
- Amyloidosis or POEMS syndrome.
- Vasculitic neuropathy.
- Autoimmune nodopathy.
- Motor neurone disease.
CIDP should not be diagnosed from elevated CSF protein or mild nerve-conduction slowing alone. The clinical pattern, time course and electrodiagnostic findings must be concordant.
Treatment
Treatment aims to improve strength and function and prevent secondary axonal loss.1
Initial Treatment
IVIG
- First-line therapy for typical CIDP and most variants.
- Common induction regimen: 2 g/kg divided over 2–5 days.
- Generally preferred initially in motor CIDP.1
Corticosteroids
- Oral or pulsed corticosteroids are effective first-line options.
- Use cautiously in pure motor CIDP because some patients may deteriorate.1
Plasma exchange
- Effective therapy, particularly when IVIG or corticosteroids are ineffective or contraindicated.
- Can produce relatively rapid improvement, although benefit may be temporary.1
Maintenance Treatment
Patients who relapse after initial improvement may require:
- Regular IVIG.
- Subcutaneous immunoglobulin.
- Maintenance corticosteroids.
- Selected use of repeated plasma exchange.
Treatment dose and interval should be individualised and periodically reduced or extended where possible to determine whether ongoing treatment is still required.1
Refractory Disease
Failure to improve should prompt reassessment of the diagnosis, adequacy of treatment and the possibility of significant irreversible axonal loss or an alternative neuropathy.
Immunosuppressive therapies such as rituximab or other steroid-sparing agents may be considered in selected refractory patients, although evidence is less robust than for established first-line therapies.
Supportive Management
- Physiotherapy and rehabilitation.
- Occupational therapy.
- Walking aids or ankle–foot orthoses when required.
- Falls prevention.
- Treatment of neuropathic pain.
- Bone protection and metabolic monitoring with prolonged corticosteroid use.
Complications & Prognosis
Complications
- Persistent weakness and impaired mobility.
- Falls due to weakness, sensory loss or ataxia.
- Muscle wasting.
- Secondary axonal loss causing irreversible disability.
- Neuropathic pain and fatigue.
- Treatment-related adverse effects.
Prognosis
Most patients improve with immunomodulatory treatment.1
The disease may be monophasic, relapsing–remitting or chronically progressive. Some patients achieve sustained remission, whereas others require prolonged maintenance treatment.
Early recognition and treatment may reduce permanent axonal loss and disability.
References
- Van den Bergh PYK, van Doorn PA, Hadden RDM, et al. European Academy of Neurology/Peripheral Nerve Society guideline on diagnosis and treatment of chronic inflammatory demyelinating polyradiculoneuropathy: report of a joint Task Force—second revision. Eur J Neurol. 2021;28(11):3556–3583. doi:10.1111/ene.14959. Available from: https://pubmed.ncbi.nlm.nih.gov/34327760/
- Puma A, Grecu N, Badea RȘ, et al. Typical CIDP, distal variant CIDP, and anti-MAG antibody neuropathy: an ultra-high frequency ultrasound comparison of nerve structure. Sci Rep. 2024;14:4643. doi:10.1038/s41598-024-54452-8. Available from: https://www.nature.com/articles/s41598-024-54452-8