

Deep Vein Thrombosis
Overview
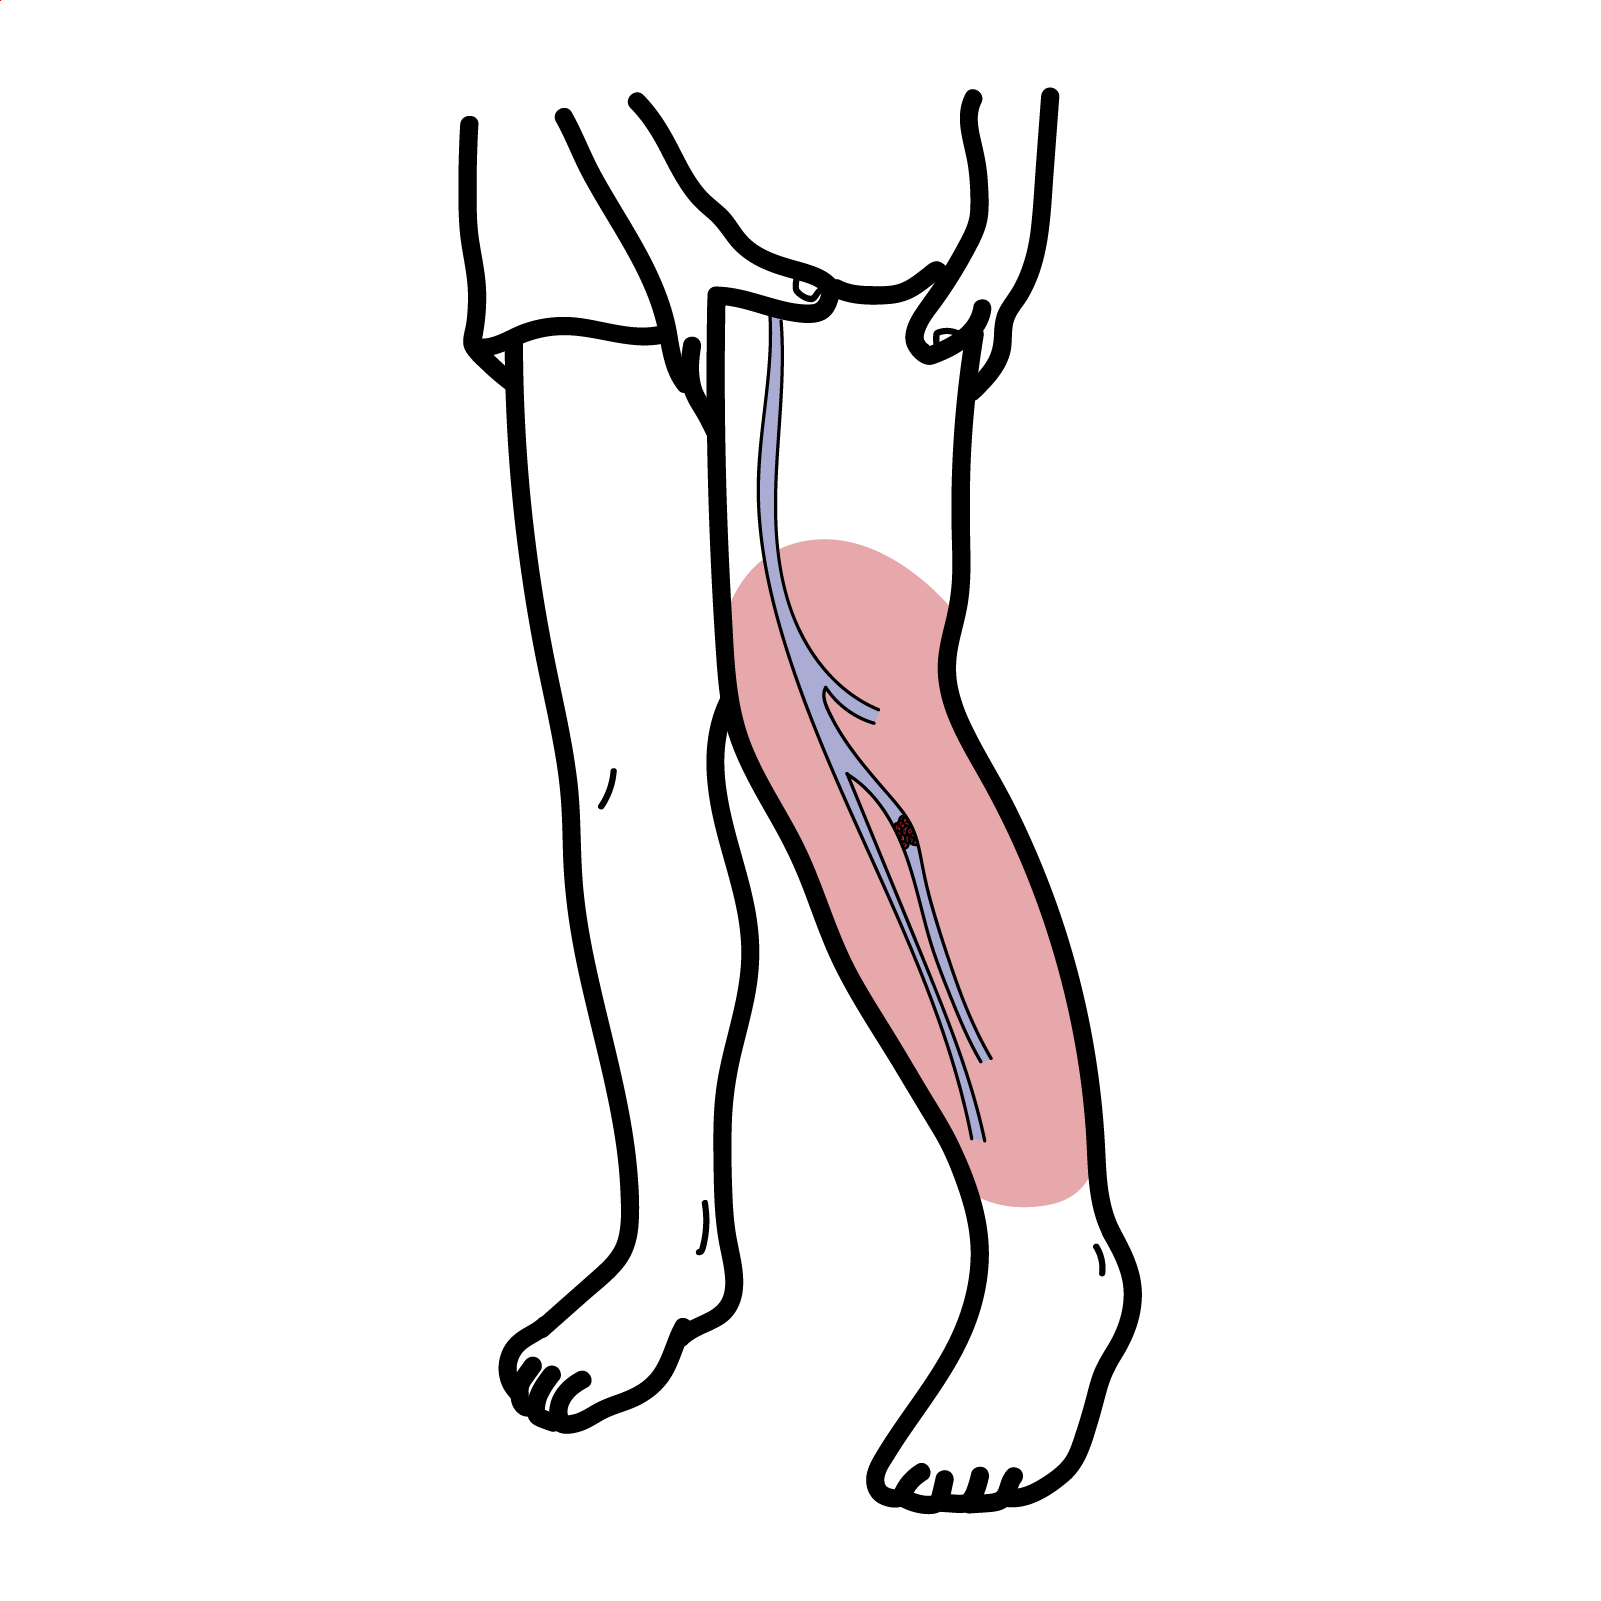
Deep vein thrombosis (DVT) is the formation of a blood clot in a vein deep under the skin 25-50% of surgical patients and many non-surgical patients. 65% of DVT are below the knee are symptomatic and rarely embolism to the lung. There are many causes of DVT.
Definition
Thrombus: blood clot
Thrombosis: blood clot that forms in a vessel and remains there
Deep Vein Thrombosis (DVT): Formation of a blood clot in one of the deep veins of the body, usually in the leg
Pulmonary Embolism (PE):occurs most often from a disloged thrombus from teh lower limb (DVT). The embolyus travels towards the lung and becomes lodged in the pulmonary artery resulting in infarction of the lung tissue.
Venous Thromboembolism (VTE): Formation, development, or existence of a blood clot or thrombus within the venous system that has/potential to embolize.
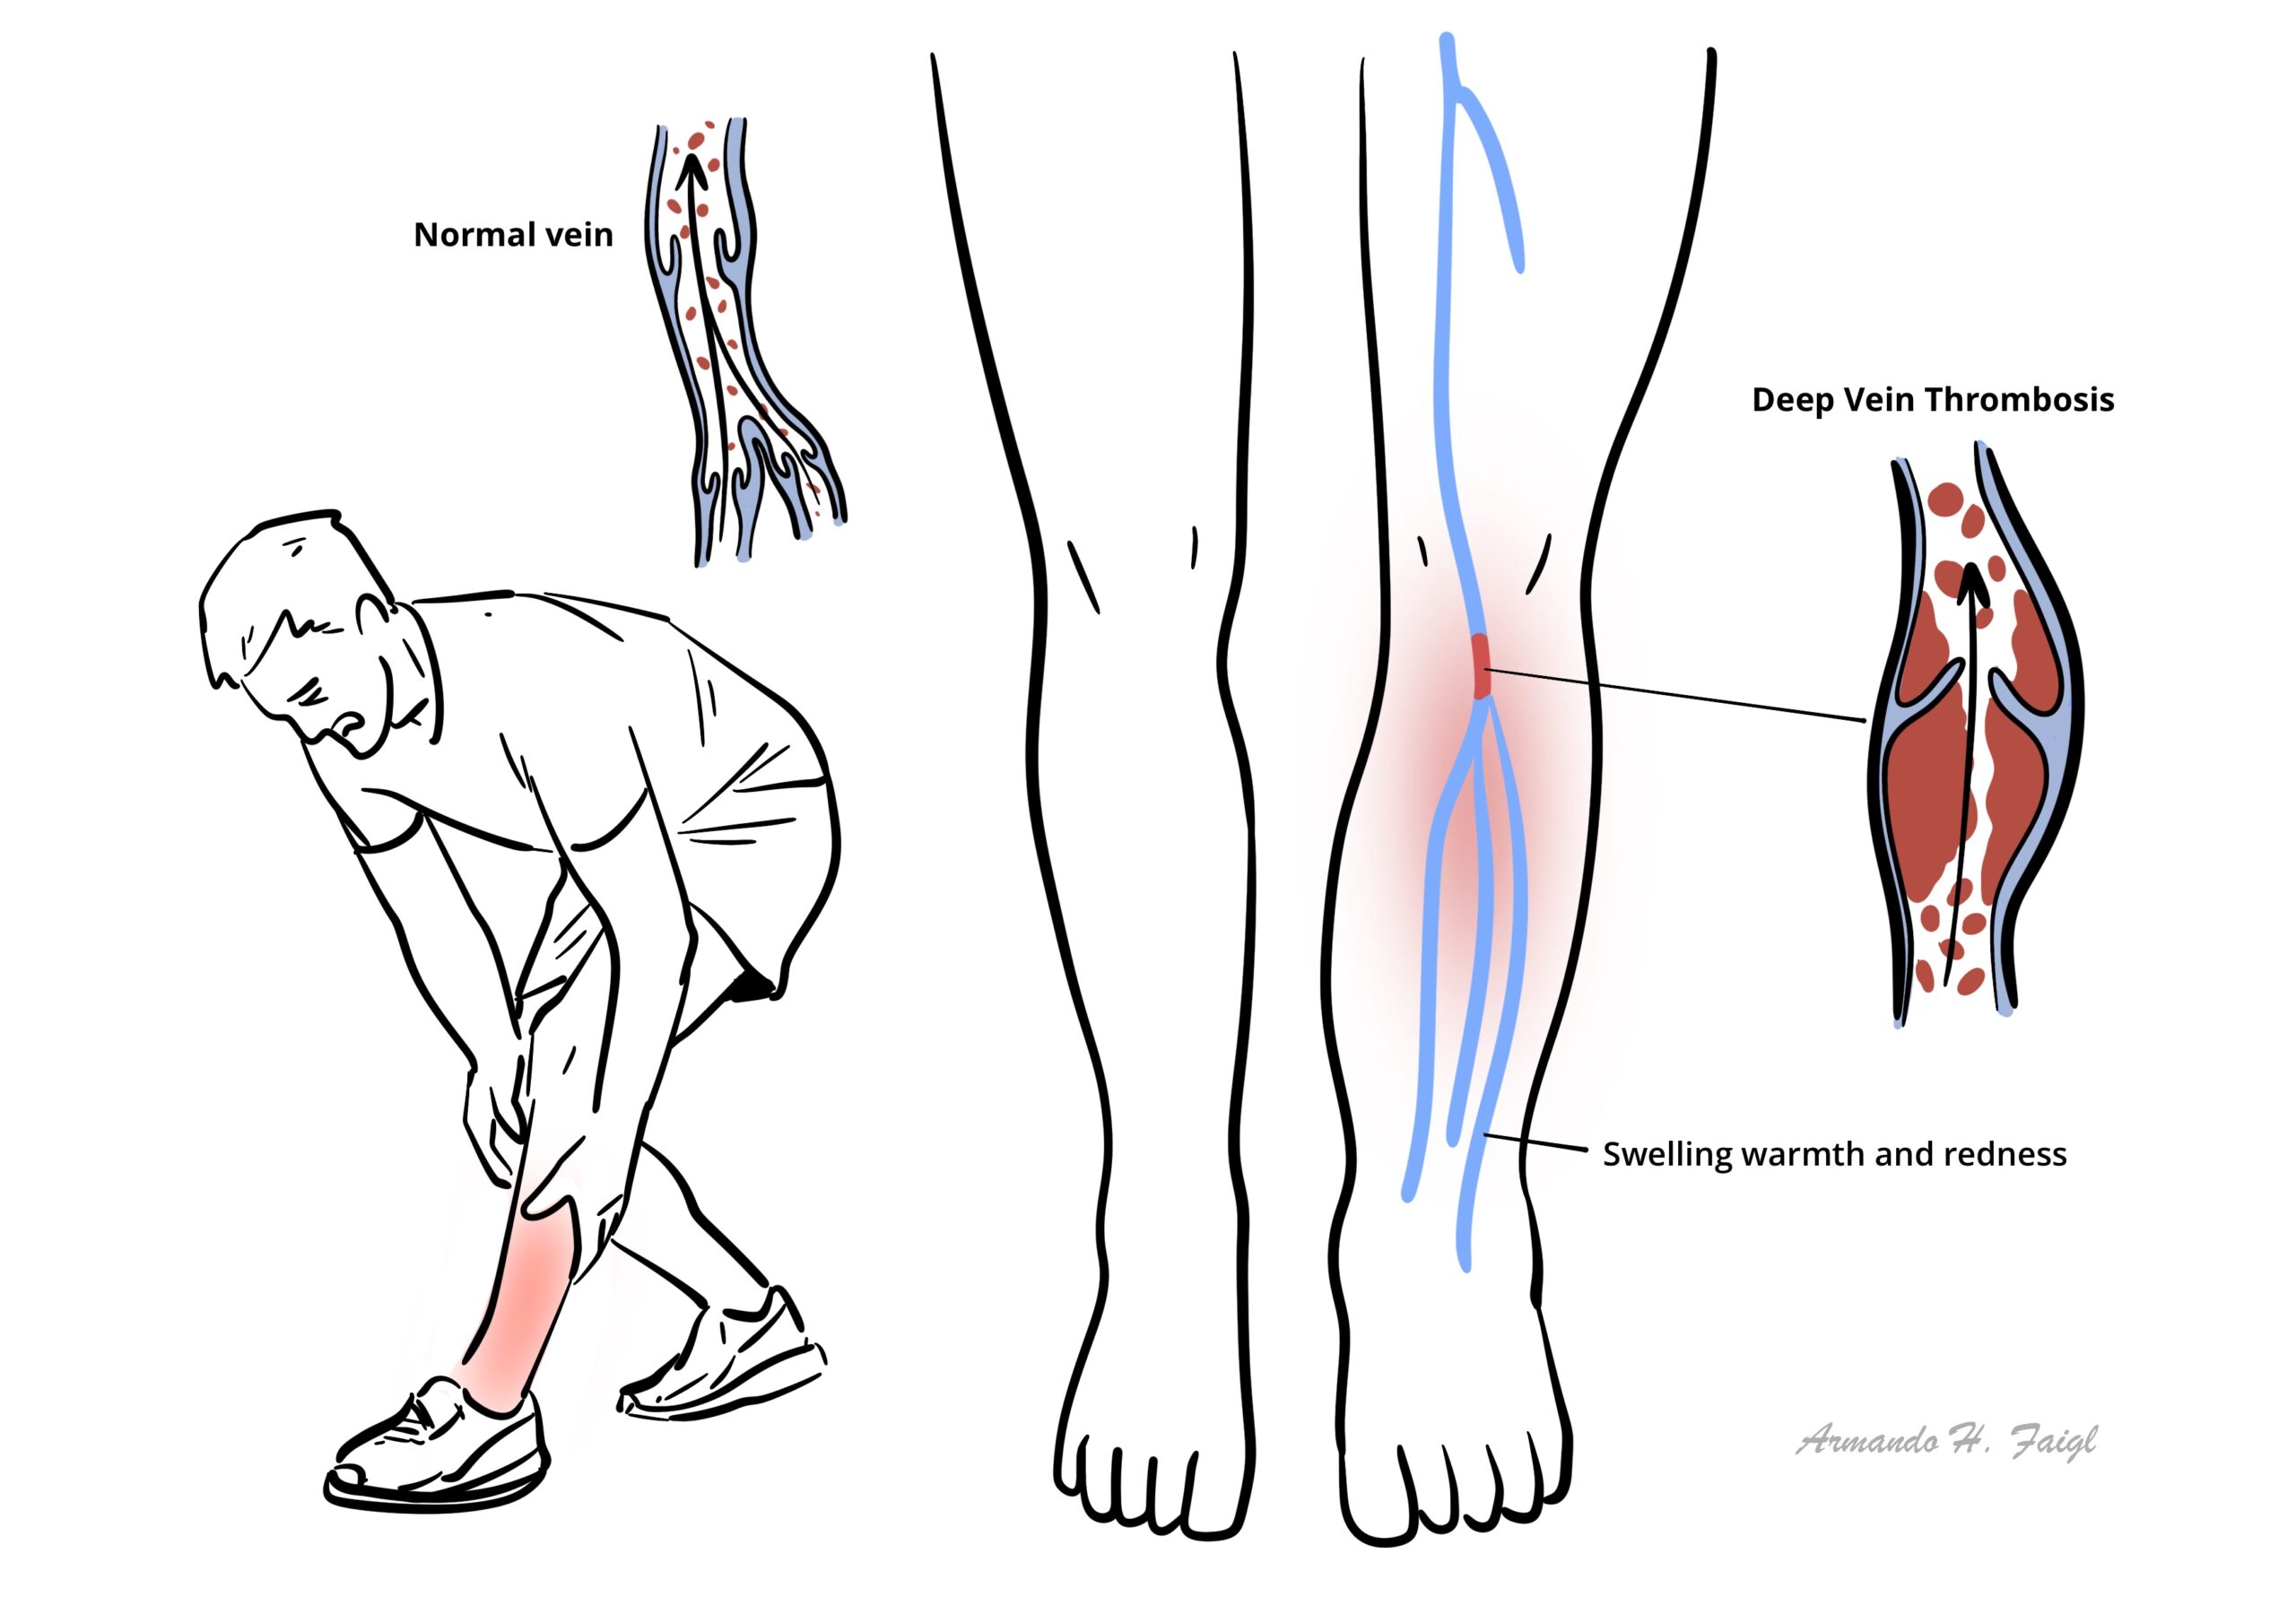
What to notice
Detailed image description
Pathophysiology
All comes down to Virchow’s Triad. Any change to Virchows triad increases the risk of VTE.
Virchows Triad: Hypercoagulability, Vessel wall injury, Stasis.
Hypercoagulability
- Malignancy
- Surgery
- Trauma
- Oral contraceptive pill
- Genetic
- Antiphosphlipid syndrome
- Hyper homocysteine level
| Inherited Thombophilias |
| Factor 5 leiden mutation |
| Pro-thrombin gene mutation |
| Protein S deficiency |
| Protein C deficiency |
Stasis
- Immobility, e.g. after surgery
- Pregnancy
- Obesity
- Heart failure
- Cast on the leg
- Extended travel in plane/vehicle
Endothelial injury
- Inflammation
- Previous thrombosis
- Atherosclerosis
- Fracture
Clinical Manifestation
Clinical Presention DVT usually affects the veins in the legs, notably the calf.
- Asymmetrical pain and/or tenderness
- Asymmetrical warmth/ erythema
- Asymmetrical swelling
Signs of Pulmonary embolism (complication of DVT)
- Breathlessness
- Chest pain
- Coughing
- Tachycardia
- Haemoptysis
Wells Criteria
| MODIFIED WELL CRITERIA | |
|---|---|
| Clinical features | Score |
| Active cancer | 1 |
| Paralysis, paresis, or recent cast immobilization of the lower extremities | 1 |
| Recently bedridden for ≥ 3 days, or major surgery within the previous 12 weeks requiring general or regional anesthesia | 1 |
| Localized tenderness along the distribution of the deep venous system | 1 |
| Entire leg swelling | 1 |
| Calf swelling at least 3 cm larger than that on the asymptomatic side | 1 |
| Pitting edema confined to the symptomatic leg | 1 |
| Collateral superficial veins (non-varicose) | 1 |
| Previously documented deep vein thrombosis | 1 |
| Alternative diagnosis at least as likely as deep vein thrombosis | 2 |
Wells Scoring System – help tailor investigations
- Low probability: 0
- Moderate probability: 1-2
- High probability: 3-8
Diagnosis
- Cellulitis
- Thrombophlebitis
- Arthritis
- Asymmetric peripheral oedema secondary to heart failure, renal disease or liver disease
- Haematoma
- Lymphoedema
- Ruptured backers cyst
- Varicose veins
D-dimer assay is only useful if it is negative; it helps in ruling out DVT.
Diagnosis
- Duplex ultrasound
- Venography (phlebography) – Gold standard
Treatment
The aim of treatment is to prevent PE, reduce morbidity and prevent or minimise the risk of developing the postphlebitic syndrome
- Pain management – analgesia +/- opioids
- Anticoagulation
- Low risk bleeding – Low molecular weight heparin (enoxaparin 1.5mg/kg SC daily)
- Average risk bleeding – Unfractionated heparin
| MANAGEMENT DURATION | |
| Clinical situation | Duration |
| VTE provoked by transient major risk factor | 3 months |
| Distal unprovoked DVT or PE | 3 months |
| First unprovoked proximal DVT or PE | 6 months |
| First unprovoked VTE plusActive malignancyMultiple thrombophiliasAntiphospholipid syndrome | Indefinite |
| Recurrent unprovoked VTE | Indefinite |
Complications & Prognosis
Complications
- Acute
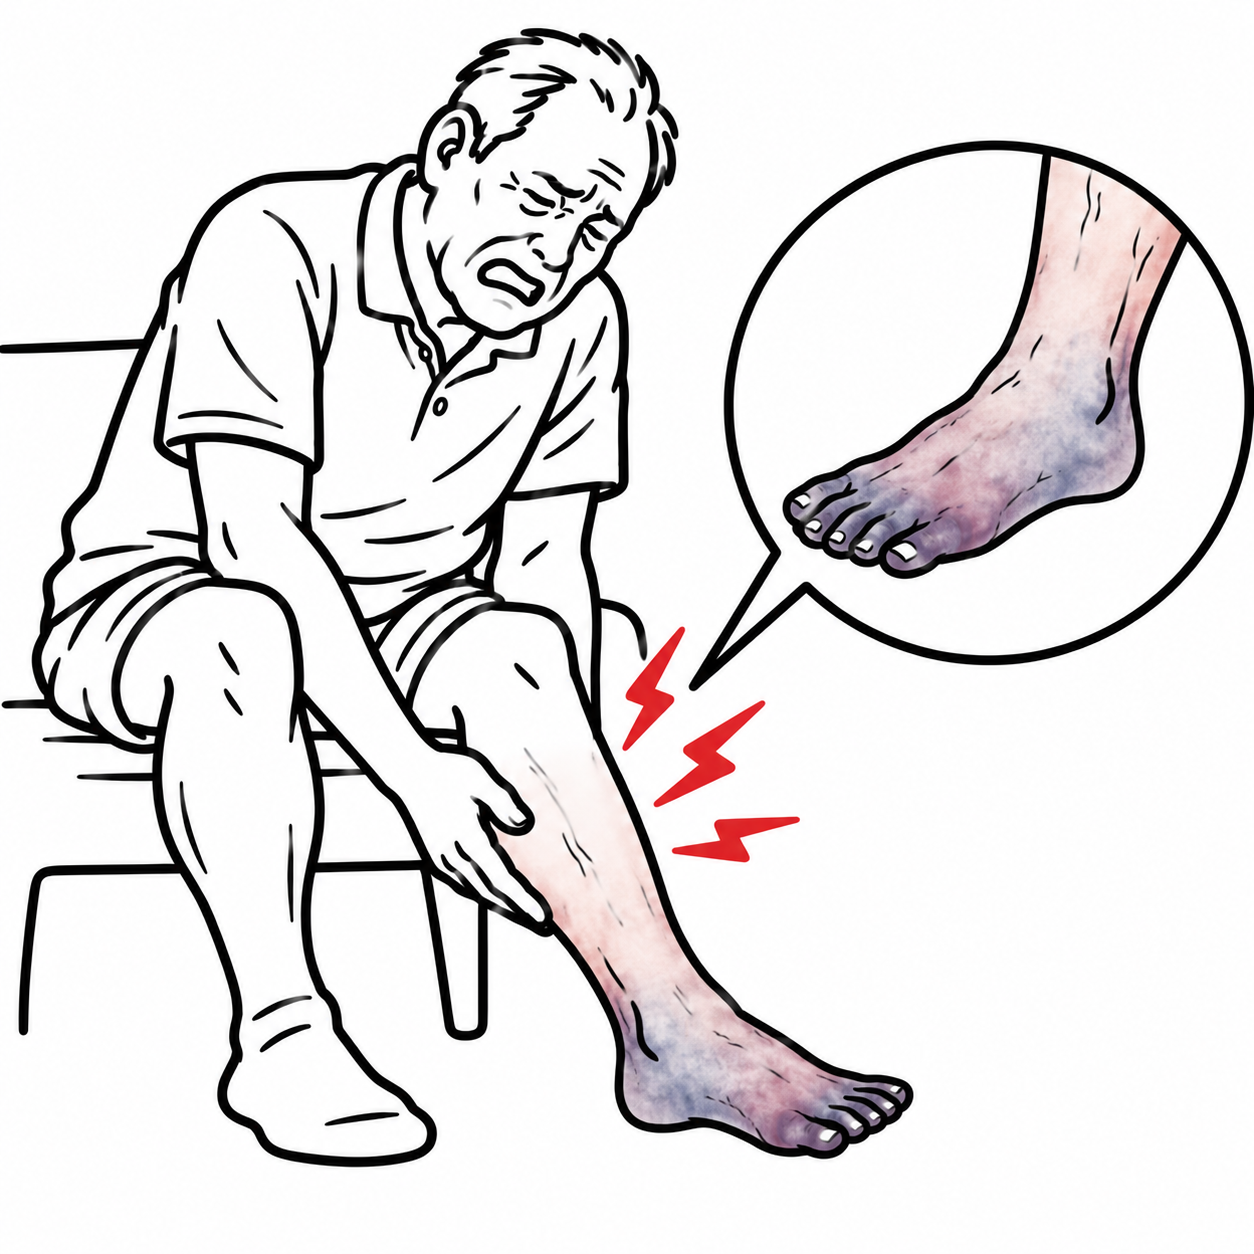
- Phlegmasia cerulea dolens (acute limb gangrene)
- Chronic
- Post thrombotic syndrome
- Chronic venous insufficiency
Prognosis
Prevention
- Identify patient at risk
- Prevent Dehydration
- Mechanical prophylaxis
- Intermittent Pneumotic Compression
- Calf compression stockings
- Encourage movement
- Exercise
- Quit smoking
- Medication – Warfarin to therapeutic dose INR 2-3 OR NOAC of choice
- IVC filter
Prevention in surgery
- High Risk – LMWH (40mg daily) + mechanical prophylaxis
- Orthopaedic Surgery
- Major trauma
- Fracture
- Major surgery >40yo
- Medium Risk – LMWH (20mg daily) + mechanical prophylaxis
- Low Risk – Consider LMWH + mechanical prophylaxis
- All other surgery
Make sure there are no contraindications for LMWH and Mechanical prophylaxis.
References
- Di Nisio M, van Es N, Büller HR. Deep vein thrombosis and pulmonary embolism. Lancet. 2016;388(10063):3060-3073.
- Lim W, Le Gal G, Bates SM, Righini M, Haramati LB, Lang E, et al. American Society of Hematology 2018 guidelines for management of venous thromboembolism: diagnosis of venous thromboembolism. Blood Adv. 2018;2(22):3226-3256. doi:10.1182/bloodadvances.2018024828.
- Wells PS, Anderson DR, Rodger M, Forgie M, Kearon C, Dreyer J, et al. Evaluation of D-dimer in the diagnosis of suspected deep-vein thrombosis. N Engl J Med. 2003;349(13):1227-1235. doi:10.1056/NEJMoa023153.
- Ortel TL, Neumann I, Ageno W, Beyth R, Clark NP, Cuker A, et al. American Society of Hematology 2020 guidelines for management of venous thromboembolism: treatment of deep vein thrombosis and pulmonary embolism. Blood Adv. 2020;4(19):4693-4738. doi:10.1182/bloodadvances.2020001830.
- Stevens SM, Woller SC, Kreuziger LB, Bounameaux H, Doerschug K, Geersing GJ, et al. Antithrombotic therapy for VTE disease: second update of the CHEST guideline and expert panel report. Chest. 2021;160(6):e545-e608. doi:10.1016/j.chest.2021.07.055.
- Anderson DR, Morgano GP, Bennett C, Dentali F, Francis CW, Garcia DA, et al. American Society of Hematology 2019 guidelines for management of venous thromboembolism: prevention of venous thromboembolism in surgical hospitalized patients. Blood Adv. 2019;3(23):3898-3944. doi:10.1182/bloodadvances.2019000975.
- Kahn SR, Comerota AJ, Cushman M, Evans NS, Ginsberg JS, Goldenberg NA, et al. The postthrombotic syndrome: evidence-based prevention, diagnosis, and treatment strategies: a scientific statement from the American Heart Association. Circulation. 2014;130(18):1636-1661. doi:10.1161/CIR.0000000000000130.

Members only discussions coming soon…