

Overview
Cardiac amyloidosis is an infiltrative cardiomyopathy caused by extracellular deposition of misfolded protein fibrils within the myocardium, conduction system, valves and intramyocardial vessels. Progressive amyloid accumulation increases ventricular wall thickness and stiffness, producing restrictive physiology, heart failure, arrhythmias and conduction disease.1,2
More than 98% of clinically recognised cardiac amyloidosis is caused by either:
- Immunoglobulin light-chain amyloidosis (AL): amyloid fibrils arise from monoclonal light chains produced by an abnormal plasma-cell clone.
- Transthyretin amyloidosis (ATTR): amyloid fibrils arise from destabilised transthyretin and may be wild-type (ATTRwt) or hereditary/variant (ATTRv).2
Early identification is essential because treatment is subtype-specific. AL amyloidosis is a haematological emergency requiring rapid suppression of light-chain production, whereas ATTR cardiomyopathy is treated with therapies that stabilise transthyretin or reduce its production.1
Definition
- Cardiac amyloidosis
- An infiltrative cardiomyopathy caused by extracellular deposition of amyloid fibrils within cardiac tissue.
- AL amyloidosis
- Amyloidosis caused by misfolded monoclonal immunoglobulin light chains produced by an abnormal plasma-cell clone.
- ATTR amyloidosis
- Amyloidosis caused by misfolding and aggregation of transthyretin.
- Restrictive physiology
- Impaired ventricular filling caused by reduced myocardial compliance, often with relatively preserved systolic function early in the disease.
Anatomy & Physiology
The ventricles normally fill during diastole as the myocardium relaxes and expands. Ventricular compliance allows the heart to accommodate blood without a marked rise in filling pressure.
Transthyretin is a transport protein produced mainly by the liver. It circulates as a tetramer and carries thyroxine and retinol-binding protein. Dissociation of the tetramer into unstable monomers is a key step in ATTR amyloid formation.
The atrioventricular node, His–Purkinje system and intramyocardial vessels are embedded within the cardiac interstitium. Amyloid deposition in these structures explains the combination of restrictive heart failure, conduction block, arrhythmia and microvascular ischaemia.
Aetiology & Risk Factors
Aetiology
The two major causes are AL and ATTR amyloidosis.1,2
| Type | Amyloid precursor | Underlying process | Characteristic associations |
|---|---|---|---|
| AL amyloidosis | Immunoglobulin light chain | Clonal plasma cells produce amyloidogenic light chains | Monoclonal gammopathy, plasma-cell dyscrasia, multiple myeloma |
| ATTRwt amyloidosis | Normal transthyretin | Age-related destabilisation of wild-type transthyretin | Older age, predominantly male phenotype |
| ATTRv amyloidosis | Variant transthyretin | Pathogenic TTR variant destabilises the transthyretin tetramer | Autosomal dominant inheritance; cardiac, neurological or mixed phenotype |
Other amyloid proteins can involve the heart, but these are uncommon. Cardiac involvement in AA amyloidosis is substantially less frequent than in AL or ATTR amyloidosis.2
Risk Factors
Important risk factors and clinical associations include:
- Increasing age: particularly for ATTRwt cardiomyopathy
- Male sex: ATTRwt is recognised more frequently in older men
- Monoclonal gammopathy or plasma-cell disorder: increases suspicion for AL amyloidosis
- Pathogenic TTR variant or family history: supports ATTRv amyloidosis
- African ancestry: associated with a higher prevalence of the TTR p.Val142Ile variant
- Bilateral carpal tunnel syndrome: may precede ATTR cardiac disease by several years
- Lumbar spinal canal stenosis
- Spontaneous distal biceps tendon rupture
- Atraumatic joint replacement
- Peripheral or autonomic neuropathy
- Unexplained increased ventricular wall thickness
- Heart failure with preserved ejection fraction
- Low-flow, low-gradient aortic stenosis in an older adult
ATTR amyloid may accumulate in tendons and ligaments before clinically apparent cardiac disease. Bilateral carpal tunnel syndrome, lumbar spinal stenosis or spontaneous biceps tendon rupture can therefore provide an early clue to otherwise unexplained heart failure.
Pathophysiology
Cardiac injury develops through a sequence of protein instability, misfolding and tissue deposition:
- Production of an amyloidogenic precursor: AL amyloidosis: a plasma-cell clone produces abnormal free light chains. ATTRwt amyloidosis: normal transthyretin becomes unstable with ageing. ATTRv amyloidosis: a pathogenic TTR variant reduces tetramer stability.
- Protein misfolding: The precursor protein dissociates or unfolds into unstable monomers that aggregate into oligomers and insoluble amyloid fibrils.
- Myocardial deposition: Amyloid accumulates throughout the extracellular interstitium, increasing ventricular wall thickness without true cardiomyocyte hypertrophy.
- Restrictive physiology: Ventricular compliance falls, impairing diastolic filling and raising left- and right-sided filling pressures. Stroke volume becomes relatively fixed, so cardiac output depends increasingly on heart rate.
- Progressive cardiac dysfunction: Continued infiltration produces worsening diastolic dysfunction, atrial enlargement, functional mitral or tricuspid regurgitation and, later, systolic impairment.
- Electrical and vascular involvement: Amyloid infiltration of the atria and conduction system promotes atrial fibrillation, atrioventricular block and ventricular arrhythmia. Involvement of intramyocardial vessels may cause angina or troponin elevation without obstructive epicardial coronary disease.1,2
Circulating light chains in AL amyloidosis also exert direct toxic effects on cardiomyocytes. Consequently, severe cardiac dysfunction may develop with a smaller amyloid burden than in ATTR cardiomyopathy.
A thickened ventricular wall usually suggests hypertrophy from hypertension or aortic stenosis. In cardiac amyloidosis, the apparent “hypertrophy” is caused largely by extracellular infiltration. This explains why marked wall thickening may coexist with low ECG voltage rather than the high voltage expected from true left ventricular hypertrophy.
Classification
Cardiac amyloidosis is classified according to the amyloid precursor protein.
AL cardiac amyloidosis
AL amyloidosis results from a clonal plasma-cell disorder. Cardiac involvement is common and is the principal determinant of prognosis. Other clues include nephrotic-range proteinuria, macroglossia, periorbital purpura, hepatomegaly and peripheral or autonomic neuropathy.
Wild-type ATTR cardiac amyloidosis
ATTRwt results from deposition of structurally normal transthyretin. It predominantly causes cardiomyopathy in older adults and commonly coexists with carpal tunnel syndrome, lumbar spinal stenosis or tendon disease.
Hereditary ATTR cardiac amyloidosis
ATTRv is caused by a pathogenic germline TTR variant and is inherited in an autosomal dominant pattern with variable penetrance. The phenotype may be:
- Predominantly cardiomyopathic
- Predominantly neuropathic
- Mixed cardiac and neurological disease
The age of onset and pattern of organ involvement vary substantially between variants and families.
Clinical Manifestations
Cardiac amyloidosis commonly presents as heart failure with preserved or mildly reduced ejection fraction, although the presentation varies with disease stage and amyloid subtype.1–3
Symptoms
- Progressive exertional dyspnoea
- Fatigue and reduced exercise tolerance
- Peripheral oedema
- Abdominal distension or ascites
- Orthopnoea or paroxysmal nocturnal dyspnoea
- Palpitations
- Presyncope or syncope
- Angina-like chest discomfort
- Postural dizziness from low cardiac output, autonomic dysfunction or diuretic treatment
- Unintentional weight loss in systemic AL amyloidosis
Cardiovascular signs
- Elevated jugular venous pressure
- Peripheral oedema and ascites
- Hepatomegaly
- Third heart sound
- Systolic murmur from functional mitral or tricuspid regurgitation
- Hypotension or a narrow pulse pressure
- Irregular pulse from atrial fibrillation
- Bradycardia or other evidence of conduction disease
Extracardiac clues
Features suggesting ATTR amyloidosis:
- Bilateral carpal tunnel syndrome
- Lumbar spinal stenosis
- Spontaneous distal biceps tendon rupture
- Peripheral sensorimotor neuropathy
- Autonomic dysfunction
- Family history of cardiomyopathy or neuropathy
Features suggesting AL amyloidosis:
- Nephrotic-range proteinuria
- Macroglossia
- Periorbital purpura
- Unexplained bruising
- Hepatomegaly
- Peripheral or autonomic neuropathy
- Monoclonal gammopathy
Cardiac amyloidosis should be considered when heart failure, increased ventricular wall thickness or aortic stenosis occurs alongside “red-flag” extracardiac features such as bilateral carpal tunnel syndrome, neuropathy, nephrotic proteinuria, macroglossia or periorbital purpura.
Diagnosis & Investigations
The diagnostic objectives are to:
- Recognise an amyloid cardiac phenotype.
- Rapidly exclude AL amyloidosis.
- Establish whether ATTR amyloidosis can be diagnosed non-invasively.
- Obtain and type tissue when the non-invasive pathway is inconclusive.
- Assess cardiac severity and extracardiac involvement.1,2
Recognise the cardiac phenotype
Electrocardiography
Possible findings include:
- Low QRS voltage, particularly in the limb leads
- Disproportionately low voltage relative to ventricular wall thickness
- Prolonged PR interval
- Bundle branch block
- Atrioventricular block
Low voltage is a useful clue but is not sufficiently sensitive to exclude cardiac amyloidosis.
Cardiac biomarkers
- NT-proBNP or BNP: reflects haemodynamic stress and assists with staging, prognosis and treatment monitoring.
- High-sensitivity cardiac troponin: may remain chronically elevated because of myocardial injury.
Both biomarkers can be influenced by renal function, atrial fibrillation and volume status and must be interpreted in context.
Echocardiography
Important findings include:
- Increased left and right ventricular wall thickness
- Biatrial enlargement
- Restrictive diastolic filling
- Reduced longitudinal systolic function despite preserved ejection fraction
- Small or normal ventricular cavity
- Thickened valves or interatrial septum
- Small pericardial effusion
- Reduced tissue Doppler velocities
- Relative apical sparing on longitudinal strain imaging
Relative apical sparing supports the diagnosis but is not specific enough to determine the amyloid type.
Cardiac magnetic resonance imaging
Cardiac magnetic resonance may demonstrate:
- Diffuse subendocardial or transmural late gadolinium enhancement
- Abnormal myocardial and blood-pool nulling
- Increased native T1
- Increased extracellular volume
- Atrial and right ventricular involvement
Cardiac magnetic resonance is valuable when echocardiography is equivocal and can assess disease burden, but it cannot reliably distinguish AL from ATTR amyloidosis.
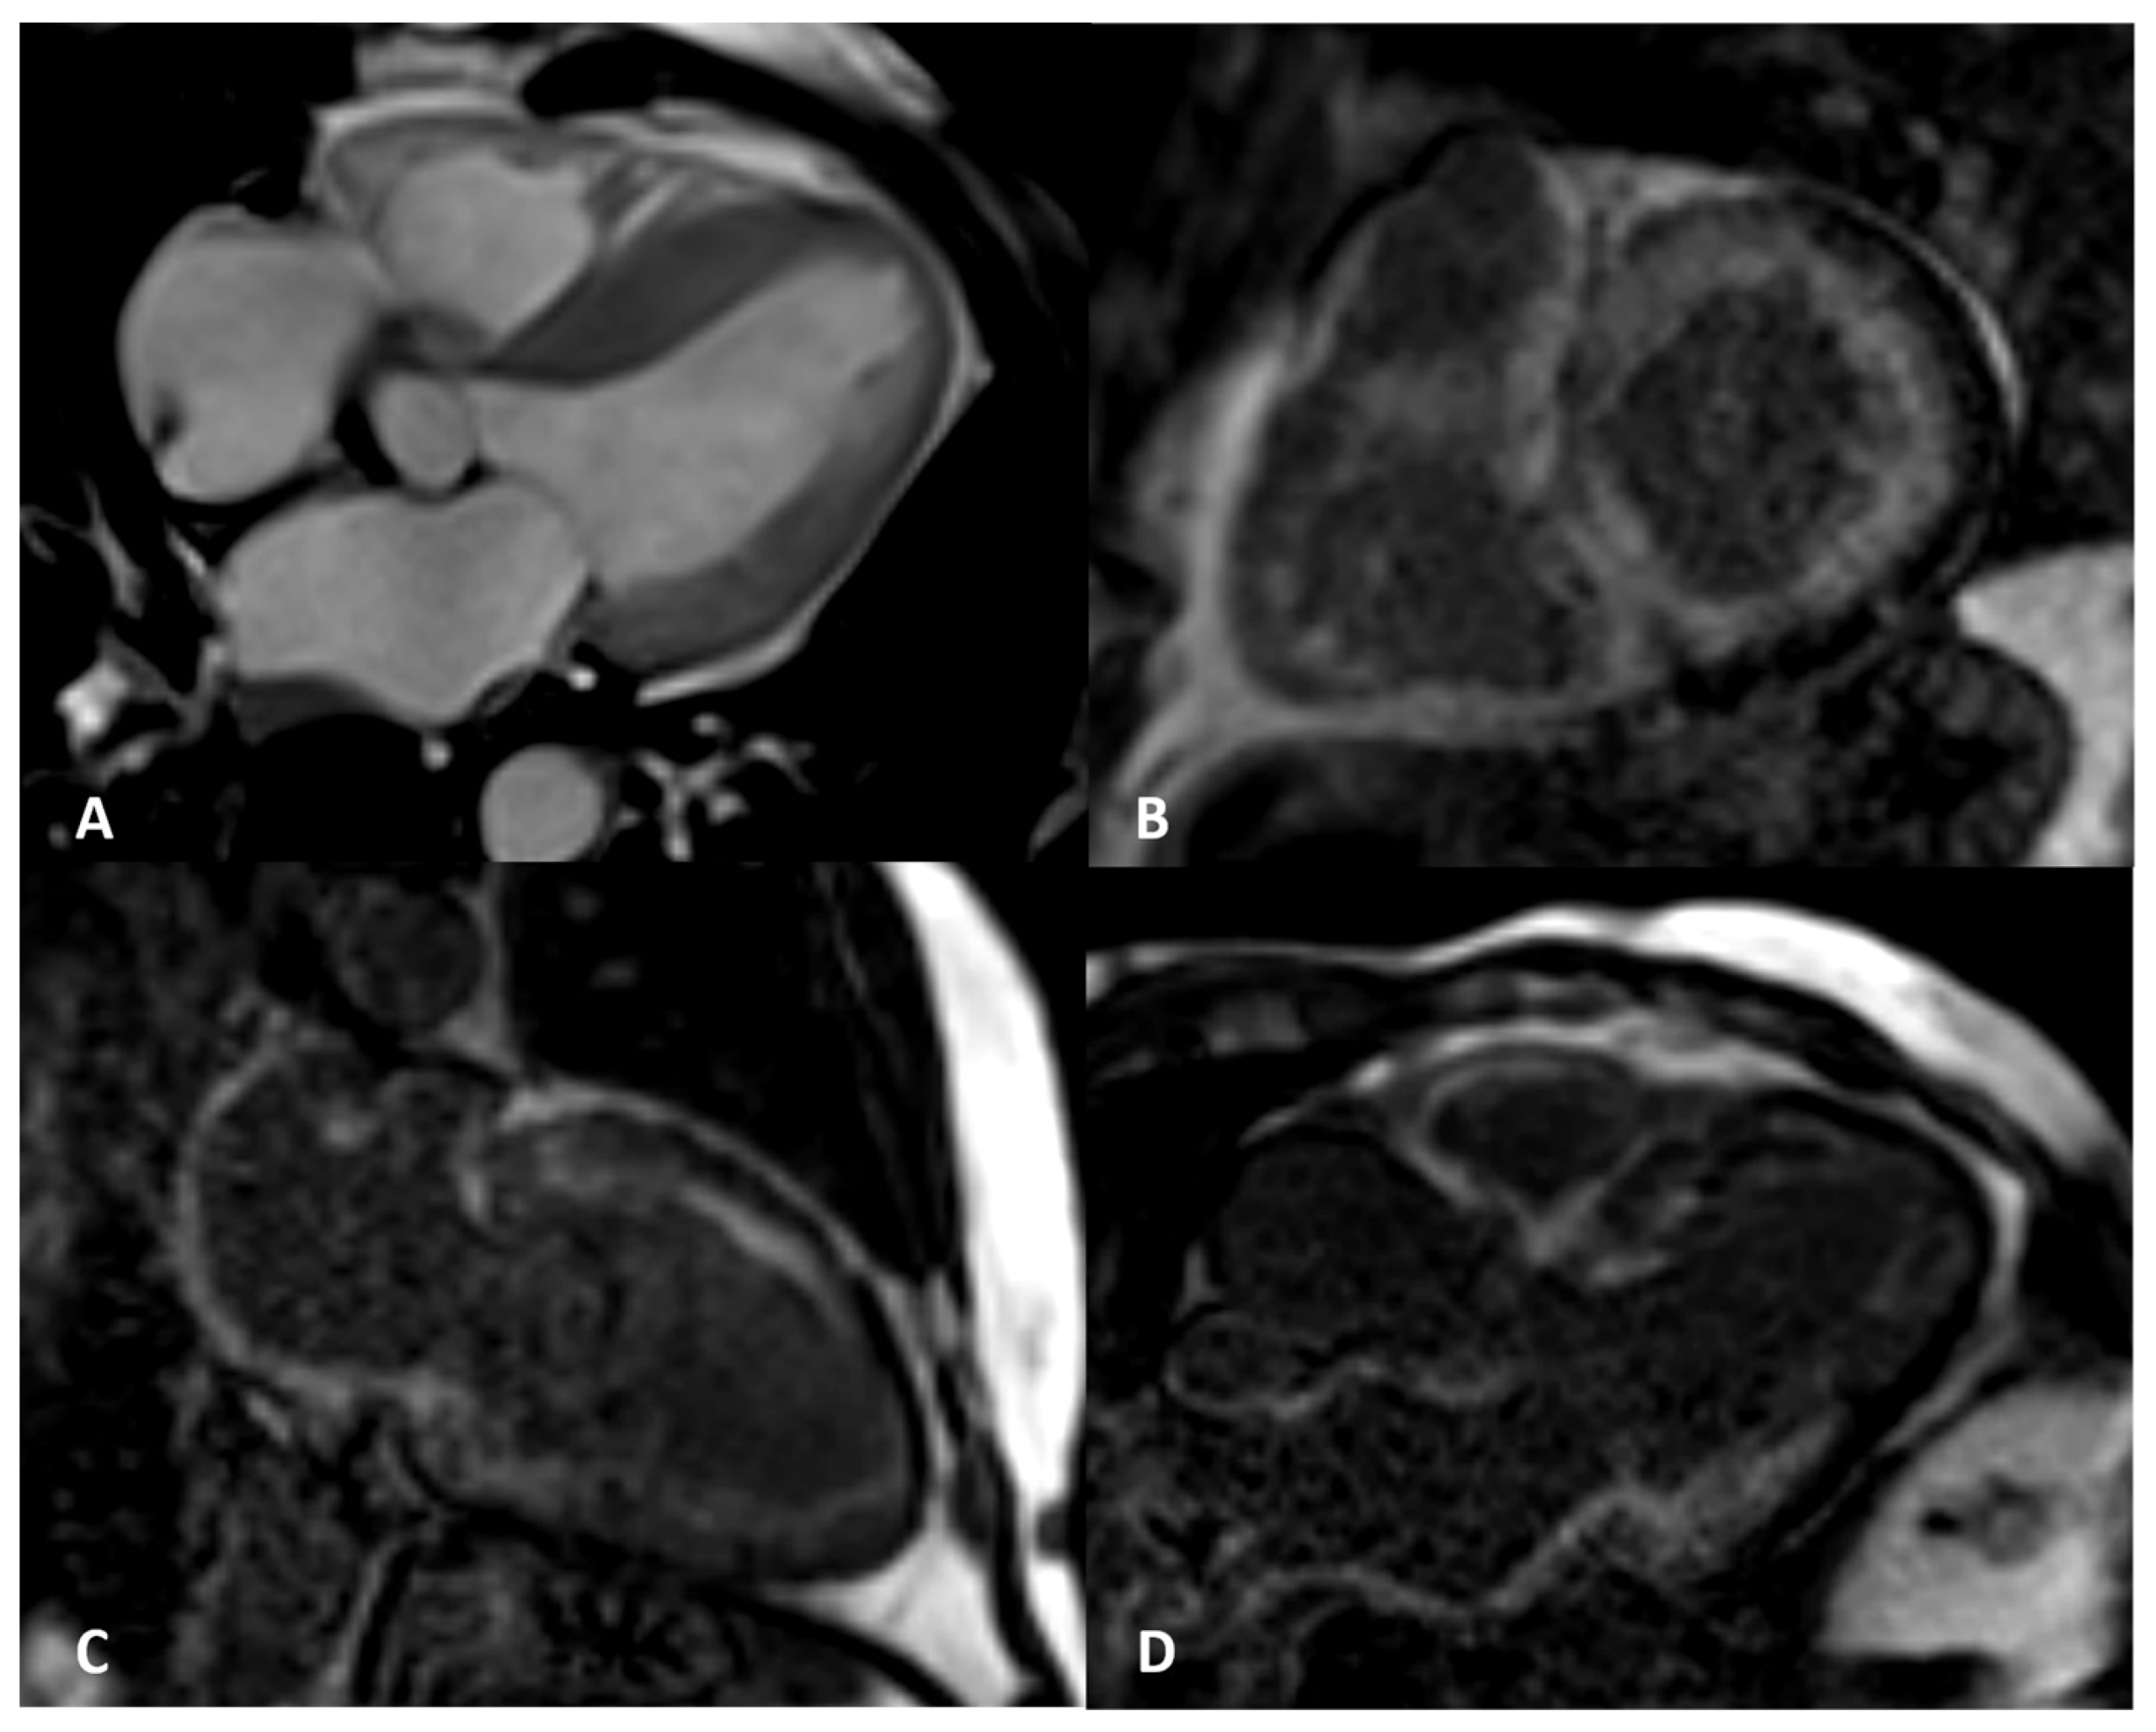
Cardiac magnetic resonance in biopsy-confirmed cardiac amyloidosis. Native T1 mapping is diffusely elevated, with transmural left ventricular and subendocardial right ventricular late gadolinium enhancement. From Maggialetti et al., licensed under CC BY 4.0.
What to notice
Detailed image description
Source: https://www.mdpi.com/2075-4426/14/4/407 — Figure 2. Creator: Maggialetti N et al. Licence: Creative Commons Attribution 4.0 International (CC BY 4.0), https://creativecommons.org/licenses/by/4.0/. Original asset: https://mdpi-res.com/d_attachment/jpm/jpm-14-00407/article_deploy/html/images/jpm-14-00407-g002.png. Imported without modification on 25 August 2026.
Exclude AL amyloidosis
All patients with suspected cardiac amyloidosis require a complete monoclonal protein assessment:
- Serum free light-chain assay
- Serum immunofixation electrophoresis
- Urine immunofixation electrophoresis
Serum or urine protein electrophoresis without immunofixation is insufficiently sensitive. The free light-chain ratio must be interpreted cautiously in chronic kidney disease.
An abnormal result requires urgent haematology assessment and generally tissue confirmation with definitive amyloid typing. A coincidental monoclonal gammopathy is common in older adults and does not establish AL amyloidosis.1,2
Never diagnose ATTR cardiac amyloidosis from a positive bone scan until AL amyloidosis has been excluded with serum free light chains plus serum and urine immunofixation. Bone-tracer uptake can occur in AL amyloidosis, and delayed treatment of AL disease can be fatal.
Bone-tracer scintigraphy
Scintigraphy uses a technetium-labelled bone tracer, such as:
- 99mTc-DPD
- 99mTc-PYP
- 99mTc-HMDP
Planar imaging should be accompanied by single-photon emission computed tomography (SPECT) or SPECT/CT to confirm that uptake is within the myocardium rather than the blood pool.
Cardiac uptake is graded relative to bone:
- Grade 0: no cardiac uptake
- Grade 1: cardiac uptake less than bone
- Grade 2: cardiac uptake equal to bone
- Grade 3: cardiac uptake greater than bone with reduced bone signal
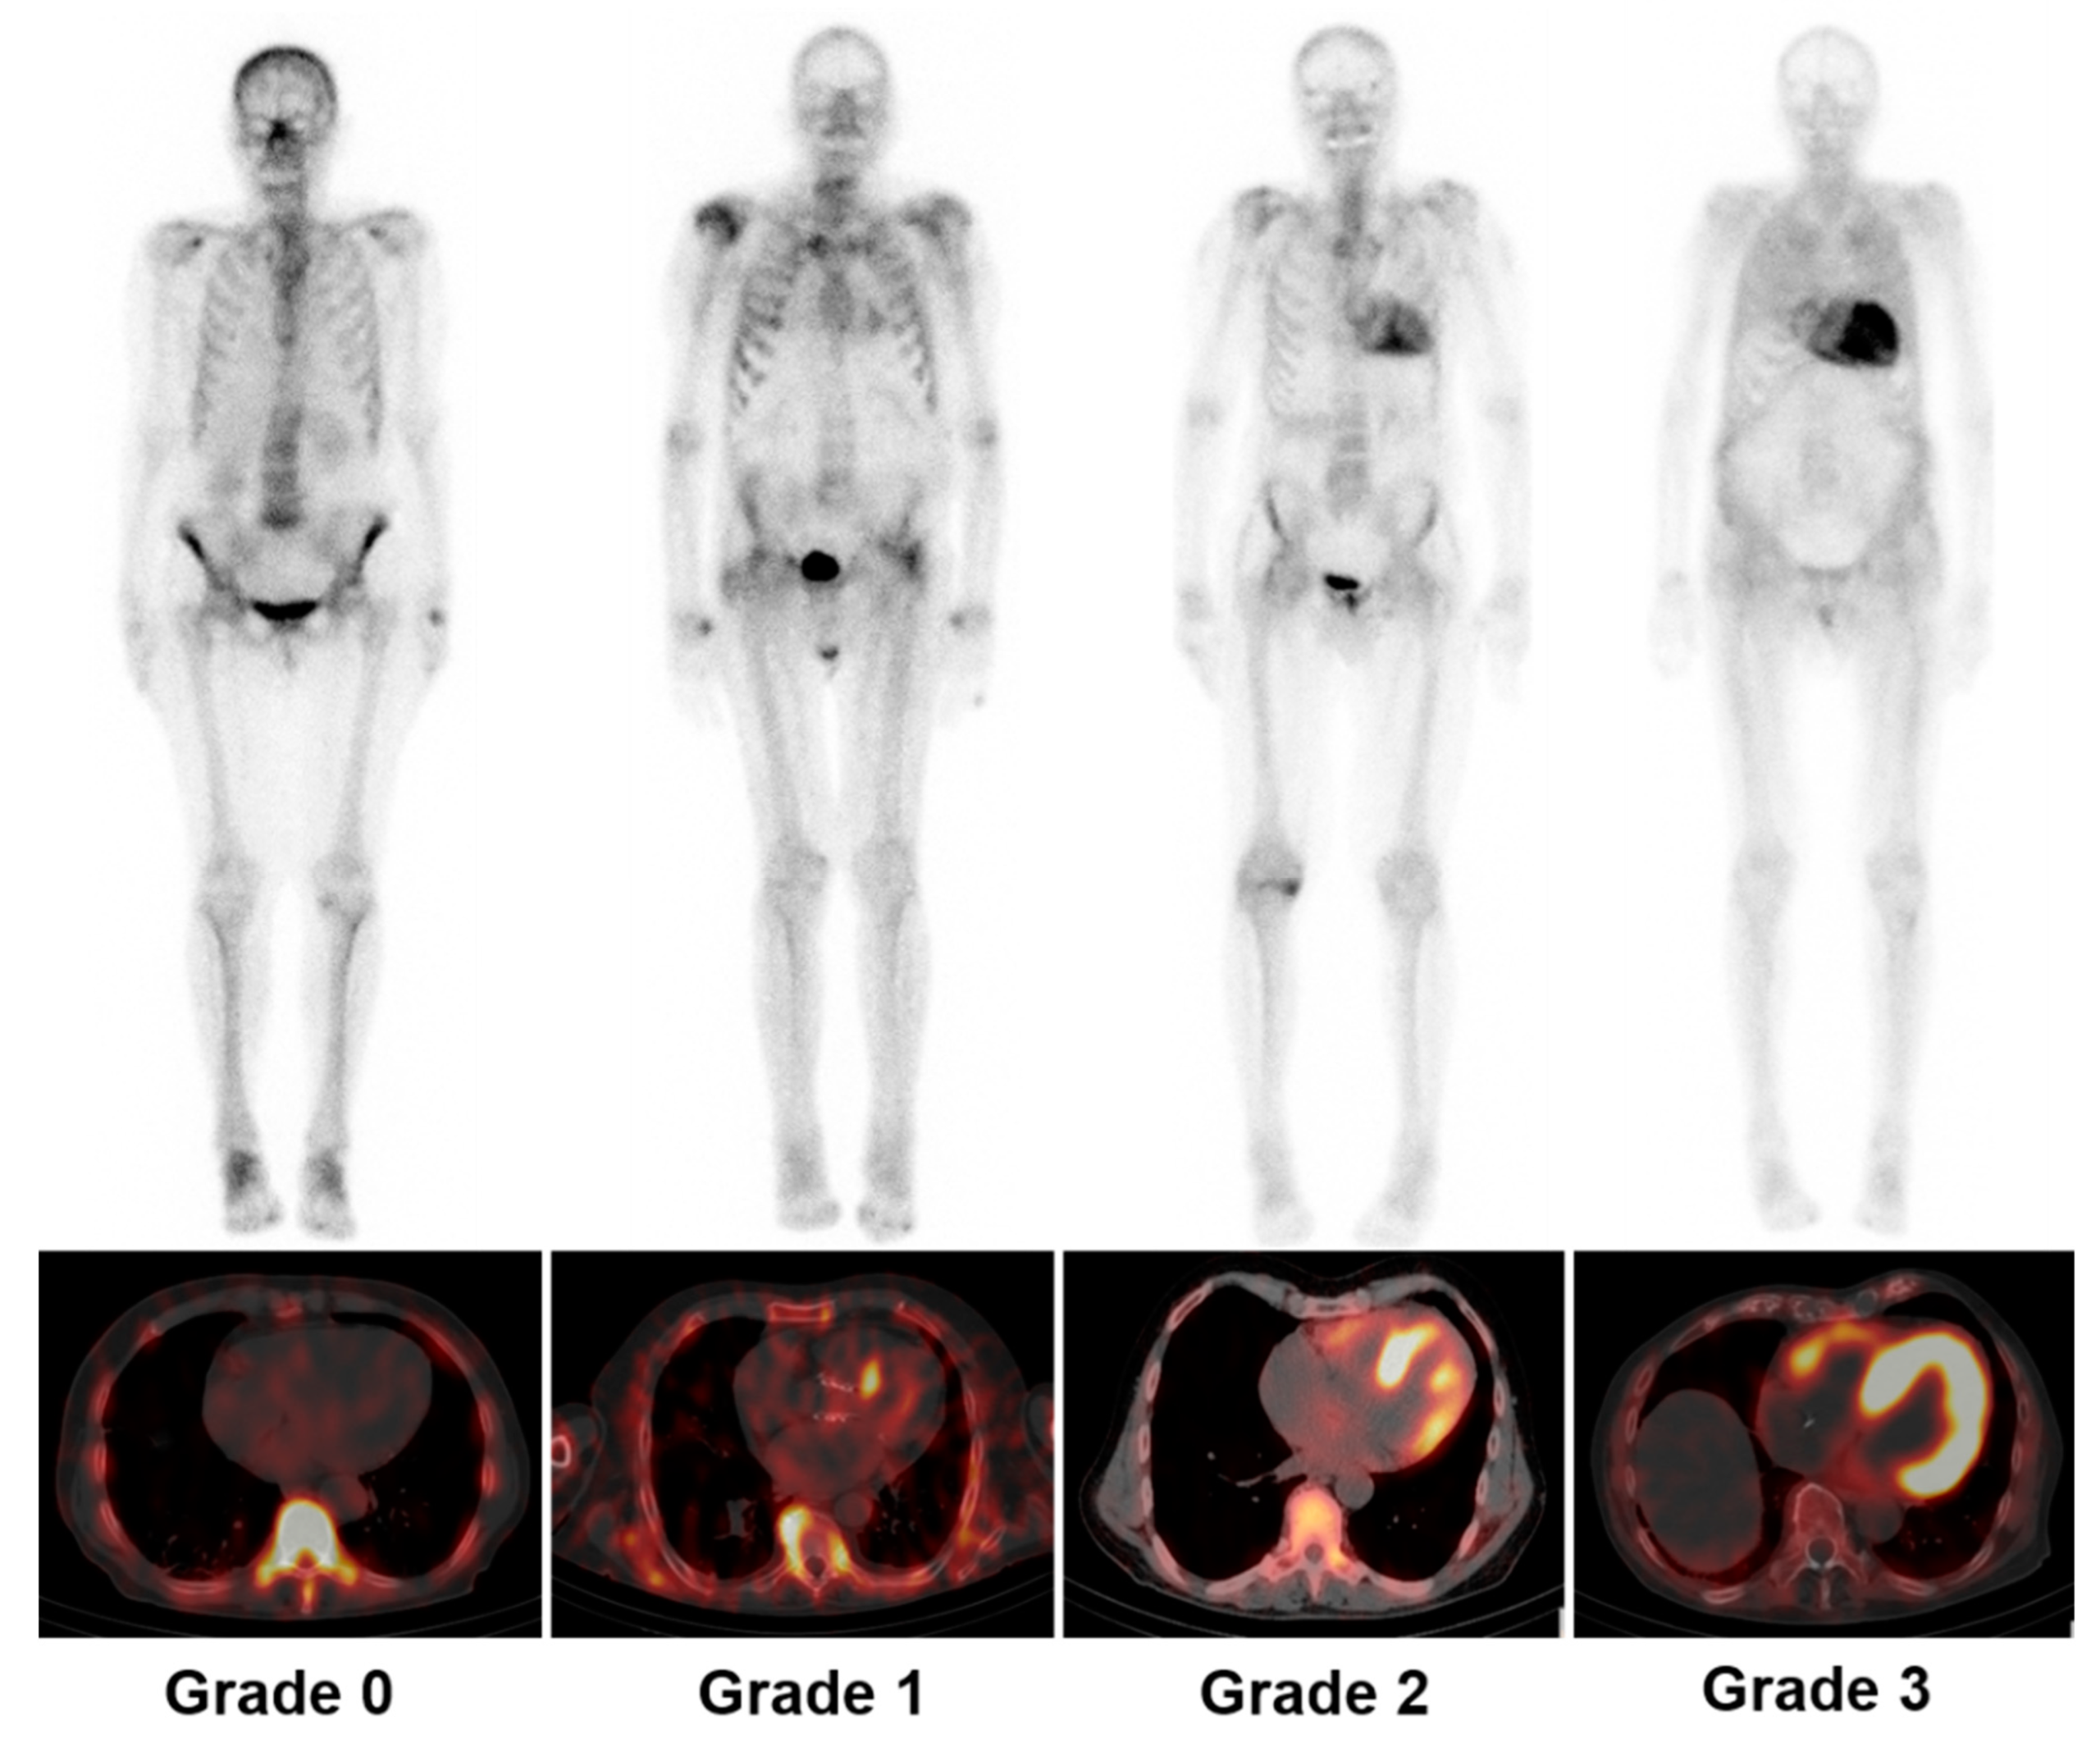
Representative Perugini grading of cardiac uptake on technetium-labelled bone scintigraphy. Grade 0 shows no myocardial uptake; Grade 1 uptake is less than bone; Grade 2 equals bone; and Grade 3 exceeds bone with reduced skeletal signal. From Zhao et al., licensed under CC BY 4.0.
What to notice
Detailed image description
Source: https://www.mdpi.com/2079-7737/11/10/1395 — Figure 2. Creator: Zhao M et al. Licence: Creative Commons Attribution 4.0 International (CC BY 4.0), https://creativecommons.org/licenses/by/4.0/. Original asset: https://mdpi-res.com/d_attachment/biology/biology-11-01395/article_deploy/html/images/biology-11-01395-g002.png. Imported without modification on 25 August 2026.
ATTR cardiac amyloidosis can be diagnosed without cardiac biopsy when there is:
- A compatible cardiac imaging phenotype
- Grade 2 or 3 myocardial uptake on bone-tracer scintigraphy
- No monoclonal protein detected on serum free light-chain testing and serum and urine immunofixation1,2,7
Grade 0 or 1 uptake does not exclude AL amyloidosis and may occur in some ATTRv variants.
When is biopsy required?
Biopsy is required when:
- A monoclonal protein is present
- Bone scintigraphy is negative or equivocal despite high clinical suspicion
- Uptake is Grade 1
- Imaging and laboratory findings conflict
- An uncommon amyloid type is suspected
Potential biopsy sites include abdominal fat, bone marrow or an affected extracardiac organ. Endomyocardial biopsy has high diagnostic sensitivity and is appropriate when extracardiac biopsy is negative or the diagnosis remains uncertain.
Amyloid is confirmed by Congo red staining with apple-green birefringence under polarised light. The deposited protein must then be typed, preferably by laser microdissection and mass spectrometry when available.
A positive monoclonal protein screen and a positive bone scan do not prove ATTR amyloidosis. The patient may have AL amyloidosis, ATTR amyloidosis with an incidental monoclonal gammopathy, or rarely both. Tissue biopsy with accurate amyloid typing is required.
Genetic testing
Once ATTR amyloidosis is established, perform TTR genetic testing regardless of age or apparent absence of family history. Identification of a pathogenic variant distinguishes ATTRv from ATTRwt and enables genetic counselling and appropriate evaluation of adult relatives.1,2
Treatment
Management requires coordinated care involving cardiology, haematology and an amyloidosis-experienced multidisciplinary service. Treatment combines control of cardiac complications with urgent subtype-directed therapy.1–3
Heart failure and volume management
- Loop diuretics are the main treatment for congestion.
- A mineralocorticoid receptor antagonist may be added when blood pressure, renal function and potassium permit.
- Monitor weight, renal function, electrolytes and orthostatic symptoms closely.
- Avoid excessive diuresis because the stiff, preload-dependent ventricle may develop hypotension or renal impairment with small reductions in circulating volume.
- Sodium restriction may assist congestion, while fluid restriction is individualised.
Conventional heart-failure therapies are often poorly tolerated:
- ACE inhibitors, angiotensin receptor blockers and angiotensin receptor–neprilysin inhibitors may worsen hypotension.
- Beta-blockers may reduce the compensatory heart-rate response required to maintain cardiac output.
- Sodium–glucose cotransporter-2 inhibitors may be considered in selected patients, although evidence specific to cardiac amyloidosis remains less established than in general heart failure.
- Non-dihydropyridine calcium-channel blockers are generally avoided because of negative inotropy, conduction effects and potential binding to amyloid fibrils.
- Digoxin should be used only when clearly indicated, at low doses and with careful monitoring for toxicity.
The amyloid-infiltrated ventricle has a small, relatively fixed stroke volume. Cardiac output therefore depends on adequate preload and heart rate. This explains why aggressive diuresis, vasodilators or excessive rate slowing may cause profound hypotension and clinical deterioration.
Arrhythmia and thromboembolism
- Atrial fibrillation is common and frequently poorly tolerated.
- Anticoagulation is generally recommended for atrial fibrillation in cardiac amyloidosis irrespective of the conventional CHA₂DS₂-VASc score, unless contraindicated.
- Amiodarone is commonly used when rhythm control is appropriate.
- Rate-control therapy must be individualised because beta-blockers may be poorly tolerated.
- Evaluate symptomatic bradycardia and advanced conduction disease for permanent pacing.
- Implantable cardioverter-defibrillator decisions should follow standard indications and be individualised; a survival benefit from routine prophylactic implantation has not been established.1,2
AL cardiac amyloidosis
Suspected AL amyloidosis requires urgent haematology referral because ongoing light-chain production can cause rapid and irreversible cardiac deterioration.
Treatment aims to rapidly suppress the plasma-cell clone. For many newly diagnosed patients, first-line therapy includes:
- Subcutaneous daratumumab
- Bortezomib
- Cyclophosphamide
- Dexamethasone
ATTR cardiac amyloidosis
Disease-modifying treatment should be considered as early as possible because established amyloid-related damage may not fully reverse.
Transthyretin stabilisers
- Tafamidis binds transthyretin and reduces tetramer dissociation.
- Acoramidis is a high-affinity transthyretin stabiliser.
Transthyretin gene silencers
- Vutrisiran is a small-interfering RNA therapy that reduces hepatic transthyretin production.
Transplantation
Heart transplantation may be considered in carefully selected patients with advanced, otherwise refractory cardiac disease and limited extracardiac involvement.
Complications & Prognosis
Complications
Important complications include:
- Progressive restrictive heart failure
- Right ventricular failure
- Recurrent pleural or pericardial effusions
- Atrial fibrillation and atrial flutter
- Intracardiac thrombus and systemic embolism
- Sinus-node dysfunction
- Atrioventricular block
- Ventricular arrhythmia
- Sudden cardiac death
- Cardiorenal syndrome
- Hypotension and autonomic dysfunction
- Functional mitral or tricuspid regurgitation
- Microvascular myocardial ischaemia
- Treatment-related toxicity
- Progressive extracardiac renal, neurological, gastrointestinal or hepatic disease
Prognosis
Prognosis depends on the amyloid subtype, disease stage at diagnosis, cardiac biomarker burden, functional status, renal involvement and response to subtype-directed treatment. Cardiac involvement is the major determinant of survival in AL amyloidosis.
Earlier recognition has become increasingly important because effective therapy can slow progression, reduce cardiovascular events and improve survival. It may not, however, reverse advanced myocardial infiltration.
The most important diagnostic step is not merely proving that amyloid is present—it is identifying the amyloid protein. AL and ATTR cardiac amyloidosis require fundamentally different treatments, and delay in treating AL amyloidosis can lead to rapid irreversible deterioration.
References
- Kittleson MM, Ruberg FL, Ambardekar AV, Brannagan TH, Cheng RK, Clarke JO, et al. 2023 ACC expert consensus decision pathway on comprehensive multidisciplinary care for the patient with cardiac amyloidosis. J Am Coll Cardiol. 2023;81(11):1076–1126. doi:10.1016/j.jacc.2022.11.022
- Garcia-Pavia P, Rapezzi C, Adler Y, Arad M, Basso C, Brucato A, et al. Diagnosis and treatment of cardiac amyloidosis: a position statement of the ESC Working Group on Myocardial and Pericardial Diseases. Eur Heart J. 2021;42(16):1554–1568. doi:10.1093/eurheartj/ehab072
- Arbelo E, Protonotarios A, Gimeno JR, Arbustini E, Barriales-Villa R, Basso C, et al. 2023 ESC Guidelines for the management of cardiomyopathies. Eur Heart J. 2023;44(37):3503–3626. doi:10.1093/eurheartj/ehad194
- Rimbas RC, Dulgheru R, Vinereanu D. New advanced imaging parameters and biomarkers—a step forward in the diagnosis and prognosis of TTR cardiomyopathy. J Clin Med. 2022;11(9):2360. doi:10.3390/jcm11092360
- Maggialetti N, Torrente A, Lorusso G, Villanova I, Ficco M, Gravina M, et al. Role of cardiovascular magnetic resonance in cardiac amyloidosis: a narrative review. J Pers Med. 2024;14(4):407. doi:10.3390/jpm14040407
- Zhao M, Calabretta R, Yu J, Binder P, Hu S, Hacker M, et al. Nuclear molecular imaging of disease burden and response to treatment for cardiac amyloidosis. Biology (Basel). 2022;11(10):1395. doi:10.3390/biology11101395
- Gillmore JD, Maurer MS, Falk RH, Merlini G, Damy T, Dispenzieri A, et al. Nonbiopsy diagnosis of cardiac transthyretin amyloidosis. Circulation. 2016;133(24):2404–2412. doi:10.1161/CIRCULATIONAHA.116.021612
- Kastritis E, Palladini G, Minnema MC, Wechalekar AD, Jaccard A, Lee HC, et al. Daratumumab-based treatment for immunoglobulin light-chain amyloidosis. N Engl J Med. 2021;385(1):46–58. doi:10.1056/NEJMoa2028631
- Maurer MS, Schwartz JH, Gundapaneni B, Elliott PM, Merlini G, Waddington-Cruz M, et al. Tafamidis treatment for patients with transthyretin amyloid cardiomyopathy. N Engl J Med. 2018;379(11):1007–1016. doi:10.1056/NEJMoa1805689
- Gillmore JD, Judge DP, Cappelli F, Fontana M, Garcia-Pavia P, Gibbs S, et al. Efficacy and safety of acoramidis in transthyretin amyloid cardiomyopathy. N Engl J Med. 2024;390(2):132–142. doi:10.1056/NEJMoa2305434
- Fontana M, Berk JL, Gillmore JD, Witteles RM, Grogan M, Drachman B, et al. Vutrisiran in patients with transthyretin amyloidosis with cardiomyopathy. N Engl J Med. 2025;392(1):33–44. doi:10.1056/NEJMoa2409134