

Conjunctival Disease (Conjunctivitis)

Overview
The conjunctiva is a thin, translucent mucous membrane that lines the posterior surface of the eyelids (palpebral conjunctiva), reflects over the anterior sclera (bulbar conjunctiva), and forms the superior and inferior ciliary junctions (fornices) up to the corneal limbus.
Conjunctival diseases encompass a wide spectrum of infectious, allergic, inflammatory, degenerative, and autoimmune conditions. Among these, conjunctivitis (“pink eye”) is the single most common cause of eye redness in primary care. While most cases are self-limiting, identifying key clinical features and ruling out sight-threatening “red eye” emergencies (such as bacterial keratitis, acute angle-closure glaucoma, and anterior uveitis) is a vital clinical skill.
Viral Conjunctivitis
Overview
Viral conjunctivitis is an acute, highly contagious infection of the conjunctival membrane. It is the single most common cause of infectious conjunctivitis overall, accounting for up to 75% of acute cases in primary care settings.
Definition
Epidemic Keratoconjunctivitis (EKC): A severe, highly contagious subtype caused by specific adenoviral serotypes, featuring severe conjunctival hyperemia, keratitis, and subepithelial corneal infiltrates.
Pharyngoconjunctival Fever (PCF): A clinical syndrome characterized by triad of viral conjunctivitis, fever, and acute pharyngitis.
Follicle: A small (0.5–1.5 mm) pale, avascular lymphoid aggregation on the palpebral conjunctiva with fine blood vessels encircling its base—the classic physical finding in viral conjunctivitis.
Aetiology & Risk Factors
Aetiology
- Adenovirus: Responsible for 65% to 90% of viral cases (Serotypes 8, 19, 37 cause EKC; Serotypes 3, 7 cause PCF).
- Herpes Simplex Virus (HSV-1): Important unilateral cause, often accompanied by vesicular skin lesions.
- Enterovirus 70 / Coxsackievirus A24: Cause Acute Hemorrhagic Conjunctivitis.
Risk Factors
- Recent upper respiratory tract infection (URI)
- Direct contact with infected individuals
- Exposure in crowded environments (schools, swimming pools)
- Contaminated ophthalmic equipment.
Pathophysiology
Adenoviral infection and replication injure conjunctival epithelial cells and trigger inflammation. Parallel vascular and lymphoid responses account for redness, watering, follicles and possible preauricular lymphadenopathy. Epidemic keratoconjunctivitis may also involve the cornea, producing keratitis and later subepithelial infiltrates with photophobia or visual disturbance. These findings overlap with other causes and are not individually diagnostic.4
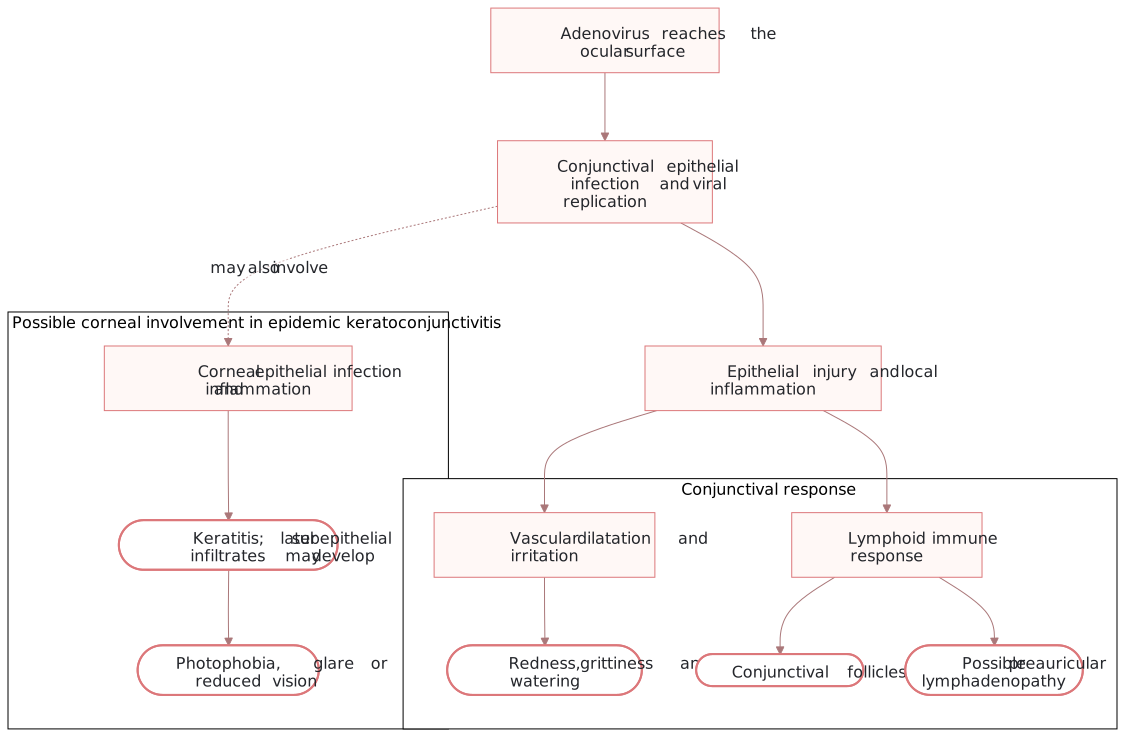
Viral replication produces parallel conjunctival and lymphoid findings. The dotted branch shows possible corneal involvement in epidemic keratoconjunctivitis; it is not inevitable.
What to notice
Detailed image description
Adenovirus reaches the ocular surface, infects conjunctival epithelial cells and replicates. Epithelial injury and inflammation have parallel effects: vascular dilatation and irritation produce redness, grittiness and watering; the lymphoid response can produce follicles and preauricular lymphadenopathy. In epidemic keratoconjunctivitis, corneal epithelial infection and inflammation may cause keratitis and later subepithelial infiltrates, with photophobia, glare or reduced vision. Solid arrows show the main mechanism; the dotted labelled branch indicates possible corneal involvement. Clinical findings overlap between causes and are not individually diagnostic.
Clinical Manifestations
- Sudden onset of watery/serous discharge, burning, grittiness, and foreign body sensation
- Starts in one eye and frequently spreads to the fellow eye within 24–48 hours.
Clinical examination
- Lids & Discharge: Eyelid edema with profuse watery (non-purulent) lacrimation.
- Conjunctiva: Diffuse conjunctival injection and lower tarsal follicles.
- Lymph Nodes: Tender preauricular lymphadenopathy (pathognomonic hallmark).
- Pseudomembranes: Coagulated fibrin exudate adhering to the palpebral conjunctiva in severe adenoviral EKC.
Diagnosis
- Diagnosis is clinical. Laboratory testing (viral PCR or rapid adenoviral antigen immunoassay) is reserved for severe or atypical cases.
Differential Diagnosis
- Bacterial Conjunctivitis: Distinguished by purulent, thick discharge and matted eyelids.
- HSV Keratoconjunctivitis: Identified via fluorescein staining showing classic dendritic corneal ulcers.
- Anterior Uveitis / Acute Glaucoma: Differentiated by deep eye pain, ciliary flush, photophobia, and altered pupils.
Treatment
- Supportive Care (First-Line): Cold compresses, preservative-free artificial tears, and topical OTC decongestants for symptom relief. Reassure the patient that symptoms typically peak at days 3–5 and take 2–3 weeks to resolve fully.
- Strict Infection Control: High contagiousness; instruct patients on hand hygiene, changing towels/pillowcases, and staying off work or school until discharge resolves.
- HSV Conjunctivitis: Topical Ganciclovir 0.15% gel or oral Acyclovir. Topical corticosteroids are strictly contraindicated.
Complications & Prognosis
Complications
- Subepithelial Infiltrates (SEIs): Immune-mediated focal corneal opacities that can persist for months after adenoviral infection, causing glare and reduced vision.
Prognosis
Excellent; self-limiting condition that resolves without permanent visual deficits in uncomplicated cases.
Bacterial Conjunctivitis
Overview
Bacterial conjunctivitis is an acute pyogenic infection of the conjunctival mucosa. While less common than viral cases in adults, it accounts for up to 50% of conjunctivitis cases in pediatric populations.
Definition
Mucopurulent / Purulent Discharge: Thick, yellow-green inflammatory exudate composed of dead neutrophils, bacteria, and epithelial debris; classic feature of bacterial infection.
Papilla: A vascular projection with a central red capillary core surrounded by edema, forming a polygonal red dot on the palpebral conjunctiva.
Hyperacute Bacterial Conjunctivitis: Rapidly progressive, explosive infection (typically N. gonorrhoeae) carrying an immediate threat of corneal perforation.
Aetiology & Risk Factors
Aetiology
- Staphylococcus aureus (most common cause in adults).
- Streptococcus pneumoniae and Haemophilus influenzae (most common in children).
- Pseudomonas aeruginosa (predominant pathogen in contact lens wearers).
- Neisseria gonorrhoeae (sexually transmitted or neonatally acquired).
Risk Factors
- Contact lens wear (especially overnight wear)
- Trauma
- Compromised tear production
- Exposure to infected individuals.
Pathophysiology
Bacterial inoculation or overgrowth of resident flora produces local conjunctival inflammation. Vascular changes cause redness and swelling, while inflammatory exudate produces mucopurulent discharge and matted eyelids. Corneal involvement is a possible complication, especially with gonococcal infection or impaired corneal defences, and may progress to ulceration or perforation. Discharge alone does not establish the aetiology.4
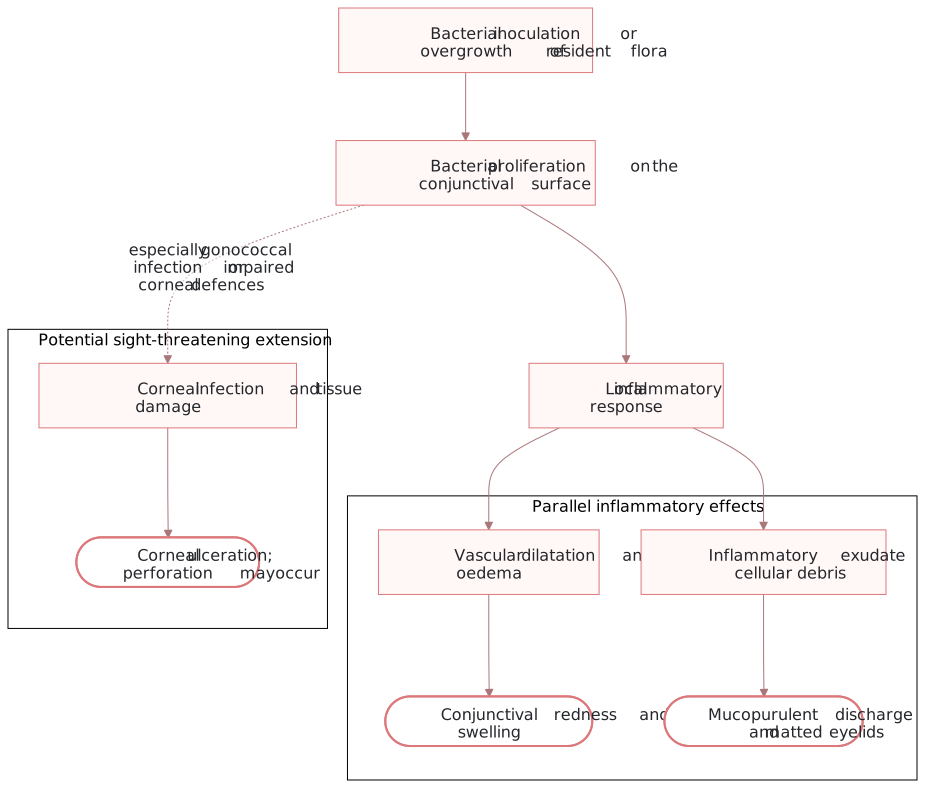
Bacterial inflammation produces vascular changes and exudate in parallel. The dotted branch marks possible corneal damage, especially in high-risk infection.
What to notice
Detailed image description
Bacterial inoculation or overgrowth of resident flora leads to bacterial proliferation on the conjunctival surface and local inflammation. Vascular dilatation and oedema cause redness and swelling. In parallel, inflammatory exudate and cellular debris produce mucopurulent discharge and matted eyelids. The dotted labelled branch indicates possible corneal infection and damage, particularly with gonococcal infection or impaired corneal defences; ulceration and perforation may occur. This is a mechanism diagram, not a diagnostic rule: discharge and examination findings overlap with other causes.
Clinical Manifestations
- Rapid onset of red eye
- Matted eyelids stuck shut upon waking
- Thick purulent discharge
- Mild globe discomfort
Clinical examination
- Discharge: Continuous purulent or mucopurulent yellow-green discharge that reaccumulates within minutes of wiping.
- Conjunctiva: Marked conjunctival injection, chemosis, and tarsal papillae.
- Preauricular Nodes: Characteristically absent (except in hyperacute Neisseria infection).
Diagnosis
- Uncomplicated cases are diagnosed clinically.
Microbiological Workup (Gram Stain & Culture)
Mandatory in:
- Hyperacute purulent conjunctivitis (Gonococcal)
- Neonatal conjunctivitis (Ophthalmia Neonatorum).
- Contact lens wearers or treatment failures.
Differential Diagnosis
- Viral Conjunctivitis: Watery discharge with tender preauricular node.
- Bacterial Keratitis: Presence of a corneal focal white infiltrate or ulcer; requires immediate ophthalmology evaluation.
Treatment
Empiric First-Line Antibiotics
Topical broad-spectrum drops for 5 to 7 days:
- Standard Cases: Chloramphenicol 0.5% drops or Tobramycin / Polymyxin B.
- Contact Lens Wearers: Must cover Pseudomonas; use topical fluoroquinolones (Ciprofloxacin or Ofloxacin).
Hyperacute Gonococcal Infection
Medical emergency requiring single-dose parenteral Ceftriaxone 1g IM/IV plus saline eye lavage and oral Azithromycin 1g for chlamydial coverage.
Complications & Prognosis
Complications
- Corneal Ulceration & Perforation: Can occur within 24–48 hours in N. gonorrhoeae or Pseudomonas infections.
Prognosis
Excellent with prompt antibiotic therapy; uncomplicated cases resolve completely within 5 to 7 days.
Allergic Conjunctivitis
Overview
Allergic conjunctivitis is a non-infectious, IgE-mediated inflammatory condition of the conjunctiva. It is extremely common, affecting up to 20% of the population, and is closely linked to other systemic atopic diseases.
Definition
Pruritus (Itching): The hallmark, single most specific symptom of ocular allergy.
Vernal Keratoconjunctivitis (VKC): Severe, bilateral allergic disease in young males featuring giant cobblestone papillae on the upper tarsal conjunctiva.
Horner-Trantas Dots: Transient gelatinous white clumps of eosinophils and epithelial debris at the corneal limbus in severe VKC.
Aetiology & Risk Factors
Triggering Allergens
- Airborne environmental antigens including grass/tree pollens
- Dust mites
- Mold spores
- Animal dander
Risk Factors
- Personal or family history of atopic disease (asthma, allergic rhinitis, atopic dermatitis).
Pathophysiology
In seasonal and perennial allergic conjunctivitis, allergen exposure activates sensitised conjunctival mast cells through IgE cross-linking. Histamine produces immediate itching, tearing and vascular changes; other mediators recruit inflammatory cells and sustain a later response. Severe vernal or atopic keratoconjunctivitis involves additional mechanisms and may damage the corneal epithelium; this is not an inevitable progression of uncomplicated allergy.4,5
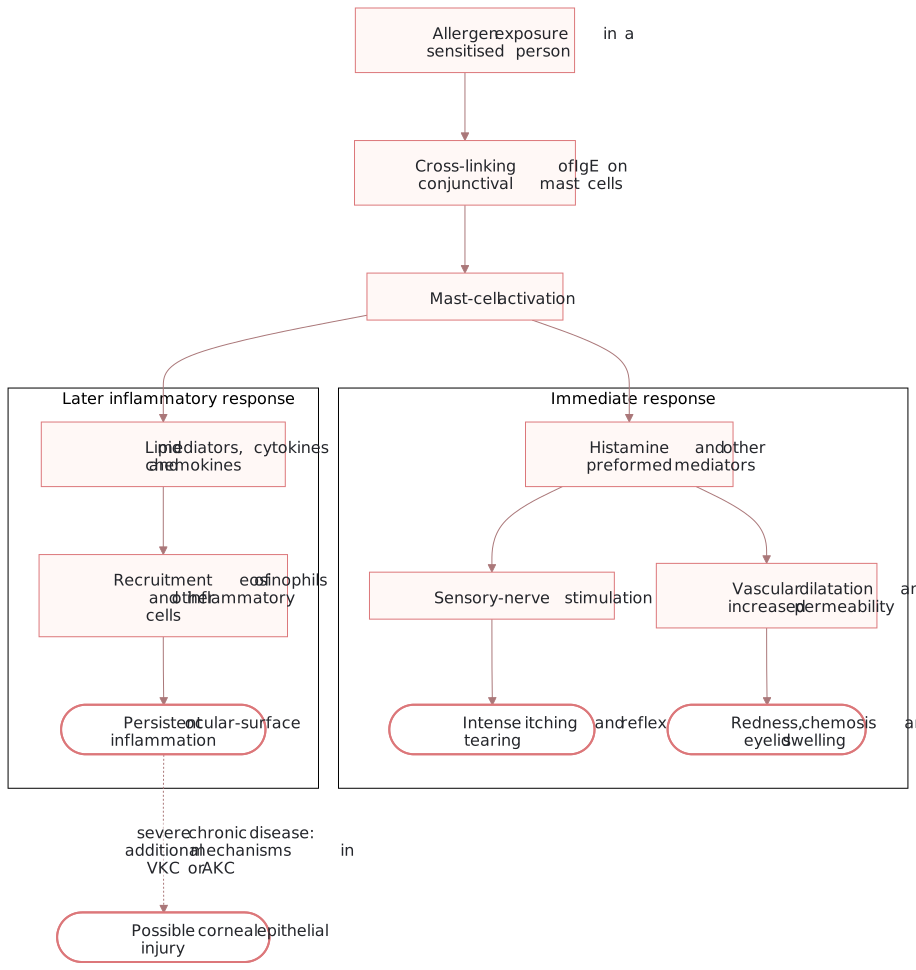
Immediate histamine effects and later inflammatory-cell recruitment are distinct pathways. The dotted branch shows a possible severe-disease complication; VKC = vernal keratoconjunctivitis, AKC = atopic keratoconjunctivitis.
What to notice
Detailed image description
Allergen exposure in a sensitised person cross-links IgE on conjunctival mast cells, causing activation. In the immediate response, histamine and other preformed mediators stimulate sensory nerves, causing intense itching and reflex tearing, and increase vascular dilatation and permeability, causing redness, chemosis and eyelid swelling. A parallel later response involves lipid mediators, cytokines and chemokines recruiting eosinophils and other inflammatory cells, sustaining ocular-surface inflammation. The dotted labelled branch indicates possible corneal epithelial injury in severe chronic vernal or atopic keratoconjunctivitis, which involve additional mechanisms. VKC means vernal keratoconjunctivitis; AKC means atopic keratoconjunctivitis. Corneal injury is not an inevitable progression of uncomplicated seasonal or perennial allergy.
Clinical Manifestations
- Intense itching (pruritus)
- Bilateral lacrimation
- Burning sensation
- Ropy stringy mucoid discharge.
Clinical examination
- Laterality: Strictly bilateral presentation.
- Conjunctiva: Diffuse injection, marked chemosis (glassy, swollen conjunctiva), and palpebral papillae.
- Corneal Findings (Severe VKC): Shield ulcers or limbal Horner-Trantas dots.
Diagnosis
Clinical Diagnosis
- Based on classic history of itching, bilateral presentation, atopic history, and presence of tarsal papillae.
Differential Diagnosis
- Infectious Conjunctivitis: Absence of significant itching; presence of purulent discharge (bacterial) or preauricular nodes (viral).
- Dry Eye Syndrome: Burning sensation without true allergic pruritus.
Treatment
- General Measures: Cold compresses, allergen avoidance, and preservative-free artificial tears (flushes out allergens).
- First-Line Pharmacotherapy: Topical dual-action Antihistamine / Mast Cell Stabilizers (e.g., Olopatadine, Ketotifen).
- Refractory / Severe Cases: Short courses of low-penetration topical corticosteroids (e.g., Loteprednol or Fluorometholone) administered exclusively under ophthalmologist supervision to monitor intraocular pressure.
Complications & Prognosis
Complications
- Corneal Shield Ulcers: Chronic mechanical abrasion from giant papillae in VKC can cause permanent corneal scarring.
- Steroid-Induced Complications: Secondary glaucoma and cataracts from unmonitored topical steroid use.
Prognosis
Excellent for SAC/PAC; chronic subtypes (VKC/AKC) require long-term management to protect corneal integrity.
Summary Table
| Feature | Viral Conjunctivitis | Bacterial Conjunctivitis | Allergic Conjunctivitis |
| Primary Symptom | Watery eyes, grittiness | Matted eyelids, stick shut | Intense Pruritus (Itching) |
| Discharge | Serous / Watery | Purulent / Mucopurulent | Ropy / Stringy / Mucoid |
| Laterality | Unilateral starting, then bilateral | Often bilateral | Strictly Bilateral |
| Preauricular Node | Present & Tender | Absent (except Neisseria) | Absent |
| Tarsal Findings | Follicles | Papillae | Papillae (or Cobblestone) |
| First-Line Tx | Cold compresses, supportive | Topical Chloramphenicol/Tobramycin | Topical Olopatadine / Ketotifen |
References
- Azari AA, Barney NP. Conjunctivitis: a systematic review of diagnosis and treatment. JAMA. 2013;310(16):1721-1729. doi:10.1001/jama.2013.280318
- Rubenstein JB, Viradiya P. Conjunctivitis: infectious and noninfectious. Dis Mon. 2014;60(6):269-281. doi:10.1016/j.disamonth.2014.03.008
- Leonardi A, Bogacka E, Fauquert JL, et al. Ocular allergy: recognizing and managing hypersensitivity disorders of the eye. Allergy. 2012;67(11):1327-1337. doi:10.1111/all.12009
- Azari AA, Arabi A. Conjunctivitis: a systematic review. J Ophthalmic Vis Res. 2020;15(3):372-395. doi:10.18502/jovr.v15i3.7456. Full text.
- Elieh Ali Komi D, Rambasek T, Bielory L. Clinical implications of mast cell involvement in allergic conjunctivitis. Allergy. 2018;73(3):528-539. doi:10.1111/all.13334. PubMed.

Members only discussions coming soon…