

Gallstone Disease
Overview
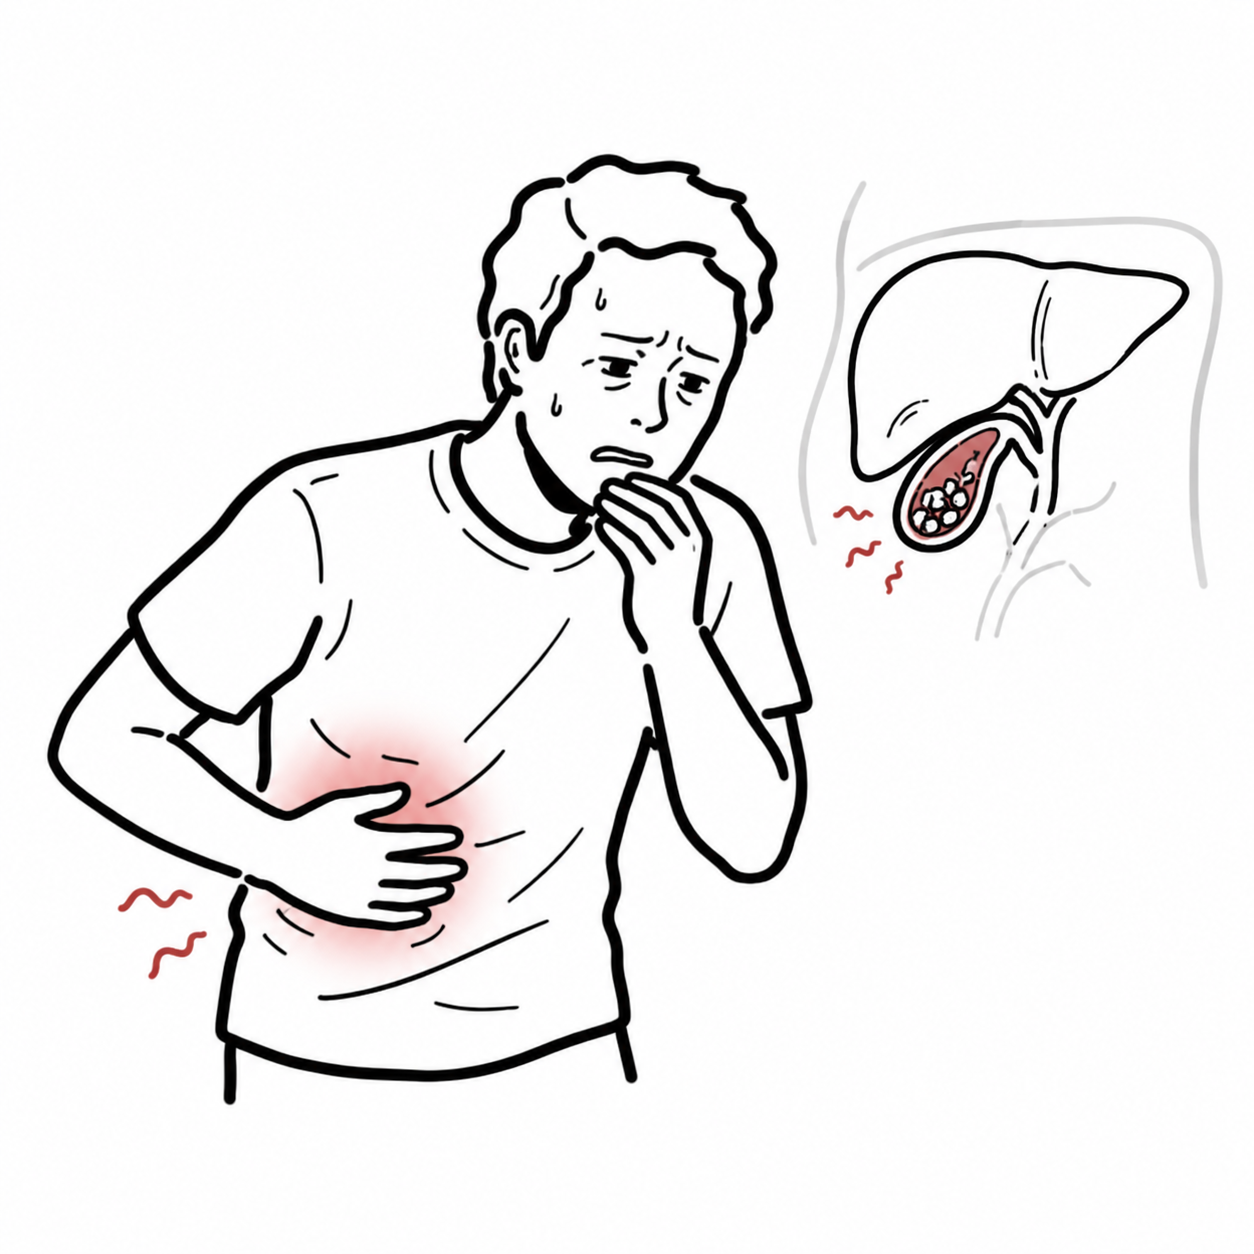
Gallstone disease encompasses stones in the gallbladder (cholelithiasis) and their consequences when they obstruct the cystic duct, common bile duct or ampulla. Stones are composed predominantly of cholesterol or pigment. Most are asymptomatic, but symptomatic disease can cause episodic biliary pain, acute cholecystitis, choledocholithiasis, cholangitis or acute pancreatitis. Distinguishing uncomplicated biliary pain from infection or duct obstruction guides the urgency of assessment and treatment.
Definition
Cholelithiasis: Gallstones within the gallbladder.
Biliary colic: An episode of sustained biliary pain caused by transient cystic duct obstruction; despite the name, pain is usually steady.
Choledocholithiasis: A stone within the common bile duct.
Acute calculous cholecystitis: Gallbladder inflammation, usually from persistent cystic duct obstruction.
Cholangitis: Infection of the biliary tree in the setting of impaired drainage.
ERCP: Endoscopic retrograde cholangiopancreatography, generally used therapeutically to drain the duct or remove stones.
What to notice
Detailed image description
Anatomy & Physiology
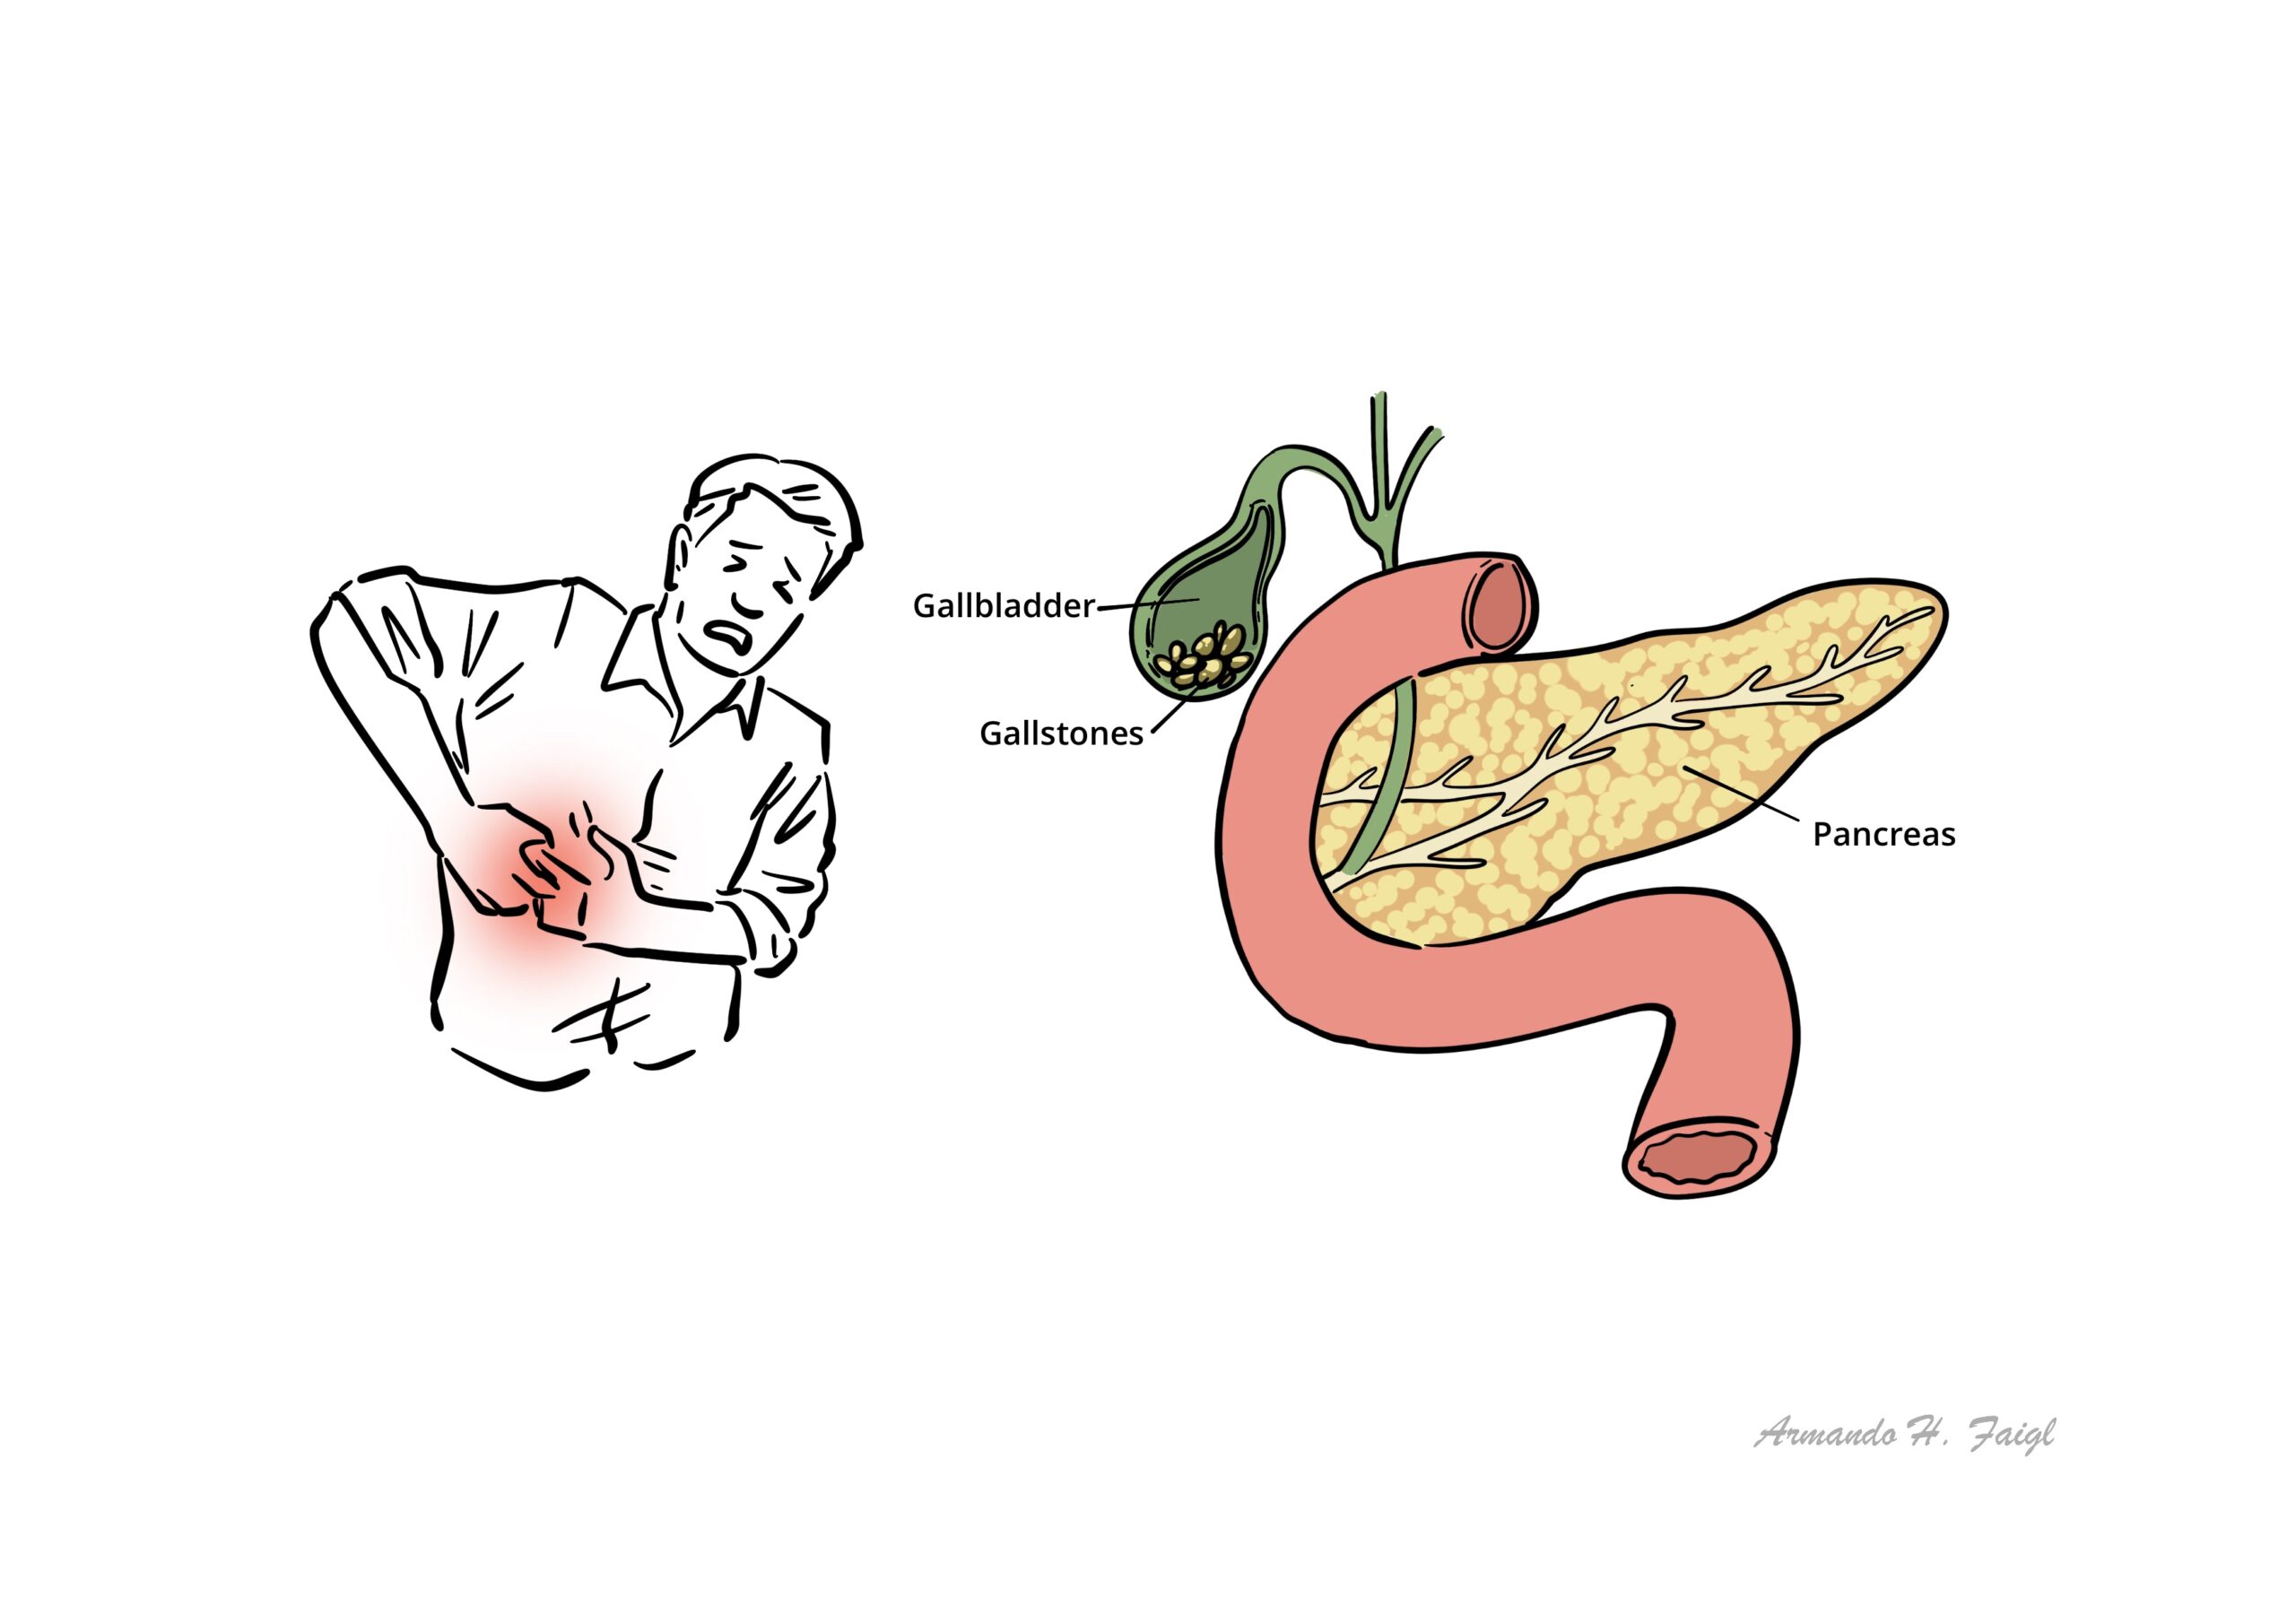
The gallbladder stores and concentrates bile produced by the liver. It empties through the cystic duct, which joins the common hepatic duct to form the common bile duct. Bile passes through the distal duct and ampulla into the duodenum; the pancreatic duct opens at or near the same ampulla. Transient blockage of the cystic duct causes biliary pain, prolonged obstruction may cause cholecystitis, and a common bile duct stone may cause jaundice, cholangitis or pancreatitis.
Aetiology & Risk Factors
| Stone type or factor | Mechanism and associations |
|---|---|
| Cholesterol stones | Cholesterol supersaturation, crystal formation and gallbladder hypomotility; associated with increasing age, female sex, pregnancy, obesity, diabetes, rapid weight loss, family history and oestrogen exposure. |
| Black pigment stones | Calcium bilirubinate stones associated with chronic haemolysis and cirrhosis. |
| Brown pigment stones | Associated with biliary stasis and infection; may form within the bile ducts. |
| Other contributors | Terminal ileal disease or resection alters bile salt circulation; prolonged fasting or parenteral nutrition promotes stasis. Some medicines, including ceftriaxone and somatostatin analogues, can promote biliary precipitates or stones. |
Pathophysiology
Gallstones form when bile components become supersaturated, precipitate and aggregate while gallbladder emptying is impaired. Cholesterol crystals may grow in mucin-rich bile. Pigment stones arise from precipitation of calcium bilirubinate, with differing mechanisms for black and brown stones. A stone lodged transiently in the cystic duct raises gallbladder pressure and produces biliary pain. Persistent obstruction causes inflammation and can be complicated by infection or perforation. Migration to the common bile duct can obstruct bile flow; infection behind an obstructed duct produces cholangitis, while obstruction near the ampulla can precipitate pancreatitis.
Gross and Microscopic Pathology
Cholesterol stones are often yellow-green; pigment stones are darker and may be black or brown. Chronic cholecystitis may produce a thickened, fibrotic gallbladder wall. Acute cholecystitis features an inflamed, oedematous wall and may progress to gangrene or perforation. Stone colour alone does not establish the cause in an individual patient.
Clinical Manifestation
| Presentation | Key symptoms and signs |
|---|---|
| Asymptomatic stones | No biliary symptoms; stones are found incidentally. |
| Biliary colic | Steady right upper quadrant or epigastric pain, often radiating to the back or right scapula, lasting at least 30 minutes and typically resolving within hours; nausea or vomiting may occur. Fever and persistent jaundice suggest another process. |
| Acute cholecystitis | Persistent right upper quadrant pain and tenderness, fever, nausea or vomiting, and sometimes a positive Murphy sign. |
| Common bile duct stone | Biliary pain with jaundice, dark urine or pale stools may occur; some stones are clinically silent. |
| Acute cholangitis | Fever or rigors, jaundice and right upper quadrant pain (Charcot triad); hypotension or confusion suggests severe infection. The complete triad need not be present. |
| Gallstone pancreatitis | Severe epigastric pain often radiating to the back, with nausea or vomiting. |
Fever, jaundice, hypotension, confusion or persistent severe pain in a patient with suspected gallstones requires urgent assessment for cholangitis, cholecystitis or pancreatitis.
Diagnosis
Assess pain pattern, fever, jaundice, previous episodes and risk factors. Examine for right upper quadrant tenderness, Murphy sign, jaundice and signs of sepsis. Laboratory tests and imaging are selected according to the suspected complication.
| Investigation | Typical role and findings |
|---|---|
| Full blood count and CRP | Leucocytosis or raised inflammatory markers support inflammation or infection but are not specific. |
| Liver biochemistry and bilirubin | A cholestatic pattern or bilirubin rise raises concern for common bile duct obstruction; results can be normal early or after stone passage. |
| Lipase | Elevation supports acute pancreatitis in a compatible clinical setting. |
| Transabdominal ultrasound | First-line imaging for gallbladder stones; may show wall thickening, pericholecystic fluid, sonographic Murphy sign or duct dilatation. |
| MRCP or endoscopic ultrasound | Clarifies suspected common bile duct stones when risk is intermediate or ultrasound is inconclusive. |
| ERCP | Primarily therapeutic when duct clearance or drainage is indicated; carries procedure-related risk. |
| CT or HIDA scan | CT assesses alternative diagnoses or complications; cholescintigraphy (HIDA) can help if cholecystitis remains uncertain after initial imaging. |
Differential Diagnosis
- Peptic ulcer disease, gastritis or gastro-oesophageal reflux.
- Acute hepatitis and other causes of jaundice.
- Acute pancreatitis from other causes.
- Right lower lobe pneumonia or pleurisy.
- Renal colic or pyelonephritis.
- Acute coronary syndrome, particularly with atypical epigastric pain.
Classification
| Category | Site or defining mechanism | Clinical implication |
|---|---|---|
| Asymptomatic cholelithiasis | Stones remain in gallbladder without biliary symptoms. | Observation is usually appropriate. |
| Symptomatic uncomplicated cholelithiasis | Transient cystic duct obstruction causes biliary colic. | Elective cholecystectomy is commonly offered for recurrent or troublesome symptoms. |
| Acute calculous cholecystitis | Persistent cystic duct obstruction with gallbladder inflammation. | Requires acute assessment and usually early surgery when feasible. |
| Choledocholithiasis | Stone in common bile duct. | Assess need for duct clearance and cholecystectomy. |
| Acute cholangitis | Infected, obstructed biliary system. | Urgent antibiotics and biliary drainage according to severity. |
| Gallstone pancreatitis | Stone passage or ampullary obstruction triggers pancreatic inflammation. | Supportive care; manage persistent obstruction or cholangitis, then prevent recurrence. |
Treatment
| Presentation | Management |
|---|---|
| Asymptomatic gallbladder stones | No routine cholecystectomy for most patients; counsel about symptoms and individual exceptions. |
| Biliary colic | Analgesia and antiemetics during an attack; laparoscopic cholecystectomy for recurrent or significant symptomatic disease. |
| Acute calculous cholecystitis | Fluids, analgesia and antibiotics when indicated, with early laparoscopic cholecystectomy when feasible. Consider gallbladder drainage if surgery is unsafe or infection cannot be controlled. |
| Choledocholithiasis | Risk-stratify; confirm with MRCP or endoscopic ultrasound when appropriate. ERCP for indicated duct clearance, or surgical bile duct exploration where available, followed by cholecystectomy when appropriate. |
| Acute cholangitis | Sepsis care, intravenous antibiotics and timely biliary drainage, commonly by ERCP; urgency depends on severity. |
| Gallstone pancreatitis | Supportive pancreatitis care. ERCP is indicated for concurrent cholangitis or persistent biliary obstruction, not routinely for every case. Cholecystectomy is generally performed during the same admission after mild disease; timing differs after severe pancreatitis. |
ERCP is not a routine diagnostic test for every gallstone: ultrasound is first-line for gallbladder stones, while MRCP or endoscopic ultrasound can confirm an uncertain common bile duct stone before therapeutic ERCP.
Complications & Prognosis
Complications
- Recurrent biliary pain and acute or chronic cholecystitis.
- Gallbladder empyema, gangrene or perforation and associated sepsis.
- Choledocholithiasis with obstructive jaundice, cholangitis or acute pancreatitis.
- Mirizzi syndrome: an impacted neck or cystic duct stone compresses the common hepatic duct.
- Gallstone ileus: bowel obstruction from a stone passing through a biliary-enteric fistula.
- Recurrent biliary infection or duct stricture in selected patients with intrahepatic stones (hepatolithiasis).
- Treatment complications include bile duct injury, bile leak or retained stones after surgery, and pancreatitis after ERCP.
Prognosis
Most incidentally discovered gallstones remain asymptomatic. Biliary colic can recur, while complicated disease may cause serious infection, pancreatitis or obstruction. Cholecystectomy usually resolves gallbladder-related symptoms and prevents further gallbladder stone episodes; outcome after cholangitis or pancreatitis depends on severity and prompt control of obstruction and infection.
References
- Lammert F, Gurusamy K, Ko CW, Miquel JF, Méndez-Sánchez N, Portincasa P, et al. Gallstones. Nat Rev Dis Primers. 2016;2:16024. doi:10.1038/nrdp.2016.24.
- European Association for the Study of the Liver (EASL). EASL Clinical Practice Guidelines on the prevention, diagnosis and treatment of gallstones. J Hepatol. 2016;65(1):146-181. doi:10.1016/j.jhep.2016.03.005.
- Pisano M, Allievi N, Gurusamy K, Borzellino G, Cimbanassi S, Boerna D, et al. 2020 World Society of Emergency Surgery updated guidelines for the diagnosis and treatment of acute calculus cholecystitis. World J Emerg Surg. 2020;15(1):61. doi:10.1186/s13017-020-00336-x.
- ASGE Standards of Practice Committee, Buxbaum JL, Abbas Fehmi SM, Sultan S, Fishman DS, Qumseya BJ, et al. ASGE guideline on the role of endoscopy in the evaluation and management of choledocholithiasis. Gastrointest Endosc. 2019;89(6):1075-1105.e15. doi:10.1016/j.gie.2018.10.001.
- Miura F, Okamoto K, Takada T, Strasberg SM, Asbun HJ, Pitt HA, et al. Tokyo Guidelines 2018: initial management of acute biliary infection and flowchart for acute cholangitis. J Hepatobiliary Pancreat Sci. 2018;25(1):31-40. doi:10.1002/jhbp.509.
Members only discussions coming soon…