

Anorexia Nervosa

Overview
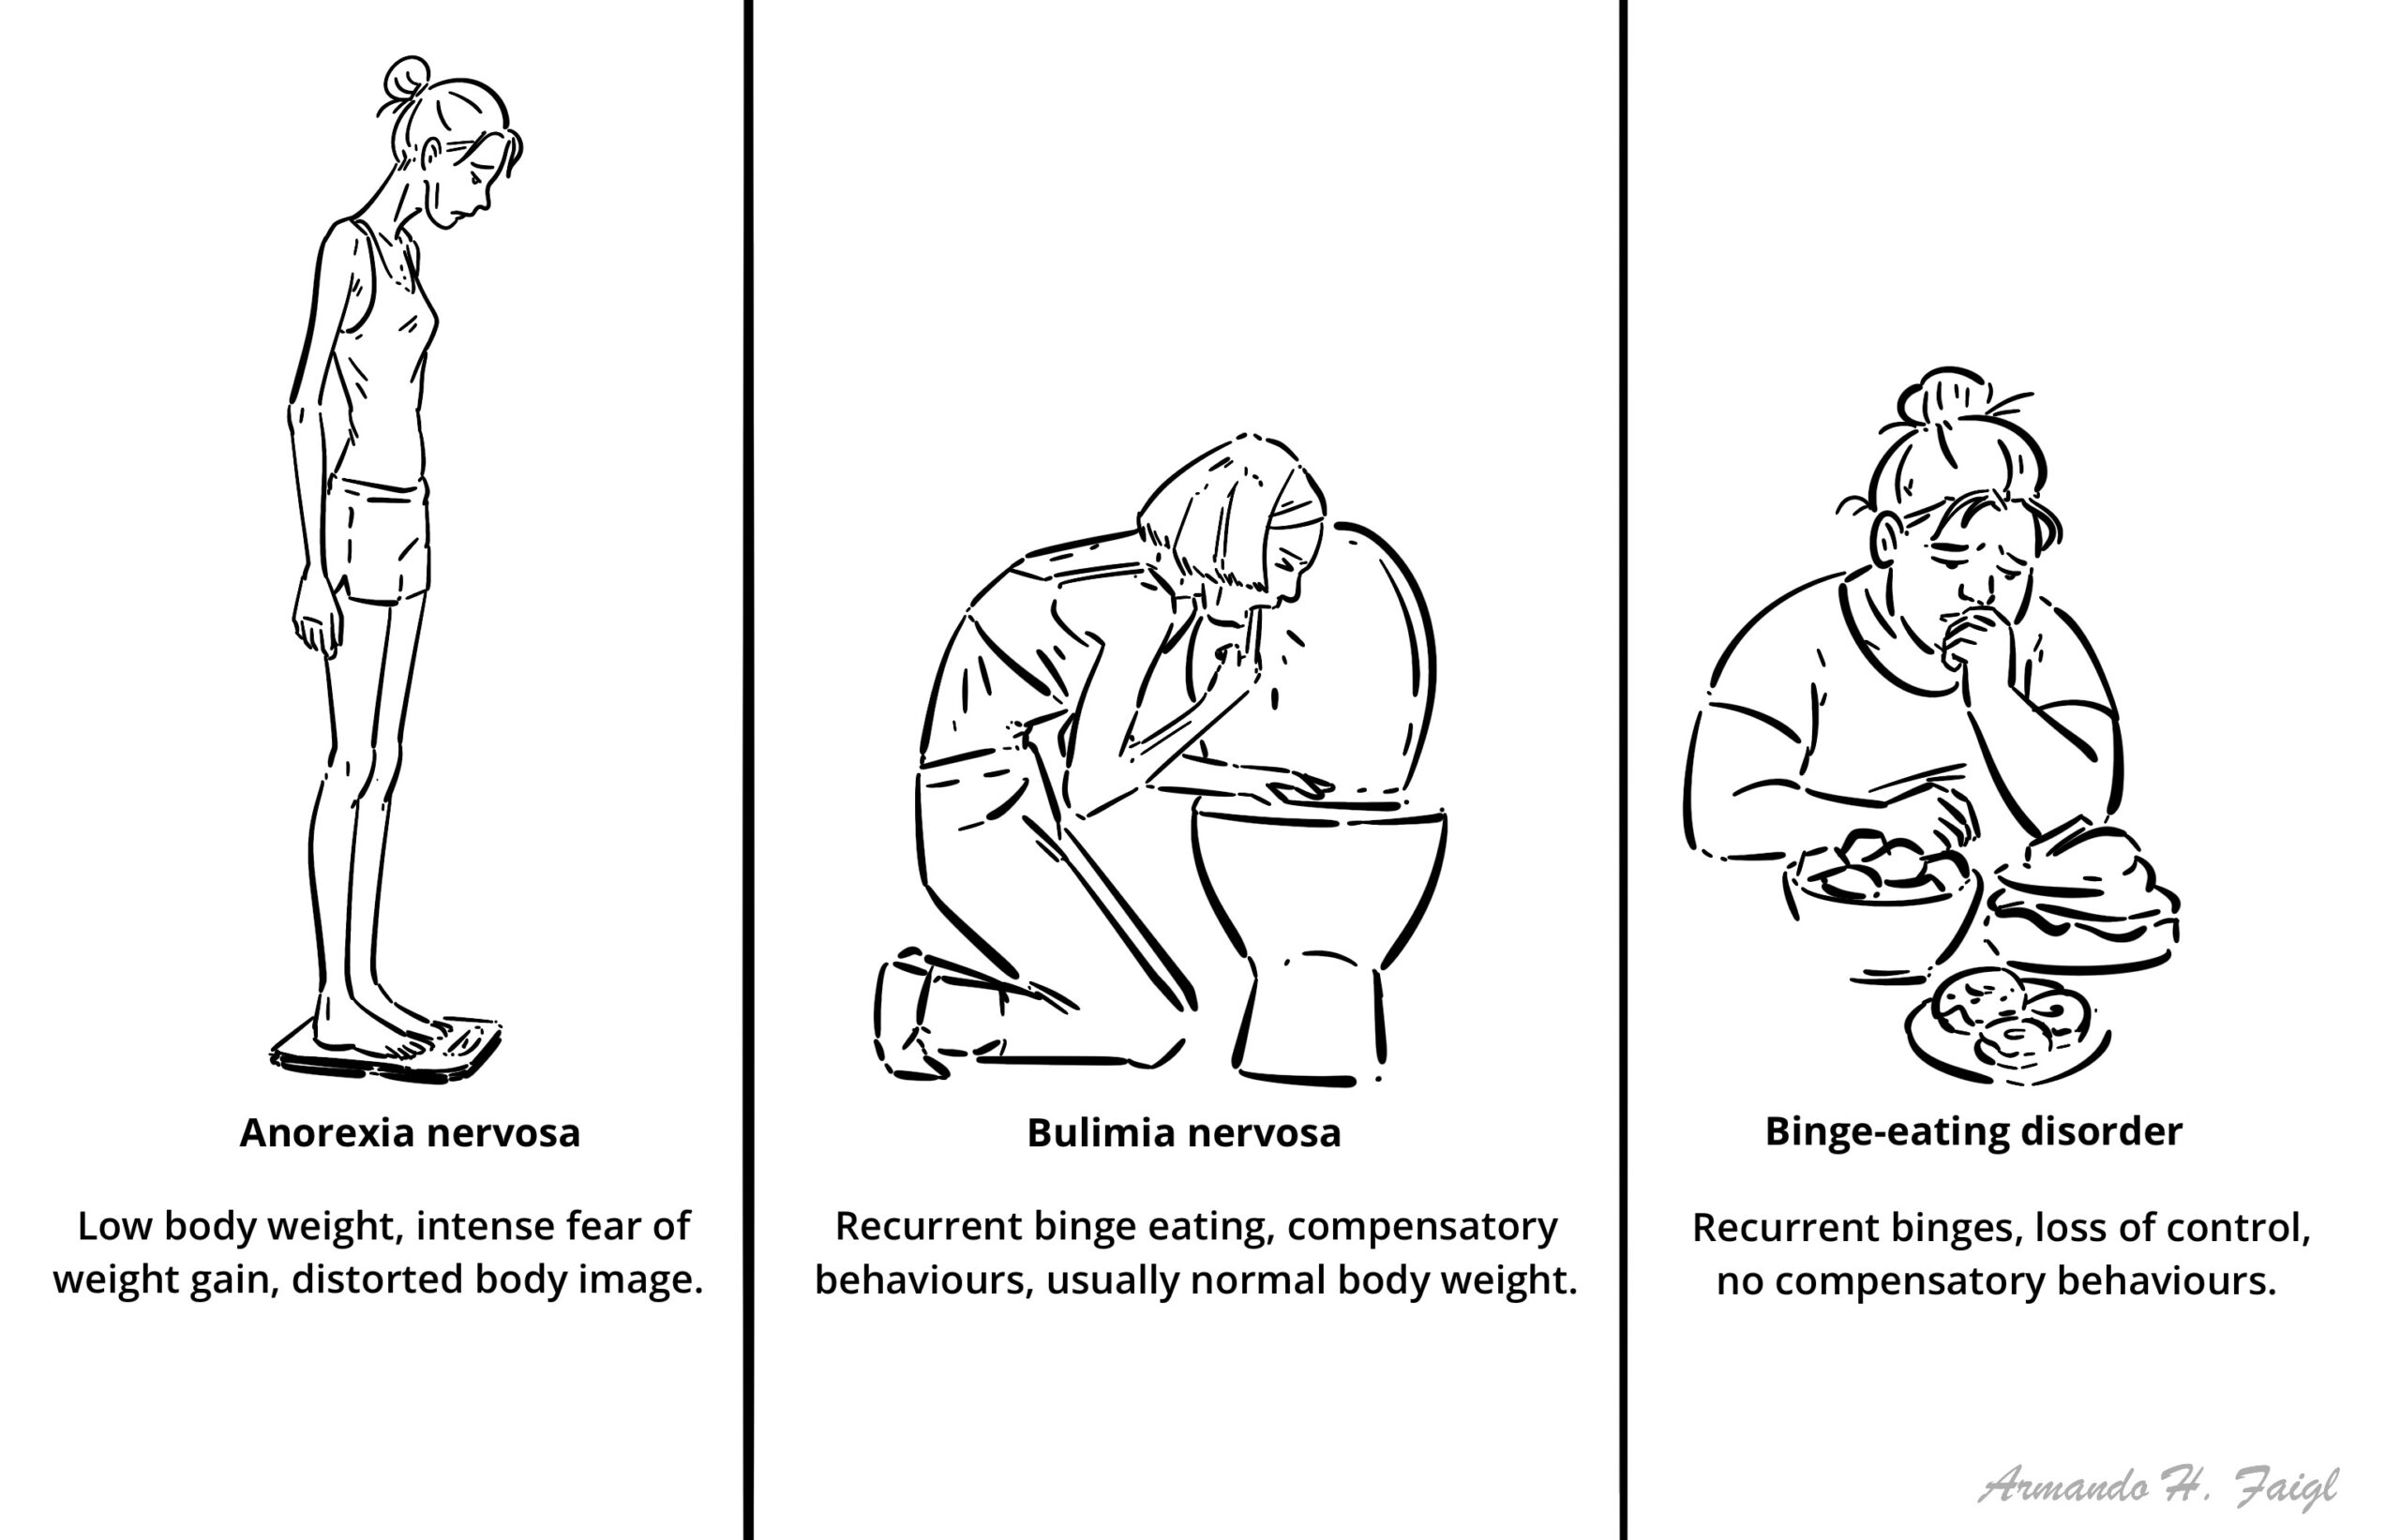
Anorexia nervosa is an eating disorder characterised by restriction of energy intake leading to significantly low body weight, intense fear of weight gain or persistent behaviours preventing weight gain, and disturbance in the experience or significance of body weight and shape. It often begins in adolescence or young adulthood and is more frequently recognised in females, but affects all genders and backgrounds. Clinical features include restrictive eating, weight loss, excessive exercise and physiological consequences of malnutrition. It can cause life-threatening medical instability and increased suicide risk; early multidisciplinary treatment supports nutritional, psychological and functional recovery.
Definition
- Anorexia nervosa
- a psychiatric eating disorder with restrictive intake, significantly low weight and characteristic weight/shape-related psychopathology. Anorexia, as a symptom, means reduced appetite and is not synonymous with anorexia nervosa.
- Refeeding syndrome
- potentially dangerous metabolic and fluid shifts when nutrition is reintroduced after significant undernutrition.
Anatomy & Physiology
- Energy availability supports cardiac function, thermoregulation, growth and reproductive endocrine function.
- Prolonged undernutrition affects multiple organ systems, including cardiovascular, gastrointestinal, endocrine, skeletal and neurological function.
- Hypothalamic–pituitary–gonadal suppression contributes to amenorrhoea or reduced libido; impaired bone health reflects nutritional and hormonal effects.
Aetiology & Risk Factors
Aetiology
A multifactorial disorder involving genetic susceptibility, biological and metabolic factors, psychological traits and environmental influences. Genetic research supports overlapping psychiatric and metabolic contributions; there is no single causal gene or universal precipitant. Families should not be blamed for causing the illness.
Risk Factors
- Family history of eating disorders and genetic vulnerability.
- Adolescence, dieting or restrictive eating, and exposure to weight/shape pressure or weight stigma.
- Perfectionism, anxiety and rigid patterns of thinking may contribute to vulnerability or maintenance.
- Participation in settings emphasising leanness, appearance or weight control.
- Trauma and adverse experiences may be relevant in some individuals, but are not required for diagnosis.
Pathophysiology
| Process | Clinical consequence |
|---|---|
| Restriction and inadequate energy intake | Weight loss, loss of muscle and fat, reduced physiological reserve. |
| Starvation-related cardiovascular adaptation | Bradycardia, hypotension and reduced exercise tolerance. |
| Endocrine and metabolic adaptation | Hypothermia, reproductive suppression and impaired bone health. |
| Malnutrition and psychological reinforcement | Food preoccupation, impaired concentration and increasingly rigid behaviours can maintain restriction. |
| Reintroduction of nutrition after starvation | Insulin-mediated shifts of phosphate, potassium and magnesium into cells, increased thiamine demand and fluid retention can produce refeeding complications. |
Malnutrition can worsen mood, cognition and gastrointestinal symptoms, making eating and psychological treatment more difficult. Nutritional rehabilitation is therefore part of treatment of the illness rather than simply correction of a laboratory abnormality. No characteristic tissue biopsy is required for diagnosis. [2,3,5,6]
How might starvation-related bloating, anxiety and impaired concentration reinforce food restriction?
Clinical Manifestation
Eating behaviours and psychological features
- Restriction, avoidance of energy-dense foods, rigid food rules or rituals, and distress around meals.
- Fear of weight gain, body checking, excessive influence of weight/shape on self-evaluation, or limited recognition of illness severity.
- Excessive exercise; some patients also have binge eating, self-induced vomiting or misuse of laxatives/diuretics.
- Social withdrawal, irritability, low mood, anxiety and impaired concentration.
Physical symptoms and examination
- Weight loss or failure to gain expected weight during growth; fatigue, weakness, dizziness or syncope.
- Cold intolerance, constipation, abdominal bloating and early satiety.
- Bradycardia, hypotension, postural changes, hypothermia, muscle wasting, dry skin and lanugo hair.
- Amenorrhoea or menstrual irregularity, reduced libido, delayed puberty or faltering growth.
- Purging may produce dental erosion, parotid enlargement or hand calluses, but their absence does not exclude it.
Amenorrhoea is not required for diagnosis. A person can have severe restrictive-eating-related medical instability at a normal or higher BMI, including in atypical anorexia nervosa.
Diagnosis
Diagnostic Criteria/Scoring Systems
Diagnosis is clinical. The core DSM-5-TR criteria can be summarised as follows; assess all three together and consider age, development, weight trajectory and physical health.
| Criterion | Summary |
|---|---|
| Restricted intake and low weight | Energy restriction results in significantly low body weight for the person’s age, sex, development and health. |
| Fear or weight-gain-preventing behaviour | Intense fear of gaining weight/becoming fat, or persistent behaviour interfering with weight gain despite low weight. |
| Weight/shape disturbance or impaired recognition | Disturbed experience of weight/shape, excessive influence on self-evaluation, or persistent lack of recognition of the seriousness of low weight. |
Clinical assessment
- Take a sensitive, non-judgemental history of intake, weight trajectory, exercise, bingeing/purging and medication or substance use.
- Assess depression, anxiety, self-harm, suicide risk and impact on school, work and relationships. Seek collateral history with appropriate consent.
- Record weight and height, growth trajectory in young people, temperature, hydration, pulse and lying/standing blood pressure.
- SCOFF can support screening but cannot establish or exclude the diagnosis alone. Normal blood results do not establish medical safety.
Investigations
| Investigation | Purpose / possible findings |
|---|---|
| FBC | Anaemia, leucopenia or thrombocytopenia from malnutrition. |
| Electrolytes, renal function, glucose, phosphate and magnesium | Dehydration, hypoglycaemia and purging/refeeding-related electrolyte disturbances; baseline results may be normal. |
| Liver function and calcium/bone profile | Assess hepatic effects and nutritional complications. |
| ECG | Bradycardia, arrhythmia and QTc prolongation; consider electrolyte abnormalities and medicines that prolong QT. |
| Targeted tests | Pregnancy testing, thyroid testing, coeliac testing or other investigations when history suggests alternative/coexisting disease. |
| Bone density assessment | Consider with prolonged underweight, bone pain or recurrent fractures; apply age-specific specialist guidance. |
Medical risk: do not miss
- Urgent medical assessment for syncope, severe weakness, chest pain, arrhythmia, marked bradycardia, hypotension, hypothermia, dehydration or confusion.
- Severe electrolyte disturbance, hypoglycaemia, acute food/fluid refusal, rapid weight loss or inability to maintain safe intake require escalation.
- Assess suicidality and self-harm alongside physical instability. Hospitalisation decisions use the complete risk profile and local adult/paediatric protocols, rather than a BMI threshold alone.
Differential Diagnosis
- Atypical anorexia nervosa: the anorexia nervosa pattern is present, but weight remains within or above the normal range despite significant weight loss.
- Avoidant/restrictive food intake disorder (ARFID): restriction related to low interest, sensory characteristics or fear of aversive consequences rather than weight/shape concerns.
- Bulimia nervosa: recurrent bingeing and compensatory behaviours without the significantly low weight defining anorexia nervosa.
- Medical causes of weight loss: coeliac disease, inflammatory bowel disease, hyperthyroidism, diabetes, chronic infection or malignancy.
- Depression or other psychiatric illness causing reduced intake; assess the reason for restriction and coexisting disorders.
Classification
| Subtype / specifier | Key distinction |
|---|---|
| Restricting type | During the preceding three months, no recurrent binge eating or purging; weight loss chiefly through restriction, fasting and/or excessive exercise. |
| Binge-eating/purging type | Recurrent binge eating or purging during the preceding three months; purging may occur without binge eating. |
| Partial or full remission | Describes sustained improvement after previously meeting full diagnostic criteria. |
BMI helps describe nutritional status but does not fully capture illness severity. The APA’s May 2026 severity-specifier update emphasises symptoms, functional impairment and medical complications. Assess rapid weight loss, vital signs, electrolytes, ECG and psychiatric risk independently. [8]
Treatment
General approach
Use coordinated care involving a medical clinician, eating-disorder mental health team and dietitian, with family/carer involvement where appropriate. Goals include medical stabilisation, restoration of adequate nutrition and a healthy individual weight trajectory, reduction of eating-disorder behaviours and psychological recovery. Use the least restrictive setting that can safely provide treatment.
Nutritional rehabilitation and refeeding
- Establish a supervised, individualised nutritional plan; oral nutrition is preferred when feasible, with enteral feeding when clinically needed.
- Assess refeeding risk before starting and monitor phosphate, potassium, magnesium, glucose, fluid balance and clinical status closely during early rehabilitation.
- Provide thiamine and correct electrolyte deficits according to the specialist/local refeeding protocol.
- Avoid both unsafe unmonitored refeeding and prolonged underfeeding; prescribe intake and increases according to clinical risk and monitoring capacity.
- Manage dehydration cautiously; severely malnourished patients may poorly tolerate rapid fluid loading.
Refeeding syndrome may present with falling phosphate, fluid retention, weakness, arrhythmia or organ dysfunction. Normal baseline phosphate does not remove the need for monitoring.
Psychological treatment
- Children/adolescents: offer anorexia-focused family therapy/family-based approaches; carers support nutritional recovery without being blamed for the illness.
- Adults: eating-disorder-focused CBT, MANTRA or specialist supportive clinical management are established options.
- Adapt treatment to development, preferences, comorbidity and response; include relapse prevention and a plan for returning to everyday activities.
Medication and associated problems
- Medication is not a sole treatment for anorexia nervosa. Treat psychiatric comorbidity when indicated, accounting for malnutrition, electrolyte abnormalities and cardiac risk.
- Restrict excessive exercise during medical instability; address constipation, bone health and nutritional deficiencies through the treatment plan.
- Severe refusal of life-preserving treatment requires urgent specialist assessment of capacity and the applicable care framework.
Complications and Prognosis
Complications
- Cardiovascular: severe bradycardia, hypotension, arrhythmias and cardiac failure; correct contributing electrolyte deficits and monitor high-risk patients.
- Metabolic: hypoglycaemia, dehydration and electrolyte derangement, including refeeding syndrome.
- Endocrine/skeletal: reproductive dysfunction, impaired growth, low bone density and fractures.
- Gastrointestinal/haematological: constipation, impaired gastric emptying, liver abnormalities and cytopenias.
- Psychiatric: depression, anxiety, self-harm, suicide risk and social/educational impairment.
- Treatment-related: refeeding complications and medication adverse effects; monitor rather than withholding necessary nutrition.
Prognosis
- Recovery is possible, but may require prolonged treatment; relapse and persistent illness occur. Weight restoration alone does not demonstrate complete psychological recovery.
- Early recognition, sustained engagement and continuity of care support recovery. Monitor eating behaviours, functioning, growth/weight trajectory and medical risk.
- Mortality is increased from medical complications and suicide. A historical meta-analysis reported approximately 5.1 deaths per 1,000 person-years and a standardised mortality ratio of 5.86; these pooled cohort estimates are not an individual prediction. [11]
References
1. American Psychiatric Association. Diagnostic and statistical manual of mental disorders. 5th ed, text revision. Washington (DC): American Psychiatric Association Publishing; 2022.
2. National Institute for Health and Care Excellence. Eating disorders: recognition and treatment. NICE guideline NG69 [Internet]. London: NICE; 2017 [updated 2020; cited 2026 Oct 6]. Available from: https://www.nice.org.uk/guidance/ng69
3. National Institute of Mental Health. Eating disorders: what you need to know [Internet]. Bethesda (MD): NIMH; [cited 2026 Oct 6]. Available from: https://www.nimh.nih.gov/health/publications/eating-disorders
4. American Psychiatric Association. What are eating disorders? [Internet]. [cited 2026 Oct 6]. Available from: https://www.psychiatry.org/patients-families/eating-disorders/what-are-eating-disorders
5. Watson HJ, Yilmaz Z, Thornton LM, Hübel C, Coleman JRI, Gaspar HA, et al. Genome-wide association study identifies eight risk loci and implicates metabo-psychiatric origins for anorexia nervosa. Nat Genet. 2019;51(8):1207–1214. doi:10.1038/s41588-019-0439-2.
6. Royal College of Psychiatrists. Medical emergencies in eating disorders: guidance on recognition and management. College Report CR233. London: RCPsych; 2022. Available from: https://meed.org.uk/
7. Royal Children’s Hospital Melbourne. Management of eating disorders in the emergency department [Internet]. [cited 2026 Oct 6]. Available from: https://www.rch.org.au/clinicalguide/guideline_index/Management_of_Eating_Disorders_in_the_Emergency_Department/
8. American Psychiatric Association. Proposed changes: approved DSM-5-TR updates — eating-disorder severity specifiers, May 2026 [Internet]. [cited 2026 Oct 6]. Available from: https://www.psychiatry.org/psychiatrists/practice/dsm/proposed-changes
9. NSW Ministry of Health. Guidelines for the inpatient management of adult eating disorders in general medical and psychiatric settings in NSW. Sydney: NSW Ministry of Health; 2014. Available from: https://www.health.nsw.gov.au/mentalhealth/resources/Publications/inpatient-adult-eating-disorders.pdf
10. National Institute for Health and Care Excellence. 2024 exceptional surveillance of eating disorders: recognition and treatment (NG69) [Internet]. London: NICE; 2024. Available from: https://www.nice.org.uk/guidance/ng69/resources
11. Arcelus J, Mitchell AJ, Wales J, Nielsen S. Mortality rates in patients with anorexia nervosa and other eating disorders: a meta-analysis of 36 studies. Arch Gen Psychiatry. 2011;68(7):724–731. doi:10.1001/archgenpsychiatry.2011.74.










Members only discussions coming soon…