

Piriformis Syndrome
Overview
Piriformis syndrome describes buttock pain attributed to irritation or entrapment of the sciatic nerve near the piriformis muscle. Pain may radiate down the back of the thigh and resemble lumbar sciatica. Prolonged sitting often aggravates symptoms.
Diagnosis can be difficult because buttock and leg pain have several possible causes and there is no single definitive test for piriformis syndrome. The term deep gluteal syndrome is broader: it includes sciatic nerve entrapment elsewhere in the deep gluteal space. Management usually begins with activity modification and physiotherapy, while an image-guided injection may be considered if symptoms persist.
Definition
- Piriformis muscle
- A deep buttock muscle extending from the sacrum to the greater trochanter that helps rotate and stabilise the hip.
- Piriformis syndrome
- Buttock pain, sometimes with radiating leg symptoms, attributed to irritation of the sciatic nerve in relation to the piriformis muscle.
- Deep gluteal syndrome
- Non-disc-related entrapment of the sciatic nerve in the deep gluteal space; piriformis-related entrapment is one possible cause.
- FAIR manoeuvre
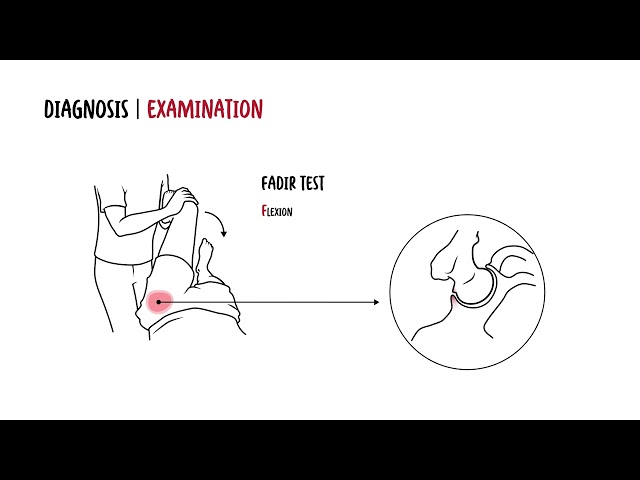
- Hip flexion, adduction and internal rotation, used to provoke symptoms by placing tension on structures in the deep buttock.
Anatomy & Physiology
The piriformis arises from the anterior surface of the sacrum and attaches to the greater trochanter of the femur. It assists with external rotation of the extended hip and contributes to hip stability. The sciatic nerve usually passes beneath the piriformis before travelling down the posterior thigh. Their close relationship means that changes in the muscle or surrounding tissues may affect the nerve.
Anatomical variation in the course of the sciatic nerve can occur, but variation alone does not establish the diagnosis. Other structures in the deep gluteal space can also irritate the sciatic nerve.
“Piriformis syndrome” names a proposed site of sciatic nerve irritation. Deep gluteal syndrome is the broader term when sciatic nerve entrapment outside the spine is suspected but the exact structure is uncertain.
Aetiology & Risk Factors
Aetiology
The proposed mechanisms include local muscle or tendon irritation, scarring after trauma, and compression of the sciatic nerve by structures in the deep gluteal space. In many patients, a single cause cannot be confirmed.
Associated Factors
- A fall or other injury to the buttock.
- Activities that repeatedly load or irritate the deep hip rotators.
- Prolonged sitting that aggravates an existing painful area.
- Previous hip or pelvic pathology that may alter movement or load through the gluteal region.
These factors can support the history but are not diagnostic on their own.
Pathophysiology
Irritation or mechanical pressure on the sciatic nerve near the piriformis may produce deep buttock pain and pain, tingling or numbness extending into the posterior thigh or leg. Hip movement can increase tension or pressure in the deep gluteal space and reproduce symptoms.
The same pattern of radiating pain can arise from a lumbar nerve root. Clinical findings should therefore be interpreted in the context of the lumbar spine, hip, peripheral nerves and other potential sources of posterior hip pain.
Clinical Manifestations
- Deep buttock pain, commonly on one side.
- Pain radiating into the posterior thigh and sometimes farther down the leg.
- Symptoms aggravated by prolonged sitting; some patients also report pain with walking, running, climbing stairs or particular hip movements.
- Tenderness in the deep gluteal region or near the greater sciatic notch.
- Reproduction of familiar buttock pain during manoeuvres that tension or activate the piriformis.
Tingling or numbness can occur, but marked or progressive neurological weakness should prompt reassessment for another cause.
| Feature | Piriformis or deep gluteal source | Lumbar radiculopathy |
|---|---|---|
| Predominant pain | Often centred in the deep buttock | Often begins in the lower back or buttock and follows a nerve-root pattern |
| Sitting | Frequently aggravates buttock pain | May also aggravate disc-related symptoms |
| Local examination | Deep gluteal or sciatic-notch tenderness may be present | A focal tender point in the buttock is less characteristic |
| Neurological findings | Often no clear nerve-root pattern | Dermatomal sensory change, myotomal weakness or reflex change may help localise a root |
| Provocation | Familiar pain may occur with hip-position tests | Spinal movement or nerve-root tension tests may reproduce familiar leg pain |
These features overlap. No single row reliably separates the two diagnoses.
Red flags — urgent assessment
New bladder or bowel dysfunction, saddle sensory change, severe or progressive leg weakness, fever with significant spinal or pelvic pain, or a history suggesting fracture, infection or malignancy requires prompt assessment for an alternative serious cause. Do not attribute these features to uncomplicated piriformis syndrome.
Clinical Examination
Palpation of the deep gluteal region may reproduce familiar pain. Provocation manoeuvres include the seated piriformis stretch and FAIR position; pain with resisted hip movement may also be informative. A positive manoeuvre supports clinical suspicion but does not prove that the piriformis is compressing the sciatic nerve.
Diagnosis and Investigation
History and Examination as above
Imaging
- No single imaging or examination test confirms every case. Investigations are guided by the presentation and the need to assess other causes.
- Lumbar MRI: Consider when examination suggests radiculopathy, neurological deficits are present, red flags arise, or persistent symptoms make spinal pathology an important alternative.
- Hip or pelvic imaging: Consider when hip disease, a mass, injury or another local cause is suspected. Specialist imaging may help in selected cases but is not routinely required.
- Electrodiagnostic studies: May be considered when the site of nerve dysfunction remains unclear or another neuropathy is suspected; normal results do not necessarily exclude a deep gluteal pain source.
- Image-guided local anaesthetic injection: Symptom relief after a targeted injection may support the suspected pain source and can also have a therapeutic role. Its result should be interpreted alongside the whole clinical picture.
Differential Diagnosis
| Condition | Clue favouring the alternative |
|---|---|
| Lumbar radiculopathy | Nerve-root distribution, concordant weakness or reflex change, or matching lumbar imaging |
| Hip joint pathology | Groin-centred pain or restricted, painful hip joint movement |
| Greater trochanteric pain syndrome | Focal lateral hip tenderness and pain when lying on that side |
| Sacroiliac or other referred pain | Pain pattern and examination findings that fit a spinal or pelvic source |
| Other deep gluteal entrapment | Sciatic symptoms arising from a structure other than the piriformis |
| Proximal hamstring pathology | Pain localised near the ischial tuberosity and provoked by hamstring loading |
Treatment
Initial Management
Explain the uncertainty of the diagnosis and identify activities that consistently aggravate symptoms. Reduce prolonged sitting or provoking exercise temporarily, while maintaining comfortable movement and gradually returning to normal activity.
Physiotherapy may address hip mobility, gluteal and hip-rotator strength, movement control and a graded return to activity. Stretching can be tried if tolerated; avoid repeatedly forcing movements that reproduce severe radiating pain. Simple analgesia or a short course of an NSAID may be considered when appropriate after assessing individual risks.
Treatment should be guided by the patient’s symptoms and examination. Improvement with physiotherapy does not, by itself, prove that the piriformis was the source of sciatic nerve irritation.
Persistent Symptoms
Reassess the diagnosis if symptoms persist, especially when neurological findings emerge or progress. In selected patients with a convincing deep gluteal pain pattern, a specialist may consider an image-guided local anaesthetic injection, sometimes with corticosteroid, around the suspected structure. The response may help guide further management, although evidence for individual interventions remains limited.
Surgical decompression or release is reserved for uncommon, carefully selected refractory cases after alternative causes have been evaluated.
Complications & Prognosis
Complications
Persistent buttock and radiating leg pain can limit sitting, exercise, work and sleep. An incorrect attribution to piriformis syndrome may delay diagnosis of lumbar radiculopathy, hip disease or another cause. Procedures also carry their own risks, which should be discussed before treatment.
Prognosis
Many patients improve with activity adjustment and rehabilitation, but recovery varies and symptoms can recur. Prognosis is less certain when the pain source has not been clearly established. Persistent symptoms warrant reassessment of the working diagnosis rather than indefinite treatment for presumed piriformis syndrome.
References
- Martin HD, Reddy M, Gómez-Hoyos J. Deep gluteal syndrome. Journal of Hip Preservation Surgery. 2015;2(2):99–107.
- Külcü DG, et al. Deep gluteal syndrome: An underestimated cause of posterior hip pain. 2024.
- Monteleone G, et al. Piriformis syndrome: A systematic review of case reports. 2025.


Members only discussions coming soon…