

Endometrial Cancer

Overview
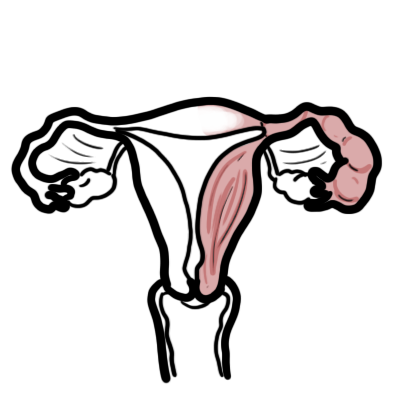
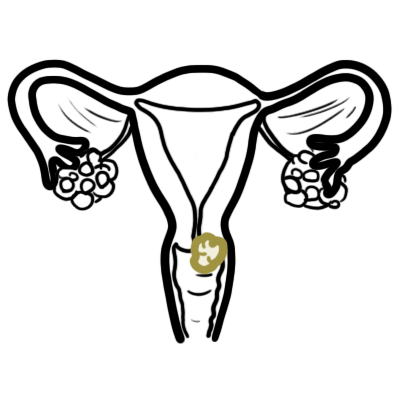
Endometrial carcinoma is an epithelial malignancy of the uterine corpus mucosa, usually an adenocarcinoma. Endometrial carcinoma is the most common female genital tract malignancy. Postmenopausal bleeding always needs to be investigated because it can indicate malignant disorders and premalignant conditions, such as endometrial hyperplasia. The most common etiology of postmenopausal bleeding is atrophic endometritis or vaginitis.
Definition
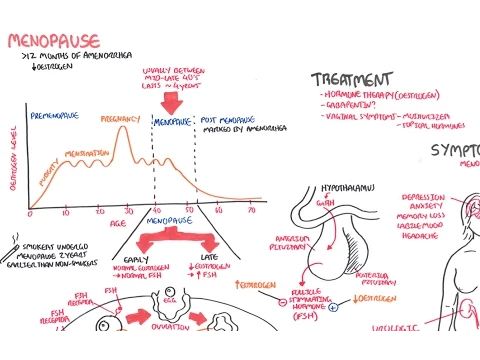
Menopause: Permanent cessation of menstrual periods, determined retrospectively after a woman has experienced 12 months of amenorrhoea without any other obvious pathological cause. The average age is 52, with a range between 45-55 years
Endometrial Carcinoma: An epithelial malignancy of the uterine corpus mucosa, usually an adenocarcinoma.
Endometrial Hyperplasia: Characterised by proliferation of endometrial glands resulting in a greater gland-to-stroma ratio than is observed in normal endometrium
Endometrial Sampling (biopsy): A thin catheter is introduced through the cervix into the uterine cavity under some suction to aspirate endometrial cells.
Endometrial polyps: A growth of endometrial glands and stroma, which projects into the uterine cavity, usually on a stalk; it can cause postmenopausal bleeding.
Atrophic Endometrium: The most common cause of postmenopausal bleeding is friable tissue of the endometrium or vagina due to low estrogen levels.
Endometrial Stripe: Transvaginal sonographic assessment of the endometrial thickness; a thickness greater than 5 mm is abnormal in a postmenopausal woman.
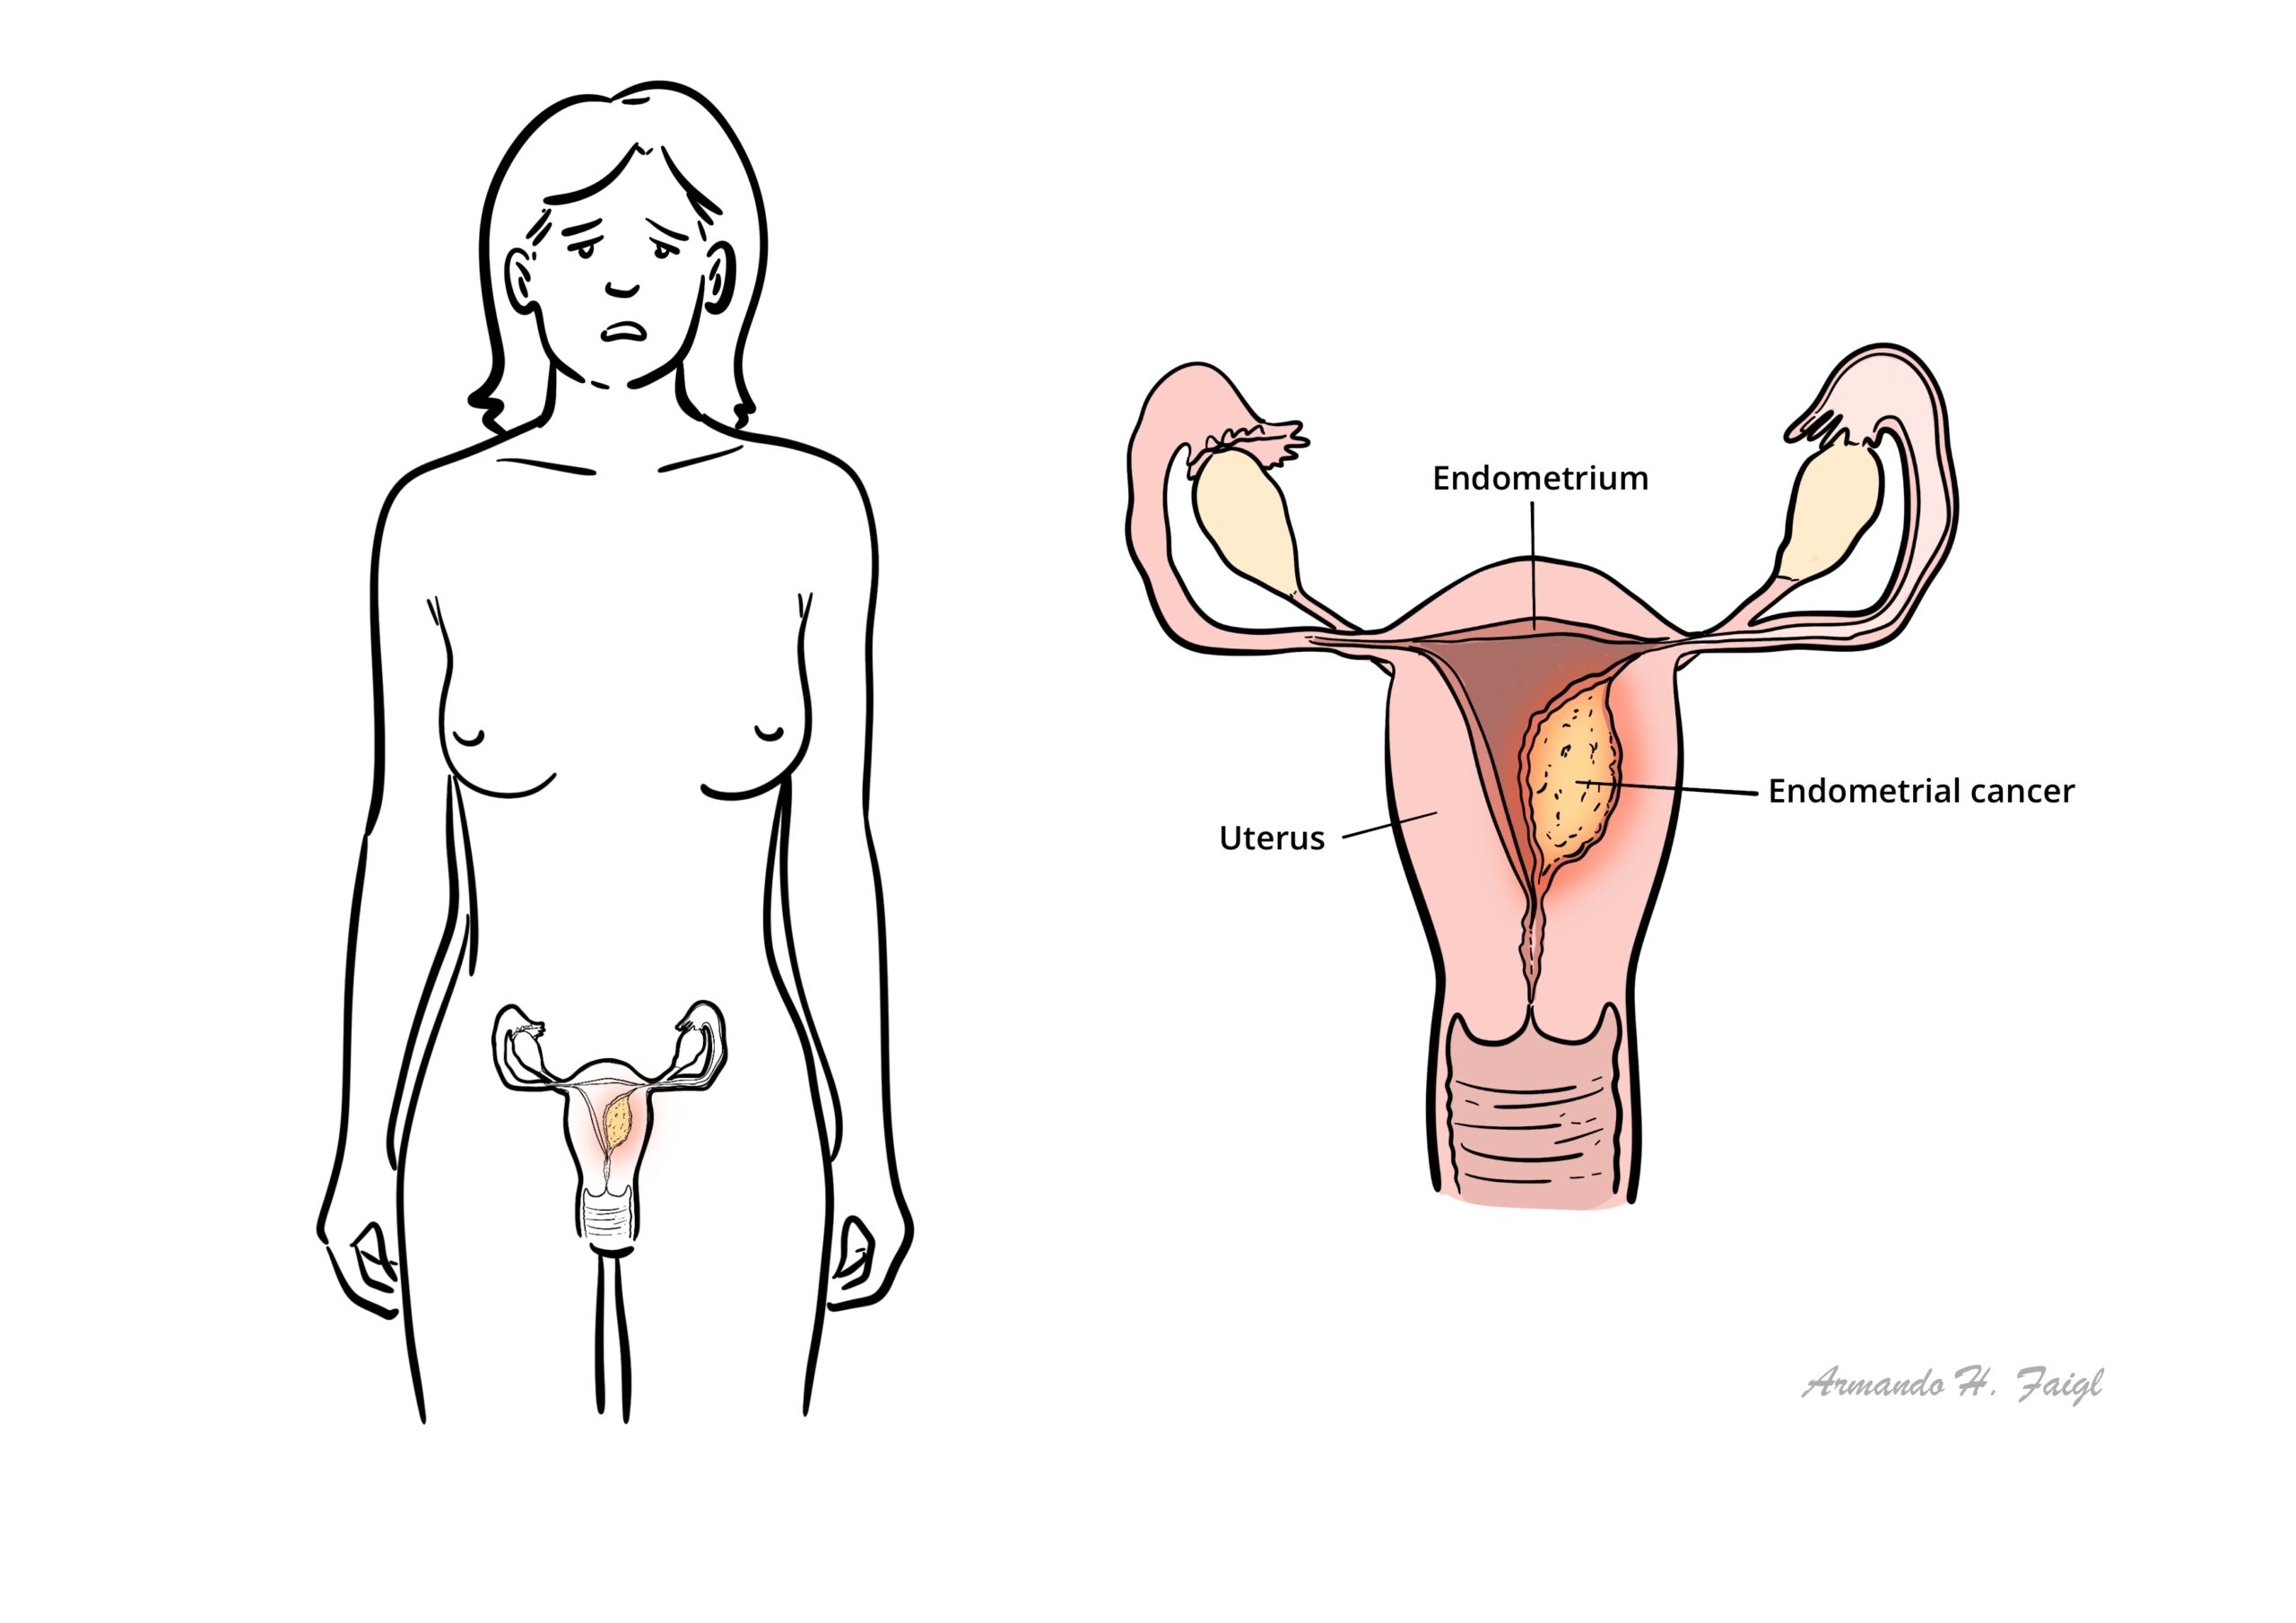
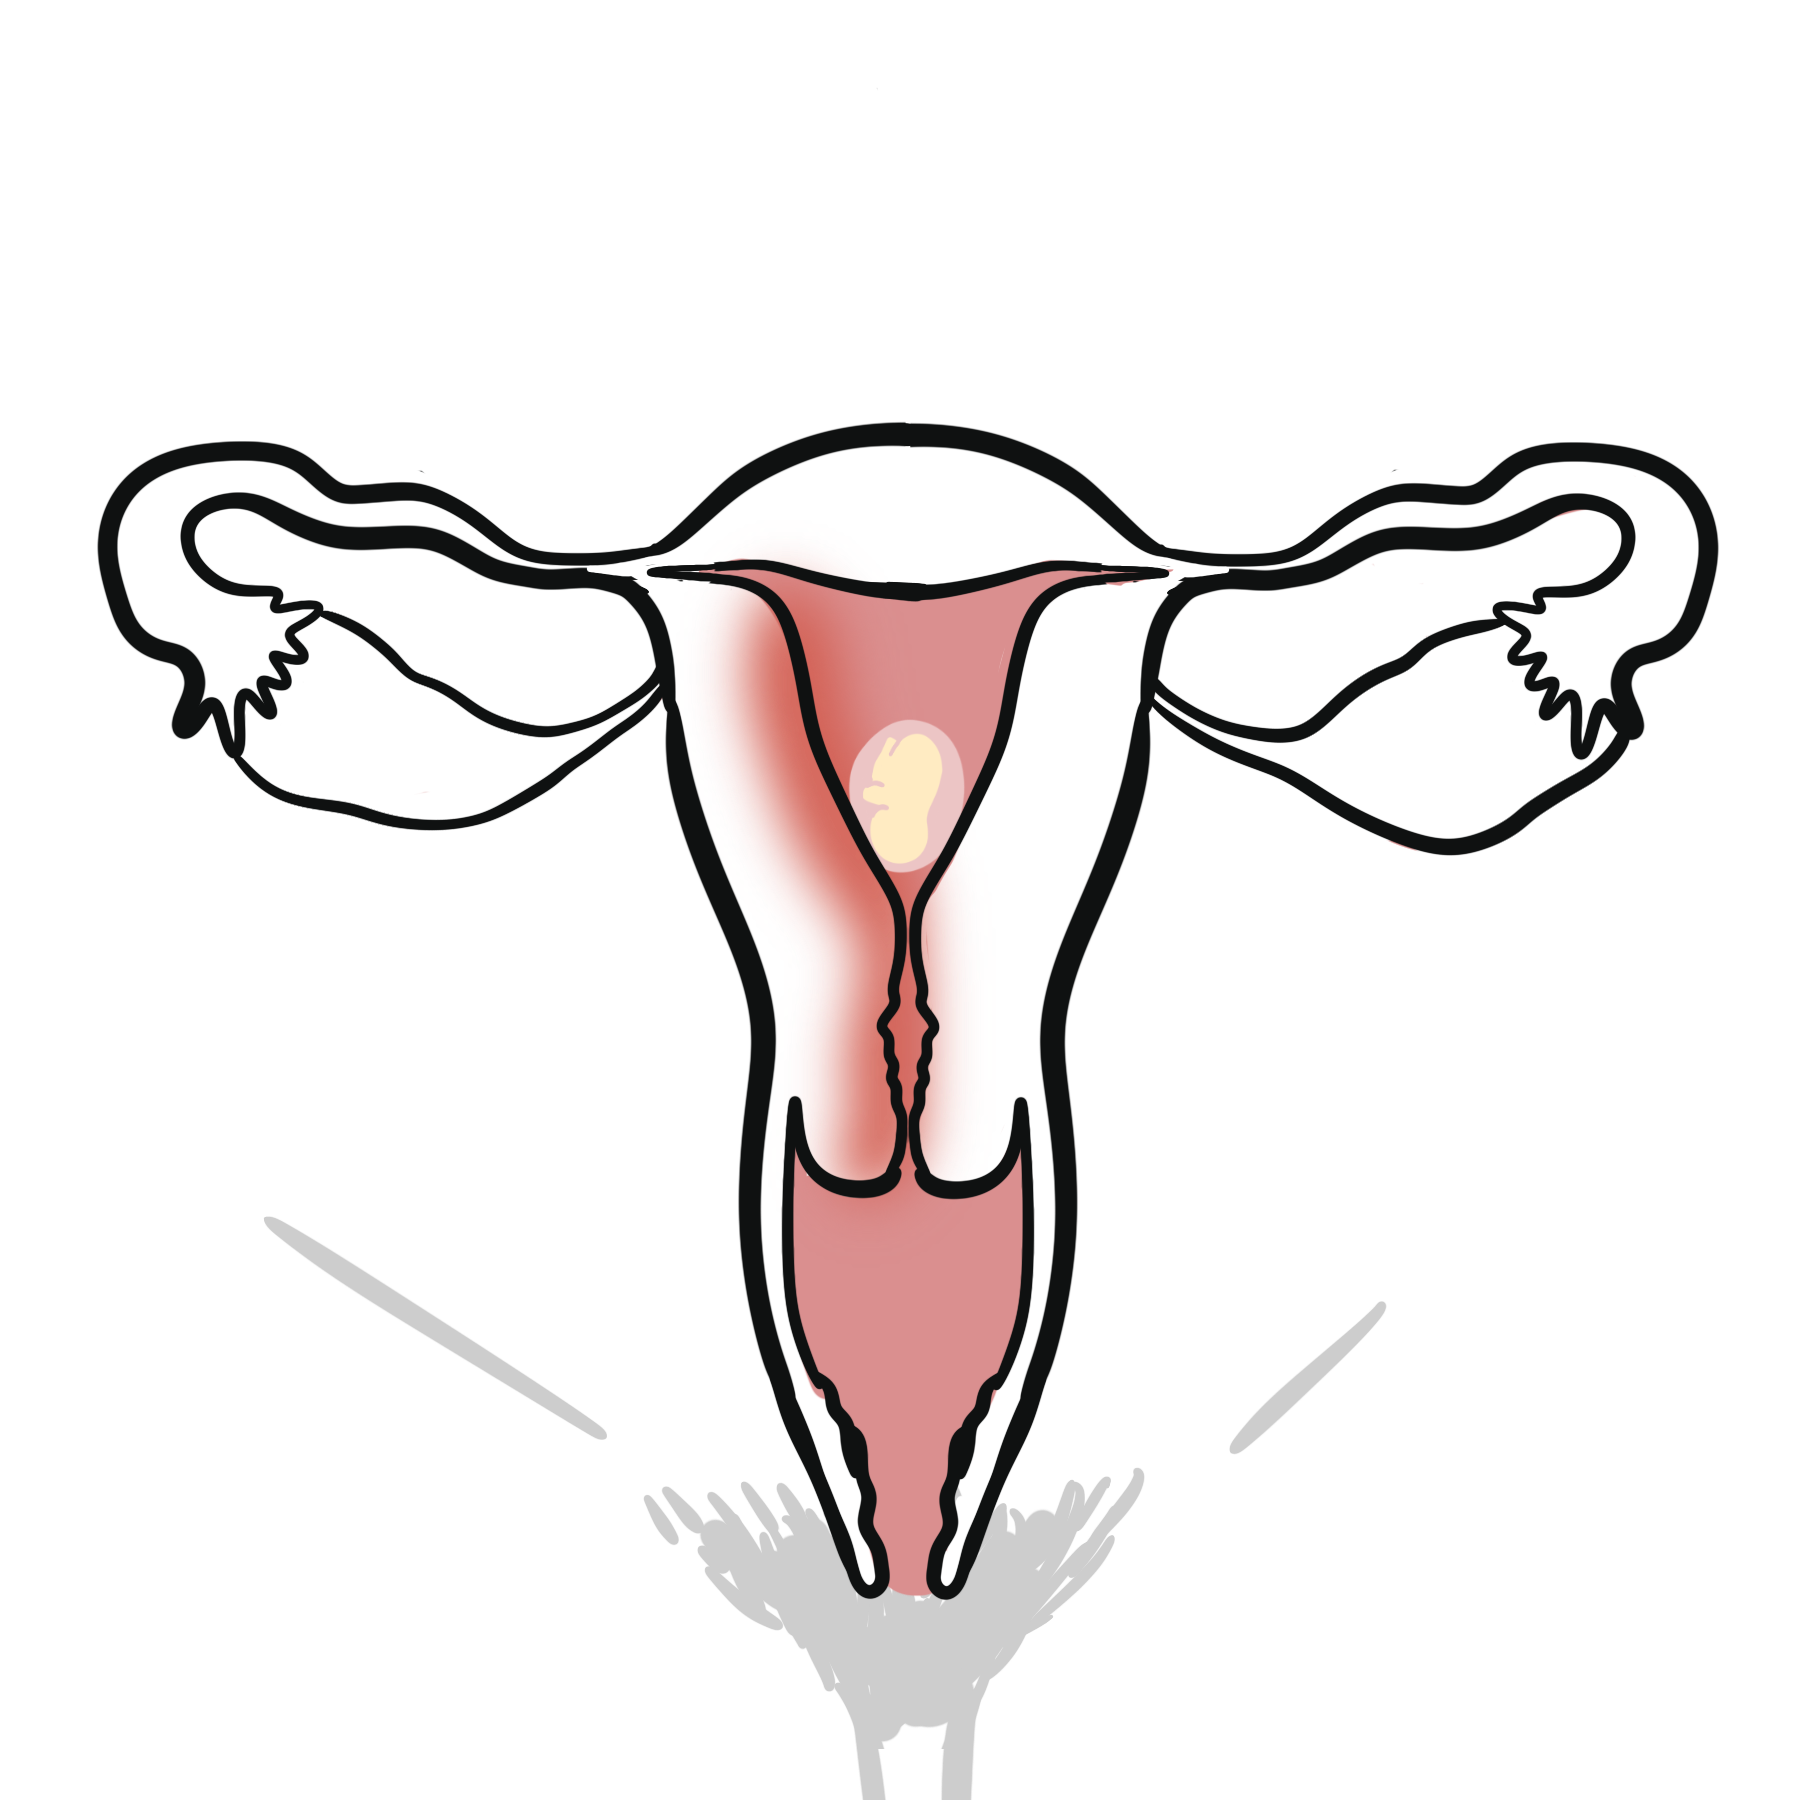
What to notice
Detailed image description
Endometrial carcinoma is the most common female genital tract malignancy.
Epidemiology
- Most common lower gyaenocological cancer
- Most common in postmenopausal women
Atiology & Risk Factors
Aetiology
- Endometrial hyperplasia
- Unopposed endogenous/exogenous oestrogen
- Familial cancer syndromes (family history, Lynch syndrome, Cowden’s syndrome)
Risk Factors
Endometrial malignancy typically developed from unopposed oestrogen. Progesterone stabilises the endometrium.
| Increased risk of endometrial cancer | Protective Factors |
| Early Menarche | Parity (high progesterone in pregnancy) |
| Post-menopausal women | Combined Oral Contraceptive Pill |
| Obestiy, Hypertension, Diabetes | |
| Endometrial hyperplasia | |
| Tamoxifen use | |
| Unopposed endogenous/exogenous oestrogen | |
| Family history of endometrial cancer | |
| Family history of ovarian and breast cancer | |
| Lynch syndrome | |
| Radiotherapy |
Endometrial carcinoma must be ruled out in any patient with postmenopausal bleeding.
Pathophysiology
Epithelial tumours (endometrial carcinoma) is the most common type of endometrial carcinoma, found in up to 90%.
Clinical Manifestation
Abnormal uterine bleeding in postmenopausal women is the cardinal symptom of endometrial cancer. Occasionally, women with no abnormal uterine bleeding present with abnormal findings on cervical cytology. The clinical presentations of the following age group need prompt evaluation to rule out endometrial cancer
- Postmenopausal women – Any bleeding
- Premenopausal (>45yo) – Abnormal uterine bleeding including intermenstrual bleeding , frequent, heavy or prolonged bleeds.
- Younger than 45yo – Persistent abnormal uterine bleeding with risk factors or failed management of the bleeding
Endometrial sampling required for women >45yo with abnormal menstrual symptoms.
Clinical Examination
- Uterine mass
- Fixed uterus or adnexal mass indicating extra-uterine disease
↑ Vaginal discharge due to infection of the uterus (Pyometra) in post-menopasual women is associated with carcinoma in 50% of cases.
Diagnosis & Investigations
- Pelvic Ultrasound (sonography) is first line
- Transvaginal ultrasound
- Endometrial sampling (biopsy)
- Hysteroscopy and D&C if biopsy is not possible
- Pap smear – Primarily used to screen for cervical dysplasia. It is not a screening test for endometrial cancer
Persistent postmenopausal bleeding warrants further investigation (such as hysteroscopy) even after a normal endometrial sampling.
Endometrial carcinoma is a histologic diagnosis made based upon the results of evaluation of an endometrial biopsy, curettage sample, or hysterectomy specimen.
Staging
| International Federation of Gynecology and Obstetrics (FIGO) staging of uterine cancer (2009) | |
| Stage | Description |
| I | Tumour invades cervical stroma, but does not extend beyond the uterus |
| II | Tumour invades cervical stroma, but does not extend beyond the uterus |
| III | Local and regional spread of the tumour |
| IV | Tumour invades the bladder and/or bowel mucosa and/or distant metastases |
Treatment
Management Endometrial cancer is treated by surgery, radiotherapy, chemotherapy, or, commonly, a combination of these therapies, with the goal of maximising the chance of cure, with minimal morbidity.
Hyperplasia is treated with progesterone (oral contraceptive) to stabilize the endometrium.
Surgery (First-line)
- Total hysterectomy + bilateral salpingo-oophorectomy
- Sentinel lymph node biopsy for staging when indicated
Adjuvant Treatment (Risk-dependent)
- Vaginal brachytherapy.
- Carboplatin + paclitaxel ± radiotherapy
Advanced Disease (Stage III–IV)
- Cytoreductive surgery if feasible.
- Chemotherapy: Carboplatin + paclitaxel.
- Immunotherapy: Pembrolizumab or dostarlimab combined with chemotherapy in eligible patients.
Recurrent or Metastatic Disease
- dMMR/MSI-H: PD-1 inhibitors (pembrolizumab or dostarlimab).
- pMMR/MSS: Pembrolizumab + lenvatinib after platinum chemotherapy in eligible patients.
- Hormonal therapy: Progestins for selected low-grade, ER/PR-positive cancers.
- Palliative radiotherapy for symptom control
| Term | Meaning | Clinical significance |
|---|---|---|
| dMMR | Deficient mismatch repair | Defective DNA repair; often responds well to immunotherapy |
| pMMR | Proficient mismatch repair | Functional DNA repair; generally less responsive to immunotherapy alone |
| MSI-H | Microsatellite instability–high | High levels of DNA replication errors; often associated with dMMR |
| MSS | Microsatellite stable | Minimal microsatellite instability; usually associated with pMMR |
Molecular Classification
- POLE-mutated: Excellent prognosis; may allow treatment de-escalation.
- MMRd/MSI-H: Responsive to immunotherapy.
- p53-abnormal: High-risk; often requires intensive treatment.
- NSMP: Treatment guided by stage, grade and other risk factors.
Tumour biomarker status PTEN, Mismatch-repair genes, p53 and HER-2.
Complications & Prognosis
Complications
- Bladder instability following surgery
- Radiotherapy induced vaginal stenosis/atrophy
- Radiotherapy induced bowel or bladder distulae
- Sexual dysfunction following treatment
- Metastatic disease
- Lymphoedema
- Chemotherapy associated toxicity
Most recurrences of endometrial cancer occur within 2 years.
Prognosis
The 5-year survival rate for all types and grades of endometrial adenocarcinoma, following treatment, is:
- 75% to 95% for stage I
- 70% for stage II
- 50% to 60% for stage III
- 5% to 15% for stage IV
References
- Bokhman JV. Two pathogenetic types of endometrial carcinoma. Gynecol Oncol. 1983;15(1):10-17. doi:10.1016/0090-8258(83)90111-7.
- Clarke MA, Long BJ, Del Mar Morillo A, Arbyn M, Bakkum-Gamez JN, Wentzensen N. Association of endometrial cancer risk with postmenopausal bleeding in women: a systematic review and meta-analysis. JAMA Intern Med. 2018;178(9):1210-1222. doi:10.1001/jamainternmed.2018.2820.
- American College of Obstetricians and Gynecologists. ACOG Committee Opinion No. 734: The role of transvaginal ultrasonography in evaluating the endometrium of women with postmenopausal bleeding. Obstet Gynecol. 2018;131(5):e124-e129.
- Cancer Genome Atlas Research Network. Integrated genomic characterization of endometrial carcinoma. Nature. 2013;497(7447):67-73. doi:10.1038/nature12113.
- Creasman W. Revised FIGO staging for carcinoma of the endometrium. Int J Gynaecol Obstet. 2009;105(2):109. doi:10.1016/j.ijgo.2009.02.010.
- Berek JS, Matias-Guiu X, Creutzberg C, Fotopoulou C, Gaffney D, Kehoe S, et al. FIGO staging of endometrial cancer: 2023. Int J Gynaecol Obstet. 2023;162(2):383-394. doi:10.1002/ijgo.14923.
- Concin N, Matias-Guiu X, Vergote I, Cibula D, Mirza MR, Marnitz S, et al. ESGO/ESTRO/ESP guidelines for the management of patients with endometrial carcinoma. Int J Gynecol Cancer. 2021;31(1):12-39. doi:10.1136/ijgc-2020-002230.








Members only discussions coming soon…