

Long-Term Complications of Diabetes (Overview)
Overview
Long-term complications of diabetes are chronic injuries affecting blood vessels, nerves and organs in both type 1 and type 2 diabetes. The principal groups are microvascular disease (retinopathy, kidney disease and neuropathy) and macrovascular disease (coronary, cerebrovascular and peripheral arterial disease). They may develop silently before causing visual loss, kidney failure, pain, disability or limb loss. Screening and multifactorial treatment can prevent or delay many outcomes.1
Definition
- Microvascular complications
- Damage involving small vessels and associated tissues, particularly the retina, kidneys and peripheral nerves.
- Macrovascular complications
- Disease of larger arteries, predominantly atherosclerosis affecting coronary, cerebral and peripheral circulations.
- Diabetes-related foot disease
- Foot ulceration, infection or tissue destruction associated with neuropathy and/or peripheral arterial disease; it is not solely a macrovascular complication.
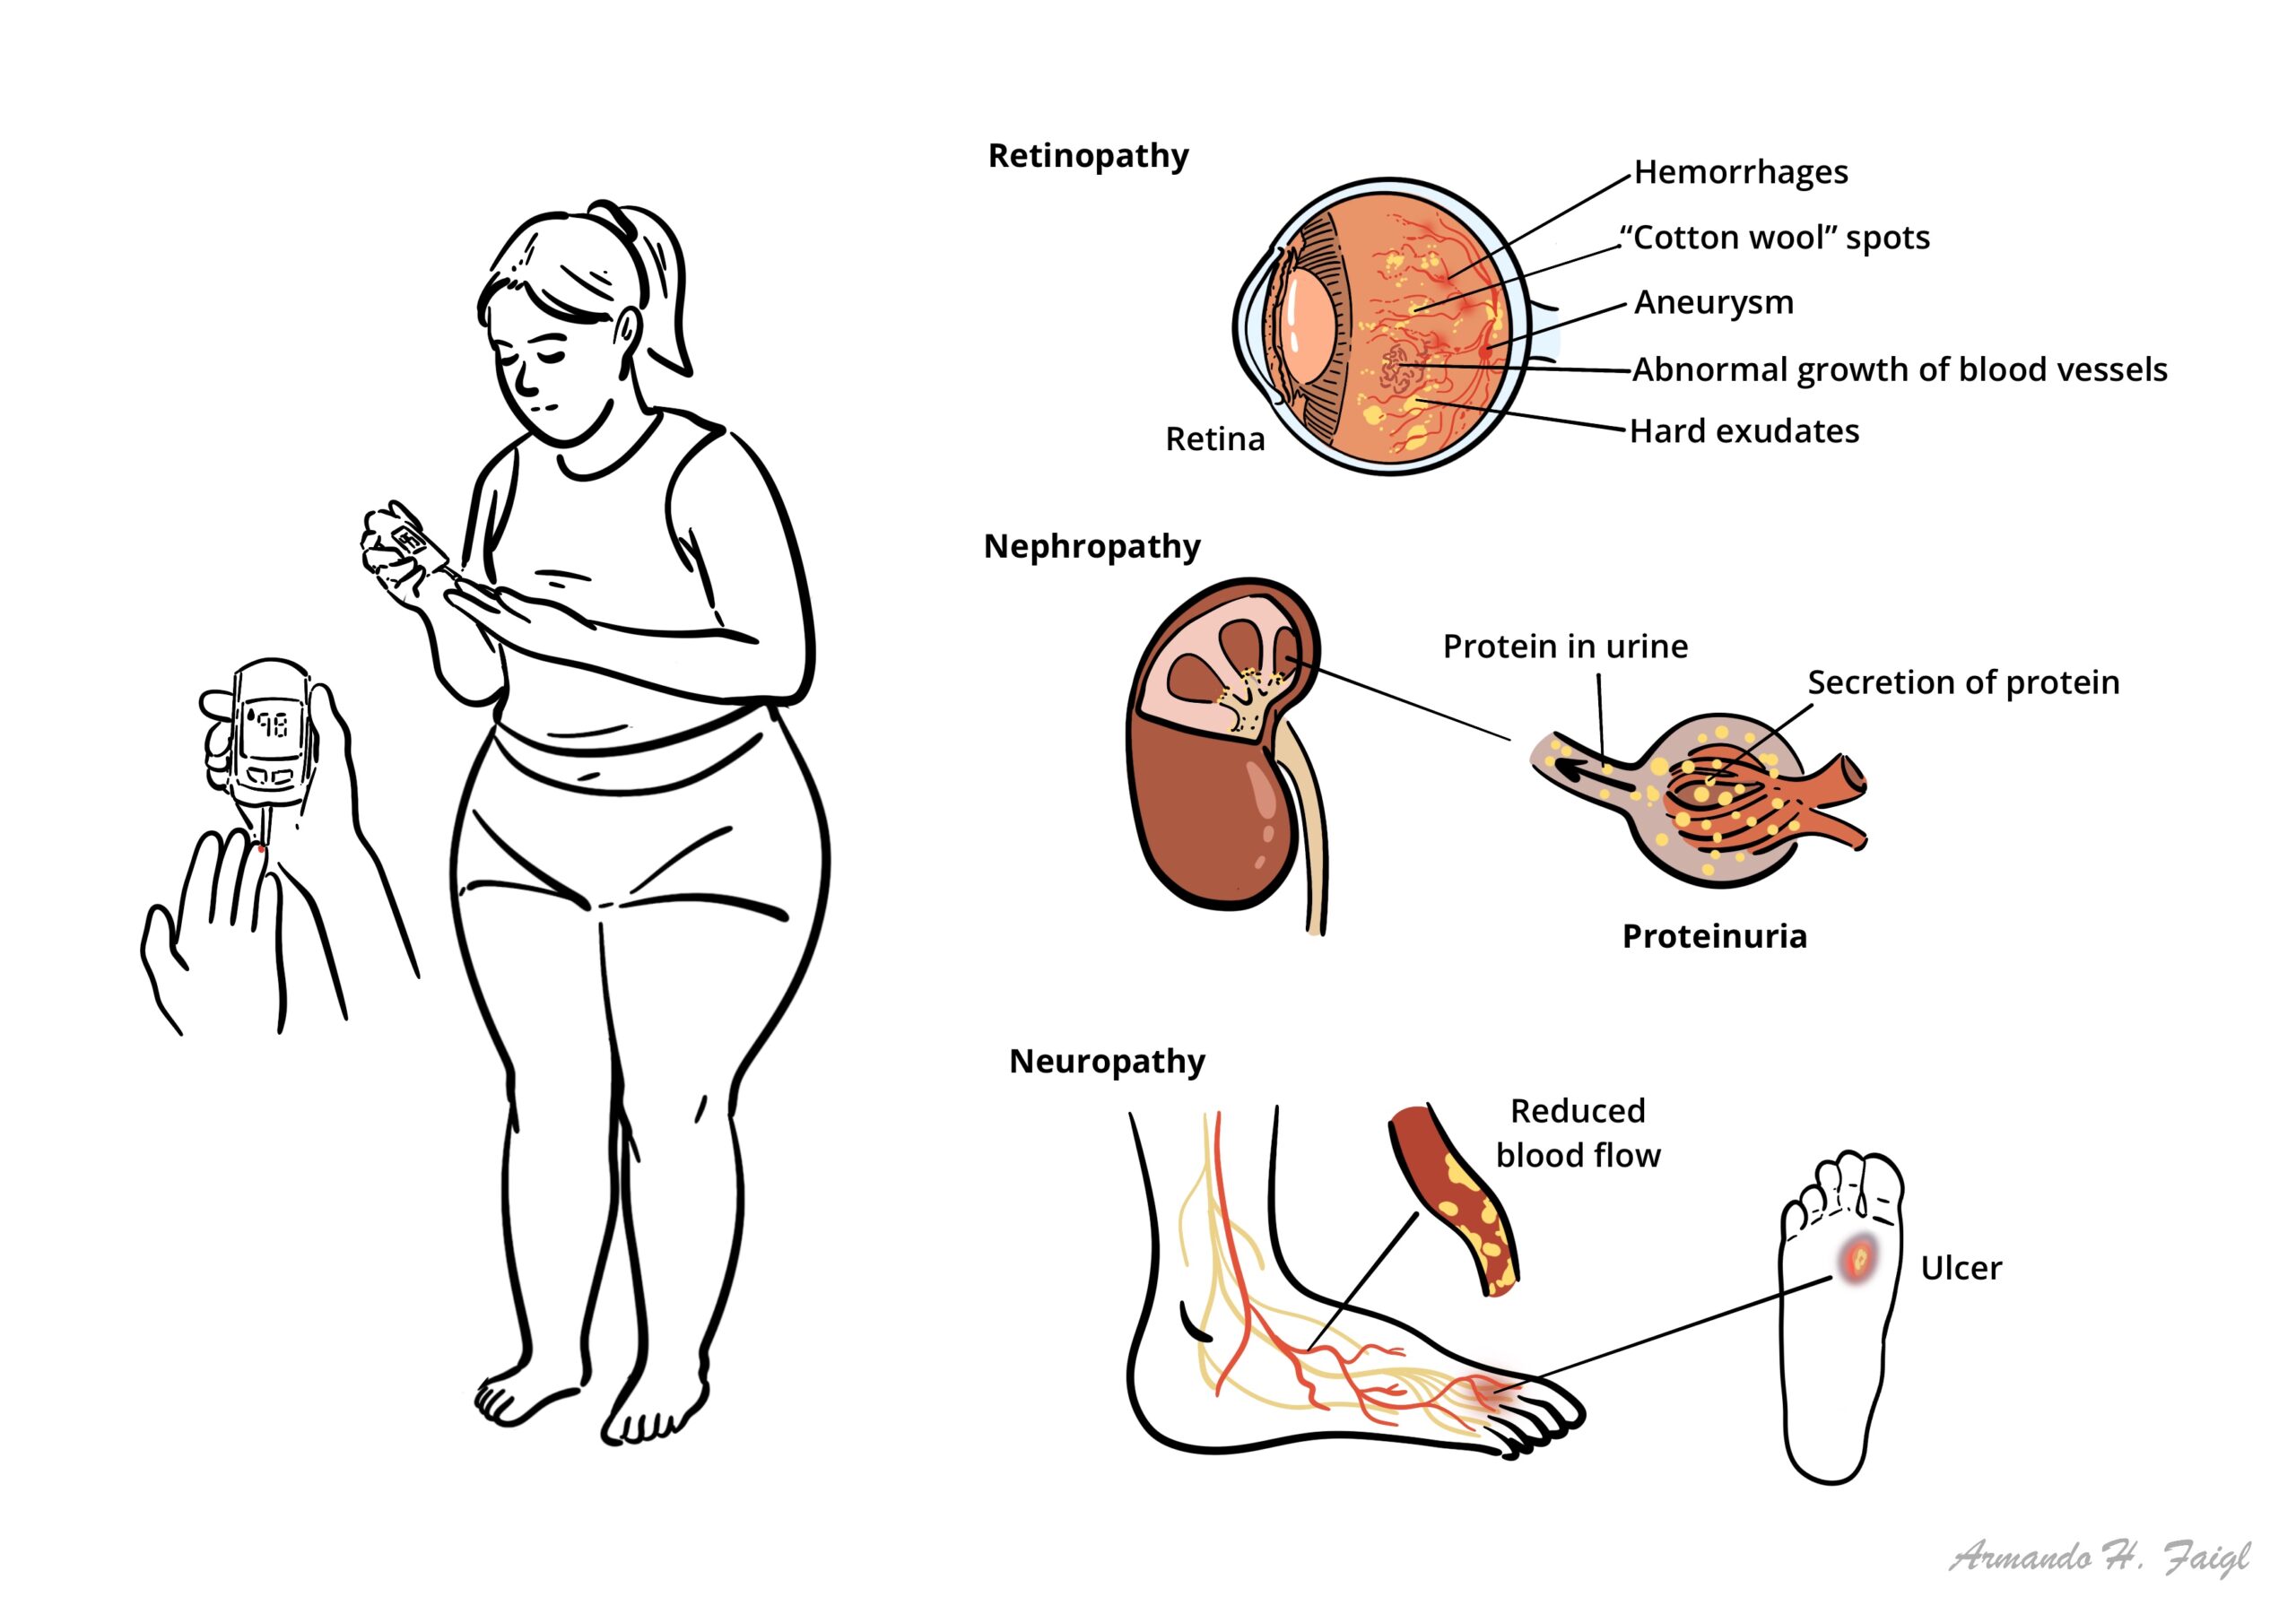
Retinal microvascular injury, kidney filtration-barrier damage and combined nerve/perfusion abnormalities contribute to chronic diabetes complications. Proteinuria reflects leakage through a damaged filtration barrier; neuropathy and peripheral arterial disease are distinct contributors to foot disease.
What to notice
Detailed image description
Classification
| Group | Major complications | Key distinction |
|---|---|---|
| Microvascular | Retinopathy; diabetes-related kidney disease; peripheral and autonomic neuropathy. | Early disease can be asymptomatic; screening is essential.2,3 |
| Macrovascular | Coronary artery disease, ischaemic stroke and peripheral arterial disease. | Treat systemic cardiovascular risk, not glucose alone.4 |
| Multifactorial foot disease | Neuropathic, ischaemic or neuro-ischaemic ulceration; infection; Charcot neuroarthropathy. | Loss of protective sensation, abnormal pressure and impaired perfusion often coexist.5 |
Heart failure is another important diabetes-associated cardiovascular outcome and is not always caused by atherosclerotic coronary disease.4
Aetiology & Risk Factors
Aetiology
Persistent hyperglycaemia causes cumulative metabolic and vascular injury. Hypertension, dyslipidaemia and smoking contribute additional vascular risk. Complications may already be present when type 2 diabetes is diagnosed because hyperglycaemia can precede recognition.3,4
Risk Factors
- General: longer diabetes duration, sustained above-target glycaemia, hypertension, dyslipidaemia and smoking.2,4
- Retinopathy progression: existing retinopathy, kidney disease and pregnancy increase risk.6
- Foot ulceration: loss of protective sensation, peripheral arterial disease, deformity, unsuitable footwear and previous ulcer or amputation. Visual impairment and kidney disease complicate self-care and healing.5
Pathophysiology
Hyperglycaemia promotes advanced glycation end products, oxidative stress and inflammatory signalling. Endothelial dysfunction and tissue injury contribute to microvascular damage and accelerate atherosclerotic disease.7
- Retina: capillary leakage produces oedema; capillary occlusion causes ischaemia, stimulating vascular endothelial growth factor (VEGF) and fragile new vessels.2
- Kidneys: haemodynamic and metabolic injury damage the filtration barrier, producing albuminuria and/or declining filtration. Histological changes include basement membrane thickening, mesangial expansion and glomerulosclerosis; nephrotic syndrome is a possible advanced presentation, not the definition of diabetic kidney disease.3,7
- Nerves and feet: nerve injury reduces protective sensation; motor dysfunction changes foot mechanics and autonomic dysfunction affects skin integrity. Repetitive trauma can then cause ulcers, while arterial disease impairs healing.5,8
Clinical Manifestations
Diabetic Retinopathy
- Often asymptomatic initially; later blurred vision, reduced acuity or new floaters.
- Non-proliferative retinopathy: microaneurysms, intraretinal haemorrhages, hard exudates, cotton wool spots, venous beading and intraretinal microvascular abnormalities.
- Proliferative retinopathy: retinal/disc neovascularisation, with risk of vitreous haemorrhage and tractional detachment. Macular oedema may occur at any retinopathy stage and threaten central vision.2,6
Diabetes-Related Kidney Disease
Usually silent early. Albuminuria and/or reduced estimated glomerular filtration rate (eGFR) precede symptoms; advanced disease may cause oedema and uraemic symptoms. Reduced eGFR can occur without albuminuria.3
Diabetic Neuropathy
- Distal symmetrical polyneuropathy: burning pain, tingling or numbness, usually beginning in the feet; reduced pinprick, vibration, ankle reflexes and protective sensation.
- Autonomic neuropathy: orthostatic symptoms, resting tachycardia, early satiety or vomiting from gastroparesis, bowel disturbance, bladder dysfunction and sexual dysfunction.
- Focal/proximal neuropathies: entrapment or cranial neuropathies, or painful asymmetric proximal leg weakness (diabetic lumbosacral radiculoplexus neuropathy). Acute, asymmetric or predominantly motor presentations require assessment for other causes.2,8
Macrovascular & Foot Disease
- Macrovascular: angina or myocardial infarction, transient ischaemic attack/stroke, or peripheral arterial disease with claudication, rest pain or tissue loss. Ischaemic symptoms may be muted by neuropathy.4,8
- Feet: callus, deformity, reduced sensation, absent pulses or a non-healing ulcer. Neuropathic plantar ulcers may be painless; ischaemic and neuropathic changes often coexist.5
- Urgent findings: sudden visual loss, an acutely cold/ischaemic limb, spreading foot infection, gangrene, or a hot swollen neuropathic foot suspicious for Charcot neuroarthropathy require urgent assessment.2,9
A painless foot lesion is not reassuring. Assess sensation, perfusion and infection separately; neuropathy may mask tissue injury.5,9
Diagnosis & Investigations
There is no single test for “diabetic complications”. Use regular organ-specific screening, then targeted investigations to establish severity and exclude alternative causes.
| Domain | Initial assessment / screening | Follow-up or targeted testing |
|---|---|---|
| Eyes | Type 2: dilated examination at diagnosis. Adults with type 1: initial examination within five years of onset.2 | Australian type 2 guidance allows 1–2-year screening when no/minimal retinopathy is present; use shorter intervals for higher risk or established/progressive disease. Optical coherence tomography assesses macular oedema.6 |
| Kidneys | At least annual urine albumin-to-creatinine ratio (uACR) and eGFR in all type 2 diabetes and type 1 diabetes of ≥5 years’ duration.3 | Repeat abnormal results; monitor established CKD more often according to stage and progression risk.3 |
| Neuropathy | Assess from type 2 diagnosis and five years after type 1 onset, then at least annually. Test pinprick/temperature, vibration and 10-g monofilament sensation.2 | Check B12, thyroid/renal function and medication/alcohol exposure when indicated; consider nerve conduction studies or specialist review for atypical findings.8 |
| Feet | At least annual assessment in low-risk feet: history, skin, deformity, protective sensation and pedal pulses.5 | More frequent review for higher risk. Doppler/toe pressures help assess perfusion; ankle pressures may be misleading in calcified arteries.5 |
| Cardiovascular | Review symptoms, smoking, blood pressure, lipids and established vascular disease; assess absolute risk where appropriate.4 | Investigate symptoms promptly. Further testing is guided by clinical findings.4 |
Kidney Diagnostic Criteria & Differentials
CKD means abnormalities of kidney structure or function persisting for at least three months: eGFR <60 mL/min/1.73 m² and/or evidence of damage such as uACR ≥3 mg/mmol. Classify by cause, GFR category and albuminuria category.10
Confirm elevated uACR with repeat samples: generally two of three abnormal measurements over 3–6 months. Infection, exercise, menstruation and marked hyperglycaemia can transiently increase it. Haematuria/active sediment, rapidly falling eGFR or abrupt heavy proteinuria warrant evaluation for non-diabetic kidney disease and possible nephrology referral.3
Active Foot Disease & Other Differentials
Diagnose foot infection clinically. If osteomyelitis is suspected, initial assessment combines probe-to-bone testing, plain radiographs and inflammatory markers; MRI is used when uncertainty persists. Obtain an appropriately collected tissue specimen rather than relying on a superficial swab. A red swollen foot also raises Charcot neuroarthropathy, gout, fracture or cellulitis as alternatives.2,9
Do not automatically attribute new visual symptoms, neuropathy or kidney impairment to diabetes. Consider other retinal disease, B12 deficiency, toxic/entrapment neuropathy, acute kidney injury and non-diabetic glomerular disease according to the presentation.3,6,8
For suspected gastroparesis, exclude medication effects and mechanical obstruction before confirming delayed gastric emptying, usually with a four-hour solid-meal gastric emptying study.2
Treatment
Prevention & Multifactorial Risk Reduction
- Individualise glycaemic targets, balancing benefit against hypoglycaemia and treatment burden; an HbA1c around ≤7% (53 mmol/mol) is a usual Australian type 2 target when appropriate.11
- Address blood pressure, lipids, smoking, activity, nutrition and weight. Prescribe lipid-lowering and antithrombotic treatment according to cardiovascular disease/risk and bleeding risk; diabetes alone is not an automatic aspirin indication.4
- Provide diabetes education, daily foot checks, suitable footwear and scheduled eye, kidney and foot surveillance.5,6
Organ-Specific Management
- Retinopathy: optimise systemic risk factors and refer moderate or worse non-proliferative retinopathy, proliferative disease or macular oedema. Ophthalmic treatment includes anti-VEGF for most centre-involving macular oedema with visual impairment, and panretinal laser or selected anti-VEGF treatment for proliferative disease.2,6
- Kidney disease: use an ACE inhibitor or ARB for diabetes with hypertension and albuminuria; do not combine them. In type 2 diabetes with CKD, an SGLT2 inhibitor with demonstrated benefit is recommended when eGFR is ≥20 mL/min/1.73 m². Additional options include a GLP-1 receptor agonist with proven benefit and finerenone in eligible albuminuric CKD with appropriate eGFR and potassium monitoring.10,12
- Neuropathic pain: options include duloxetine, pregabalin, gabapentin or a tricyclic antidepressant, selected for comorbidities and adverse effects. Adjust for kidney function. These relieve pain but do not restore protective sensation; opioids are generally avoided. Manage autonomic symptoms individually.2,8
- Foot ulcers: arrange multidisciplinary care, pressure off-loading, appropriate debridement/wound care and vascular assessment; revascularise when indicated. Suspected active Charcot disease requires prompt immobilisation/off-loading and specialist assessment. See also the clinical approach to lower limb ulcers.2,5
Foot Infection & Treatment Safety
Do not give antibiotics to an uninfected ulcer. For infection, select treatment using severity, likely organisms, previous cultures, renal function and local antimicrobial guidance; narrow therapy to culture results. Severe infection, deep abscess, necrosis or severe ischaemia requires urgent surgical/vascular assessment. Antibiotics alone do not correct pressure or poor perfusion.9
Monitor creatinine/eGFR and potassium with renin–angiotensin system blockers and finerenone. Provide SGLT2 inhibitor sick-day/perioperative instructions because prolonged fasting, surgery and critical illness increase ketosis risk.10
Complications & Prognosis
Complications
- Eyes: vitreous haemorrhage, retinal detachment and irreversible visual loss.6
- Kidneys: kidney failure, fluid/electrolyte complications and increased cardiovascular risk; detailed care is covered in Chronic Kidney Disease.10
- Nerves/feet: chronic pain, falls, recurrent ulcers, osteomyelitis, amputation and impaired independence.5,8,9
- Treatment: hypoglycaemia, medication accumulation in CKD, hypotension and hyperkalaemia require ongoing medication review.10,11
Prognosis
Outcomes depend on the organ involved, disease stage, cumulative glycaemic exposure, cardiovascular risk and access to preventive care. Early detection and sustained treatment reduce progression; established tissue loss or advanced nerve injury may be irreversible. Previous ulceration/amputation, reduced eGFR, higher albuminuria and established vascular disease identify people needing closer follow-up.1,5,10
References
- International Diabetes Federation. Complications [Internet]. 2023 [updated 2026 May 6; cited 2026 Oct 26]. Available from: https://idf.org/about-diabetes/complications/
- American Diabetes Association Professional Practice Committee for Diabetes. 12. Retinopathy, neuropathy, and foot care: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S261–S276. doi:10.2337/dc26-S012. https://doi.org/10.2337/dc26-S012
- American Diabetes Association Professional Practice Committee for Diabetes. 11. Chronic kidney disease and risk management: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S246–S260. doi:10.2337/dc26-S011. https://doi.org/10.2337/dc26-S011
- Royal Australian College of General Practitioners. Type 2 diabetes and cardiovascular risk. In: Management of type 2 diabetes: A handbook for general practice [Internet]. 2024 [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/complications/type-2-diabetes-and-cardiovascular-risk
- Royal Australian College of General Practitioners. Diabetes-related foot care. In: Management of type 2 diabetes: A handbook for general practice [Internet]. 2024 [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/complications/diabetes-related-foot-care
- Royal Australian College of General Practitioners. Diabetes-related eye disease. In: Management of type 2 diabetes: A handbook for general practice [Internet]. 2024 [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/complications/diabetes-related-eye-disease
- Khalid M, Petroianu G, Adem A. Advanced glycation end products and diabetes mellitus: mechanisms and perspectives. Biomolecules. 2022;12(4):542. doi:10.3390/biom12040542. https://doi.org/10.3390/biom12040542
- Royal Australian College of General Practitioners. Diabetes-related neuropathy. In: Management of type 2 diabetes: A handbook for general practice [Internet]. 2024 [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/complications/diabetes-related-neuropathy
- Infectious Diseases Society of America; International Working Group on the Diabetic Foot. IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections [Internet]. 2023 [cited 2026 Oct 26]. Available from: https://www.idsociety.org/practice-guideline/diabetic-foot-infections/
- Kidney Disease: Improving Global Outcomes CKD Work Group. KDIGO 2024 clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney Int. 2024;105(4S):S117–S314. https://kdigo.org/wp-content/uploads/2024/03/KDIGO-2024-CKD-Guideline.pdf
- Royal Australian College of General Practitioners. Type 2 diabetes: Goals for optimum management. In: Management of type 2 diabetes: A handbook for general practice [Internet]. [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/type-2-diabetes-goals-for-optimum-management
- Royal Australian College of General Practitioners. Diabetes-related chronic kidney disease. In: Management of type 2 diabetes: A handbook for general practice [Internet]. [cited 2026 Oct 26]. Available from: https://www.racgp.org.au/clinical-resources/clinical-guidelines/key-racgp-guidelines/view-all-racgp-guidelines/management-of-type-2-diabetes/complications/diabetes-related-chronic-kidney-disease
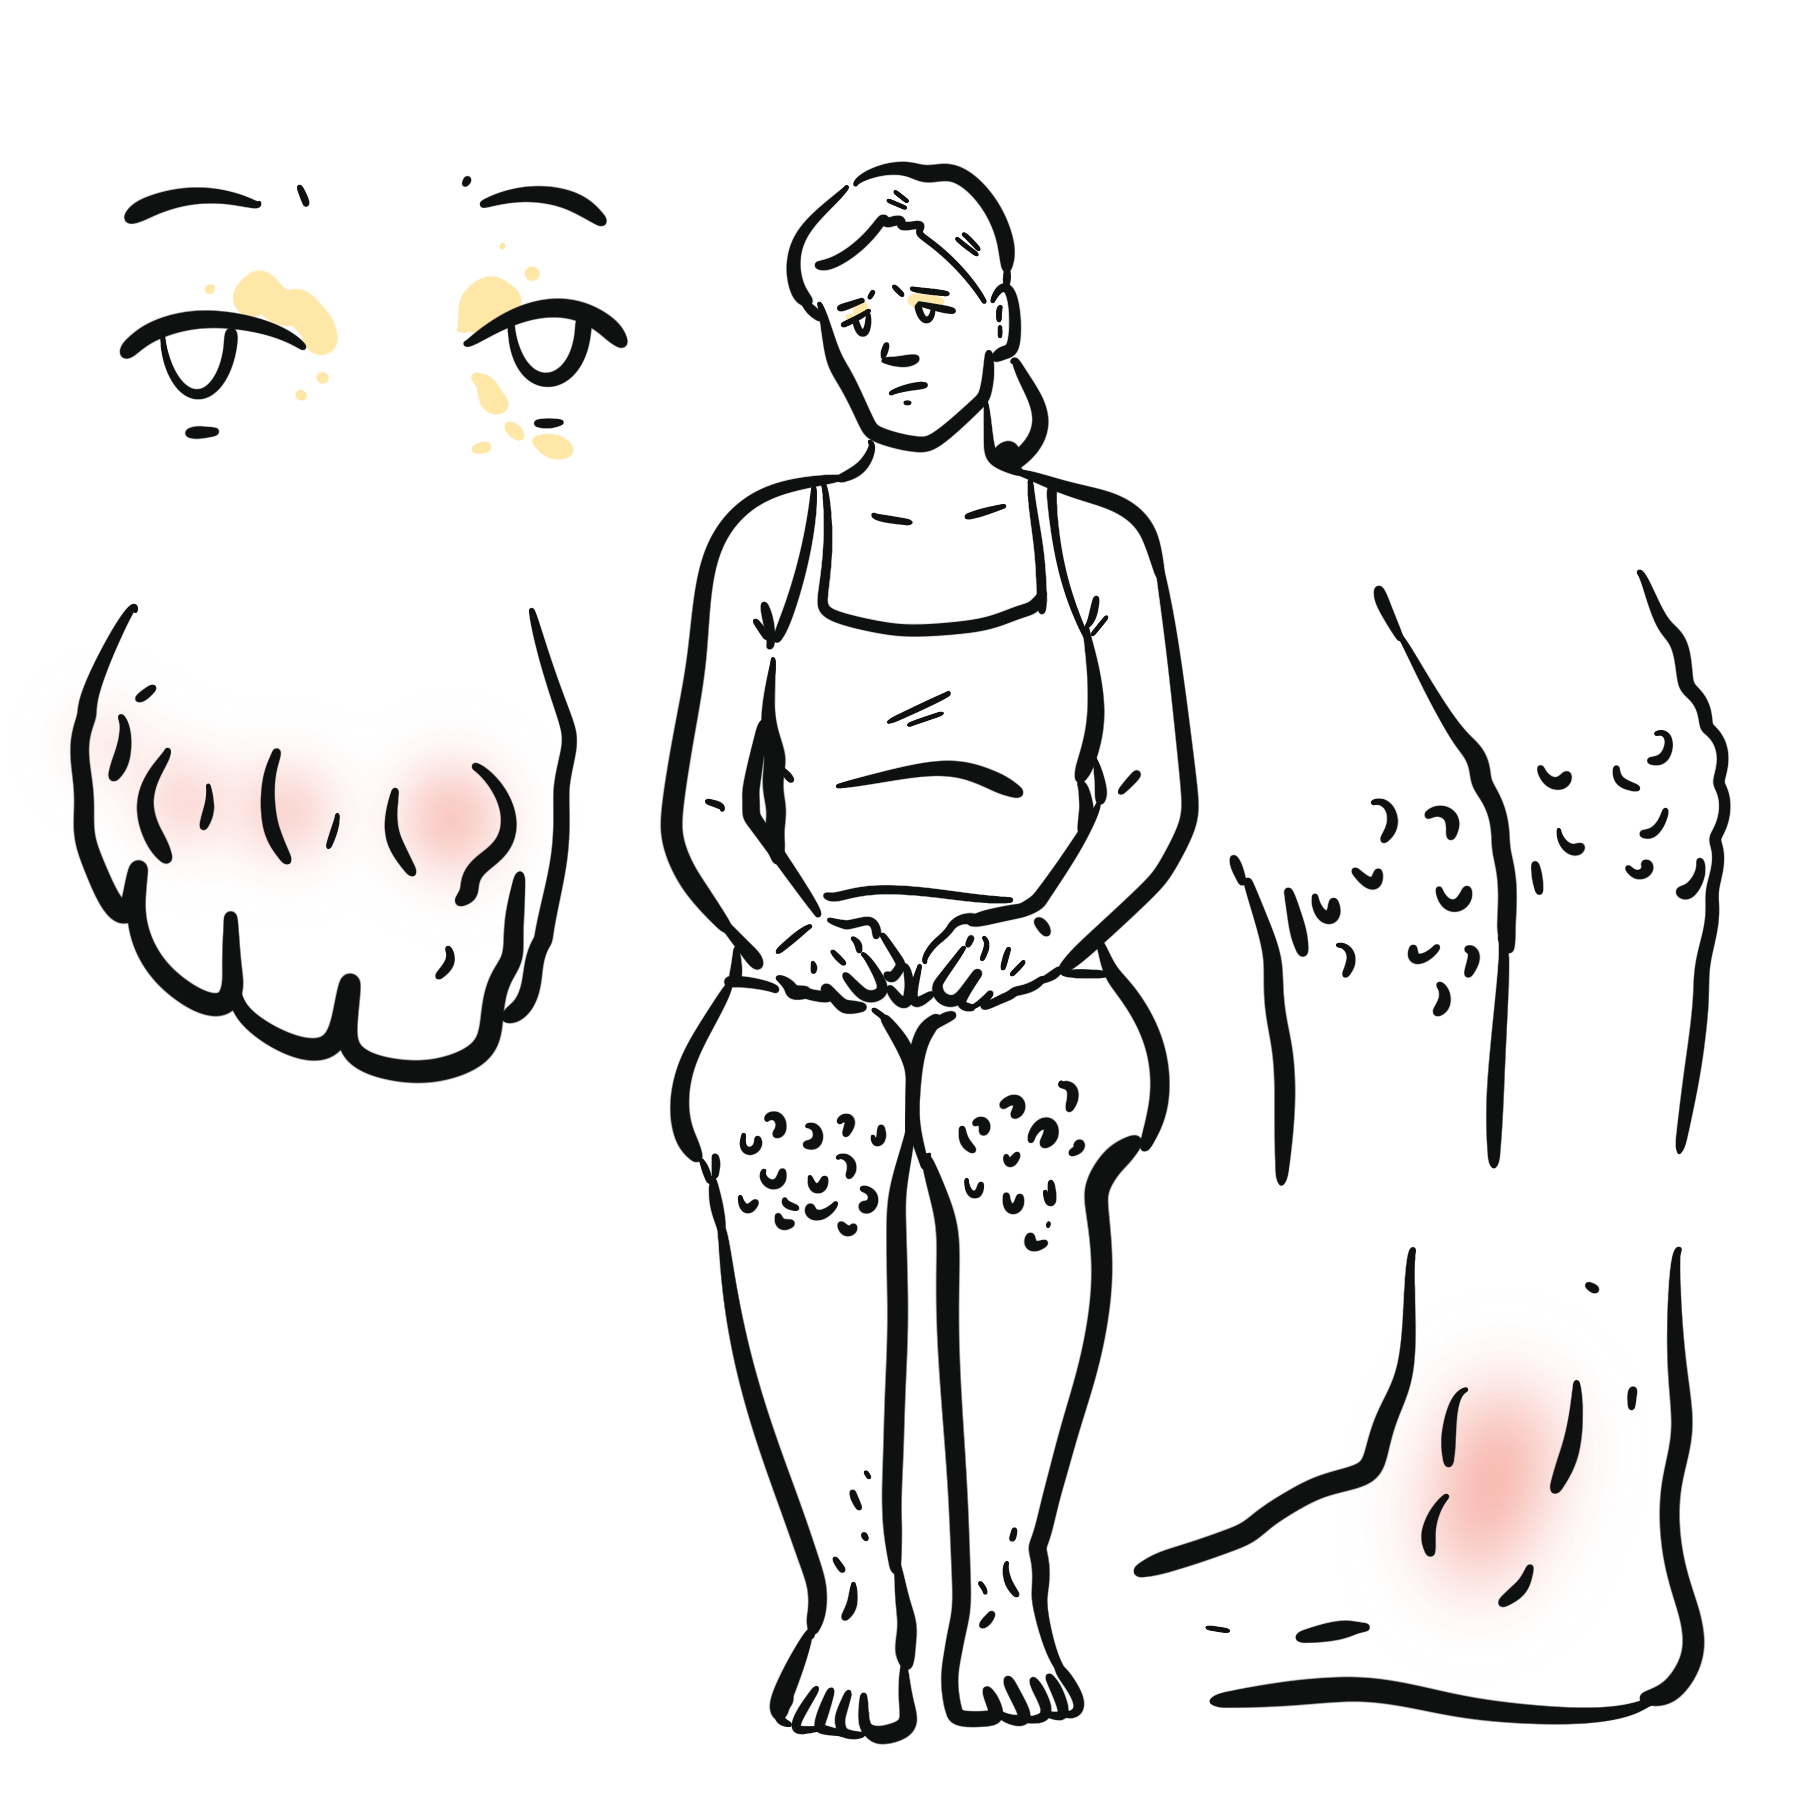





Members only discussions coming soon…