

Nephrolithiasis and Urolithiasis (Kidney Stones)
Overview
Nephrolithiasis refers to stones within the kidney, whereas urolithiasis includes stones anywhere in the urinary tract. Stones form when urine becomes supersaturated with poorly soluble substances that crystallise, aggregate and are retained within the renal collecting system.
Most urinary stones contain calcium, usually calcium oxalate with or without calcium phosphate. Other important types include uric acid, struvite or infection stones, cystine stones and drug-related stones. Identifying the stone composition can help determine the underlying cause and guide recurrence prevention.1
Renal stones may remain asymptomatic within the kidney. Symptoms commonly begin when a stone migrates into the ureter and obstructs urinary flow, producing acute renal colic. An infected obstructed kidney is a urological emergency requiring urgent drainage and antimicrobial treatment.
Definition
- Nephrolithiasis
- Formation or presence of calculi within the kidney.
- Urolithiasis
- Formation or presence of calculi anywhere in the urinary tract, including the kidneys, ureters and bladder.
- Ureterolithiasis
- A stone located within the ureter.
- Renal colic
- Severe, typically fluctuating flank pain caused by acute ureteric obstruction and increased pressure within the urinary tract.
- Hydronephrosis
- Dilatation of the renal collecting system due to impaired urinary drainage.
- Staghorn calculus
- A branching stone occupying part or most of the renal pelvis and calyces.
- Stone burden
- The total size and number of urinary calculi present.
Anatomy & Physiology
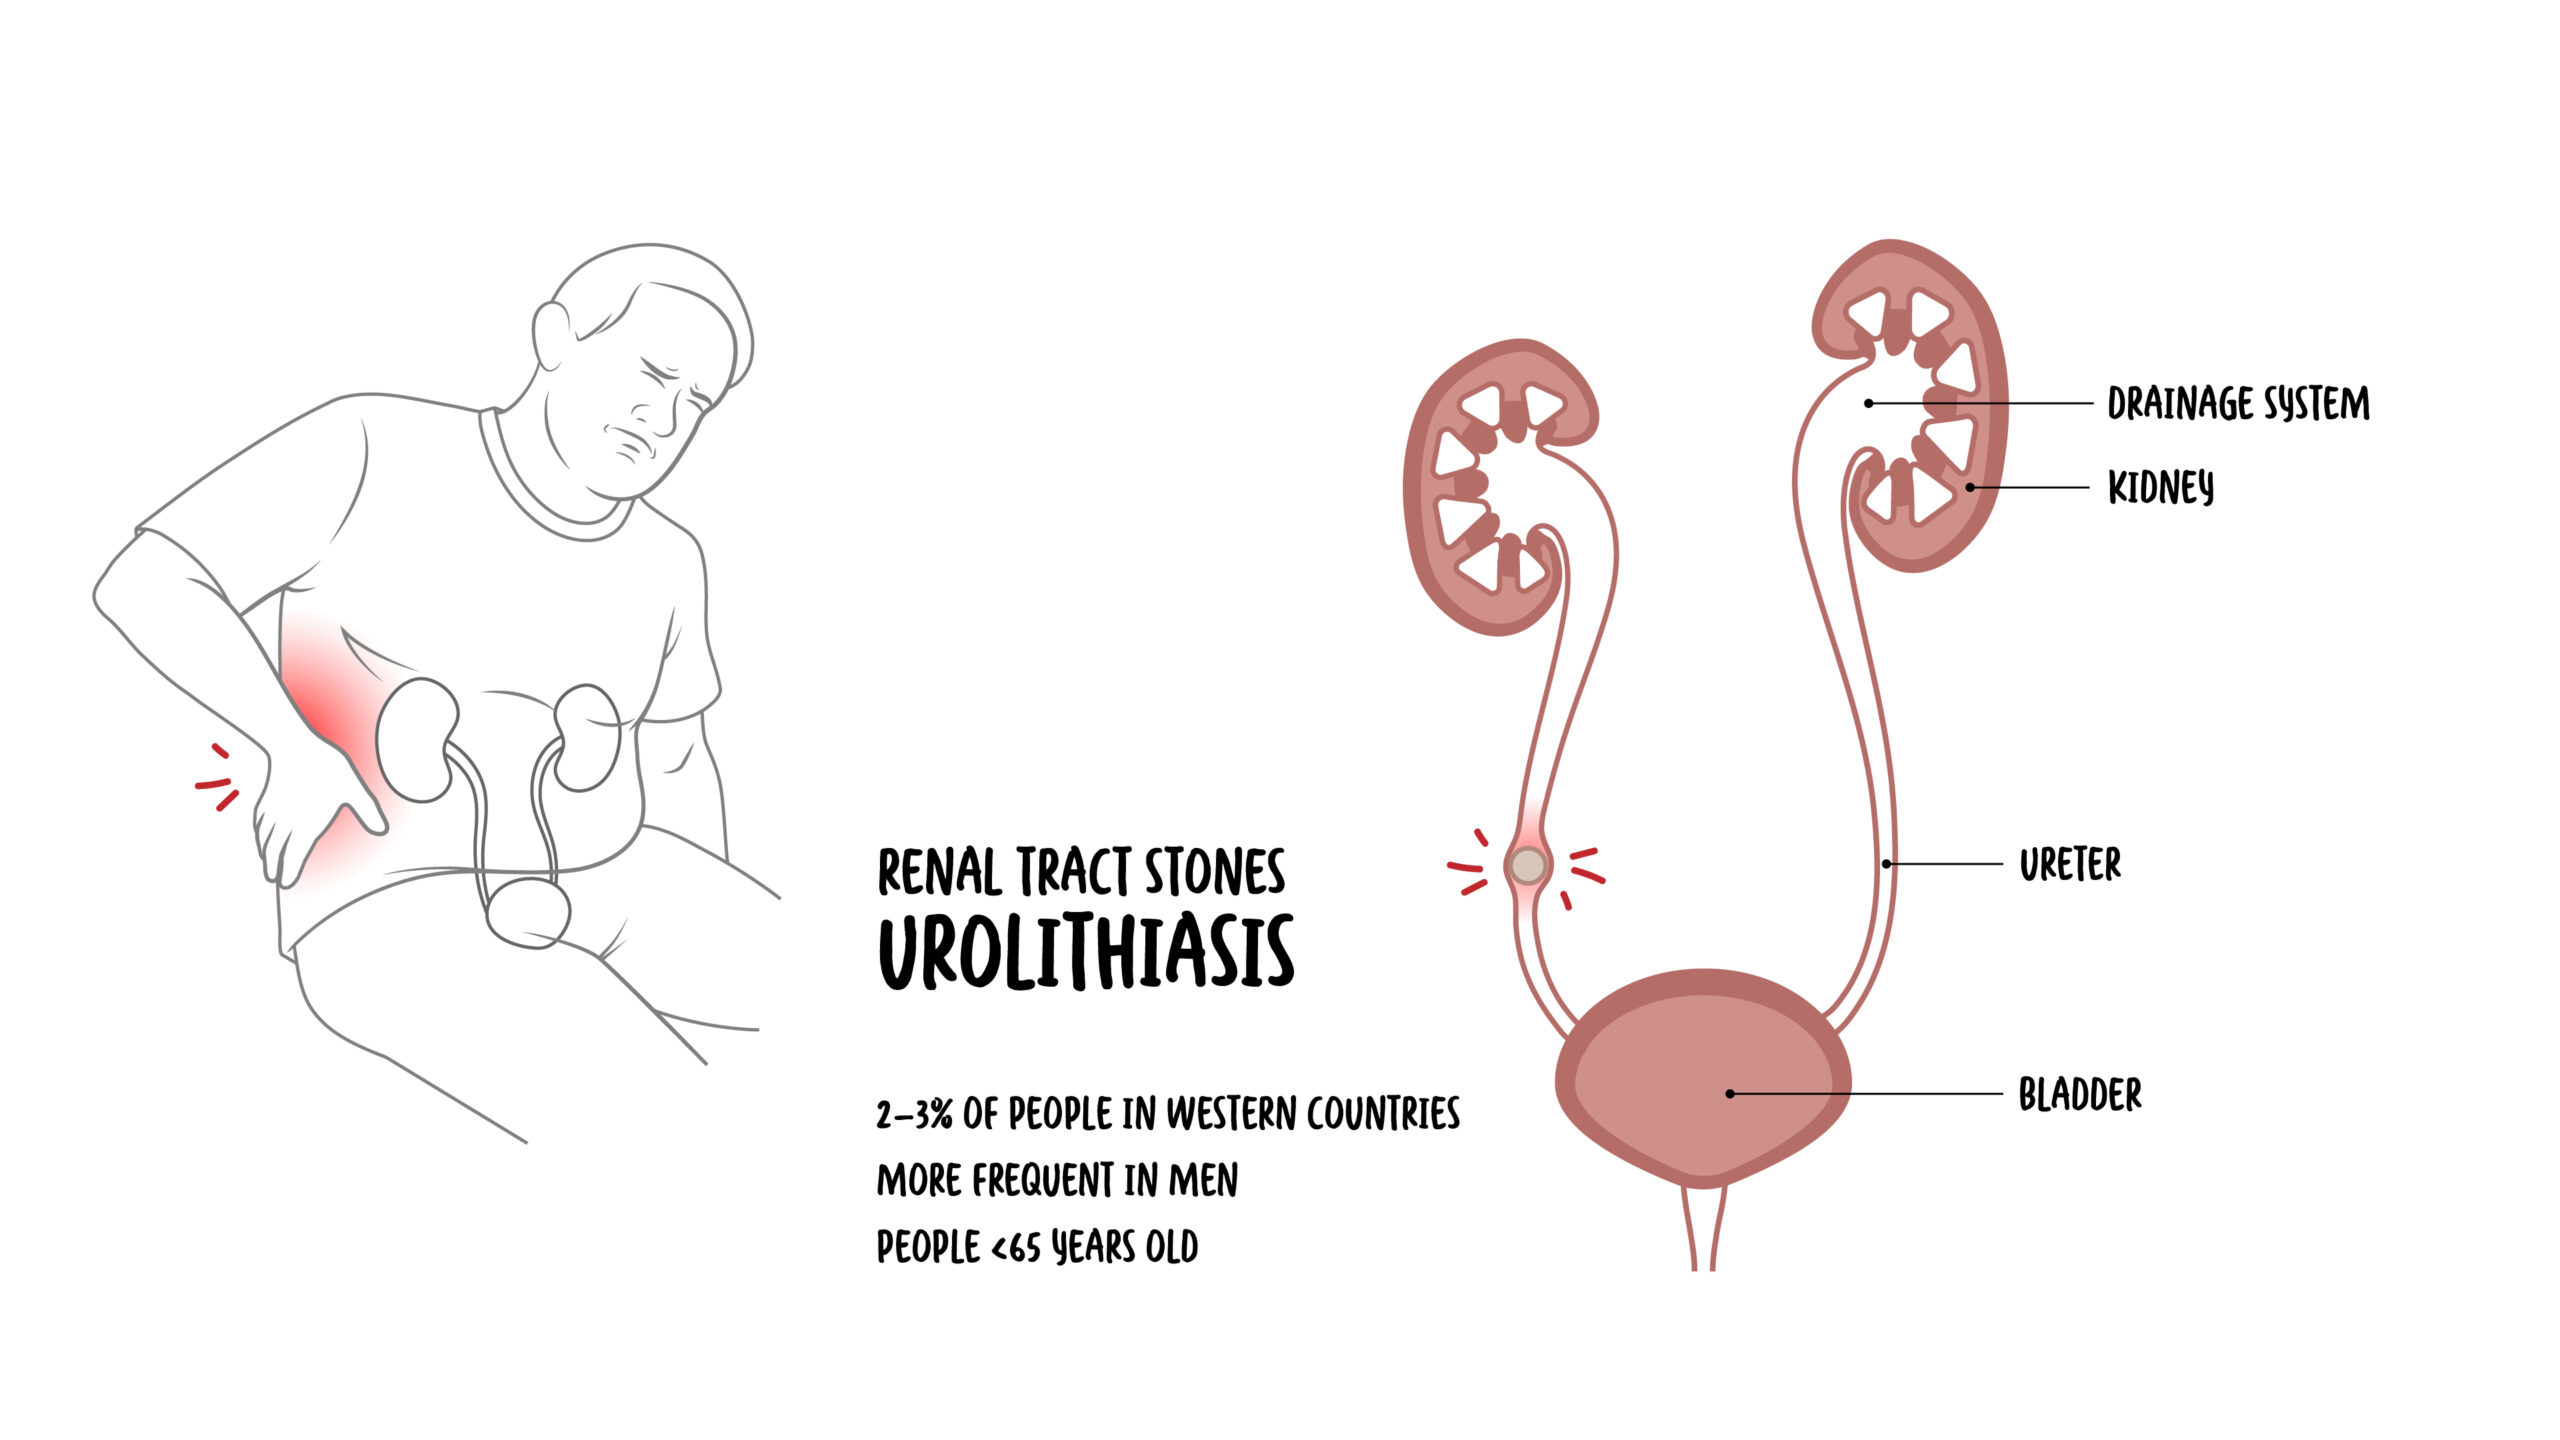
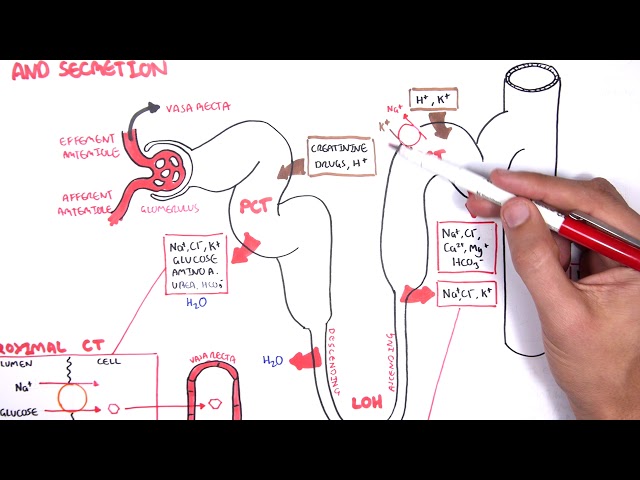
The kidneys filter the blood and produce urine, which passes through the renal calyces and renal pelvis into the ureters. The ureters transport urine to the bladder through coordinated smooth-muscle contractions known as peristalsis.
Urine normally contains dissolved calcium, oxalate, phosphate, urate and other solutes. Stone formation is prevented by adequate urine volume and urinary inhibitors such as citrate, magnesium and certain proteins.
- The renal papillae drain urine into the minor calyces.
- The minor calyces join to form major calyces, which drain into the renal pelvis.
- The ureteropelvic junction connects the renal pelvis to the ureter.
- The ureter crosses the iliac vessels and then enters the bladder through the ureterovesical junction.
- The ureteropelvic junction, pelvic brim and ureterovesical junction are relatively narrow sites where stones may become impacted.
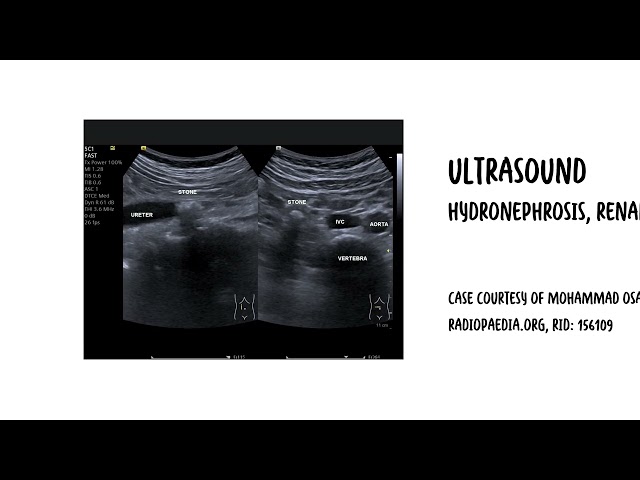
- Ureteric obstruction increases pressure within the collecting system and may cause hydronephrosis and impaired renal function.
For ureteric stones, the classic sites of obstruction/impaction are the 3 normal ureteric narrowings:
- – Ureteropelvic junction— where the renal pelvis becomes the ureter.
- – Pelvic brim — where the ureter crosses the iliac vessels.
- – Ureterovesical junction — where the ureter enters the bladder; the intramural ureter is the narrowest segment and a very common site for stones to lodge.
Aetiology & Risk Factors
Aetiology
Stone formation occurs when urine becomes supersaturated with stone-forming substances. Crystals then nucleate, enlarge, aggregate and remain within the urinary tract rather than being washed out with urine
This process may result from:
- Low urine volume.
- Increased urinary calcium, oxalate, urate or cystine.
- Reduced urinary citrate or other crystallisation inhibitors.
- Persistently acidic or alkaline urine.
- Urinary infection.
- Anatomical or functional urinary stasis.
- Foreign material within the urinary tract.
- Genetic or metabolic disease.
Risk Factors
- Previous nephrolithiasis or recurrent stones.
- Family history of kidney stones.
- Low fluid intake or recurrent dehydration.
- Hot climate, heavy exercise or occupational heat exposure.
- High dietary sodium intake.
- Excessive animal protein intake.
- High intake of free sugars or sugar-sweetened drinks.
- Obesity, insulin resistance, diabetes or metabolic syndrome.
- Gout or hyperuricaemia.
- Primary hyperparathyroidism.
- Distal renal tubular acidosis.
- Inflammatory bowel disease, chronic diarrhoea or short-bowel syndrome.
- Bariatric surgery, particularly procedures causing fat malabsorption.
- Recurrent urinary tract infection.
- Urinary tract obstruction, urinary diversion or neurogenic bladder.
- Genetic disorders such as cystinuria and primary hyperoxaluria.
- Medications including topiramate, acetazolamide, indinavir, atazanavir, triamterene and sulfadiazine.
- Excessive vitamin C supplementation, which may increase urinary oxalate.
Pathophysiology
Stone formation begins when the concentration of one or more urinary solutes exceeds their ability to remain dissolved. This creates supersaturation and allows crystals to form.
- Supersaturation: Low urine volume or increased solute excretion raises the urinary concentration of substances such as calcium, oxalate, phosphate, urate or cystine.
- Nucleation: Dissolved substances begin to form microscopic crystals. Crystals may develop freely within the urine or on structures such as Randall plaques at the renal papillae.
- Crystal growth and aggregation: Crystals enlarge and combine with other crystals. Low urinary citrate reduces inhibition of calcium crystal formation.
- Retention: Crystals remain attached to renal tissue or become trapped within the collecting system rather than being passed in the urine.
- Migration and obstruction: A stone may enter the ureter and partially or completely obstruct urinary flow. Ureteric distension, smooth-muscle spasm, oedema and increased collecting-system pressure produce renal colic.
Persistent obstruction may reduce renal perfusion and glomerular filtration. When infection occurs above an obstruction, bacteria and infected urine become trapped within a pressurised collecting system, creating a risk of pyonephrosis, bacteraemia and urosepsis.1
Why does renal colic come in waves? The ureter attempts to propel an obstructing stone towards the bladder through repeated peristaltic contractions. Increasing ureteric pressure and smooth-muscle spasm produce severe fluctuating pain rather than constant localised pain.
Classification
Calcium Oxalate Stones
Calcium oxalate is the most common stone composition. Important contributors include low urine volume, hypercalciuria, hyperoxaluria, hypocitraturia and high sodium intake. These stones are usually radiopaque on plain X-ray.
Calcium Phosphate Stones
Calcium phosphate stones are associated with relatively alkaline urine, hypercalciuria, distal renal tubular acidosis and sometimes primary hyperparathyroidism. Calcium phosphate may occur alone or together with calcium oxalate.
Uric Acid Stones
Uric acid stones form predominantly in persistently acidic urine. They are associated with gout, insulin resistance, obesity, diabetes, high purine intake, chronic diarrhoea and high cell turnover. They are radiolucent on plain X-ray but visible on non-contrast CT.
Struvite Stones
Struvite stones contain magnesium ammonium phosphate and form in association with urease-producing urinary infections. Organisms may include Proteus, Klebsiella and some Staphylococcus species.
Urease breaks down urea into ammonia, producing alkaline urine and promoting struvite crystallisation. These stones may grow rapidly and form staghorn calculi.
Cystine Stones
Cystine stones occur in cystinuria, an inherited disorder affecting renal tubular amino-acid transport. Stones frequently begin at a young age and may recur throughout life. Hexagonal cystine crystals in the urine are characteristic.
Drug-related Stones
Some medications or their metabolites crystallise directly within the urine. Examples include indinavir, atazanavir, triamterene and sulfadiazine.
Other medications increase stone risk by changing urine composition or pH. Examples include topiramate, acetazolamide and loop diuretics.
Calcium oxalate is the most common renal stone. Struvite stones are associated with urease-producing organisms and may form staghorn calculi.
Cystine stones are associated with cystinuria and form hexagonal crystals.
Clinical Manifestations
- Sudden severe unilateral flank or loin pain.
- Colicky pain occurring in waves.
- Radiation towards the lower abdomen, groin, testis or labium.
- Restlessness and inability to find a comfortable position.
- Nausea and vomiting.
- Microscopic or visible haematuria.
- Costovertebral-angle tenderness.
- Urinary frequency, urgency or dysuria with a distal ureteric stone.
- Suprapubic discomfort as a stone approaches the bladder.
- Asymptomatic stones discovered incidentally on imaging.
- Recurrent urinary tract infection or unexplained haematuria.
The location of pain does not always identify the exact stone position. Symptoms may also change as the stone moves through the ureter.
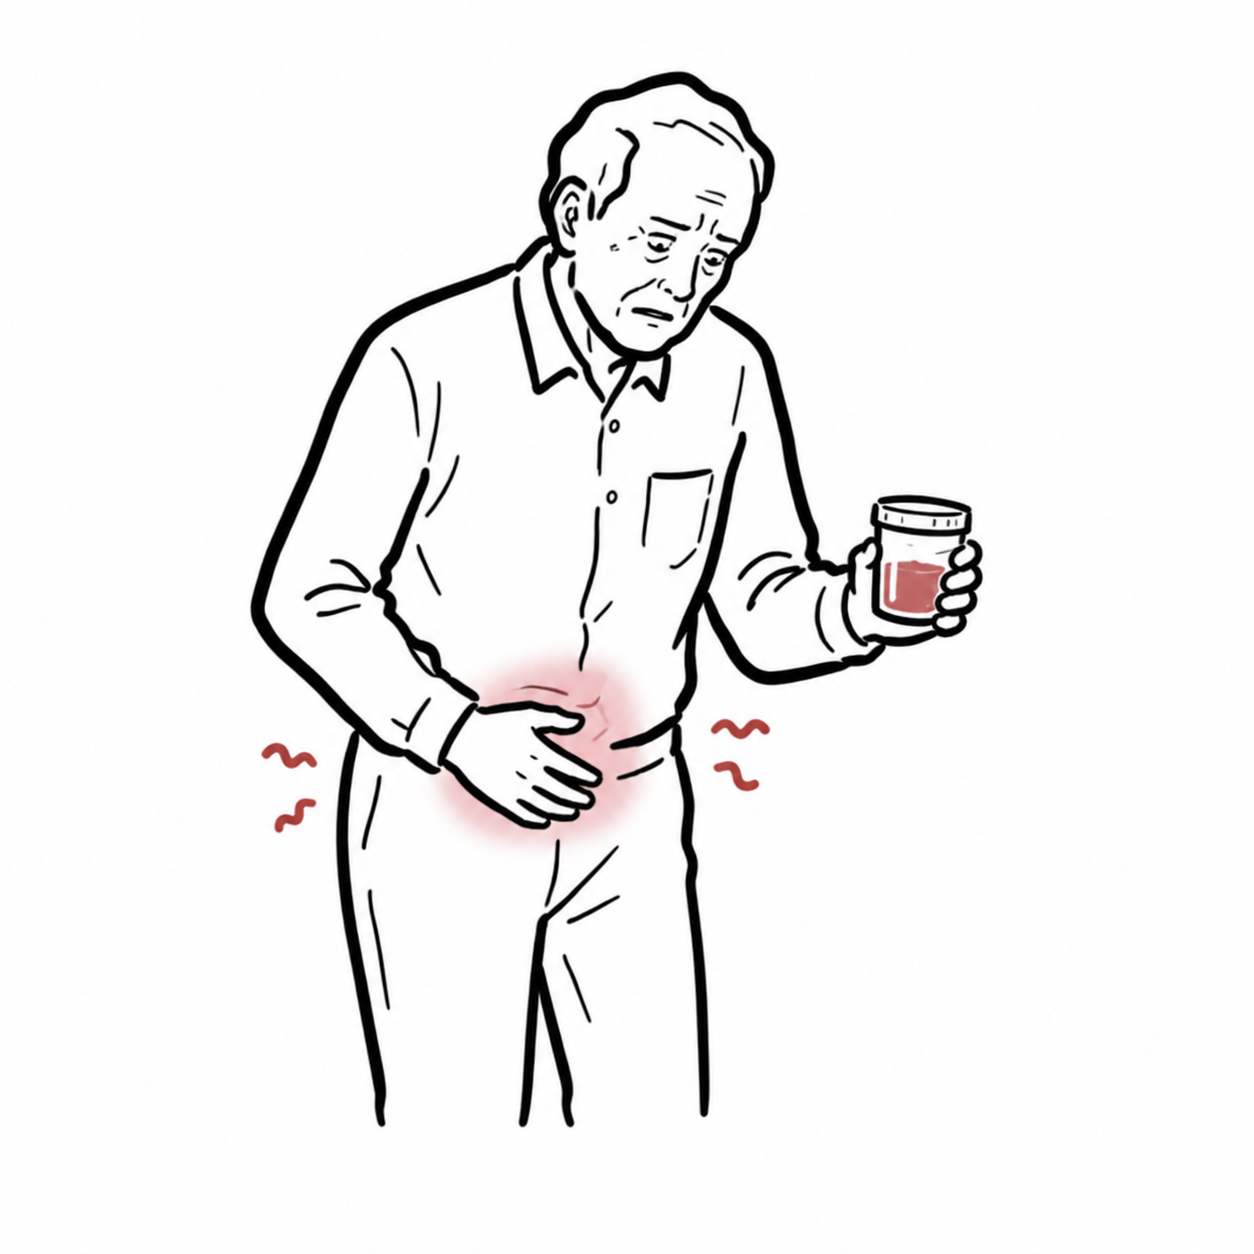
Renal stones typically cause severe colicky loin-to-groin pain with haematuria.
Features Suggesting Complicated Stone Disease
- Fever or rigors.
- Pyuria or positive urine culture.
- Hypotension, tachycardia or systemic toxicity.
- Anuria or markedly reduced urine output.
- Acute kidney injury or rising creatinine.
- Bilateral ureteric obstruction.
- Obstruction in a solitary or transplanted kidney.
- Persistent pain despite adequate analgesia.
- Persistent vomiting or inability to maintain oral intake.
- Pregnancy.
- Significant immunosuppression or major comorbidity.
Diagnosis & Investigations
The goals are to confirm a urinary stone, determine its size and location, assess the degree of obstruction, identify infection or impaired renal function, and exclude alternative causes of abdominal or flank pain.
Initial Investigations
- Urinalysis: Assess for blood, leukocytes, nitrites, urine pH and crystals. The absence of haematuria does not exclude a urinary stone.
- Urine microscopy and culture: Required when infection is suspected and before intervention where clinically indicated.
- Full blood count: May demonstrate leukocytosis or anaemia.
- Renal function and electrolytes: Assess for acute kidney injury and guide the safe use of medications and contrast where relevant.
- C-reactive protein: May support the assessment of infection or systemic inflammation.
- Serum calcium: Screens for hypercalcaemia and possible primary hyperparathyroidism.
- Serum urate: May support assessment for hyperuricaemia or uric acid stone disease.
- Pregnancy testing: Perform when relevant before ionising radiation.
- Stone analysis: Retrieve and analyse passed or surgically removed stones using infrared spectroscopy or X-ray diffraction.
Imaging
- Non-contrast low-dose CT kidney ureter bladder: The most accurate investigation for most adults with suspected renal colic. It identifies stone size, location and density, the degree of obstruction and alternative diagnoses.
- Ultrasound: Detects hydronephrosis and many renal stones without radiation. It is the preferred initial modality in pregnancy and children, although ureteric stones may be missed.
- Plain kidney ureter bladder X-ray: May be used to follow known radiopaque stones but has limited sensitivity and does not reliably exclude obstruction.
- MRI: May be considered during pregnancy when ultrasound is inconclusive. It can demonstrate obstruction but is less effective for directly visualising stones.
Non-contrast CT KUB is the investigation of choice in most adults.
Uric acid stones form in acidic urine and are radiolucent on plain X-ray.
Metabolic Evaluation
All stone formers should undergo a basic evaluation consisting of a medical and dietary history, urinalysis, serum biochemistry and stone analysis where available.
A specific metabolic evaluation should be considered for:
- Recurrent stone formation.
- Bilateral or multiple stones.
- Early-onset disease.
- A solitary kidney.
- Nephrocalcinosis.
- Cystine, uric acid or infection stones.
- Suspected primary hyperoxaluria or another genetic disorder.
- Strong family history.
- Gastrointestinal malabsorption.
- Recurrent stone formation despite preventive measures.
A detailed evaluation commonly includes two consecutive 24-hour urine collections measuring:
- Urine volume.
- Urine pH.
- Calcium.
- Oxalate.
- Citrate.
- Urate.
- Sodium.
- Creatinine.
- Cystine where clinically indicated.
Haematuria is not essential. Microscopic or visible haematuria supports the diagnosis, but its absence does not exclude nephrolithiasis. Imaging is required when the diagnosis is uncertain or a complication must be excluded.
Treatment
Management depends on stone size and location, symptom control, renal function, infection, anatomical factors and the probability of spontaneous passage.
Acute Renal Colic
- Analgesia: A non-steroidal anti-inflammatory drug is generally used as first-line treatment when not contraindicated. Paracetamol may be added. An opioid may be required when pain remains severe or NSAIDs are unsuitable.
- Antiemetic treatment: Treat nausea and vomiting as required.
- Hydration: Correct dehydration and maintain normal hydration. Forced high-volume intravenous fluids do not accelerate stone passage and may worsen pain when obstruction persists.
- Observation: Conservative management may be appropriate when symptoms are controlled, infection is absent, renal function is preserved and the stone is likely to pass spontaneously.
- Follow-up: Provide clear return precautions and arrange follow-up to confirm stone passage or resolution of obstruction.
Medical Expulsive Therapy
An alpha-blocker such as tamsulosin may be considered for selected patients with distal ureteric stones, particularly stones larger than 5 mm, when active stone removal is not immediately required.1
The expected benefit, adverse effects and off-label nature of treatment should be discussed where applicable. Medical expulsive therapy must not delay intervention when infection, renal impairment, uncontrolled pain or another complication is present.
Infected obstruction is a urological emergency. An obstructed kidney with infection, sepsis or anuria requires urgent decompression with a ureteric stent or percutaneous nephrostomy, urine and blood cultures, prompt empiric intravenous antibiotics and supportive sepsis management where required. Definitive stone treatment should be delayed until sepsis has resolved and the infection has been treated.
Antibiotics alone are insufficient because the infected collecting system remains obstructed.
Indications for Active Stone Removal
- Stone unlikely to pass spontaneously because of its size or position.
- Persistent ureteric obstruction.
- Worsening hydronephrosis.
- Deteriorating renal function.
- Ongoing pain despite adequate analgesia.
- Persistent vomiting.
- Recurrent urinary infection.
- Infection stones.
- Stone growth.
- Recurrent haematuria or other stone-related symptoms.
- Patient preference or occupational considerations.
- Limited access to urgent medical care.
- Planned pregnancy where relevant.
Extracorporeal Shock-wave Lithotripsy
External shock waves fragment selected renal or ureteric stones into smaller pieces that can pass through the urinary tract.
Treatment success depends on stone size, stone location, stone density and composition, skin-to-stone distance, and renal and urinary anatomy. Repeat treatment or an alternative procedure may be required.
Ureteroscopy and Laser Lithotripsy
A ureteroscope is passed through the urethra and bladder into the ureter or kidney. The stone can be removed intact or fragmented with a laser.
Ureteroscopy usually provides a higher immediate stone-free rate than shock-wave lithotripsy but is more invasive. A temporary ureteric stent may be required.
Percutaneous Nephrolithotomy
Percutaneous nephrolithotomy accesses the kidney through a small tract created through the back. It is generally preferred for renal stones larger than 20 mm and for many complex or staghorn stones.
It provides a high stone-clearance rate but carries risks including bleeding, infection and injury to surrounding structures.
Dissolution Therapy
Uric acid stones may sometimes be dissolved by alkalinising the urine, usually with potassium citrate or another alkalinising agent. Urine pH must be monitored to ensure adequate treatment without excessive alkalinisation.1
Most calcium-containing stones cannot be dissolved medically.
Prevention of Recurrence
General Measures
- Increase fluid intake throughout the day to achieve a urine output greater than 2.5 L per day.
- Increase fluid intake further during hot weather, exercise, fever, vomiting or diarrhoea.
- Maintain normal dietary calcium intake, generally around 1000 mg per day in adults younger than 70 years.
- Consume calcium-containing foods with meals rather than severely restricting calcium.
- Reduce dietary sodium.
- Avoid excessive animal protein.
- Maintain a diet rich in vegetables and fruit.
- Avoid excessive free sugars and sugar-sweetened drinks.
- Maintain a healthy body weight and regular physical activity.
- Avoid unnecessary high-dose vitamin C supplementation.
- Do not routinely prescribe a highly restrictive low-oxalate diet. Address clearly excessive oxalate intake when hyperoxaluria is present.
Targeted Prevention
- Hypercalciuria: Reduce sodium intake and consider a thiazide or thiazide-like diuretic after metabolic assessment, with monitoring for adverse effects.
- Hypocitraturia: Increase fruit and vegetable intake and consider potassium citrate.
- Uric acid stones: Alkalinise the urine and address hyperuricaemia, hyperuricosuria, obesity and excessive purine intake.
- Cystine stones: Use very high fluid intake, sodium restriction and urine alkalinisation. Cystine-binding medication may be required.
- Struvite stones: Aim for complete stone clearance and treatment of the associated infection.
- Enteric hyperoxaluria: Maintain high fluid intake, consume normal dietary calcium with meals, reduce excessive dietary fat and oxalate where appropriate, and treat the underlying gastrointestinal disorder.
Water is the foundation of prevention. The most broadly effective preventive measure is sufficient fluid intake to produce more than 2.5 L of urine each day. Fluid intake must be spread throughout the day and increased during heat exposure, exercise or gastrointestinal fluid loss.1,3
Complications & Prognosis
Complications
- Hydronephrosis.
- Acute obstructive kidney injury.
- Persistent obstruction causing loss of renal function.
- Pyelonephritis.
- Pyonephrosis.
- Bacteraemia and urosepsis.
- Recurrent urinary tract infection.
- Recurrent renal colic and haematuria.
- Chronic kidney disease in patients with recurrent obstruction, infection or complex bilateral disease.
- Rapid enlargement of infection stones.
- Recurrent stone formation.
- Procedure-related bleeding or infection.
- Ureteric injury or stricture.
- Residual stone fragments.
- Need for repeat intervention.
Prognosis
Many small ureteric stones pass spontaneously, although the likelihood of passage decreases as stone size increases and varies with stone location. Symptoms may resolve before the stone has passed, so follow-up imaging is required when stone passage has not been confirmed or obstruction remains a concern.1
Recurrence is common. Long-term management is improved by stone analysis, identification of metabolic abnormalities and sustained preventive measures.
Patients with infection stones, cystinuria, primary hyperoxaluria, a solitary kidney, recurrent bilateral stones or impaired renal function require closer specialist follow-up.
References
- European Association of Urology. EAU Guidelines on Urolithiasis [Internet]. Arnhem: EAU Guidelines Office; 2026. Available from: https://uroweb.org/guidelines/urolithiasis
- National Institute for Health and Care Excellence. Renal and ureteric stones: assessment and management. NICE guideline NG118 [Internet]. London: NICE; 2019. Available from: https://www.nice.org.uk/guidance/ng118
- Caring for Australasians with Renal Impairment. Nutrition therapy for the prevention of kidney stones [Internet]. Sydney: CARI Guidelines; 2026. Available from: https://www.cariguidelines.org/
- Dawson CH, Tomson CRV. Kidney stone disease: pathophysiology, investigation and medical treatment. Clin Med (Lond). 2012;12(5):467–471.
- Fontenelle LF, Sarti TD. Kidney stones: treatment and prevention. Am Fam Physician. 2019;99(8):490–496.






Members only discussions coming soon…