

Gastroenteritis (Infectious Diarrhoea)

Overview
Infectious gastroenteritis is an intestinal illness caused by viruses, bacteria or parasites, typically producing acute diarrhoea with variable vomiting, abdominal cramps and fever. Transmission is usually faecal–oral through contaminated food or water, close contact, or contaminated surfaces. It affects all ages; infants, older adults, malnourished people and immunocompromised patients are especially vulnerable to dehydration and severe infection. Most uncomplicated episodes resolve with rehydration and continued nutrition, but shock, sepsis and pathogen-specific complications require urgent recognition. Viral causes predominate in many community settings, whereas bacterial and protozoal causes become more important with travel and particular exposures. [1–4]
Definition
Diarrhoea: passage of at least three loose/liquid stools in 24 hours, or more frequent loose stools than normal for the individual; stool consistency matters, especially in breastfed infants.
Gastroenteritis: an intestinal syndrome, commonly infectious, with diarrhoea and/or vomiting; neither fever nor vomiting is obligatory.
Dysentery: diarrhoea with visible blood, often accompanied by cramps or tenesmus.
Persistent diarrhoea: diarrhoea lasting ≥14 days. Chronic diarrhoea generally refers to symptoms lasting ≥4 weeks.
STEC: Shiga toxin-producing Escherichia coli; may cause bloody diarrhoea and haemolytic uraemic syndrome (HUS).
Anatomy & Physiology
- The small intestine absorbs most ingested water and nutrients; the colon reclaims residual water and electrolytes.
- Epithelial transport, intact villi and the mucosal barrier normally limit net fluid loss.
- Sodium–glucose cotransport remains functional in most infectious diarrhoea, allowing oral rehydration solution (ORS) to promote sodium and water absorption despite ongoing stool losses. [1,3]
Aetiology and Risk Factors
Aetiology
| Group / pathogen | Typical features and exposures |
|---|---|
| Viruses: norovirus, rotavirus, enteric adenovirus, astrovirus, sapovirus | Usually watery diarrhoea; vomiting may be prominent. Norovirus causes outbreaks across ages. Rotavirus is important in young children, with severe disease reduced by vaccination. |
| Enterotoxigenic E. coli (ETEC), Vibrio cholerae | Secretory watery diarrhoea; contaminated food/water and travel. Cholera can cause exceptionally large fluid losses. |
| Campylobacter, Shigella, non-typhoidal Salmonella | Inflammatory diarrhoea, sometimes bloody, with fever and cramps; foodborne or person-to-person exposure. Salmonella can also cause invasive disease. |
| STEC | Severe cramps and watery-to-bloody diarrhoea; fever may be absent. Exposures include undercooked meat, contaminated produce and animal contact. |
| Clostridioides difficile | Toxin-mediated colitis, often after antibiotics or healthcare exposure, but community cases occur. |
| Giardia duodenalis | Persistent non-bloody diarrhoea, bloating and greasy stools/malabsorption; untreated water, travel and childcare exposure. |
| Cryptosporidium, Cyclospora; Entamoeba histolytica | Cryptosporidium/Cyclospora commonly cause watery or prolonged diarrhoea. E. histolytica can cause dysentery. |
| Foodborne toxin illness: Staphylococcus aureus, Bacillus cereus, Clostridium perfringens | Vomiting and/or diarrhoea after contaminated food; some syndromes begin within hours. These are often brief toxin-mediated illnesses. [1,3,4,6,7] |
Risk Factors
- Unsafe drinking water, poor sanitation, undercooked food, unpasteurised products and inadequate food handling.
- Travel, household/childcare outbreaks, institutional living, animal exposure and faecal–oral sexual exposure.
- Recent antibiotics or healthcare contact, immunosuppression, malnutrition and extremes of age.
- Low intake, frequent vomiting, profuse stool losses and pre-existing renal/cardiac disease increase the consequences of dehydration. [1–4]
Hepatitis viruses are not usual causes of acute infectious gastroenteritis. Enterobius vermicularis typically causes nocturnal perianal itching rather than acute diarrhoea; pinworm infection should not be listed as a routine gastroenteritis cause.
Pathophysiology
| Mechanism | Effect / examples |
|---|---|
| Enterotoxin-mediated secretion | Increased intestinal electrolyte secretion produces watery diarrhoea; examples include cholera and ETEC. |
| Epithelial injury and malabsorption | Viral enterocyte injury or Giardia-associated dysfunction reduces absorption; temporary lactase deficiency may follow. |
| Mucosal invasion or inflammatory injury | Colitis produces blood/mucus, pain and tenesmus; examples include Shigella and Campylobacter. |
| Shiga toxin-mediated endothelial injury | STEC can trigger microangiopathic haemolysis, thrombocytopenia and acute kidney injury (HUS). |
| Net water/electrolyte loss | Reduced circulating volume, potassium disturbance and bicarbonate loss; severe illness may cause shock and metabolic acidosis. [1,3,9] |
Gross and Microscopic Pathology
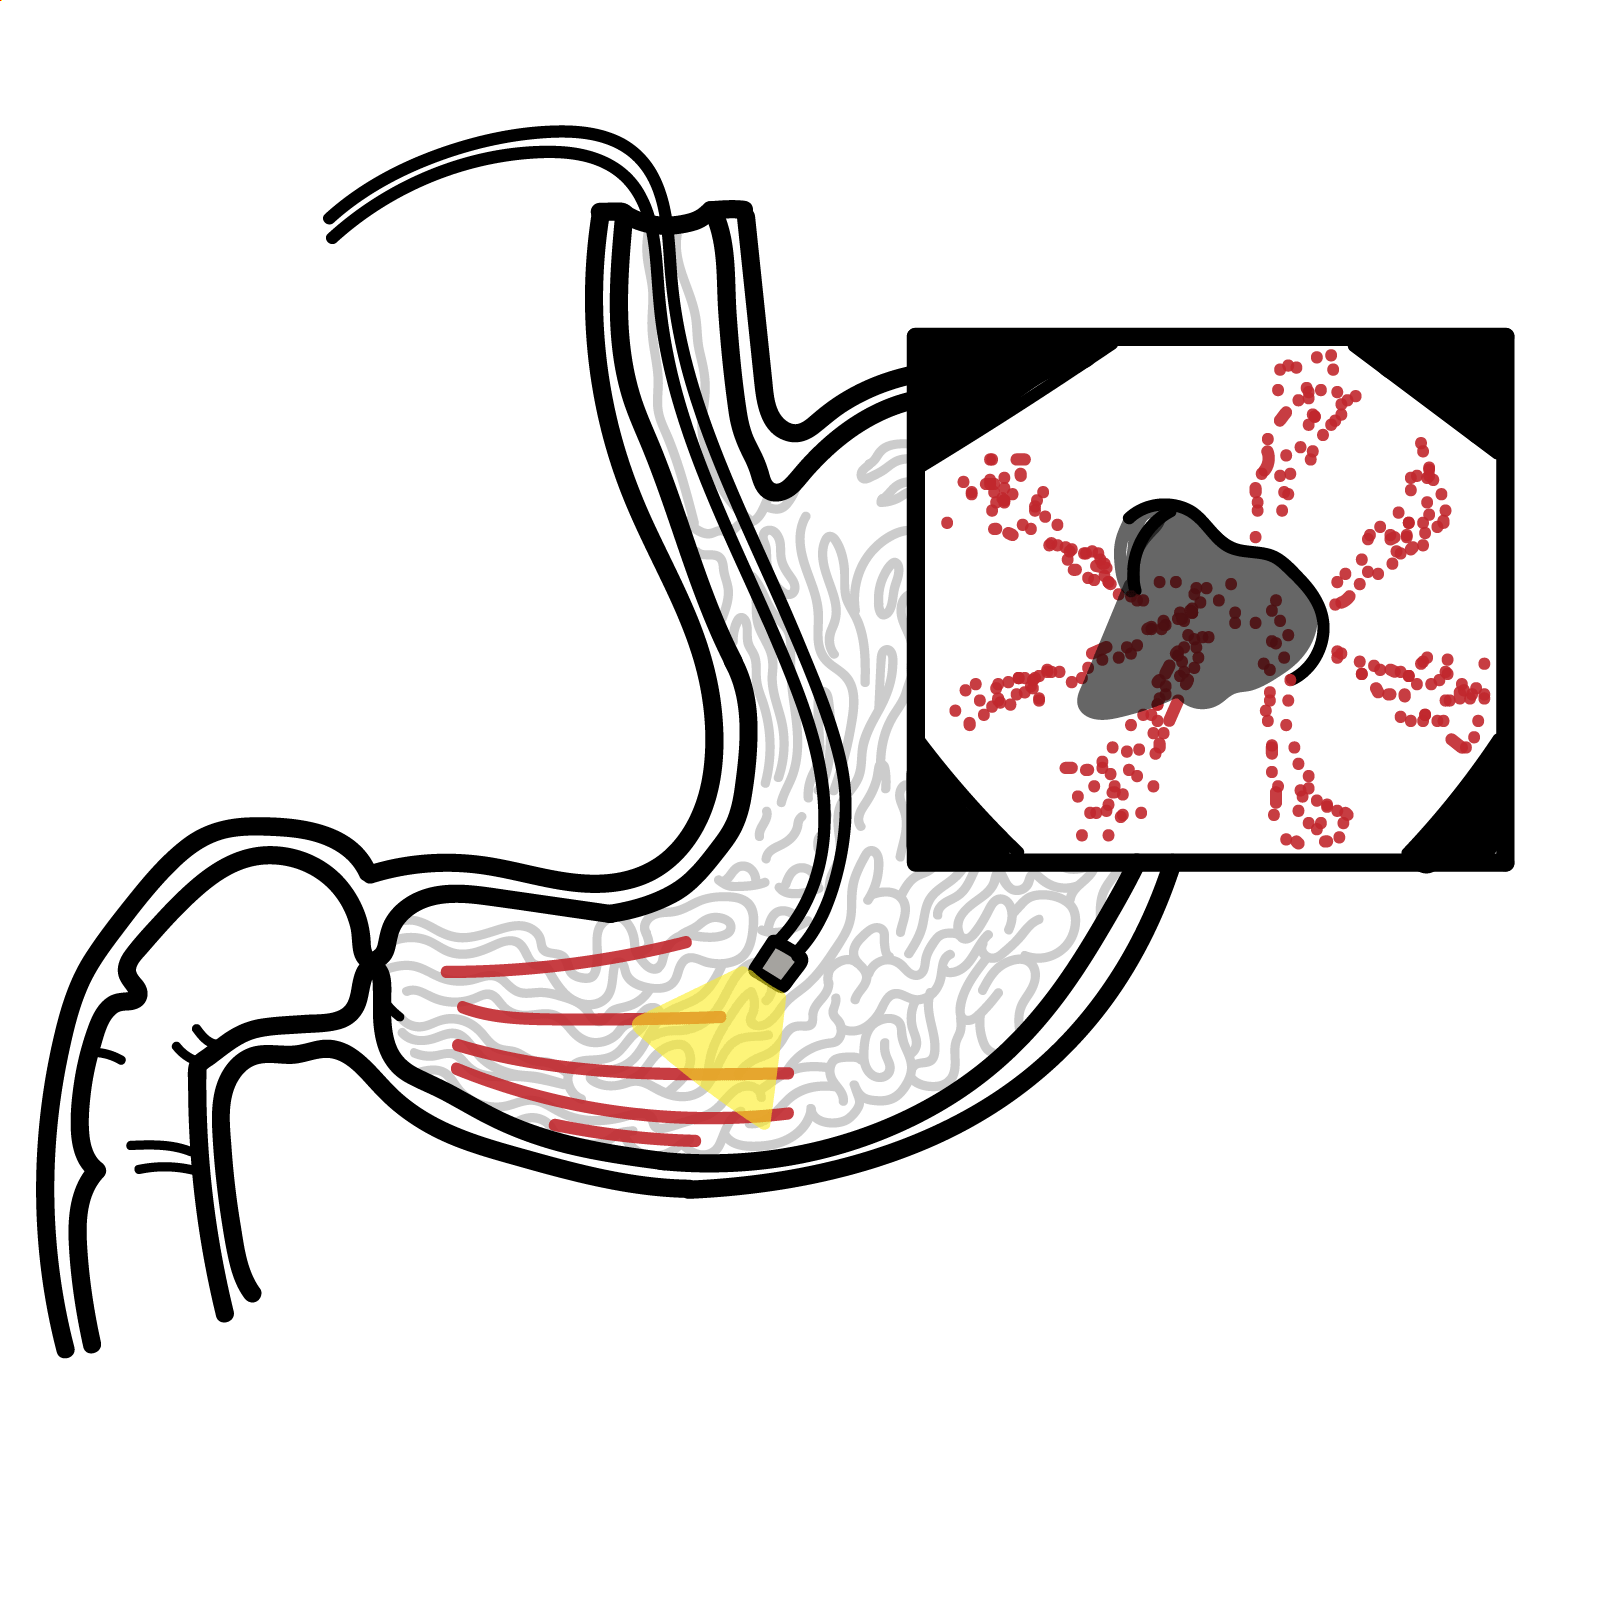
Findings vary by organism and are not usually needed for diagnosis. Enteritis can cause epithelial/villous injury; invasive colitis produces mucosal inflammation and ulceration. C. difficile may cause pseudomembranous colitis. Endoscopy or biopsy is reserved for selected atypical or persistent cases rather than routine acute gastroenteritis. [1,3,8]
Why can ORS improve hydration even while diarrhoea continues?
Clinical manifestation
Symptoms and history
- Loose/watery stools, nausea, vomiting, crampy abdominal pain and variable fever.
- Blood/mucus or tenesmus suggests inflammatory disease; profuse watery stool suggests a secretory process.
- Record onset, duration, stool/vomit frequency, oral intake, urine output, weight change and exposure history.
- Ask about travel, sick contacts, food/water, antibiotics, medications and immunocompromise. [1–4]
Examination and dehydration assessment
Assess observations, mental state, perfusion, mucous membranes, thirst, urine output and abdominal findings. In children, a recent pre-illness weight compared with current weight is the best measure of fluid deficit; otherwise use a combination of signs. These paediatric estimates are approximate and should not be inferred from one sign alone. [5]
| Severity in children | Typical pattern |
|---|---|
| Mild (<5% weight loss) | Often no objective signs; thirst or reduced urine output may occur. |
| Moderate (5–9%) | Dry mouth, sunken eyes, reduced skin recoil, irritability/lethargy and increasingly abnormal observations. |
| Severe (≥10%) / possible shock | Reduced consciousness, cold/mottled limbs, weak pulses, marked tachycardia, delayed capillary refill and possibly hypotension. Treat urgently. |
In adults, assess orthostatic symptoms, tachycardia, hypotension, oliguria and impaired perfusion, taking age and comorbidity into account. [2,3]
Bilious vomiting, severe focal pain, guarding, distension, altered consciousness or shock requires urgent reassessment for another diagnosis or complicated infection. Vomiting without diarrhoea should not automatically be labelled gastroenteritis. [4]
Diagnosis
Diagnosis is usually clinical in a short, uncomplicated illness. The first priorities are severity, hydration and exclusion of dangerous alternatives. Identifying a pathogen is useful when it changes treatment, infection control or public-health action. A positive multiplex PCR result requires clinical interpretation and may represent carriage or more than one detected organism. [1,2]
Investigations
| Investigation | When / why |
|---|---|
| No routine tests | Most otherwise well patients with brief watery diarrhoea and no red flags need neither blood tests nor stool testing. |
| Stool PCR/culture, including Shiga toxin testing when appropriate | Bloody diarrhoea, significant fever, severe pain, sepsis, immunocompromise, prolonged illness or outbreak investigation. Culture may still be needed for susceptibility testing/public-health work after a positive molecular result. |
| C. difficile testing | Clinically significant unexplained diarrhoea, especially after antibiotics/healthcare exposure. Test diarrhoeal stool; avoid indiscriminate testing of asymptomatic people or young children, where colonisation complicates interpretation. |
| Parasite antigen/PCR or microscopy | Persistent symptoms, relevant travel/water exposure or immunocompromise; specify suspected organisms because routine panels differ. |
| Electrolytes, urea/creatinine, glucose ± blood gas | Severe dehydration, altered consciousness, renal risk, major ongoing losses or IV fluid requirements. |
| FBC ± inflammatory markers; blood cultures | Suspected invasive infection/sepsis; blood cultures for suspected enteric fever or bacteraemia. Inflammatory markers do not reliably identify the stool pathogen. |
| HUS evaluation | After suspected/confirmed STEC, monitor haemoglobin, platelets, renal function and electrolytes when indicated; investigate haemolysis if HUS is suspected. |
| Imaging/endoscopy | Only when an alternative abdominal diagnosis, complication or persistent unexplained disease is suspected. [1,2,4,8,9] |
Diagnostic Criteria/Scoring Systems
There is no single mandatory diagnostic score. Clinical dehydration assessment guides management; paediatric dehydration scales can support, but cannot replace, repeated examination. Stool appearance alone does not reliably establish the organism. [1,4,5]
Differential Diagnosis
- Appendicitis, intussusception or bowel obstruction: focal pain, bilious vomiting, guarding or distension.
- Inflammatory bowel disease or ischaemic colitis: inflammatory/bloody diarrhoea, particularly with an atypical course.
- Medication-related diarrhoea, laxative use and non-infectious antibiotic-associated diarrhoea.
- Coeliac disease, lactose intolerance and other malabsorptive disorders in prolonged symptoms.
- Diabetic ketoacidosis, sepsis, urinary infection or other systemic illness, particularly when vomiting predominates.
- Functional/toddler’s diarrhoea: chronic loose stools in a well, normally growing child, after appropriate assessment. [1–4]
Classification
| Axis | Categories / relevance |
|---|---|
| Duration | Acute: <14 days; persistent: ≥14 days. Chronic diarrhoea generally lasts ≥4 weeks and warrants broader evaluation. |
| Clinical phenotype | Watery/non-inflammatory versus inflammatory or dysenteric. Overlap exists. |
| Severity | Hydration, ability to drink, perfusion, systemic illness and vulnerability determine urgency. |
| Context | Community/foodborne illness, travellers’ diarrhoea, healthcare/antibiotic-associated infection or outbreak. [1–3,6] |
Treatment
Initial management and rehydration
| Situation | Management |
|---|---|
| No significant dehydration | Maintain fluids and nutrition; use ORS to replace ongoing losses when needed. |
| Mild–moderate dehydration | Reduced-osmolarity ORS, offered in small frequent amounts. Vomiting does not automatically require IV therapy. Reassess intake, urine and hydration. |
| Unable to drink adequately, without shock | Consider supervised nasogastric ORS, especially in children, when oral treatment fails. |
| Severe dehydration, shock, ileus or failed enteral rehydration | Urgent isotonic IV crystalloid and repeated reassessment; replace remaining deficit, maintenance needs and ongoing losses. Use age/comorbidity-specific protocols. |
| Electrolyte disturbance or severe malnutrition | Specialist fluid management; avoid rapid unmonitored correction, particularly of sodium abnormalities. [1,4,5] |
Continue breastfeeding. Resume the usual age-appropriate diet during/after rehydration as tolerated; routine fasting, restrictive BRAT diets and routine lactose withdrawal are unnecessary. High-sugar drinks and water alone are poor substitutes for balanced ORS in significant dehydration. Selective temporary lactose reduction may help persistent secondary intolerance. [1,4]
Symptom relief and adjuncts
- Ondansetron may facilitate ORS in selected children older than 6 months with persistent vomiting under local protocols. Consider QT risk and electrolyte abnormalities; symptom improvement does not confirm the diagnosis. [4]
- Loperamide may be used briefly in suitable immunocompetent adults with afebrile, non-bloody watery diarrhoea after hydration. Avoid it in children, bloody/inflammatory diarrhoea, high fever, suspected STEC or C. difficile. [1,6,9]
- Probiotics are not routinely recommended; effects are strain-specific and large trials have shown no benefit for commonly used preparations. [4,10]
- WHO’s 2024 guideline suggests oral zinc 5 mg daily for up to 14 days in children up to 10 years with acute watery or persistent diarrhoea (conditional recommendation). Follow the applicable local programme; routine use is not standard in every well-nourished population. [11]
Antimicrobial treatment
Antibiotics are unnecessary for most uncomplicated watery illnesses and can cause adverse effects, antimicrobial resistance or C. difficile infection. Consider targeted treatment for invasive disease, selected severe dysentery/travellers’ diarrhoea, high-risk hosts and treatable parasites. Obtain appropriate specimens where possible, and use local resistance/susceptibility advice; do not delay sepsis treatment. [1,2,6]
| Pathogen / situation | Treatment principle |
|---|---|
| Suspected or confirmed STEC | Avoid antibiotics and antimotility drugs because of HUS risk; provide hydration and monitor for complications. |
| Shigella / severe Campylobacter | Treat selected patients; azithromycin is commonly used where appropriate, but resistance requires local advice and susceptibility testing. |
| Uncomplicated non-typhoidal Salmonella | Usually supportive care; antibiotics for invasive infection or selected vulnerable patients, including young infants/immunocompromised hosts. |
| Cholera / enteric fever | Cholera: aggressive rehydration plus antibiotics for selected severe cases. Enteric fever needs systemic antimicrobial treatment and specialist assessment. |
| C. difficile in adults | Stop unnecessary inciting antibiotics where possible. Fidaxomicin is preferred for an initial non-fulminant episode when available; oral vancomycin is an accepted alternative. Fulminant disease requires an urgent specialist regimen. |
| Giardia / E. histolytica / Cyclospora | Giardia: an appropriate agent such as tinidazole or metronidazole. Invasive amoebiasis: metronidazole/tinidazole followed by a luminal agent. Cyclospora: trimethoprim–sulfamethoxazole, when suitable. |
| Cryptosporidium | Hydration and nutritional support; optimise immune function. Selected immunocompetent patients may benefit from nitazoxanide. [1,6–9] |
Bloody diarrhoea does not automatically mean “give antibiotics”: consider STEC, arrange appropriate testing and seek advice. STEC-associated HUS may emerge as the gastrointestinal symptoms begin to improve. [1,9]
Disposition, follow-up and prevention
- Admit or obtain urgent specialist review for shock, severe dehydration, inability to maintain intake, major electrolyte/renal abnormalities, sepsis, suspected HUS, diagnostic uncertainty or high-risk patients.
- Discharge when oral intake is adequate, dehydration is corrected or mild, and follow-up/support is reliable. Return for reduced urine, lethargy, persistent vomiting, blood in stool, worsening pain or failure to improve.
- Wash hands with soap and water, use safe food/water practices and disinfect contaminated surfaces appropriately. For norovirus, hand sanitiser alone is insufficient.
- Avoid food preparation/caring for others while ill and for at least 48 hours after norovirus symptoms stop; follow local school, childcare, occupational and notification rules.
- Rotavirus vaccination reduces severe childhood disease. Selected travellers may need cholera/typhoid vaccination; these do not prevent all infectious diarrhoea. [1,4,12]
Complications and Prognosis
Complications
| Complication | Recognition / management |
|---|---|
| Dehydration, hypovolaemic shock and acute kidney injury | Prompt rehydration, perfusion/urine monitoring and renal/electrolyte assessment. |
| Electrolyte disturbance, metabolic acidosis or hypoglycaemia | Check in severe illness; correct with monitored, age-appropriate treatment. |
| HUS after STEC | Microangiopathic haemolytic anaemia, thrombocytopenia and AKI; urgent hospital/nephrology care. Pallor, bruising and oliguria are warning signs. |
| Bacteraemia/sepsis | More likely with invasive pathogens or vulnerable hosts; cultures, resuscitation and appropriate antimicrobials. |
| Toxic megacolon / severe colitis | Distension, systemic toxicity and worsening pain; urgent multidisciplinary management. |
| Post-infectious symptoms | Transient lactose intolerance, post-infectious IBS or reactive arthritis; reassess persistent illness rather than repeating empiric antibiotics. |
| Guillain–Barré syndrome after Campylobacter | New progressive weakness requires urgent neurological assessment. [1–3,7,9] |
Prognosis
Most uncomplicated viral and bacterial episodes resolve over several days; some symptoms last longer and protozoal infection may persist without treatment. Timely rehydration usually produces a good short-term outcome. Mortality risk is concentrated in severe dehydration, invasive infection and vulnerable populations; one overall mortality figure would not represent these different settings. Long-term sequelae include post-infectious IBS and, after HUS, renal impairment requiring follow-up. Persistent diarrhoea merits reassessment for ongoing infection, malabsorption or a non-infectious diagnosis. [1–3,7,9]
References
1. Shane AL, Mody RK, Crump JA, Tarr PI, Steiner TS, Kotloff K, et al. 2017 Infectious Diseases Society of America clinical practice guidelines for the diagnosis and management of infectious diarrhea. Clin Infect Dis. 2017;65(12):e45–e80. doi:10.1093/cid/cix669.
2. Riddle MS, DuPont HL, Connor BA. ACG clinical guideline: diagnosis, treatment, and prevention of acute diarrheal infections in adults. Am J Gastroenterol. 2016;111(5):602–622. doi:10.1038/ajg.2016.126.
3. DuPont HL. Acute infectious diarrhea in immunocompetent adults. N Engl J Med. 2014;370(16):1532–1540. doi:10.1056/NEJMra1301069.
4. Royal Children’s Hospital Melbourne. Clinical practice guidelines: gastroenteritis [Internet]. Melbourne: RCH; 2025 Aug [cited 2026 Oct 6]. Available from: https://www.rch.org.au/clinicalguide/guideline_index/Gastroenteritis/
5. Royal Children’s Hospital Melbourne. Clinical practice guidelines: dehydration [Internet]. Melbourne: RCH; [cited 2026 Oct 6]. Available from: https://www.rch.org.au/clinicalguide/guideline_index/dehydration/
6. Connor BA, Leung DT. Travelers’ diarrhea. In: CDC Yellow Book 2026: health information for international travel [Internet]. Atlanta: Centers for Disease Control and Prevention; 2026 Mar 24 [cited 2026 Oct 6]. Available from: CDC Yellow Book: Travelers’ Diarrhea
7. Connor BA, Leung DT. Post-travel diarrhea. In: CDC Yellow Book 2026: health information for international travel [Internet]. Atlanta: Centers for Disease Control and Prevention; 2025 Apr 23 [cited 2026 Oct 6]. Available from: CDC Yellow Book: Post-Travel Diarrhea
8. Johnson S, Lavergne V, Skinner AM, Gonzales-Luna AJ, Garey KW, Kelly CP, et al. Clinical practice guideline by the Infectious Diseases Society of America (IDSA) and Society for Healthcare Epidemiology of America (SHEA): 2021 focused update guidelines on management of Clostridioides difficile infection in adults. Clin Infect Dis. 2021;73(5):e1029–e1044. doi:10.1093/cid/ciab549.
9. Centers for Disease Control and Prevention. Information for clinicians: E. coli infection [Internet]. Atlanta: CDC; [cited 2026 Oct 6]. Available from: https://www.cdc.gov/ecoli/hcp/guidance/index.html
10. Schnadower D, Tarr PI, Casper TC, Gorelick MH, Dean JM, O’Connell KJ, et al. Lactobacillus rhamnosus GG versus placebo for acute gastroenteritis in children. N Engl J Med. 2018;379(21):2002–2014. doi:10.1056/NEJMoa1802598.
11. World Health Organization. Guideline on management of pneumonia and diarrhoea in children up to 10 years of age. Geneva: WHO; 2024. Available from: https://www.who.int/publications/i/item/9789240103412
12. Centers for Disease Control and Prevention. How to prevent norovirus [Internet]. Atlanta: CDC; [cited 2026 Oct 6]. Available from: https://www.cdc.gov/norovirus/prevention/index.html




Members only discussions coming soon…