

Atypical Pneumonia

Overview
Atypical pneumonia is a clinical term traditionally used for pneumonia caused by organisms that do not have a cell wall, live intracellularly, or are not detected on routine bacterial culture. Important causes include Mycoplasma pneumoniae, Chlamydia pneumoniae, Legionella species, Chlamydia psittaci and Coxiella burnetii. Respiratory viruses can produce a similar syndrome.
The term does not describe a reliably distinct clinical or radiological pattern. Fever, cough, focal chest signs, lobar consolidation and elevated inflammatory markers may occur with either “typical” or “atypical” pathogens. Initial treatment is therefore usually guided by pneumonia severity, epidemiological clues, comorbidities and local antimicrobial recommendations rather than by symptoms alone.
Definition
- Atypical pneumonia
- Pneumonia caused by organisms not reliably treated by beta-lactam antibiotics and often requiring molecular, antigen or serological methods for microbiological confirmation.
- Legionnaires’ disease
- Pneumonia caused by Legionella species. This is distinct from Pontiac fever, a self-limited, non-pneumonic illness that does not require antibiotics.
“Atypical” refers primarily to the organism and its microbiology—not to a guaranteed pattern of mild disease, dry cough or diffuse infiltrates. Legionella can cause rapidly progressive, severe pneumonia.
Aetiology & Risk Factors
Common and clinically important causes
| Pathogen | Typical epidemiological clues | Important clinical points |
|---|---|---|
| Mycoplasma pneumoniae | School-aged children, adolescents and young adults; households, schools, military or other close-contact settings | Gradual onset; persistent cough; extrapulmonary manifestations may occur |
| Chlamydia pneumoniae | Person-to-person transmission; outbreaks in close-contact settings | Often mild, but may be clinically indistinguishable from other CAP |
| Legionella species | Exposure to aerosolised water from plumbing systems, showers, cooling towers, spas or healthcare facilities; recent travel | Can cause severe CAP, gastrointestinal symptoms, confusion, hyponatraemia and extrapulmonary organ dysfunction |
| Chlamydia psittaci | Contact with birds, bird secretions, aviaries, poultry processing or veterinary exposure | Psittacosis may cause severe systemic illness; exposure history is central |
| Coxiella burnetii | Livestock, abattoirs, farms, animal birthing products or contaminated aerosols | Q fever may present with pneumonia or hepatitis; chronic infection has separate implications |
| Respiratory viruses | Seasonal circulation, sick contacts or outbreaks | Influenza, SARS-CoV-2, RSV and other viruses can mimic atypical bacterial pneumonia and may coexist with bacterial infection |
Risk factors for severe disease
- Older age, frailty or significant cardiopulmonary disease
- Immunocompromise, including systemic corticosteroids or other
immunosuppressive therapy - Smoking and chronic lung disease
- Delayed presentation or delayed effective antimicrobial therapy
- Recent travel or accommodation associated with possible
Legionella exposure - Healthcare-associated water exposure or a recognised outbreak
- Pregnancy, particularly with some zoonotic infections
Legionella is acquired from environmental water sources rather than usual person-to-person spread. A cluster linked to travel, a building or a healthcare facility has public-health implications and should prompt early notification according to local requirements.
Pathophysiology
- The pathogen reaches the lower respiratory tract through inhaled droplets, aerosols or, for some zoonoses, contaminated animal-derived aerosols.
- Organisms attach to respiratory epithelium or enter host cells. Mycoplasma lacks a cell wall, while Legionella, C. psittaci and C. burnetii have important intracellular phases.
- Innate and adaptive immune responses produce alveolar and interstitial inflammation, impairing ventilation and gas exchange.
- Severe inflammation can cause hypoxaemic respiratory failure, sepsis and acute respiratory distress syndrome.
- Systemic immune activation or dissemination can produce extrapulmonary manifestations involving the gastrointestinal tract, nervous system, liver, kidneys, heart, skin or blood cells.
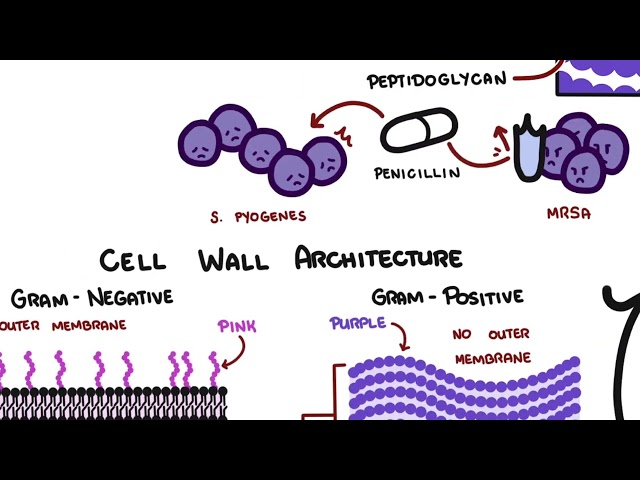
The absence of a conventional cell wall explains why beta-lactam antibiotics do not treat Mycoplasma. Intracellular pathogens require agents that achieve effective intracellular concentrations.
A patient whose pneumonia progresses despite appropriate beta-lactam therapy may have an atypical pathogen—but treatment failure should also trigger reassessment for resistant bacteria, viral infection, empyema, abscess, pulmonary embolism, aspiration, malignancy or a non-infective inflammatory process.
Clinical Manifestations
- Fever, rigors or sweats
- Cough, which may be dry initially or become productive
- Dyspnoea and reduced exercise tolerance
- Pleuritic chest pain
- Tachypnoea, tachycardia and hypoxaemia
- Crackles or bronchial breathing; chest signs may be less striking
than the radiographic abnormality
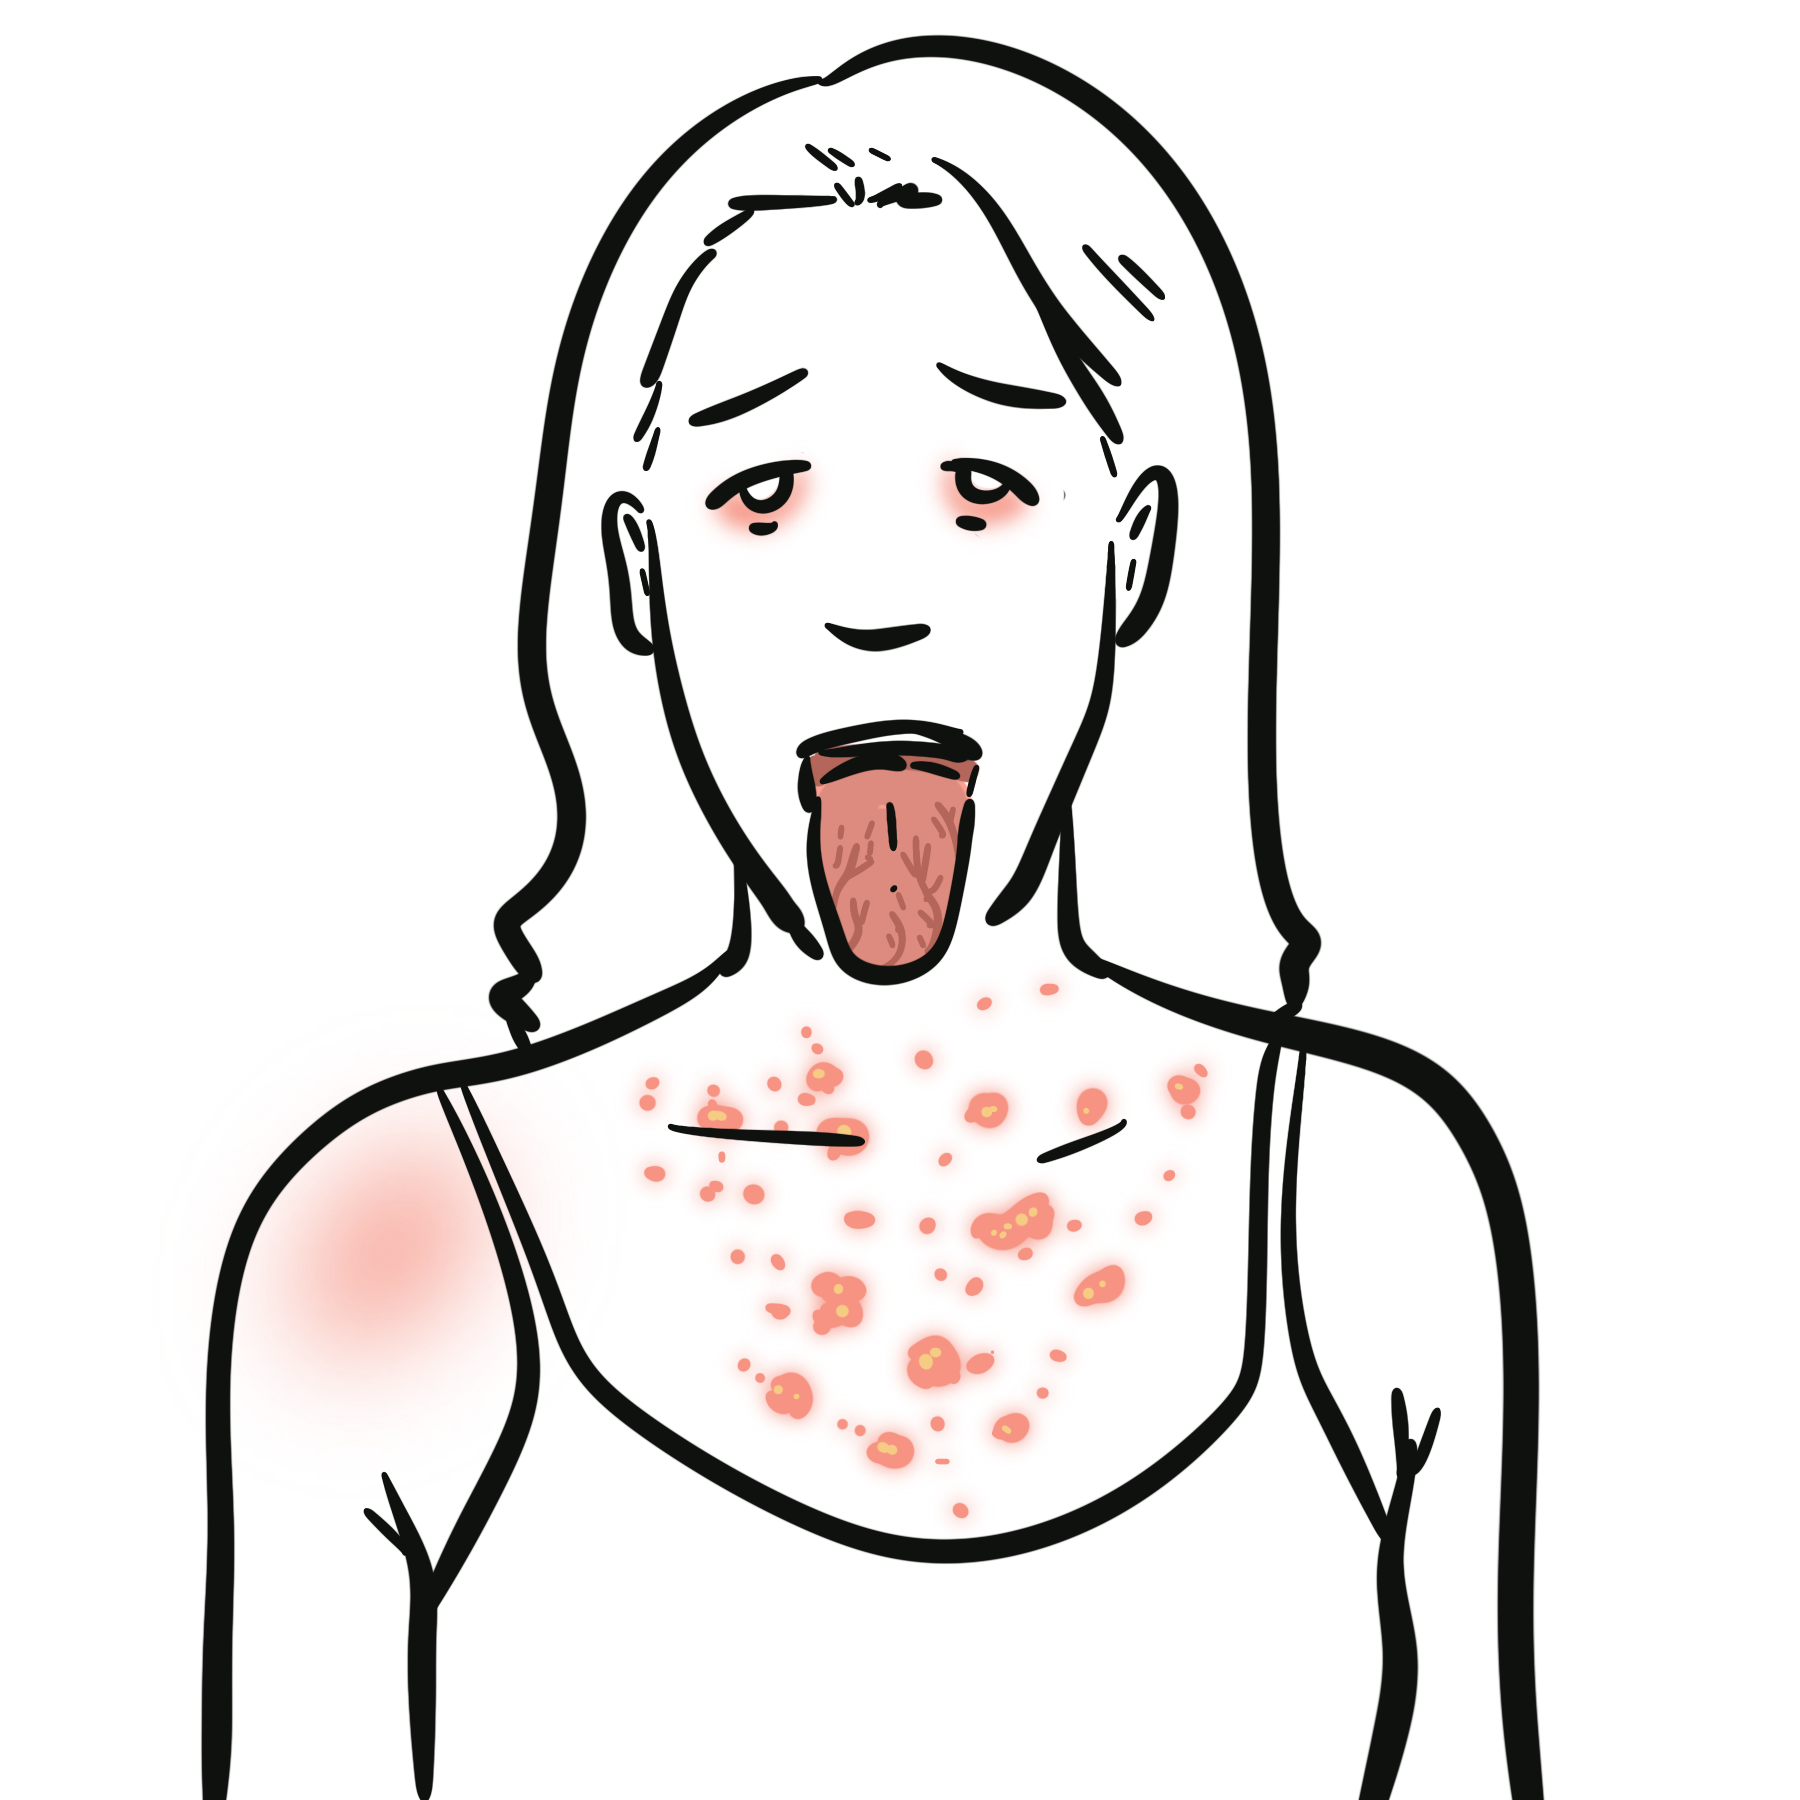
| Mycoplasma | Young adults; pharyngitis, headache, bullous myringitis; extrapulmonary manifestations |
| Legionella | High fever, relative bradycardia, diarrhea, confusion, hyponatremia, ↑LFTs; severe pneumonia |
| C. pneumoniae | Gradual illness, pharyngitis/hoarseness, persistent cough |
| Coxiella (Q fever) | Fever + atypical pneumonia ± hepatitis; exposure to farm animals/birth products |

Extrapulmonary clues can strengthen suspicion for Legionella, but microbiological testing is required when confirming the organism would alter treatment, infection-control investigation or public-health action.
Diagnosis & Investigations
The working diagnosis is pneumonia supported by compatible symptoms and new pulmonary infiltrates on imaging.
1. Confirm pneumonia and assess extent
Chest radiograph is the usual first-line imaging test for patients requiring hospital assessment or when the diagnosis is uncertain. Findings may include patchy air-space opacity, peribronchial or interstitial change, segmental or lobar consolidation and multilobar disease. The pattern does not reliably distinguish atypical from typical pathogens.

Chest CT is not routine. Consider it when:
- the chest radiograph is normal or equivocal despite strong clinical
suspicion - complications such as abscess, empyema or obstruction are
suspected - disease is severe, recurrent, non-resolving or atypical for
infection - an alternative diagnosis such as malignancy or pulmonary embolism is
being considered
2. Assess severity and physiological impact
- Pulse oximetry, respiratory rate, heart rate, blood pressure,
temperature and mental state - Full blood count, electrolytes, urea/creatinine and liver function
in patients requiring hospital assessment - C-reactive protein as a baseline inflammatory marker when it will
help assess trajectory; it does not identify the organism - Venous or arterial blood gas and lactate when there is hypoxaemia,
respiratory distress, shock or concern for ventilatory failure - A validated severity tool such as CURB-65 or the Pneumonia Severity
Index, interpreted alongside clinical judgement, oxygenation,
comorbidity and social circumstances
CURB-65 supports disposition decisions but can underestimate risk in younger patients with severe hypoxaemia or rapidly progressive disease. Never allow a low score to override abnormal physiology.
3. Use microbiological testing selectively
Routine pathogen testing is usually unnecessary in mild outpatient CAP because results rarely change immediate management.
Respiratory multiplex PCR may be useful when the result will influence antiviral therapy, antibiotic de-escalation, isolation or outbreak management. Depending on the local panel, it may detect respiratory viruses, Mycoplasma pneumoniae and Chlamydia pneumoniae. A negative panel does not exclude pathogens not included in the assay.
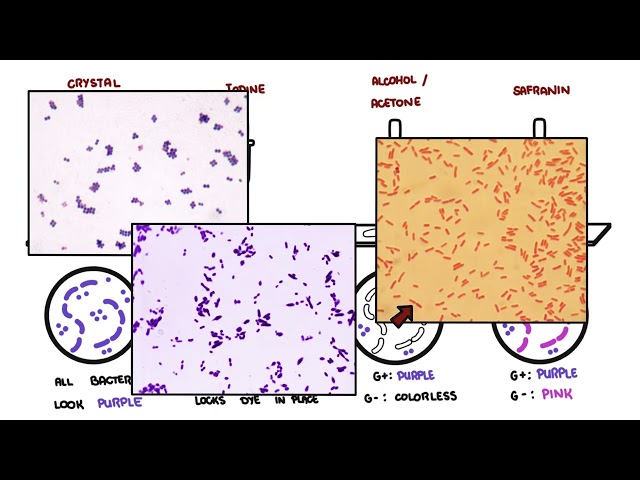
Sputum Gram stain and culture are most useful in severe CAP, intubated patients, immunocompromised patients, suspected resistant organisms, structural lung disease or treatment failure. Routine culture does not detect Mycoplasma and requires special methods for Legionella.
Blood cultures should be obtained before antibiotics when feasible in severe CAP, sepsis, suspected bacteraemia or selected patients at risk of resistant pathogens. Do not delay treatment in an unstable patient.
4. Test specifically for Legionella when indicated=
When testing is indicated, obtain both:
- Legionella urinary antigen; and
- a lower respiratory specimen for Legionella PCR and/or
specialised culture, according to local availability.
The urinary antigen primarily detects L. pneumophila serogroup 1. A negative result therefore does not exclude other serogroups or species. Respiratory culture enables broader detection and comparison with environmental isolates during outbreak investigation.
5. Reserve serology for selected zoonotic infections
Serology or specialised PCR for psittacosis or Q fever should be guided by a convincing exposure history, compatible illness and local laboratory advice. Acute and convalescent serology may be required; a single low-positive titre may not establish acute infection.
Do not order a broad “atypical pneumonia screen” indiscriminately. Choose tests that answer a specific question: Will the result alter antimicrobial choice, duration, isolation, notification, contact investigation or assessment for complications?
Treatment
General principles
- Supportive care: fluids, oxygen if required, antipyretics
- Antibiotic choice should cover atypical organisms when clinically suspected.
Antimicrobial therapy
Begin empiric therapy according to CAP severity, comorbidities, recent antimicrobial exposure, local resistance patterns and local guidelines.
Important antibiotics for atypical pneumonia
| Organism | Treatment |
|---|---|
| Mycoplasma | Macrolide (e.g. azithromycin) or doxycycline |
| Chlamydia pneumoniae | Macrolide or doxycycline |
| Legionella | Azithromycin or levofloxacin |
| Coxiella burnetii | Doxycycline |
Mycoplasma lacks a cell wall, so β-lactam antibiotics are ineffective.
Macrolide monotherapy may be unsuitable where pneumococcal macrolide resistance is substantial. Empiric treatment must cover the overall CAP differential—not merely the suspected atypical organism.
Complications & Prognosis
Mycoplasma
- Stevens–Johnson syndrome / erythema multiforme
- Hemolytic anemia
- Myocarditis/pericarditis
- Encephalitis/meningoencephalitis
- Guillain–Barré syndrome
- Otitis media
Legionella
- Respiratory failure/ARDS
- Septic shock
- Acute kidney injury
- Encephalopathy/confusion
- Multiorgan failure
- Rhabdomyolysis
Coxiella
- Chronic Q fever
- Endocarditis — particularly in patients with pre-existing valvular disease
- Hepatitis
Prognosis
- Mycoplasma and Chlamydia pneumoniae: generally good prognosis in otherwise healthy patients; recovery can be slow and cough may persist for weeks.
- Legionella: potentially severe and life-threatening, particularly in older adults and patients with comorbidities or immunosuppression.
- Coxiella: acute disease is usually self-limited, but chronic Q fever/endocarditis can occur in high-risk patients.
A persistent opacity is not automatically “slowly resolving pneumonia.” Reconsider obstruction, malignancy, organising pneumonia, tuberculosis, pulmonary infarction and an inadequately drained pleural infection.
References
- Metlay JP, Waterer GW, Long AC, et al. Diagnosis and treatment of adults with community-acquired pneumonia: an official clinical practice guideline of the American Thoracic Society and Infectious Diseases Society of America. Am J Respir Crit Care Med. 2019;200(7):e45–e67. doi:10.1164/rccm.201908-1581ST.
- Centers for Disease Control and Prevention. Clinical guidance for Legionella infections. Updated June 9, 2025. Accessed August 20, 2026. https://www.cdc.gov/legionella/hcp/clinical-guidance/index.html
- Centers for Disease Control and Prevention. Laboratory testing for Legionella. Accessed August 20, 2026. https://www.cdc.gov/legionella/php/laboratories/index.html
- Cunha BA, Burillo A, Bouza E. Legionnaires’ disease. Lancet. 2016;387(10016):376–385. doi:10.1016/S0140-6736(15)60078-2.
- Australian Government Department of Health and Aged Care. Australian Immunisation Handbook: influenza. Accessed August 20, 2026. https://immunisationhandbook.health.gov.au/contents/vaccine-preventable-diseases/influenza-flu
- Jacob M, Ramos HC, Morgado B. Legionellosis. Cureus. 2016;8(12):e937. doi:10.7759/cureus.937.
- Gonçalves RD, Carvalho R, Nunes MS, Ferreira I. Mycoplasma pneumoniae-induced rash and mucositis: how can we help? Cureus. 2025;17(5):e83794. doi:10.7759/cureus.83794.






Members only discussions coming soon…