

Acute Lymphoblastic Leukaemia
Overview
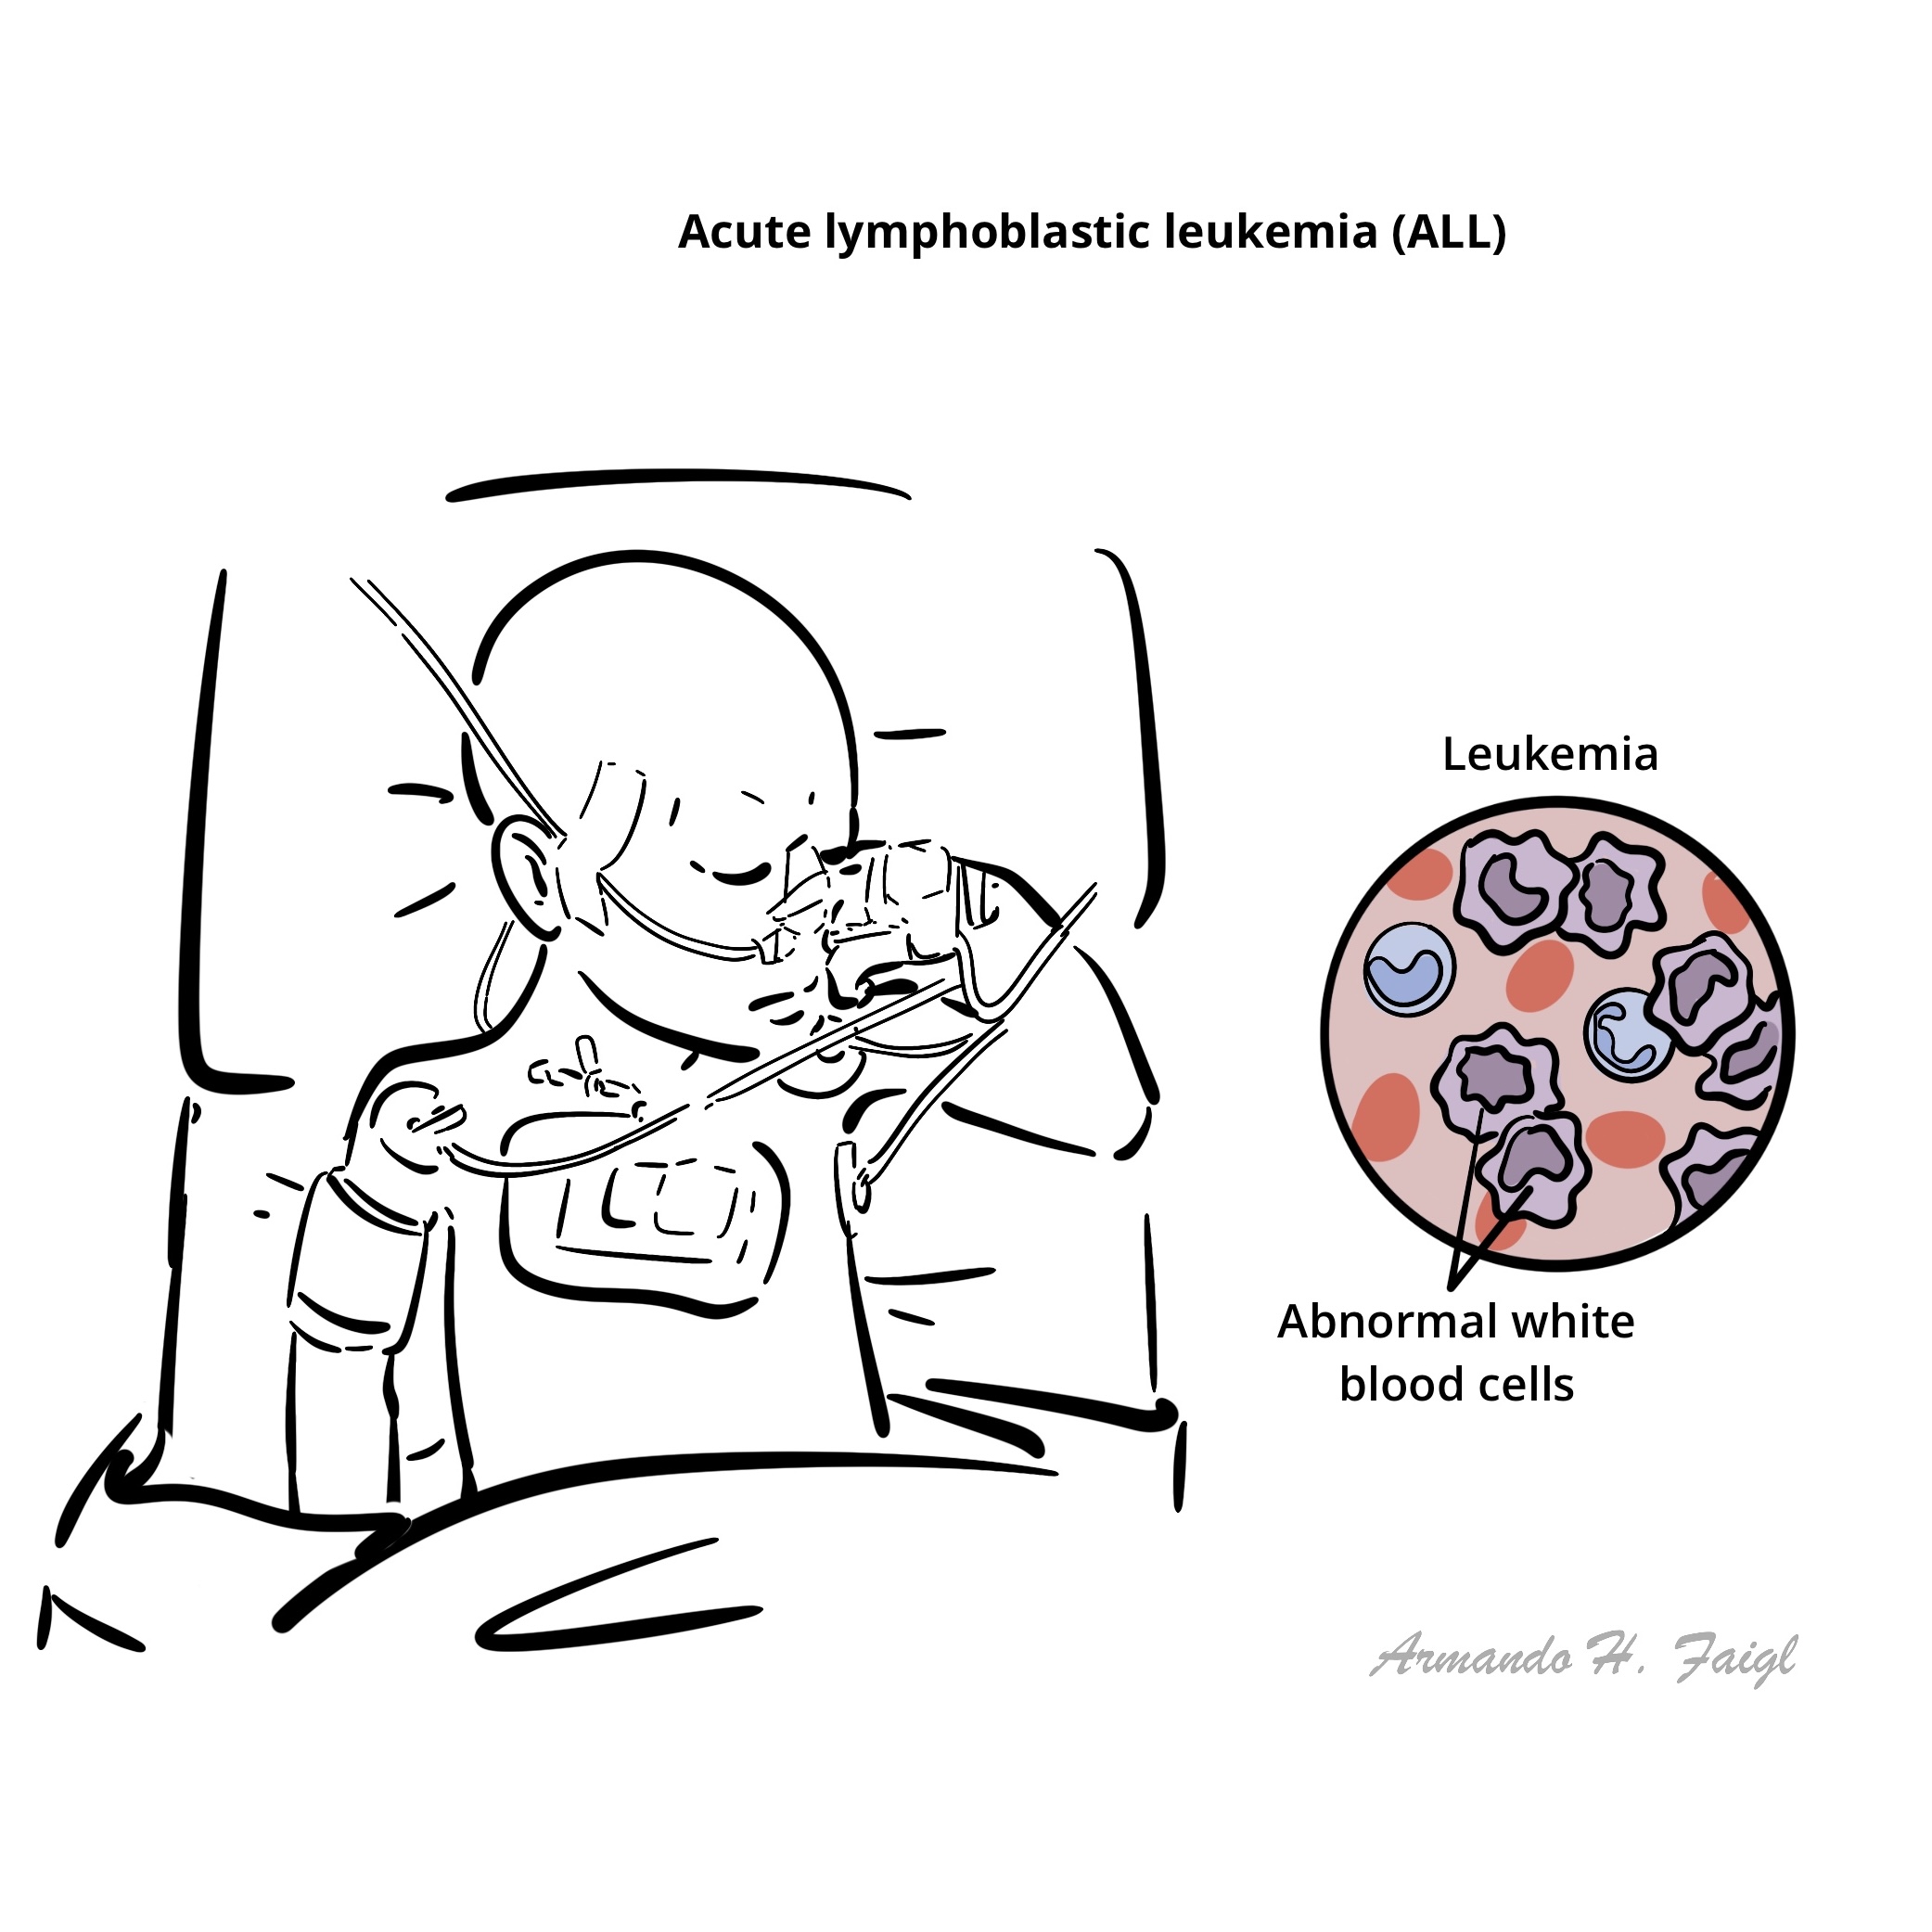
Acute lymphoblastic leukaemia (ALL) is an aggressive malignancy of immature B- or T-lymphoid precursors (lymphoblasts). Blasts accumulate in bone marrow, impair normal blood cell production and may infiltrate lymph nodes, liver, spleen, central nervous system (CNS) or testes. ALL is the most common childhood malignancy and also occurs in adults. It requires prompt diagnosis and specialist treatment; outcomes vary substantially with age, genetic subtype and treatment response.
Definition
Lymphoblast: An immature precursor cell of the B- or T-lymphoid lineage.
B-ALL and T-ALL: ALL classified by B- or T-lineage immunophenotype.
Bone marrow failure: Suppression of normal erythrocyte, neutrophil and platelet production by leukaemic blasts.
Philadelphia chromosome (BCR::ABL1): A fusion generated by t(9;22) that identifies a treatment-relevant subtype of B-ALL.
Measurable residual disease (MRD): Leukaemia detected by sensitive testing below the threshold of conventional microscopy, used to assess response and relapse risk.
What to notice
Detailed image description
Anatomy & Physiology
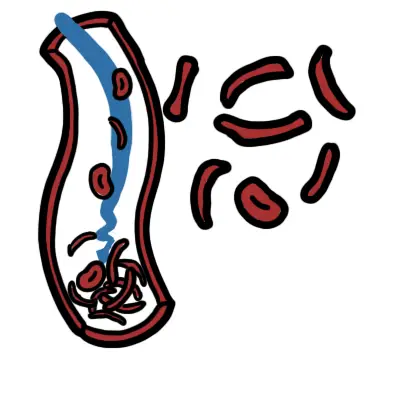
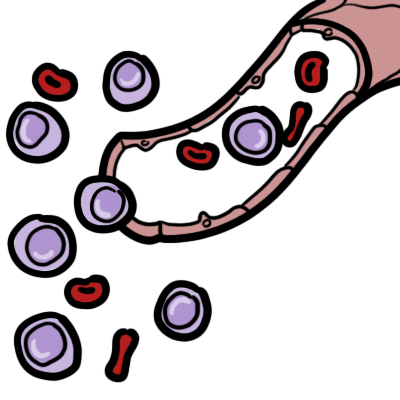
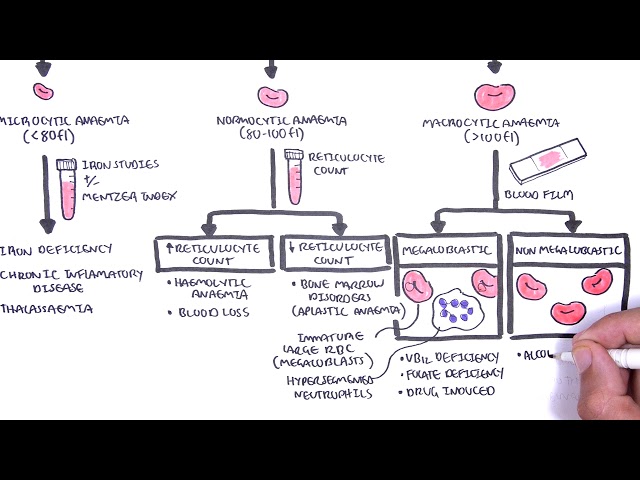
Haematopoietic stem cells in bone marrow generate myeloid and lymphoid lineages. B-cell precursors normally mature in marrow; T-cell precursors undergo further development in the thymus. Normal marrow produces erythrocytes for oxygen transport, neutrophils for infection defence and platelets for haemostasis. Excess lymphoblasts replace functional marrow, causing anaemia, neutropenia and thrombocytopenia. The CNS and testes are potential sites of leukaemic involvement that need specific consideration during treatment.
Aetiology & Risk Factors
Most cases arise sporadically after acquired genetic changes disrupt lymphoid maturation and promote proliferation. Recognised associations include inherited predisposition syndromes such as Down syndrome, certain DNA repair disorders, and prior ionising radiation or cytotoxic treatment. A specific cause is often not identifiable in an individual patient. HTLV-1 causes adult T-cell leukaemia/lymphoma, a distinct disease, and is not a usual cause of ALL.
Pathophysiology
Clonal B- or T-lymphoid precursors acquire genetic changes that block normal differentiation and permit uncontrolled survival and expansion. Replacement of the bone marrow reduces normal blood cell output, while blasts can spread to blood and extramedullary organs. Genetic lesions, including BCR::ABL1 in a subset of B-ALL, help define biologic subtype and guide targeted treatment. Persistent MRD after therapy indicates residual leukaemia even when conventional morphology shows remission.
Gross and Microscopic Pathology
Bone marrow is infiltrated by lymphoblasts, commonly with reduced normal haematopoiesis. Peripheral blood may show circulating blasts, but their absence does not exclude ALL. Blasts often have a high nuclear-to-cytoplasmic ratio and inconspicuous cytoplasm; appearance alone cannot reliably separate ALL from acute myeloid leukaemia. Flow cytometry and genetic tests establish lineage and subtype. Auer rods and myeloperoxidase expression favour myeloid differentiation rather than ALL.
Clinical Manifestation
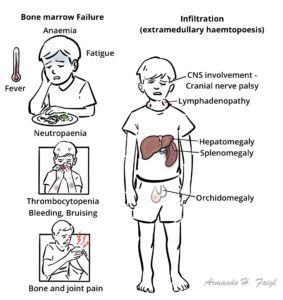
| Mechanism | Symptoms and examination findings |
|---|---|
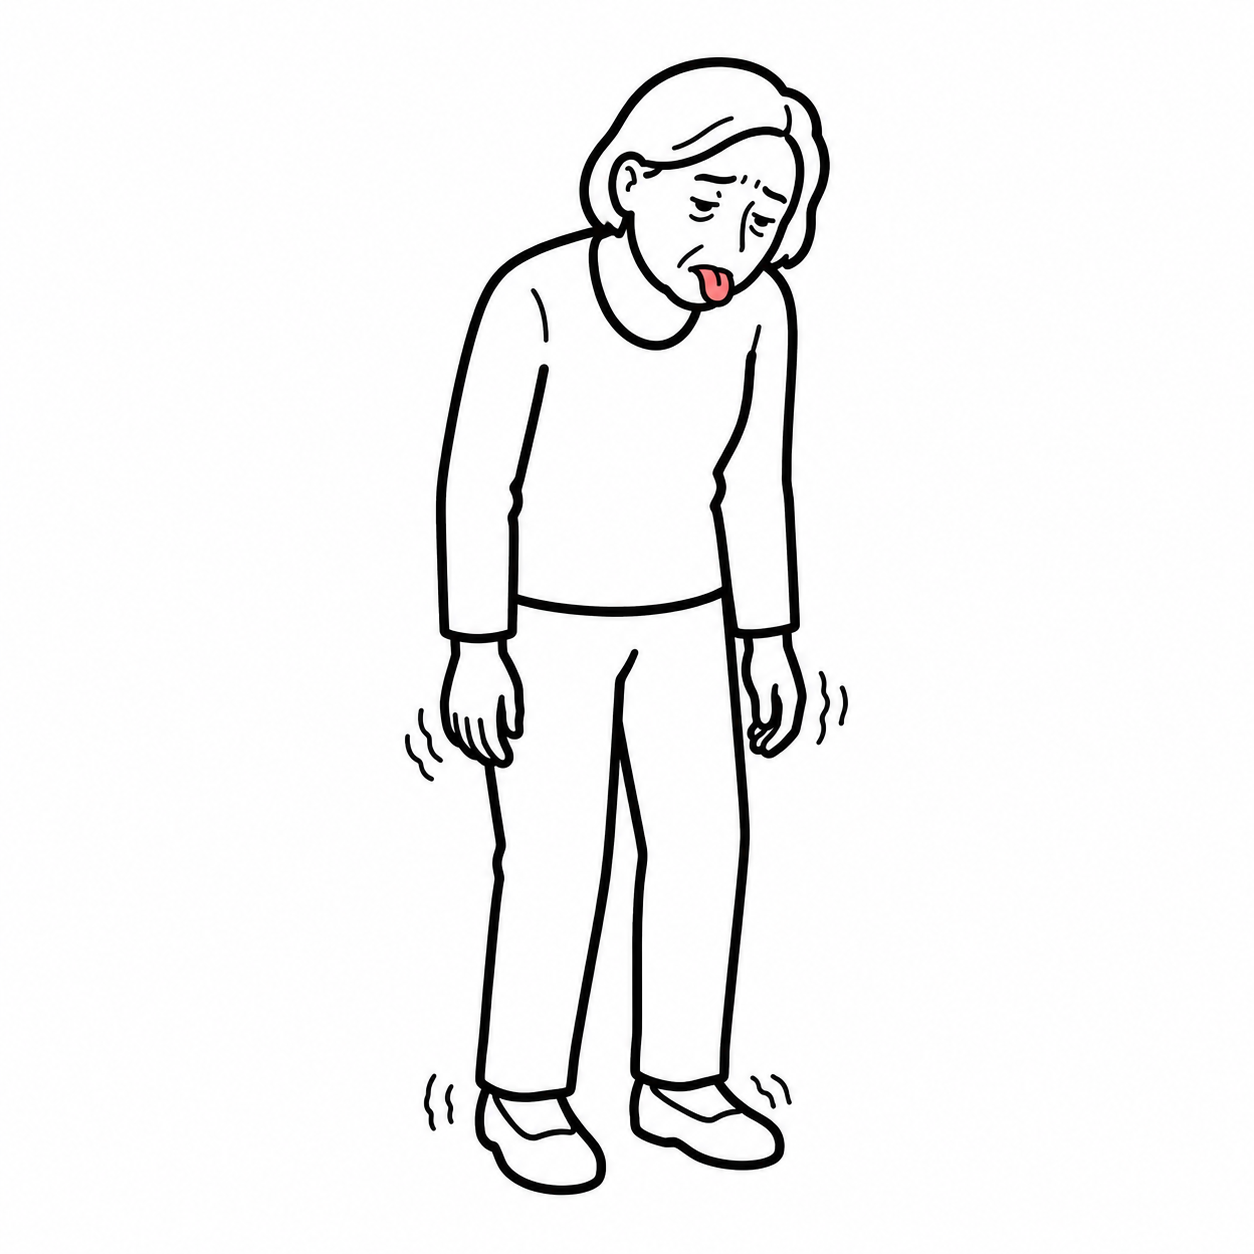
| Anaemia | Fatigue, pallor, exertional dyspnoea and reduced exercise tolerance. |
| Neutropenia or impaired immune function | Fever and infection, sometimes with few localising signs. |
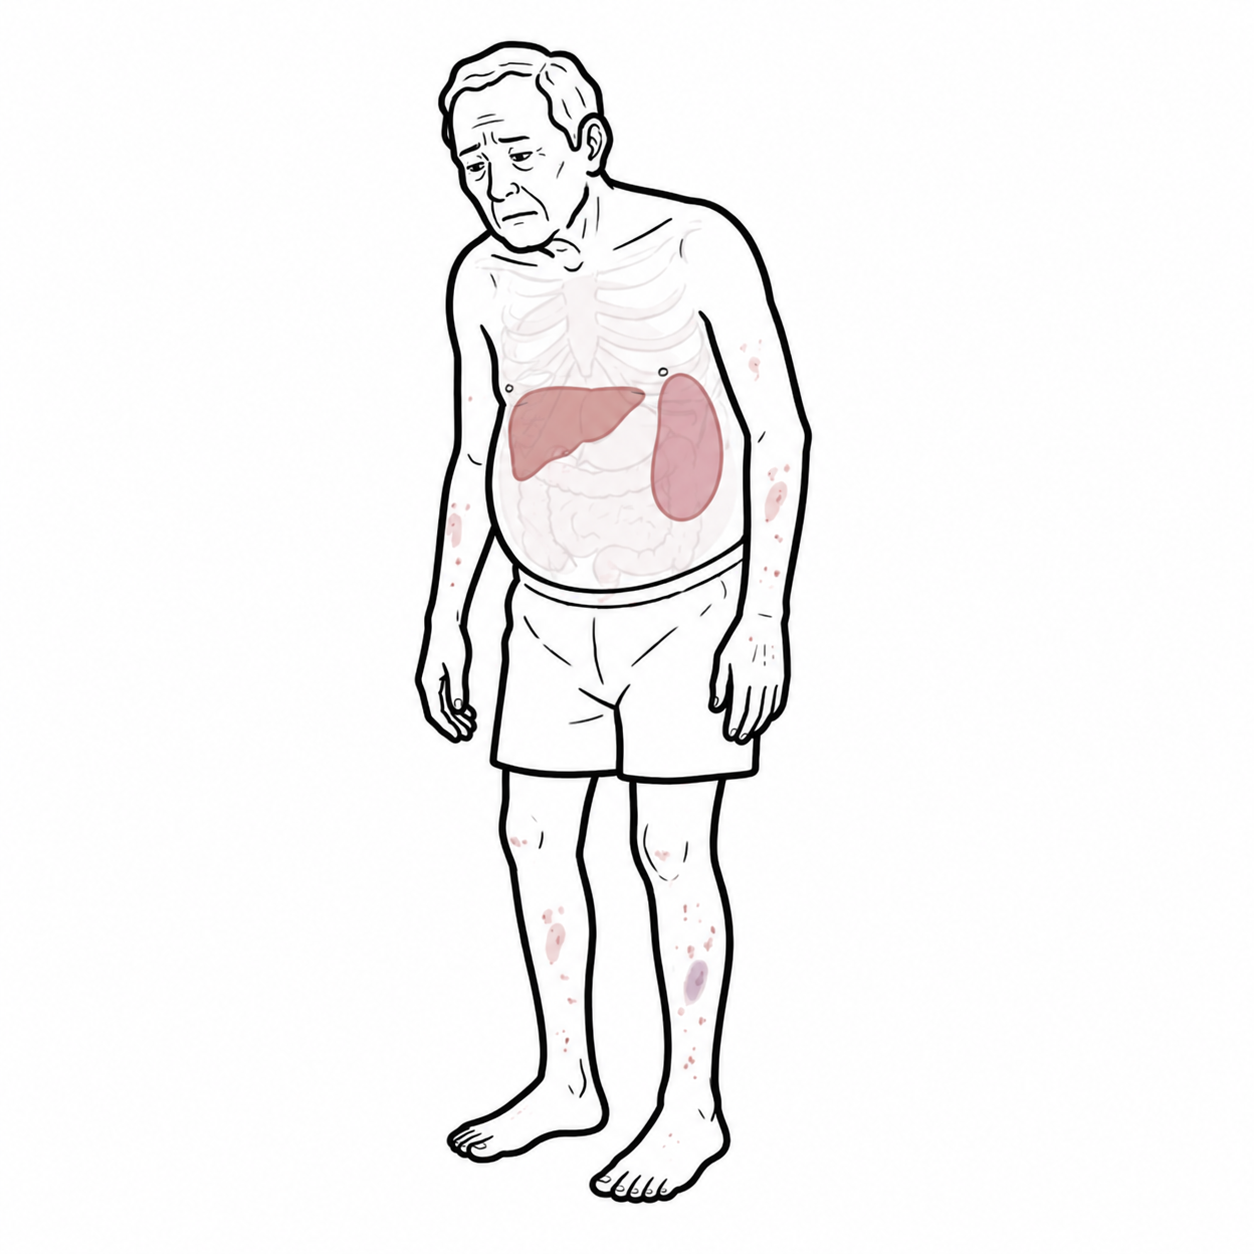
| Thrombocytopenia | Petechiae, bruising, epistaxis or other mucosal bleeding. |
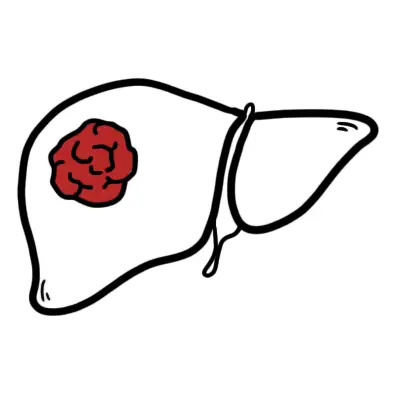
| Marrow and tissue infiltration | Bone or joint pain, lymphadenopathy, hepatomegaly or splenomegaly. |
| Extramedullary disease | Headache, vomiting, cranial nerve symptoms or testicular enlargement; a mediastinal mass may occur, especially in T-ALL. |
Fever in a patient with suspected or treated ALL, particularly with neutropenia, requires urgent assessment for infection.
Diagnosis
The diagnostic work-up requires urgent haematology assessment. Establish lineage and genetic subtype before selecting a risk-adapted treatment plan, while recognising that supportive measures may be needed immediately.
| Investigation | Purpose and possible finding |
|---|---|
| Full blood count and blood film | Anaemia and thrombocytopenia are common; white cell count may be high, normal or low, and circulating blasts may be seen. |
| Bone marrow aspirate and biopsy | Establishes marrow blast involvement and provides samples for immunophenotyping and molecular studies. |
| Flow cytometry | Confirms immature lymphoid lineage and distinguishes B-ALL from T-ALL and acute myeloid leukaemia. |
| Cytogenetics and molecular testing | Identifies defining lesions, including BCR::ABL1, and informs prognosis and targeted therapy. |
| Biochemistry, renal function, urate, phosphate and LDH | Assesses organ function, tumour burden and tumour lysis risk before treatment. |
| Lumbar puncture | Assesses CNS involvement at an appropriate point in the treatment pathway; timing depends on clinical stability and platelet count. |
| Chest imaging when indicated | Assesses suspected mediastinal mass or respiratory symptoms, especially in T-ALL. |
| MRD testing during therapy | Measures depth of response and guides subsequent risk-adapted treatment. |
Differential Diagnosis
- Acute myeloid leukaemia: distinction requires immunophenotyping and genetic studies.
- Lymphoblastic lymphoma: closely related biology but presents predominantly as tissue disease.
- Aplastic anaemia or other causes of pancytopenia.
- Infectious mononucleosis or other reactive causes of lymphadenopathy and atypical cells.
- Other marrow-infiltrating malignancies or marrow failure syndromes.
Classification
| Subtype or framework | Key point |
|---|---|
| B-lymphoblastic leukaemia | Common lineage, particularly in children; further subdivided by genetic abnormalities, including BCR::ABL1 and ETV6::RUNX1. |
| T-lymphoblastic leukaemia | T-lineage disease; may present with a mediastinal mass. |
| Genetic classification | Contemporary classifications integrate immunophenotype with cytogenetic and molecular findings; the older L1/L2/L3 morphological scheme is no longer the main clinical classification. |
| Risk stratification | Uses age, presenting white cell count, lineage, genetics, CNS involvement and early response, especially MRD. Specific protocols differ between children and adults. |
Treatment
ALL treatment is delivered by a specialist haematology or paediatric oncology team. Regimens vary by age, subtype, risk group, fitness and local protocol; CNS-directed therapy is integral rather than an optional late step.
| Phase or intervention | Purpose |
|---|---|
| Induction | Combination systemic therapy aims to achieve complete remission and restore normal marrow function. |
| Consolidation / intensification | Further therapy eradicates residual leukaemia and lowers relapse risk; intensity is adjusted to risk and response. |
| CNS-directed therapy | Intrathecal and/or CNS-penetrating systemic chemotherapy prevents or treats CNS disease. |
| Maintenance | Prolonged lower-intensity treatment for applicable subtypes and protocols, commonly over years. |
| Subtype-specific therapy | BCR::ABL1-positive ALL receives a tyrosine kinase inhibitor with the treatment regimen; immunotherapies such as blinatumomab, inotuzumab or CAR T-cell therapy may be used in selected B-ALL settings. |
| Allogeneic stem cell transplantation | Considered for selected high-risk, persistent MRD or relapsed disease according to individual circumstances. |
| Supportive care | Transfusions, infection prevention and treatment, tumour lysis prevention, and monitoring of treatment toxicity. |
Complete morphological remission generally includes fewer than 5% marrow blasts and recovery of blood counts; MRD testing can still detect leukaemia and refine relapse risk.
Complications & Prognosis
Complications
- Disease-related: severe infection, bleeding, anaemia and organ dysfunction from infiltration.
- Treatment-related: febrile neutropenia, tumour lysis syndrome, mucositis, neuropathy (for example with vincristine), steroid-associated osteonecrosis and other organ toxicities.
- Relapse may occur in marrow or extramedullary sites such as the CNS or testes.
- Long-term survivors may require monitoring for late effects of treatment, including endocrine, cardiac, fertility and secondary malignancy risks, according to their exposures.
Prognosis
Many children achieve long-term remission with modern risk-adapted therapy, while outcomes are generally less favourable in older adults. Prognosis depends on age, presenting burden, genetic subtype, CNS disease, comorbidity and, importantly, MRD response. BCR::ABL1-positive disease requires targeted therapy; its outcome should not be inferred from older untreated cohorts. Relapse or persistent MRD signals a need to reassess treatment.
References
- Hunger SP, Mullighan CG. Acute lymphoblastic leukemia in children. N Engl J Med. 2015;373(16):1541-1552. doi:10.1056/NEJMra1400972.
- Malard F, Mohty M. Acute lymphoblastic leukaemia. Lancet. 2020;395(10230):1146-1162. doi:10.1016/S0140-6736(19)33018-1.
- Alaggio R, Amador C, Anagnostopoulos I, Attygalle AD, Araujo IBO, Berti E, et al. The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Lymphoid Neoplasms. Leukemia. 2022;36(7):1720-1748. doi:10.1038/s41375-022-01620-2.
- National Cancer Institute. Childhood acute lymphoblastic leukemia treatment (PDQ®)–health professional version [Internet]. Bethesda (MD): National Cancer Institute; [cited 2026 Oct 27]. Available from: https://www.cancer.gov/types/leukemia/hp/child-all-treatment-pdq
- National Cancer Institute. Acute lymphoblastic leukemia treatment (PDQ®)–health professional version [Internet]. Bethesda (MD): National Cancer Institute; [cited 2026 Oct 27]. Available from: https://www.cancer.gov/types/leukemia/hp/adult-all-treatment-pdq





Members only discussions coming soon…